Working With What Works, Not What's Broken
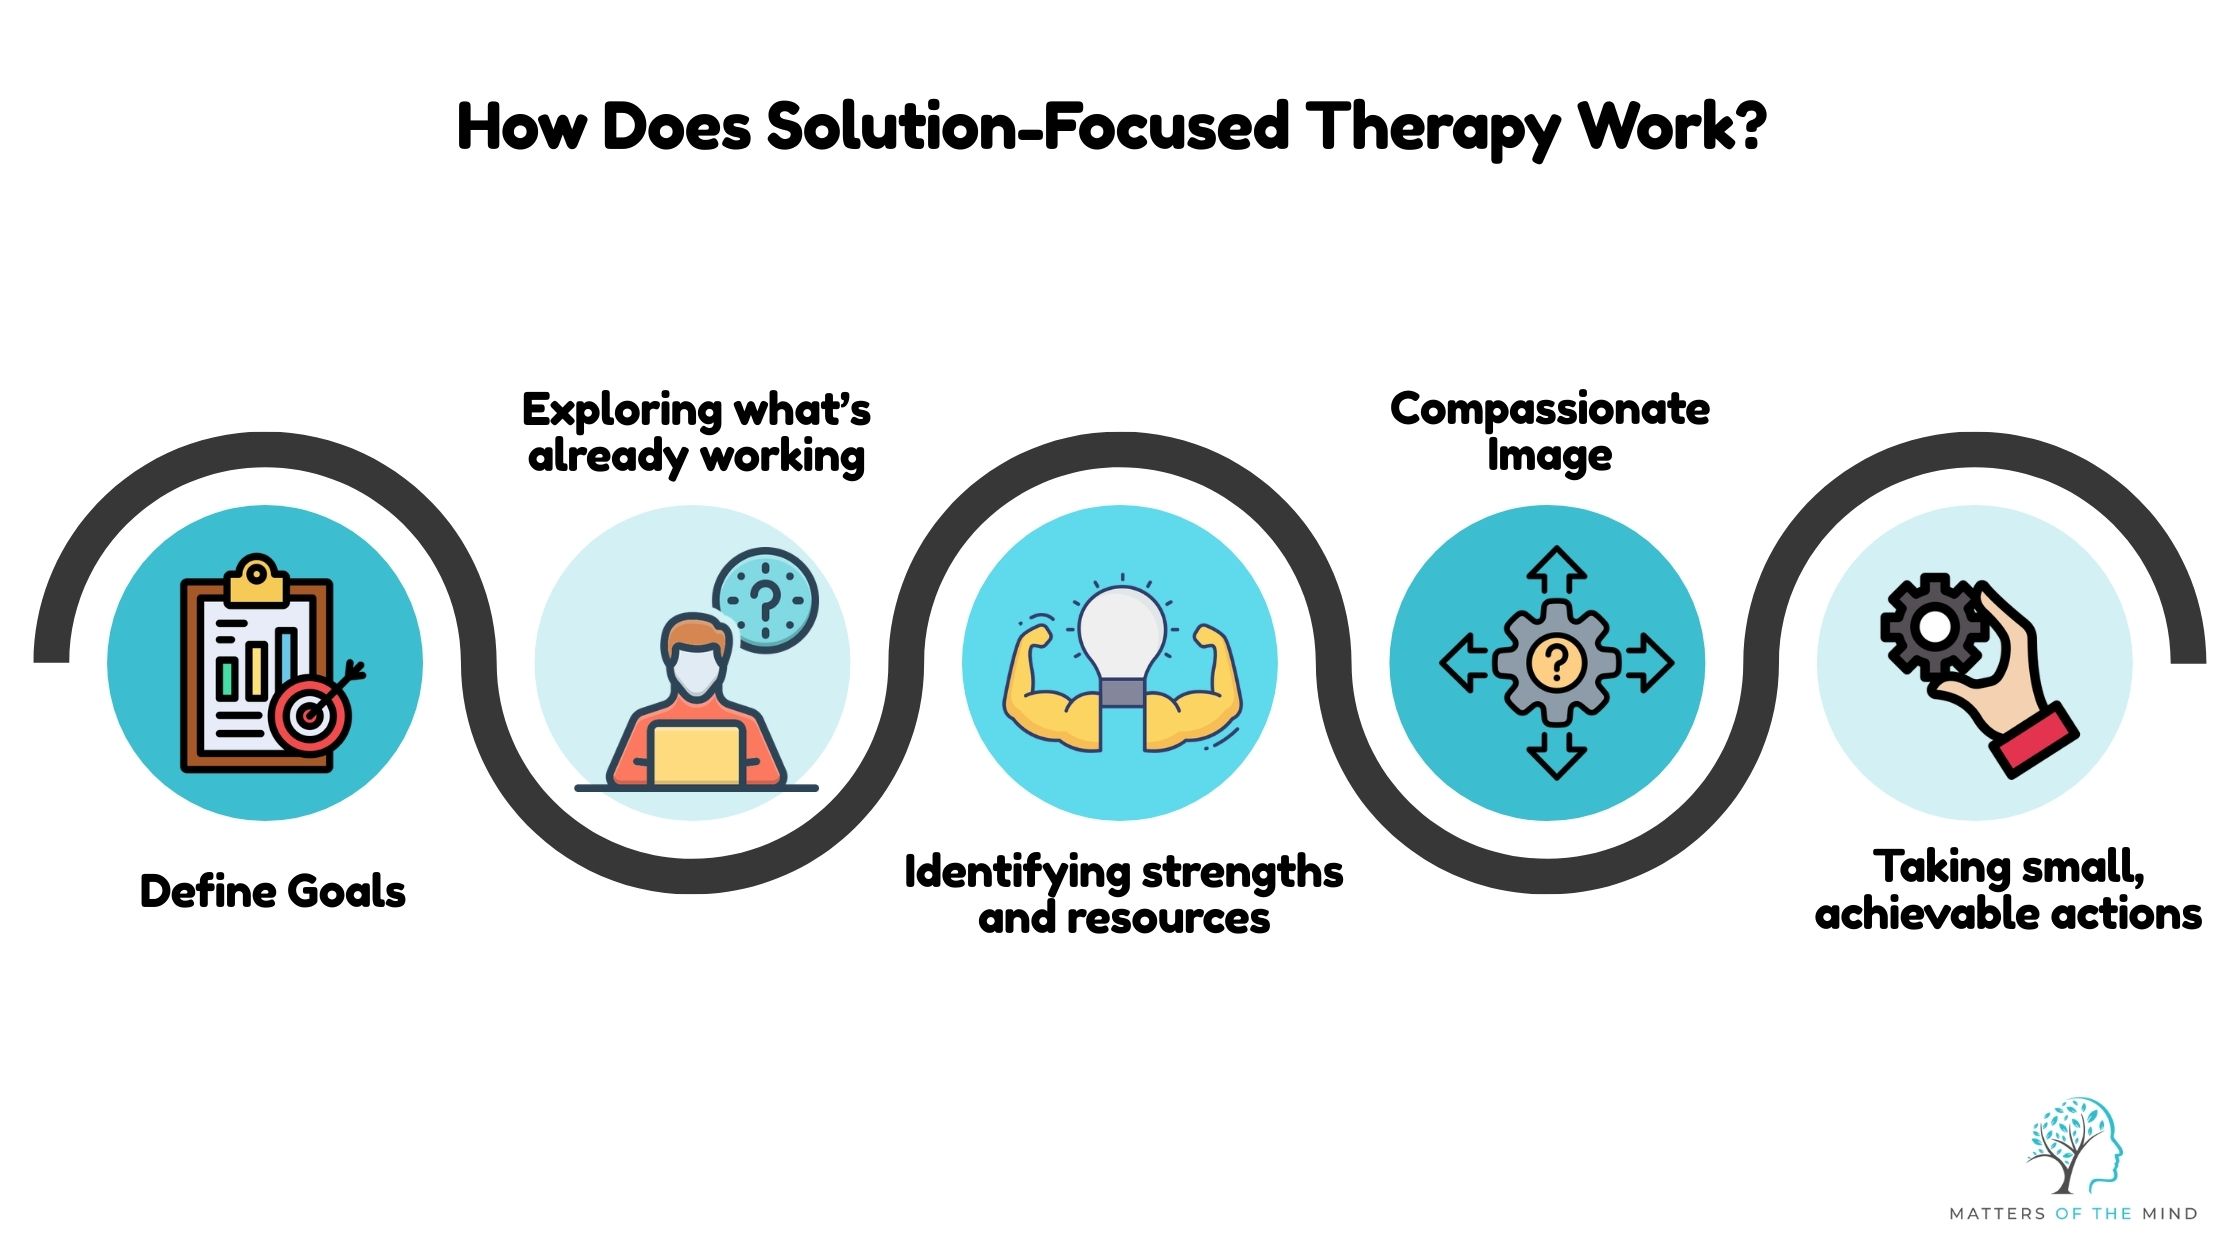
Solution Focused Theory In Social Work is one of those frameworks that sounds deceptively simple until you try to use it with a client who is genuinely angry that you are asking about solutions instead of listening to their trauma narrative for the fourth time this week. I learned this the hard way early in my career. A client came in with what looked like a textbook case for SFBT — housing instability, employment issues, family estrangement. They were cooperative, articulate, and ready to "work on goals." I jumped straight into the miracle question within five minutes of sitting down. They stared at me for a long moment and said, "Do you have any idea how insulting that is?" I had to stop, apologize, and actually hear what was underneath the resistance before I could come back to the model. That took two extra sessions I didn't think I had. The core idea is straightforward enough. Instead of spending session after session digging into the etiology of a problem, you focus on what the client wants instead of what they don't want. You look for exceptions — times when the problem wasn't present or was less intense — and you build from there. You ask scaling questions to make progress concrete. You don't pathologize. You don't spend the first three sessions just trying to establish why someone is struggling. The theory assumes that change is constant and that clients already have the resources they need, even if they can't see them yet.
How to Actually Use Solution Focused Theory In Social Work Without Making It Worse
The standard toolkit has four main techniques, and most training materials present them like they are interchangeable. They are not. You pick the right one based on where the client is in the room, not where you want them to be. The miracle question is the most famous one and the one most people mess up. The classic formulation goes something like: "Suppose tonight, while you sleep, a miracle happens and the problem that brought you here is solved. But because you're sleeping, you don't know the miracle happened. When you wake up tomorrow, what will be the first small sign that tells you something is different?" The problem is that social workers often rush through this, then move on before the client has actually imagined anything concrete. If a client responds with "I don't know" or "Nothing would change," you don't push harder. You pivot. You might say, "What would you hope for, even if it seems unlikely?" That keeps the conversation moving without turning the miracle question into an interrogation. Scaling questions are probably the most practical tool in the kit. You ask the client to rate their current situation on a scale from zero to ten. Zero is the worst it's ever been, ten is the miracle. Then you ask what would move them one point higher. This is useful because it forces specificity. You learn exactly what tiny shift matters to the client, and it gives you something measurable to track between sessions. I use this in almost every intake now. It takes about ninety seconds and usually reveals more than twenty minutes of open-ended questioning would.
Exception finding is where the real work happens. You're looking for moments when the problem didn't show up or was manageable. With depression, that might be a morning last week when they got out of bed without needing three hours of negotiation with themselves. With relationship conflict, it might be a dinner where nobody raised their voice. The trick is that clients rarely volunteer these on their own. You have to ask pointedly: "Tell me about a time recently when things were a little less bad than usual. What was different that day?" The answer almost never comes on the first try. You may need to ask three or four times before something useful surfaces. Don't give up. But don't make it feel like a grilling either. Coping questions serve a different purpose. They come in handy when a client seems completely overwhelmed and hasn't identified a single strength. You ask something like, "Given everything you're dealing with, how have you managed to keep going?" This does two things. It validates the difficulty, and it surfaces resilience that the client may have dismissed as irrelevant. I find this especially important with clients from backgrounds where surviving is treated as ordinary and therefore not worth mentioning. They'll say "I just deal with it" and you need to push gently past that to get to actual strategies.
Get the Full Details

Where This Model Actually Breaks Down
There are scenarios where Solution Focused Theory In Social Work simply does not work well, and I wish more textbooks were honest about that. Acute psychosis, active substance intoxication, and imminent safety risk are the big ones. In those situations, a brief, forward-looking, solution-oriented approach reads as dismissive at best and dangerous at worst. You don't ask a client experiencing a psychotic episode what their miracle would look like. You stabilize first. You don't do scaling questions with someone who is actively high. Those aren't gray areas. Another place where this model stumbles is with clients whose problems are structurally imposed. I had a case where a single mother was facing eviction due to wage theft by her employer. The solution-focused framing kept pushing her toward personal coping strategies and small behavioral changes. Meanwhile, the actual problem was a legal and economic violation that no amount of positive thinking would fix. I stayed with the model too long before shifting gears. We ended up needing a referral to a legal aid clinic alongside the social work intervention. The lesson was that solution-focused work assumes a certain level of agency that not all clients have, and pretending otherwise just delays getting them what they actually need. There is also a cultural dimension that gets glossed over. The emphasis on individual goal-setting and positive reframing aligns well with certain cultural norms but can feel alienating or even colonial to clients from collectivist backgrounds where the problem is understood relationally, not individually. A client whose framing of "progress" involves family harmony rather than personal achievement may find your scaling questions oddly narrow. You adapt, but it takes awareness.
A Practical Workflow That Actually Fits a Real Caseload
Most people trained in SFBT imagine using it as a standalone approach for the duration of a case. In practice, that rarely works. Here is what a realistic session structure looks like when you are juggling paperwork, multiple cases, and clients who don't always show up prepared. Session one runs about forty-five minutes. You open with a brief problem statement from the client, then immediately pivot to what they want instead. "So the issue is X. What would you like to see happen by the time we finish?" You set one or two concrete goals, establish a baseline using a scaling question, and identify one exception to take into the next session. That's it. You don't need a full genogram. You don't need a diagnostic elaboration. You need a direction and a starting point. Session two picks up where the last left off. You check the scale — has it moved? Even a half-point counts. You ask about exceptions they noticed since the last meeting. You build on what worked. If nothing moved, you explore what got in the way without treating it as failure. The conversation stays short and directed. A typical session two to four lasts twenty to thirty minutes.
Termination is usually planned from the first session. You agree on how many meetings you need and what success looks like. When the client reaches their goal or demonstrates enough independence, you close out. No drawn-out fade-outs. This model is designed to be brief, and trying to stretch it into long-term therapy undermines its effectiveness. The research backing this approach is reasonably solid for specific populations. Meta-analyses show moderate effect sizes for depression and anxiety outcomes, with particularly strong results in youth and family contexts. The evidence is weaker for complex trauma and personality disorders, where the model's brevity becomes a liability rather than a strength. Know which population you are working with before you commit to this framework wholesale. If you want to go deeper, the original work by de Shazer and Berg is still worth reading, though some of it is dense. Greenberger and Padesky's work on cognitive approaches has useful overlaps. For a more practice-oriented angle, there are several workbook-style guides that walk through each technique with transcript examples. The one I keep returning to is by James Knapp, which includes actual session recordings you can follow along with. Something about hearing the techniques used in real time rather than described on paper makes a noticeable difference in how you apply them.

At the end of the day, Solution Focused Theory In Social Work is a lens, not a religion. It teaches you to notice what is working and amplify it. That is useful regardless of whether you use it as your primary model or supplement it with other approaches. The danger is treating it as a shortcut that avoids difficult conversations. It doesn't. It just frames those conversations differently, and sometimes that frame is exactly what a client needs to move forward.