
What Solution Focused Therapy Actually Looks Like in Practice
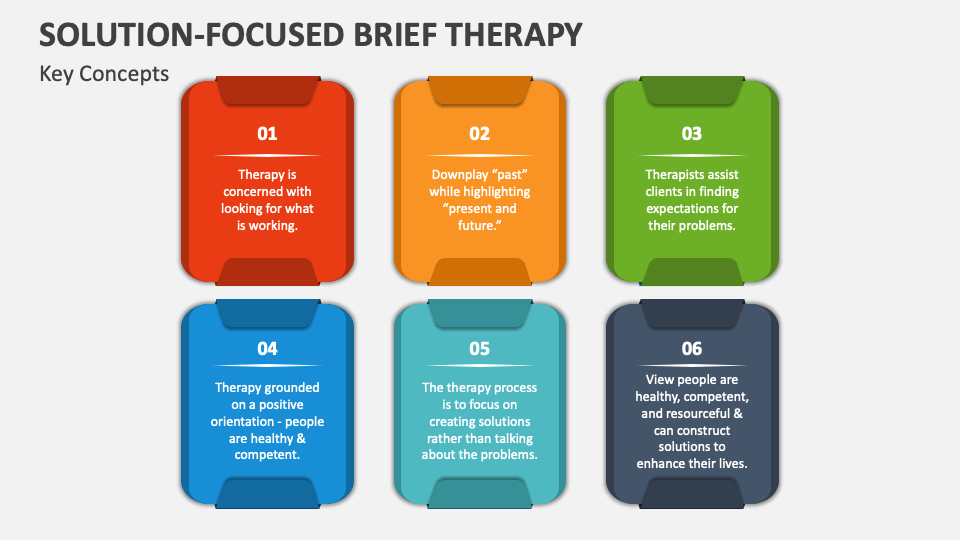
I've worked with enough clients across various mental health settings to know that theory and practice rarely align perfectly. Solution Focused Therapy Techniques exist somewhere between the textbooks and the messy reality of human behavior. When you strip away the clinical gloss, what remains is a pragmatic approach that asks people to imagine what their life would look like if their problems suddenly resolved. It sounds almost too simple until you watch it work. The fundamental premise is straightforward: instead of dissecting what went wrong, explore what works. This isn't about ignoring trauma or minimizing suffering. It's about redirecting cognitive energy toward solutions that have already worked in small increments. The therapeutic relationship becomes collaborative rather than diagnostic. Most practitioners start with what's called the miracle question. You ask someone to imagine waking up tomorrow and their problem is solved. Not how it got solved, just what would be different. This reveals priorities without triggering the defensive resistance that comes with direct questioning. I learned this the hard way early in my career when a client shut down completely during a traditional intake assessment. Switching to solution-focused framing turned the session around within twenty minutes.
Essential Techniques That Actually Work
The scaling question is probably the most versatile tool. Rate your motivation from one to ten. Where are you? What would move you one point higher? This breaks overwhelming problems into manageable steps without feeling clinical. Clients often surprise themselves with how much progress they've already made when they visualize it numerically. Coping questions serve a different purpose. Asking someone how they've survived difficult situations until now surfaces resilience that's been overlooked. A client once told me she didn't see herself as strong because she hadn't "fixed" anything. Through coping questions, she catalogued years of navigating dysfunction alone. That reframing changed everything. The exception finding technique looks for moments when the problem isn't present. Someone claiming constant depression might have exceptions like a morning when they actually got out of bed. These exceptions become building blocks for change rather than anomalies to explain away.
Advanced Nuances Beginners Miss
Here's something most training programs don't emphasize: timing matters more than technique. Pushing solution focus on someone still in acute crisis can feel dismissive. I had a client who needed twenty minutes of venting before any solution-oriented work would land. The framework doesn't eliminate empathy. It requires reading the room correctly. Another counterintuitive insight involves the relationship between structure and flexibility. Solution focused work actually requires more careful session management than insight-oriented approaches. Without the crutch of digging into the past, you need sharper questioning skills to keep momentum. Sessions can drift into problem-saturation quickly if you let them. Word choice carries unexpected weight. Saying "what do you want instead of..." rather than "what's wrong with..." isn't just semantic. Research shows the framing affects compliance rates. Clients respond differently to positive construction versus negative analysis.
Get the Full Details

Common Pitfalls and How to Avoid Them
The biggest mistake I see is using these techniques mechanically. Solution focused therapy isn't a checklist. Each session needs genuine curiosity about what the client uniquely values. When clients sense you're going through motions, engagement drops significantly. I've adjusted my own approach multiple times based on client feedback rather than rigid protocol. Another issue is overpromising results. This approach works best for clients with adequate cognitive functioning and some baseline motivation. It's less effective for severe personality disorders, active psychosis, or clients in survival mode. Being honest about limitations builds trust faster than overselling the method. There's also the risk of skipping necessary grief processing. Sometimes people need to sit with loss before they can imagine solutions. Forcing optimism prematurely can feel invalidating. The art lies in knowing when to push forward and when to pause.
Practical Application Guide
Start each session by asking what the client hopes to get out of it. This establishes collaborative goal-setting immediately. If they mention wanting relief, ask what relief would look like concretely. Vague goals like "feel better" don't guide intervention well. Use the scale question at session start and end to measure perceived progress. A single point shift represents meaningful movement that clients can track. Document these changes objectively rather than relying on subjective impressions. When clients present problems, ask about past successes briefly, then pivot to solution construction. Limit problem exploration to fifteen percent of session time maximum according to standard guidelines. The remaining time builds new behavioral patterns.
Homework assignments should be small and achievable. Asking someone to notice three exceptions to their problem this week is more effective than dramatic behavioral changes. Small wins create momentum for larger shifts.
When This Approach Fails Completely
I've watched solution focused therapy fail with clients who have severe executive function impairments. The abstract nature of "future-oriented thinking" assumes cognitive capacity some people simply don't have available. In those cases, grounding interventions in concrete skill-building produce better outcomes. Cultural considerations also matter significantly. Some populations respond better to direct advice-giving rather than Socratic questioning. The collaborative stance can read as evasive or disrespectful depending on cultural context. Adapting communication style improves engagement substantially. Financial constraints affect treatment length too. Solution focused therapy was designed for brief intervention models, but some clients need longer support regardless of methodology. Recognizing when longer-term work is necessary prevents premature termination.
Integrating With Other Approaches
Many practitioners combine solution focused techniques with cognitive behavioral methods for better outcomes. The combination addresses both thought patterns and actionable goals simultaneously. I've found that clients who learn cognitive restructuring alongside solution building maintain progress longer after discharge. Motivational interviewing pairs naturally with this framework. The change talk elicitation in MI complements the exception-finding work in solution focused therapy. Using both creates a synergistic effect that neither achieves alone. Even traditional psychodynamic therapists can benefit from occasional solution focused interventions. Brief future-focused sessions sometimes break through therapeutic impasses that endless interpretation cannot resolve. Having multiple frameworks in your toolkit makes you more effective regardless of primary orientation.
The effectiveness of Solution Focused Therapy Techniques depends entirely on implementation quality. Proper training, cultural sensitivity, and ongoing self-reflection separate competent practitioners from those who apply formulas superficially. The method works when you respect its complexity while maintaining its essential simplicity.


