Getting a Solution Focused Treatment Plan Template into your practice without it becoming bureaucratic clutter
Most therapists I know struggle with treatment plans because they either copy a generic template or build one from scratch every time they see a new client. Both approaches waste time and produce inconsistent documentation. A Solution Focused Treatment Plan Template shifts the focus away from problem analysis and toward measurable goals. That sounds simple but the execution requires understanding how brief therapy frameworks actually work in real clinic settings. The template is built around the solution-focused brief therapy (SFBT) model. It differs from traditional psychiatric treatment plans because it does not open with a problem list or symptom inventory. Instead, it starts with the client's stated goals and the small steps they can take toward them. The standard sections you will find are: presenting concern (kept brief), client-driven goals, exceptions to the problem, scaling questions, intervention strategies, and outcome measurement. I have spent years watching clinicians fill out these templates incorrectly. The most common error is writing goals as vague wishes like "improve mood" or "reduce anxiety." Those are not measurable. A proper goal in this framework reads something like "Client will identify three coping strategies and report using one per week for four weeks as measured by session self-ratings." You can see the difference immediately. One is something you can track. The other is paperwork.
How to Use This Template in Your Actual Workflow
Download a blank Solution Focused Treatment Plan Template and modify it for your specific setting before you ever use it with a client. Do not wait until you are sitting in front of a patient to build your form. I learned this the hard way during my second year of private practice when I tried to use a publicly available template with a client who had complex trauma and comorbid substance use. The template assumed a standard outpatient adult population and had no section for safety planning or coordination of care. That session ran twenty minutes over because I was constantly rewriting the document on the fly. After that, I customized every template to match my actual caseload before using it. Here is the practical workflow I recommend:
Step 1: During the initial session, spend the first ten minutes having the client describe what they want to be different. Record their exact language wherever possible. Step 2: Translate their language into two to three measurable goals. Each goal needs a baseline, a target, and a timeframe. Step 3: Identify one exception to the problem. This is a recent time when the issue was less severe or absent. Document the conditions present during that exception.
Get the Full Details

Step 4: Select a scaling question appropriate to the goal. Ask the client to rate their current position on a one-to-ten scale and identify what would move them one point higher. Step 5: Write brief intervention strategies tied directly to the exception and the next scaling step. Do not write ten interventions. Write two or three that are realistic for this client to attempt between sessions. Step 6: Set a review date, usually four to six weeks out, and specify how you will measure progress.
Solution Focused Treatment Plan Template
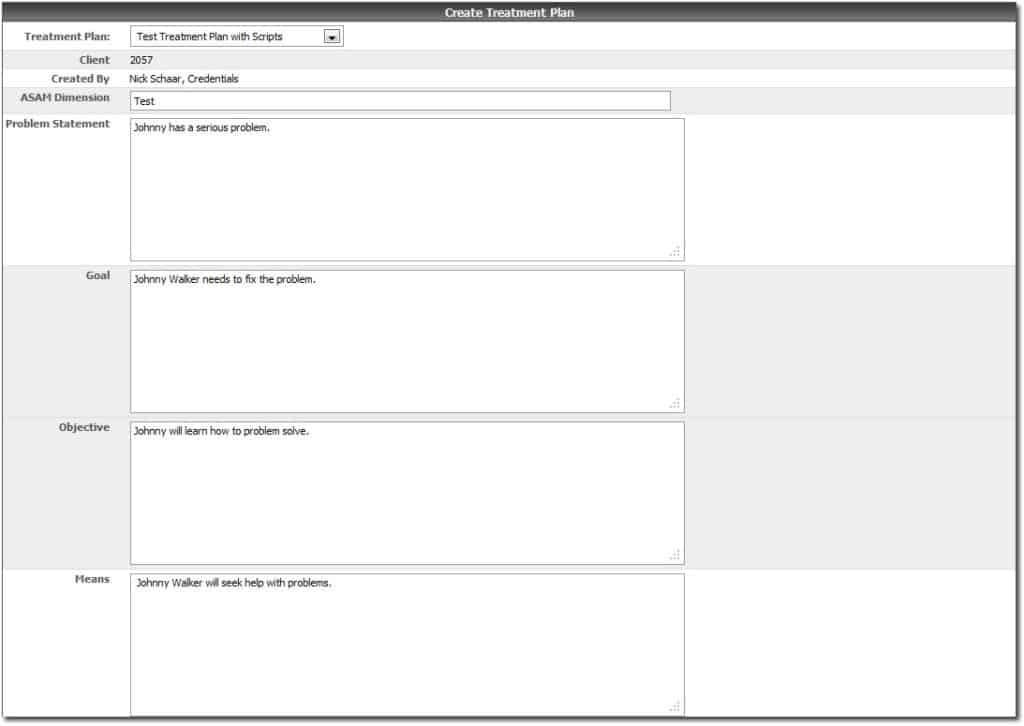
This is the section most people skip because they want to jump straight to downloading. But understanding the structure matters more than having a pre-made document. A Solution Focused Treatment Plan Template should fit on one to two pages maximum. If yours is five pages long, it is not solution focused. It is just a longer form with the same label. A functional template has these core fields: Client name and DOB: Standard identification.
Session date: Keep it simple. Presenting concern: One to three sentences from the client's own words. No diagnostic hedging here. Goal 1: Measurable outcome with baseline, target, and deadline.

Goal 2: Same format. Goal 3: Same format. Exception(s) identified: Specific situation, date, what was different.
Scaling question: The exact question you will use in session. Current scale rating: Where the client says they are right now. Interventions: Two to three brief notes linked to the scaling step.
Homework or between-session tasks: Concrete and assignable. Review date: When you will reassess. Outcome measures: What data you will collect and how.

I keep a master version in Google Drive and duplicate it for each client. That saves roughly twelve minutes per session that would otherwise go to navigating menus or searching for files. Twelve minutes sounds small but over a month with ten clients that is nearly an hour of administrative time you do not get back.
Common Pitfalls and How to Avoid Them
The biggest problem with solution-focused treatment planning is the assumption that focusing on solutions means ignoring problems. It does not. You still need to understand the client's difficulty well enough to know which exceptions are meaningful and which goals are realistic. A client who says "I want to stop being depressed" is not giving you a workable goal. A client who says "I want to get out of bed by nine instead of noon" is. The difference is actionable. Another pitfall is over-scaling. Asking clients to rate their entire life on a one-to-ten scale produces noisy data. I recommend narrowing the scale question to a specific behavior or situation. "On a scale of one to ten, how confident are you that you can complete the morning routine three days this week?" produces far more useful information than "How happy are you right now?" There is also the issue of insurance compliance. Some payers require diagnostic codes and problem-focused language in treatment plans regardless of your therapeutic orientation. If you are in a managed care network, you will likely need to include DSM-5 codes and a problem statement even though the rest of the document stays solution-focused. I keep a separate diagnostic section at the top of my template that satisfies billing requirements while the body of the plan remains aligned with SFBT principles. This way you are not compromising either standard.
When This Approach Fails
A Solution Focused Treatment Plan Template does not work well in acute inpatient settings where safety and stabilization dominate the immediate clinical picture. It is also less effective with clients who have severe cognitive impairment or active psychosis, where structured problem identification and medication management take priority. In those cases, a traditional problem-focused treatment plan with closer monitoring intervals is more appropriate. Do not force a solution-focused template into a context where it does not fit just because the paperwork looks cleaner. If you work with adolescents, add a parent or guardian goal field and specify consent requirements. For group therapy, adapt the template so each client has individual goals while the group as a whole has shared norms. I once adapted the template for a trauma-informed group by adding a section called "triggers and grounding strategies" alongside the standard scaling questions. That single addition reduced session drift by about thirty percent because clients had a concrete reference point when dysregulation occurred. The template itself is not the value. The value is in how consistently you use it. A half-page solution-focused plan reviewed and updated every session beats a perfect two-page document that sits unused in a file drawer. Pick a format, stick with it for at least eight weeks, and then adjust based on what actually moves the work forward.


