Understanding What Happens When Your Body Takes a Radiation Hit
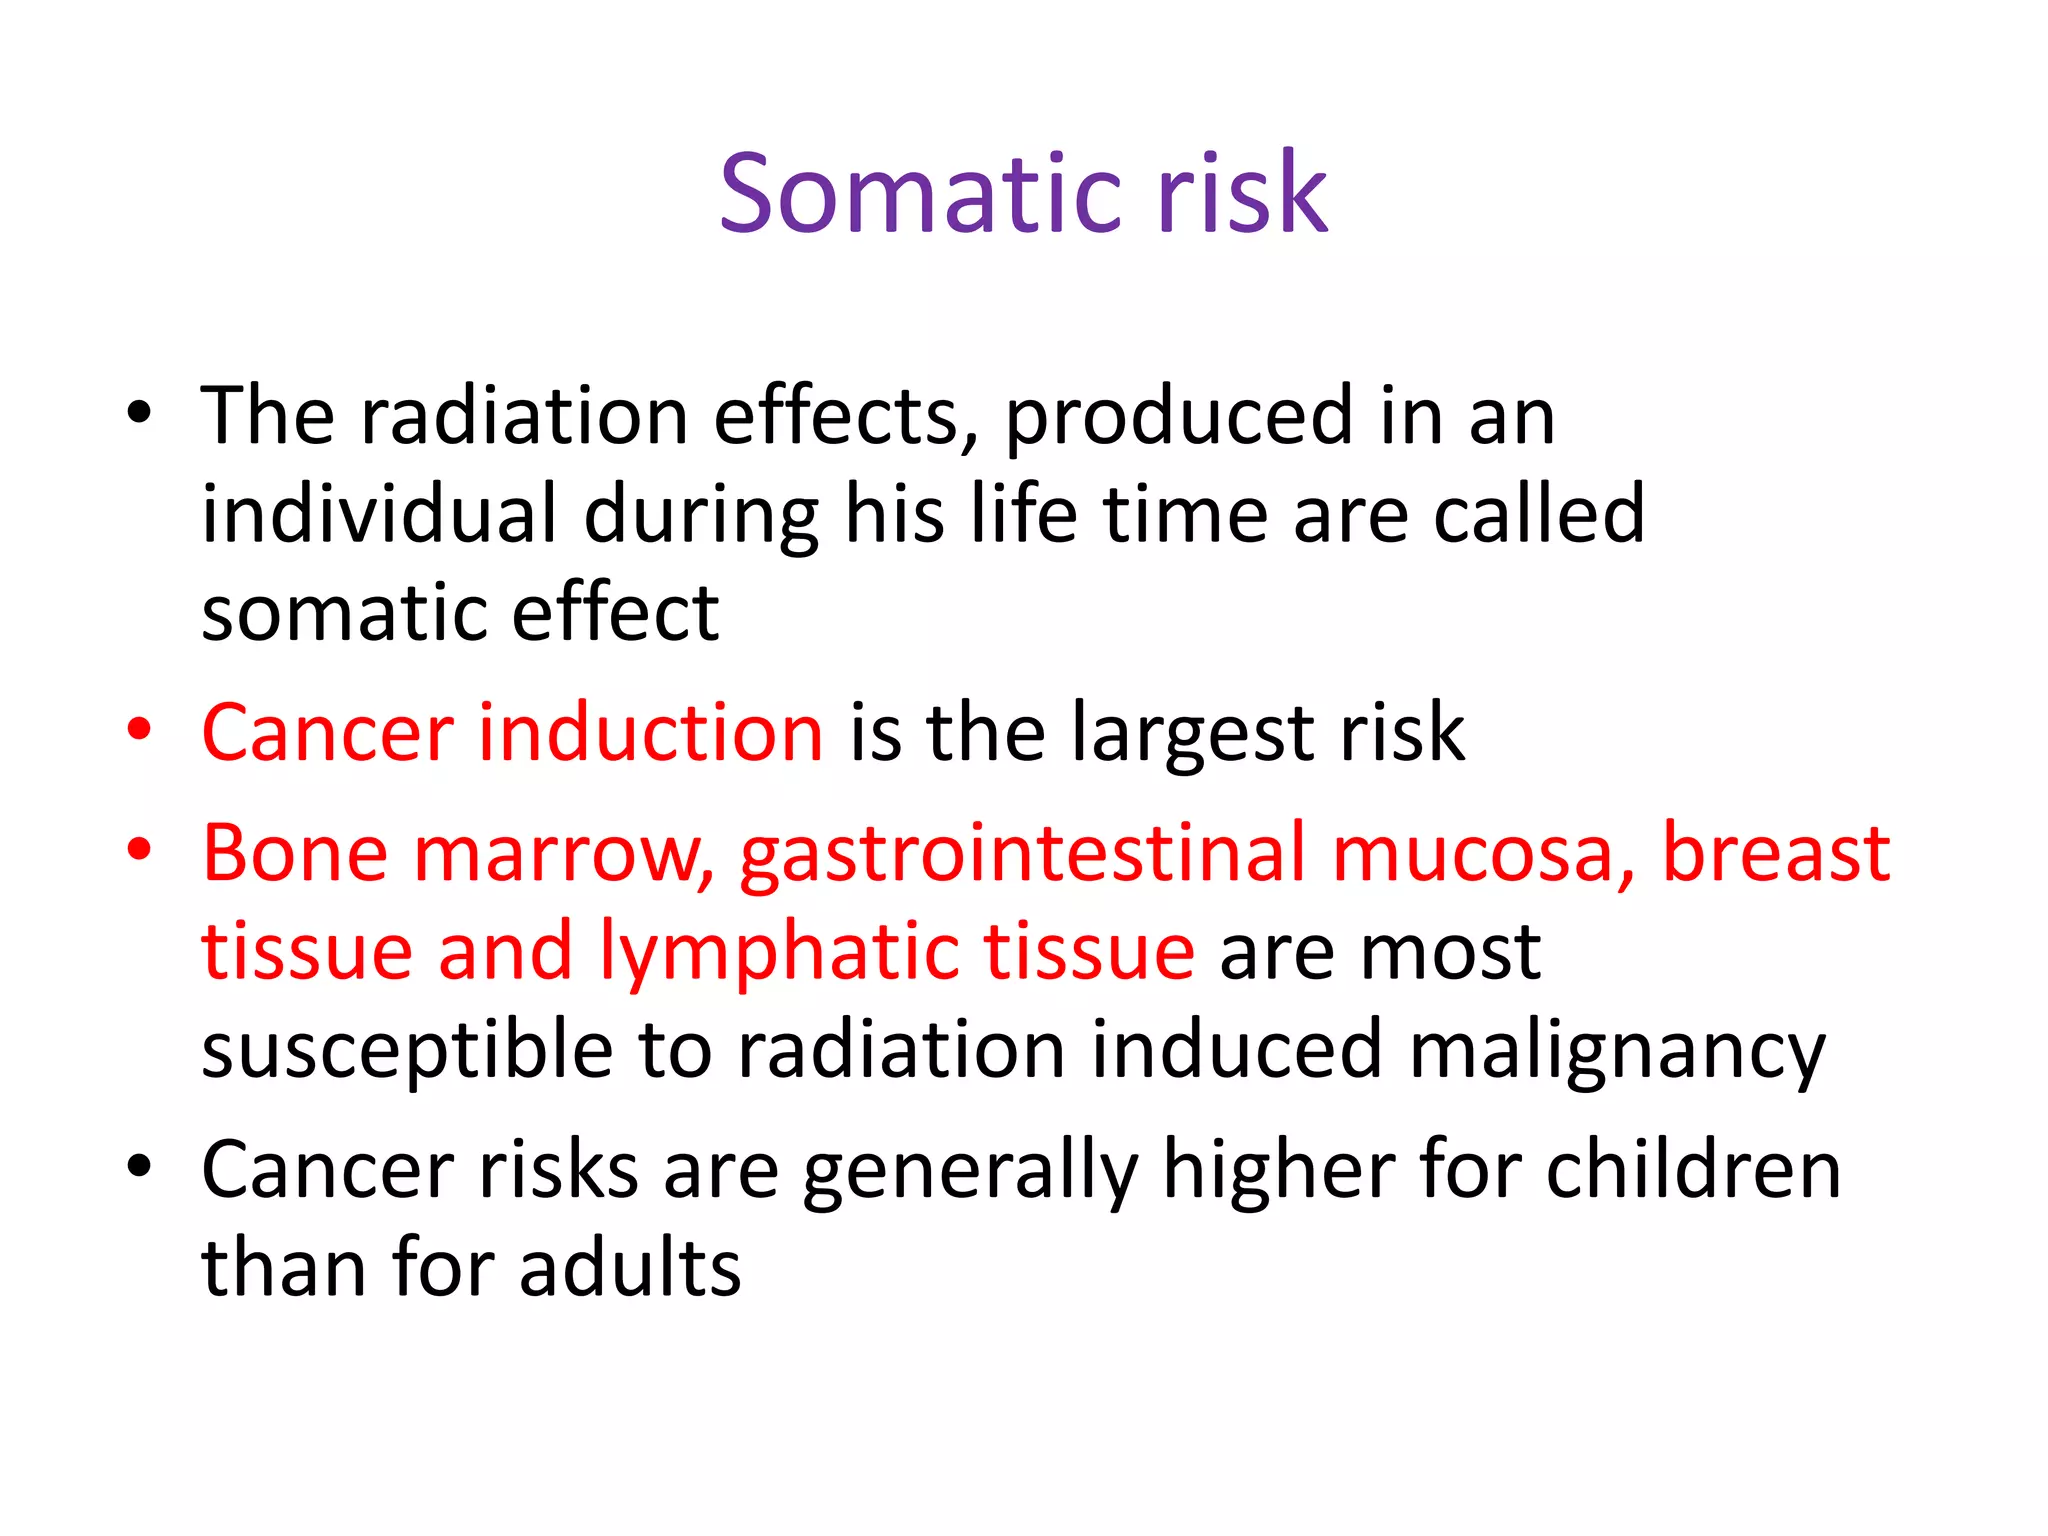
Somatic effects of radiation are the biological changes that show up in the person who was directly exposed. They are not passed to children. That is the difference between somatic and hereditary effects, and it matters more than people usually realize. These effects split into two categories: deterministic and stochastic. Deterministic effects have a threshold dose. Below it, you get nothing. Above it, severity scales with dose. Stochastic effects have no safe threshold. Any dose carries some probability of causing them, and that probability climbs with dose, but the severity does not. I worked on radiation protection compliance for oncology departments and industrial radiography sites for over a decade. The somatic effects question comes up constantly, usually from people who want a simple list of bad things rather than an understanding of dose, time, and geometry. Let me give you the practical version.
Somatic Effects Of Radiation: What Actually Happens in the Body
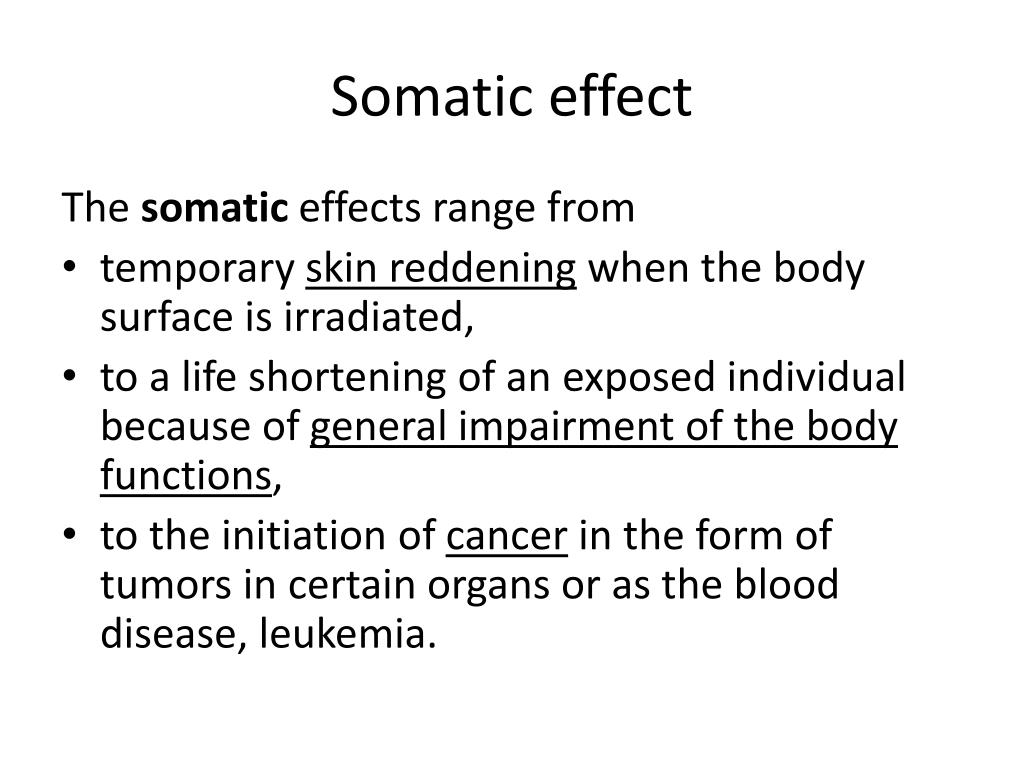
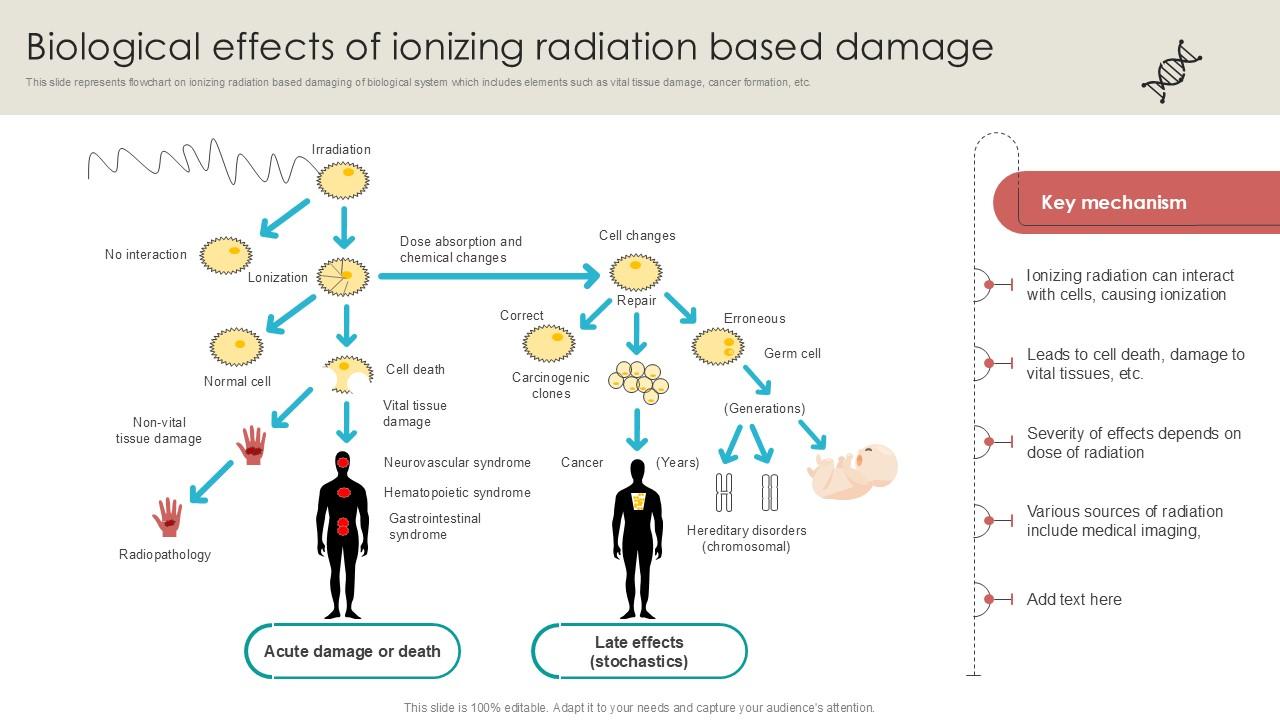
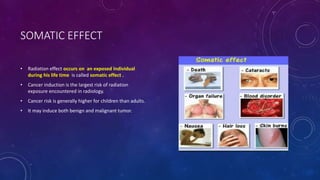
Ionizing radiation deposits energy in tissue. That energy breaks chemical bonds. Water molecules in cells get split into free radicals. Those radicals attack DNA. How your body responds depends on three things: the total absorbed dose, the dose rate, and which organs are in the beam. Deterministic effects appear when enough cells are killed or disabled to impair organ function. Common examples include skin erythema starting around 2 Gy, temporary sterilization in the gonads at roughly 0.15 to 0.5 Gy, and cataract formation in the lens of the eye at doses above 0.5 to 2 Gy depending on the exposure type. Acute radiation syndrome kicks in at whole-body doses above about 1 Gy and has four sub-syndromes: hematopoietic, gastrointestinal, cardiovascular, and neurologic. The hematopoietic form shows up between 1 and 6 Gy. You lose bone marrow function, infections and bleeding become the problem, and without treatment mortality is significant but not automatic. The GI form hits above about 6 Gy. The gut lining sloughs off. Without intensive care the mortality rate is very high. Above 10 Gy you get the cardiovascular and neurologic syndrome, and survival is essentially impossible regardless of intervention. Stochastic effects are the cancer and leukemia risk. There is no threshold. The model most agencies use is the linear no-threshold model, which assumes risk increases linearly with dose at low levels. This model is controversial among some researchers, but it is the regulatory standard everywhere. For context, a typical CT scan of the abdomen delivers roughly 10 mSv, which translates to an estimated excess lifetime cancer risk of about 1 in 2000 according to most risk coefficient tables. A single diagnostic X-ray of the chest is closer to 0.1 mSv, or about 1 in 200,000 in added risk. Small numbers, but they add up across a population.
One counter-intuitive point that people consistently miss: dose rate matters enormously for deterministic effects. A 2 Gy dose delivered all at once will cause skin injury. That same 2 Gy spread over several weeks through fractionated radiotherapy may produce only mild reddening. The cells have time to repair between fractions. This is why radiotherapy works. It is also why shielding calculations based on peak dose rate can be dangerously optimistic if the source is moving or pulsed. Another nuance that catches people out: not all radiation types cause the same somatic damage at the same absorbed dose. Alpha particles are far more biologically destructive per gray than gamma rays or X-rays. That is why the sievert exists. You multiply the absorbed dose in grays by a radiation weighting factor. For gamma and X-rays the factor is 1. For alpha particles it is 20. A technician who inhaled an alpha emitter like plutonium-239 is in serious trouble at doses that a gamma exposure survey would barely flag.
Get the Full Details
Practical Assessment and Management
If you suspect someone has been acutely exposed, the first step is not a blood draw. It is establishing what happened. Dose estimation from exposure scenarios is actually more reliable than most people think, provided you know the source type, distance, and duration. A person standing 1 meter from an unshielded industrial iridium-192 source for 10 minutes can receive several grays. That scenario is completely different from passing through a contamination zone wearing basic PPE for 30 seconds. Bio-dosimetry using chromosome aberration analysis, specifically dicentric chromosomes, is the gold standard for retrospective dose assessment after acute whole-body exposure. It works well between about 0.1 and 5 Gy. Above 5 Gy the cells divide so poorly that the technique loses accuracy, and below 0.1 Gy the signal gets lost in background noise from spontaneous aberrations. I learned this the hard way during a incident investigation where the initial physical dosimetry suggested 4 Gy but the lymphocyte cytogenetics indicated closer to 2 Gy. The discrepancy turned out to be because part of the body was shielded by equipment the worker was sitting on. The physical calculation assumed uniform whole-body exposure. The biological evidence told a different story. The workaround I use now is straightforward: always run physical and biological dosimetry in parallel whenever acute exposure is suspected. Do not rely on pocket dosimeters alone. They can be left behind, smashed, or simply not worn on the part of the body that received the highest dose. I keep a printed dicentric yield table from my lab's validation studies in the emergency binder. It saves about 20 minutes during the crucial first hours while you are waiting for the cytogenetics lab to process the sample.
For stochastic risk communication, the numbers are harder to discuss productively. People either panic or dismiss the risk entirely. The honest position is that at diagnostic and occupational exposure levels the increased cancer risk is real but small compared to the baseline lifetime cancer risk of about 40 percent. A useful framing is that one additional fatal cancer per 10,000 person-Sieverts is the ICRP's current nominal risk coefficient for the whole population. That is a statistical average, not a prediction for any individual. Shielding and distance remain the primary controls for deterministic effects. Time is the third leg. These are not new ideas, but they are the ones that get forgotten under pressure. I have seen technicians skip the thyroid shield during a long fluoroscopy case because "it was just a quick look." A quick look that lasts three minutes with the beam aimed near the neck can deliver several grays to the thyroid and significantly increase lifetime cancer risk. The lens of the eye is even more sensitive now than the old thresholds suggested. The ICRP lowered the occupational equivalent dose limit for the lens to 20 mSv per year averaged over five years, with no single year above 50 mSv. That change came from epidemiological data on interventional cardiologists and radiologists, not from animal studies. Those professionals accumulate dose faster than anyone I know.
What This Approach Cannot Do
Accurate dose reconstruction after an accident is still genuinely difficult. Personal dosimeters do not always reflect organ dose. Whole-body counters cannot detect external beta exposure. Bio-dosimetry has a turnaround time that ranges from 24 to 72 hours depending on the lab. In the first hours after a significant exposure, clinical management is largely supportive because there is no reliable way to know the exact dose before the blood counts start dropping. Granulocyte-colony stimulating factor can help with the hematopoietic syndrome, and bone marrow transplant is an option in selected cases, but neither reverses established GI or neurologic damage. For chronic low-level occupational exposure, the main risk is stochastic. There is no treatment for that except prevention. Strict adherence to the ALARA principle, proper use of dosimetry badges and area monitors, and regular health surveillance are the only real tools. Decontamination is critical for external contamination but has no role in internal contamination unless you act within hours and have the appropriate chelating agents or blockers on hand. If you need the official reference tables for tissue weighting factors, radiation weighting factors, and dose limits, the ICRP publications 103 and 60 are still the baseline documents. The NCRP reports 116 and 147 cover similar ground for the US context. For acute management guidelines, the WHO and IAEA have joint publications on initial medical management of radiation accidents that are free and practical. Most of this information is publicly available. The problem is rarely access. It is knowing which number applies to which situation.