Understanding the Split Wiring in Your Body
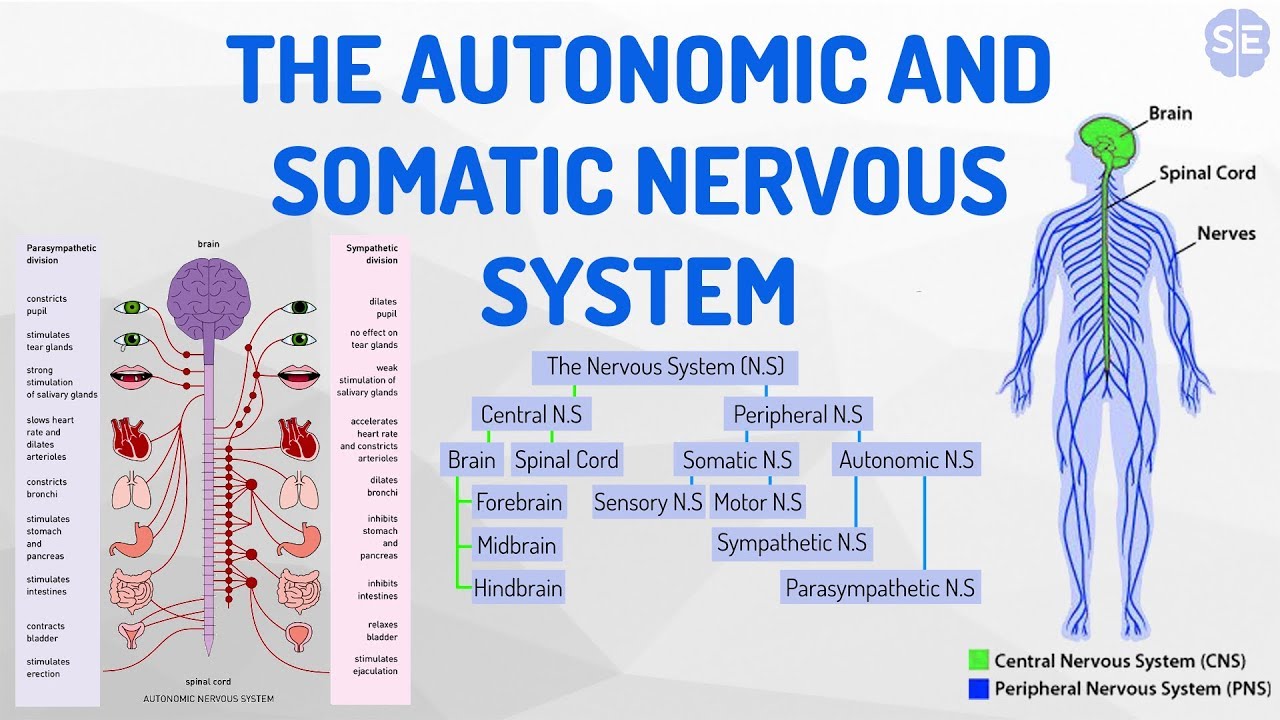
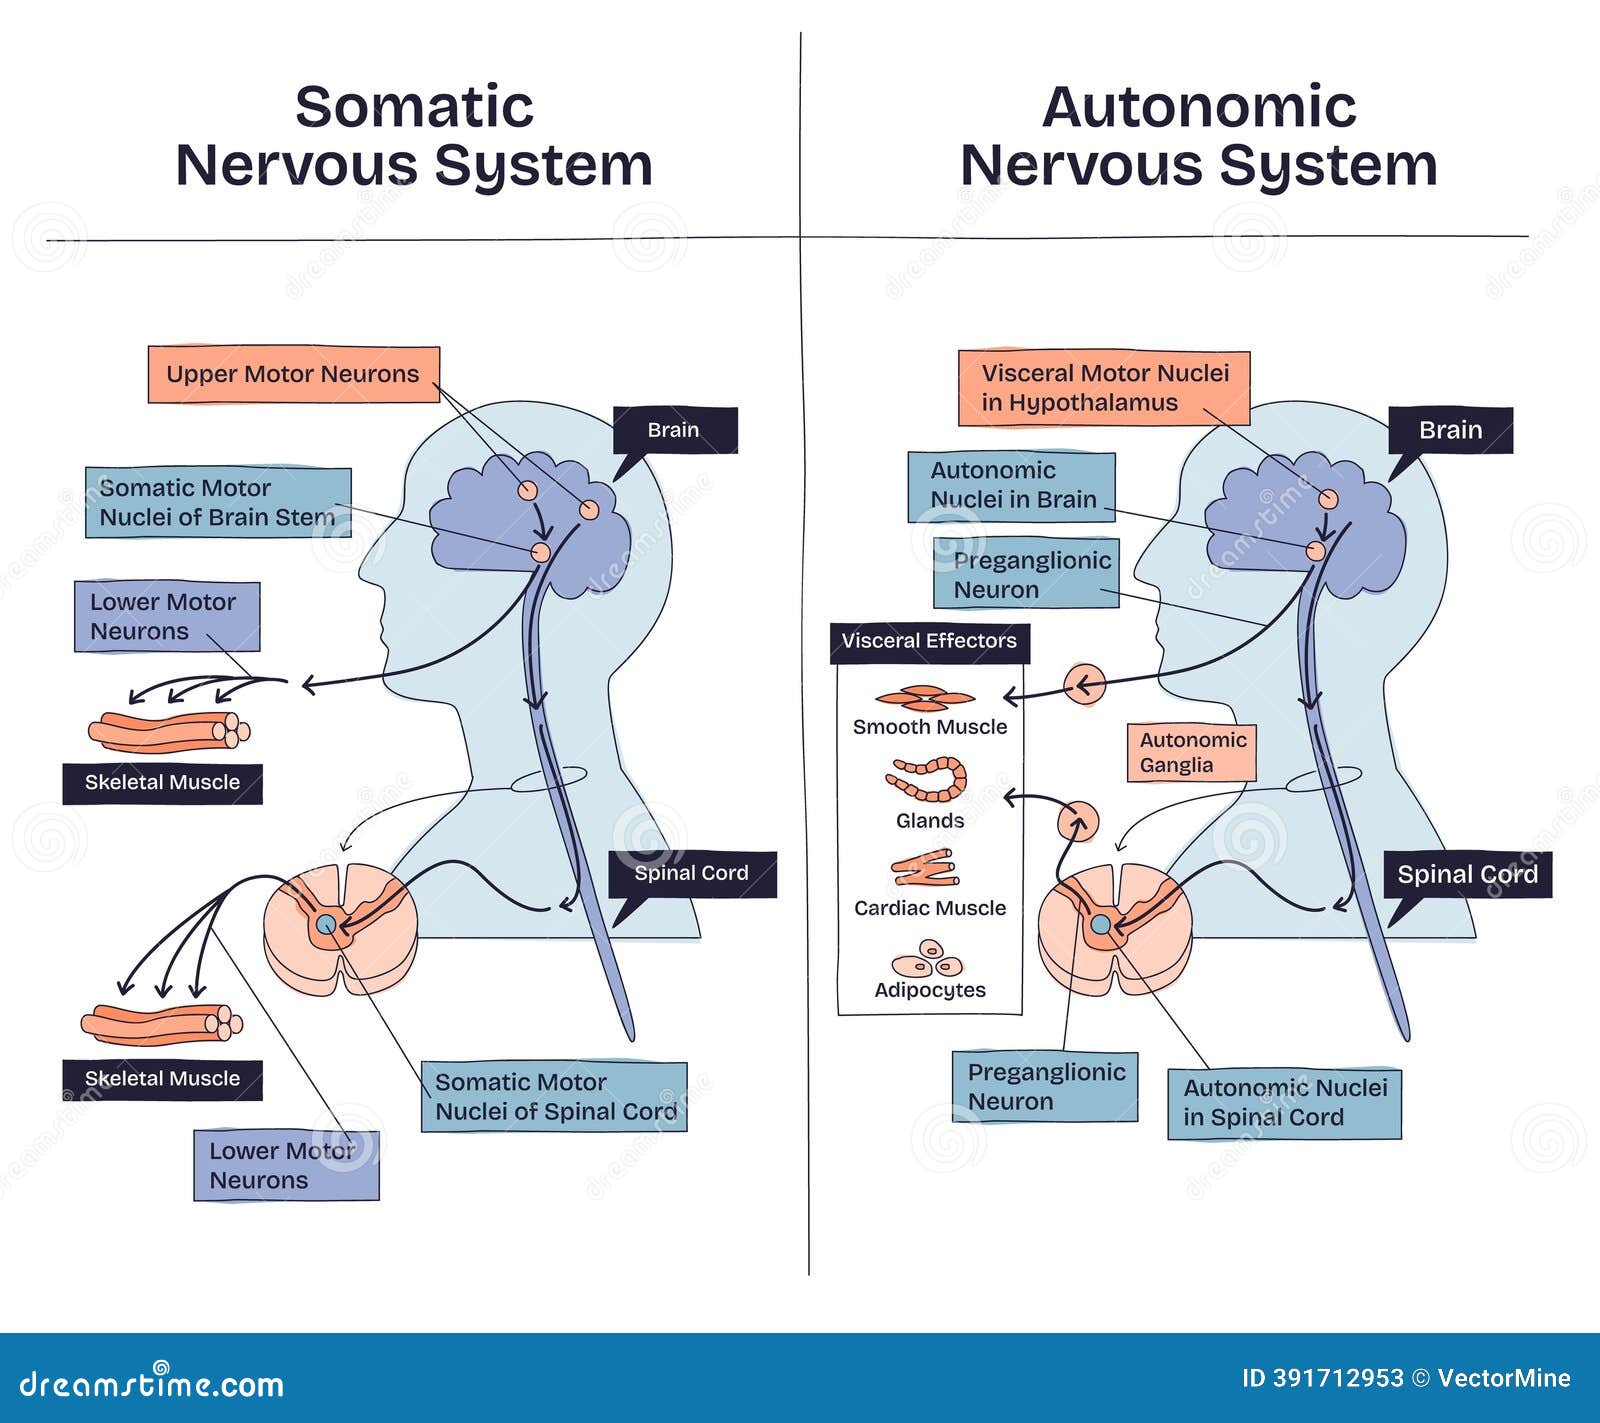
The two systems run at the same time and sometimes fight each other, which is why you can casually type on a keyboard while your heart rate spikes during a stressful phone call. Most people learn them as separate chapters in a textbook, but in practice they're constantly cross-wired and neither one gives you full conscious control. The somatic nervous system handles voluntary movement and sensory input from your skin, muscles, and joints. You decide to lift your arm and those motor neurons fire down the spinal cord to your biceps. It's relatively straightforward routing, though not as simple as it sounds once you account for reflex arcs and proprioception. The autonomic nervous system runs everything else without asking permission. Heart rate, digestion, pupil dilation, sweating, those things happen whether you like it or not. It splits further into the sympathetic branch that prepares your body for action and the parasympopathic branch that handles restoration and conservation.
I spent years troubleshooting patients who presented with what looked like isolated hand tremors or unexplained gastrointestinal issues, only to trace the root cause back to autonomic dysregulation affecting their somatic pathways. One case stands out. A carpenter came in complaining of intermittent finger numbness and muscle weakness in his dominant hand. Everyone assumed repetitive strain injury or a pinched nerve in his cervical spine. Standard workup was clean. MRI showed nothing. EMG was normal. Here's what I noticed that the standard protocol missed. His symptoms worsened after meals and during heat exposure, not just after repetitive work. That pointed toward autonomic involvement. I had him wear a simple heart rate variability monitor for two weeks and track his symptom episodes. The data showed clear dysautonomia patterns correlated with his complaints. Turns out he had undiagnosed POTS, a form of postural orthostatic tachycardia syndrome. The finger numbness wasn't mechanical at all, it was vascular, caused by poor peripheral blood flow regulation. The workaround was surprisingly unglamorous. Increased salt intake, compression garments, slower position changes, and a adjusted medication regimen. His symptoms dropped significantly within three weeks. Most doctors would have sent him straight to hand surgery consultation if he'd presented the same way a few years earlier.
There's a common misconception that the somatic system is purely voluntary and the autonomic is purely involuntary. That's not accurate. You can train autonomic functions like heart rate and body temperature to some degree through biofeedback and meditation. People can learn to modulate their vagus nerve tone intentionally. The boundary is fuzzier than introductory courses suggest. Conversely, somatic control isn't as clean as you might think. Autonomic states heavily influence your motor performance. When your sympathetic system is locked in fight-or-flight mode, your fine motor skills deteriorate even though gross motor function may improve. That's why someone can lift a car off another person in an emergency but struggle to thread a needle while panicked. Another thing beginners miss is the enteric nervous system. Sometimes called the second brain, it's technically part of the autonomic system but operates with significant independence. It contains around 500 million neurons and manages your entire digestive process. The gut-brain axis is real and it explains why stress directly causes diarrhea and why gut health affects mood and cognition.
Get the Full Details
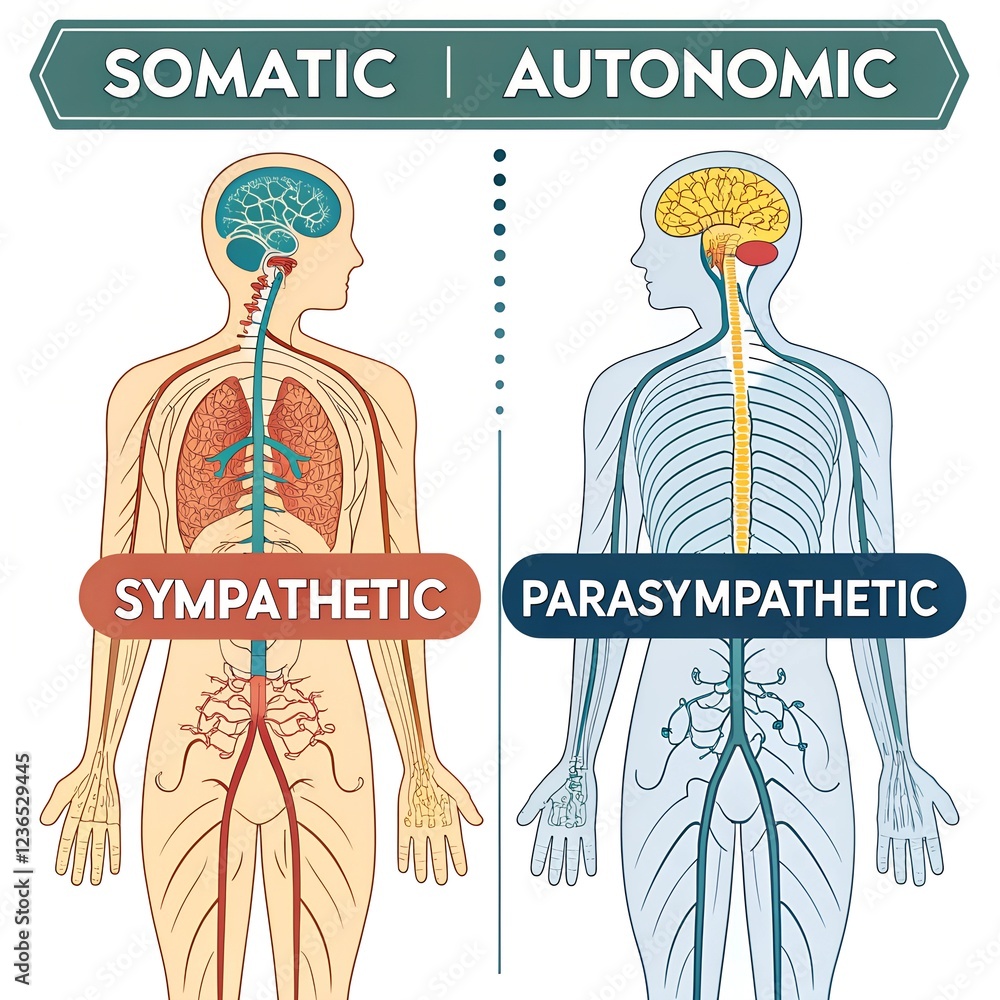
The baroreceptor reflex is another example of somatic-autonomic crossover that textbooks barely cover. When your blood pressure drops, baroreceptors in your carotid sinus and aortic arch send signals to your brainstem, which simultaneously triggers sympathetic activation and adjusts somatic vascular tone in your legs. This is why standing up too fast makes you dizzy, and why crossing your legs and tensing your muscles can help reverse a fainting episode. If you're studying this for an exam or clinical work, stop trying to memorize lists of sympathetic versus parasympathetic effects. Instead, understand the underlying logic. Sympathetic activation shunts blood away from digestion and toward skeletal muscle and heart. Parasympathetic activation does the opposite. Everything else follows from that principle. The problem with teaching this material clinically is that most resources present these systems as perfectly balanced opposites. They're not. Your baseline state is actually a mix of both, called autonomic tone, and it varies constantly based on circadian rhythm, hydration, stress level, metabolic demand, and even recent meals. Healthy people shift between states smoothly. People with dysautonomia get stuck in one state or switch too aggressively.
One practical application worth noting is how anesthesiologists use this knowledge. During surgery, they manipulate both systems deliberately. They suppress somatic motor function with neuromuscular blockers while managing autonomic responses to surgical stress with beta-blockers, anticholinergics, and fluid management. Getting this wrong means hypertensive crisis or dangerous bradycardia under anesthesia. It's a live demonstration of what happens when these systems are artificially separated. I've also seen plenty of cases where patients fixate on one system and neglect the other. Someone comes in with chronic anxiety and gets prescribed SSRIs, which address the central nervous system component, but ignore the peripheral autonomic symptoms like gastrointestinal distress and cardiovascular instability. Or vice versa, someone with IBS gets treated with anti-spasmodics while the stress-somatic connection driving their flare-ups goes unaddressed. The most effective approach treats both systems simultaneously because they're inseparable in practice. Exercise improves autonomic regulation and somatic strength at the same time. Sleep affects both. Chronic pain involves somatic signals that trigger autonomic stress responses, which then amplify the pain through central sensitization. It's a feedback loop, not a one-way street.
A word of caution about self-diagnosis. Autonomic disorders are notoriously difficult to diagnose and often take years to identify properly. Conditions like POTS, neurocardiogenic syncope, and idiopathic hyperhidrosis get misdiagnosed as anxiety disorders or chronic fatigue repeatedly. If you're researching this for personal reasons and your symptoms persist, seek out a specialist who understands dysautonomia rather than relying on internet information alone. The somatic nervous system uses acetylcholine at neuromuscular junctions and the autonomic system uses a wider neurotransmitter palette including norepinephrine, acetylcholine, dopamine, and various peptides. That chemical diversity is one reason autonomic dysfunction produces such varied and unpredictable symptoms compared to somatic nerve damage, which tends to follow cleaner anatomical patterns. Understanding how these systems interact has saved me from ordering unnecessary imaging studies and sending patients down the wrong treatment paths multiple times. The body doesn't respect the categories we invent for educational purposes. It just works, or it doesn't, and the line between voluntary and involuntary control is thinner than most people realize.