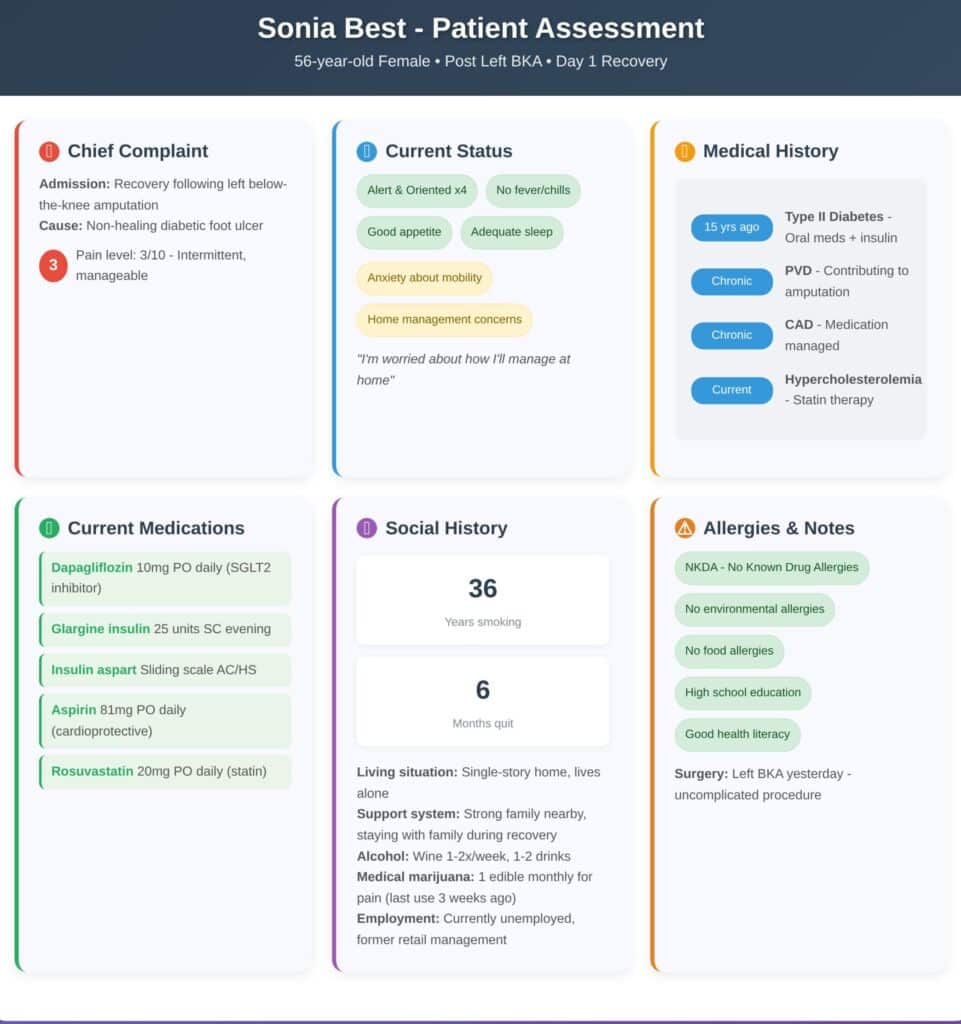
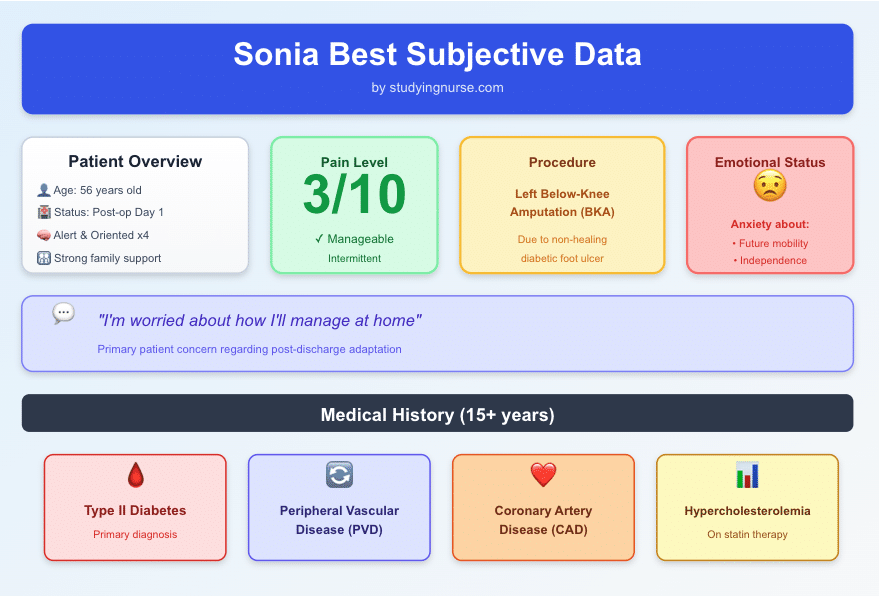
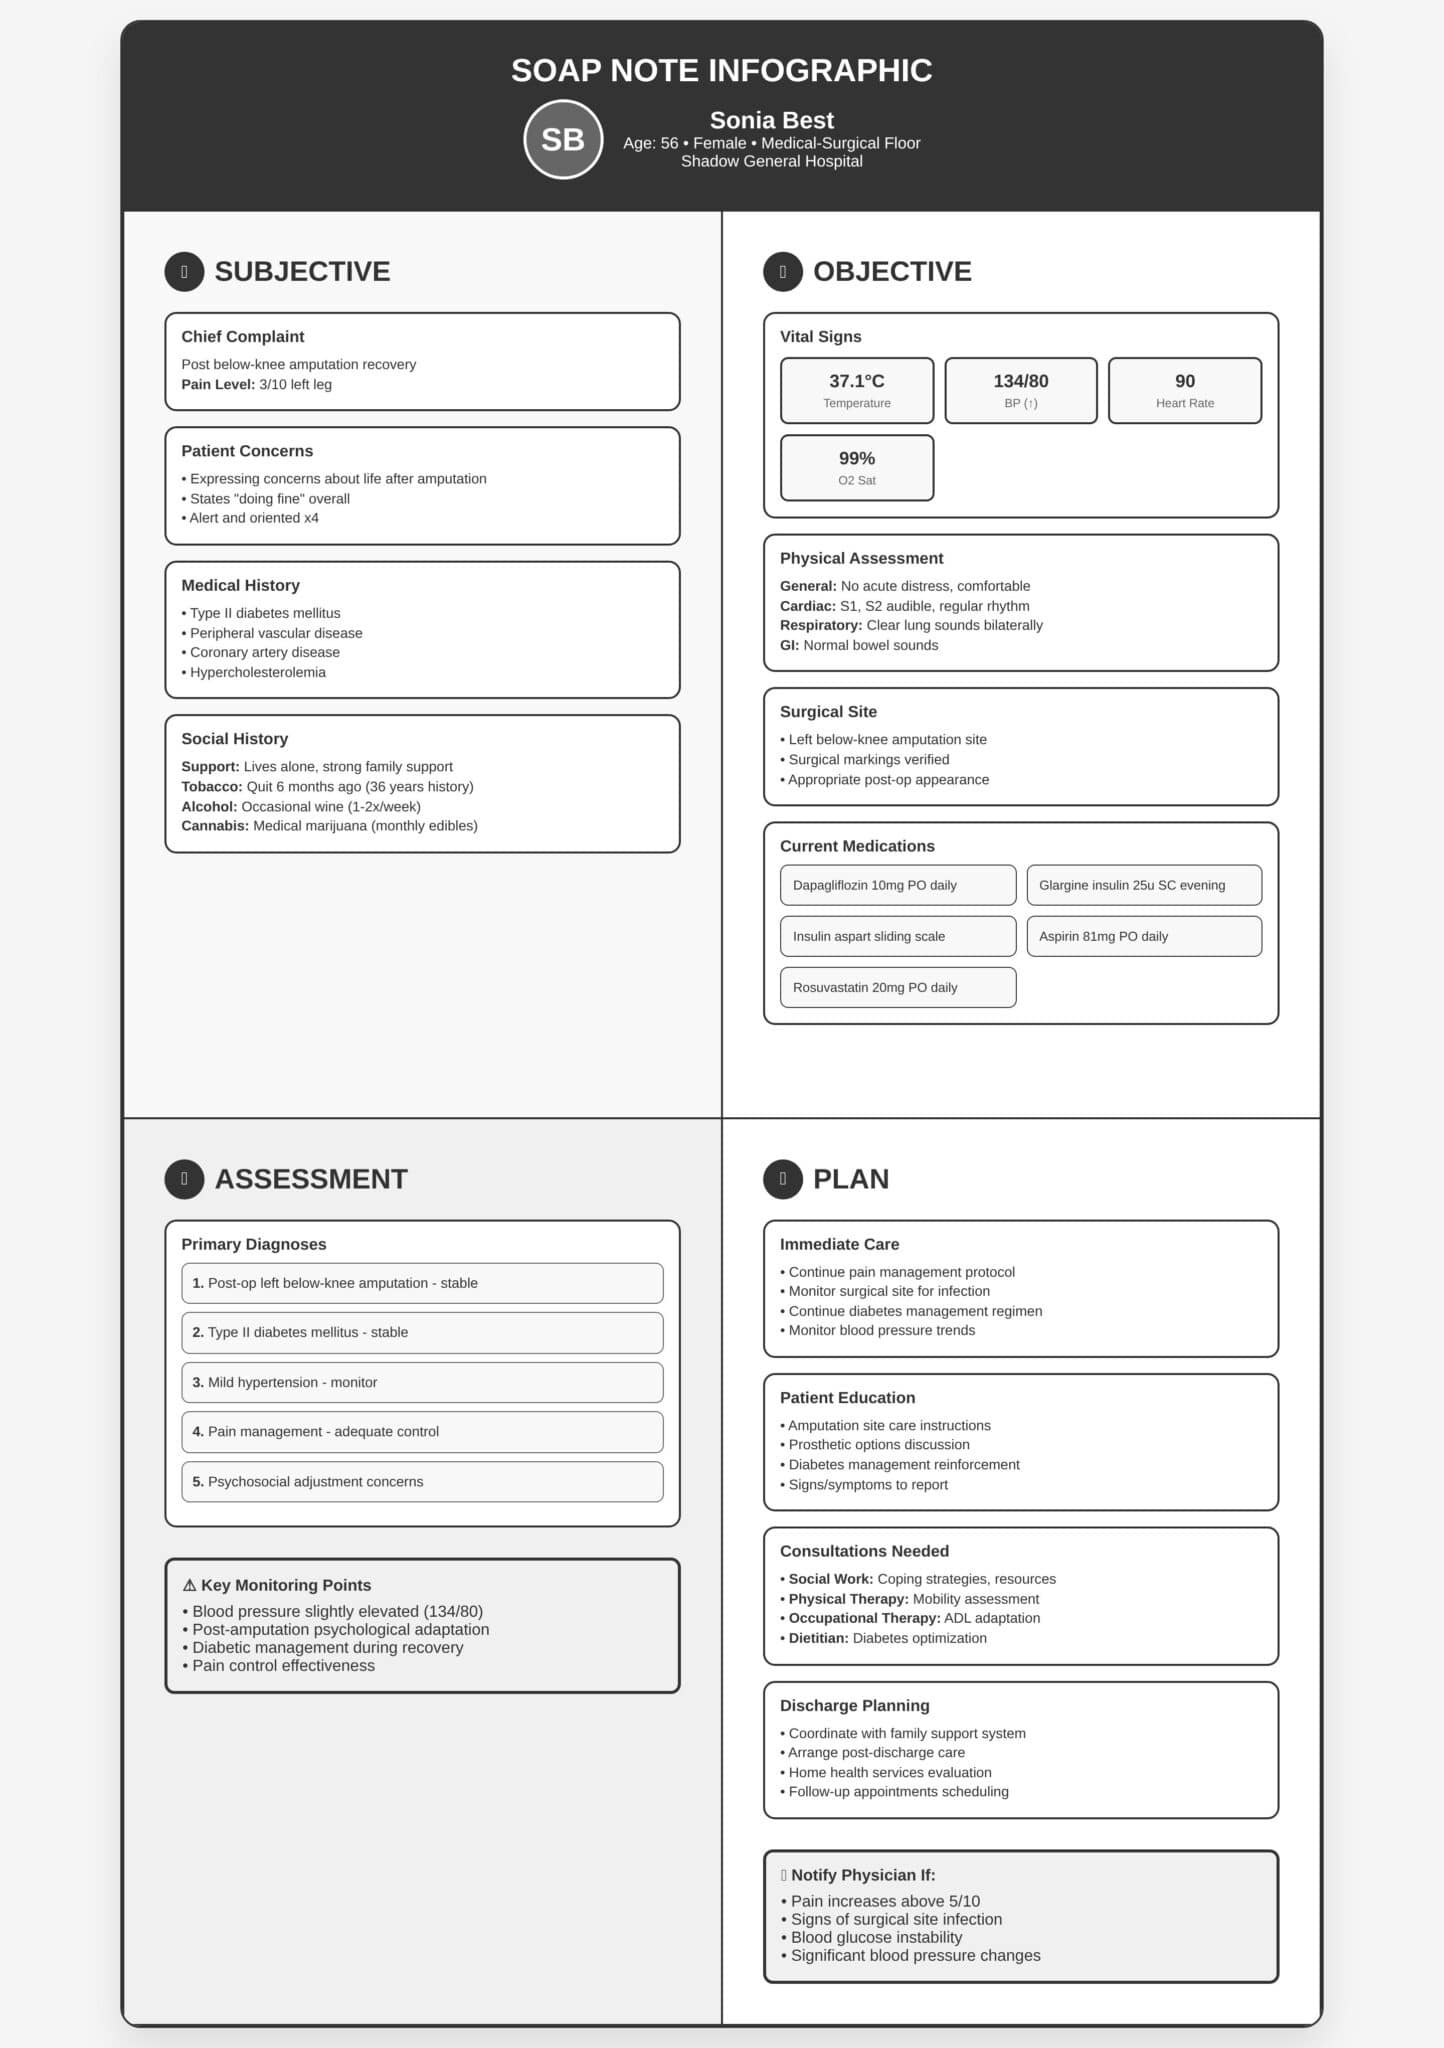
What Sonia Best Subjective Data Actually Is
Sonia Best Subjective Data isn't a product you download. It's a collection of patient-reported outcome surveys and quality-of-life metrics that researchers and clinicians at SBC (the organization behind the name) use to measure how people experience their conditions outside of lab numbers. You'll see it referenced in oncology, chronic pain, and mental health research. The core idea is straightforward: doctors and researchers ask patients to rate symptoms, mood, function, and treatment burden, then aggregate those responses into datasets. The reason people look into it is because traditional clinical endpoints miss a lot. A tumor might shrink on a scan while the patient is unable to work, sleeping poorly, and reporting severe fatigue. Subjective data captures that gap. SBC has built several validated instruments around this — things like the SOMS (Symptom Outcome Measure Suite) and patient-generated health data pipelines that feed into EHR systems. I spent about three years integrating subjective data collection into a clinical workflow at a mid-size research site. The first thing you need to understand is that the instruments themselves are the easy part. Getting patients to actually complete them consistently, and getting the data back into a format your IRB and stats team will accept, is where everything falls apart if you don't plan ahead.
Here's how the actual process works from a practical standpoint.
How to access and use Sonia Best Subjective Data instruments
Step one: figure out which instrument fits your use case. SBC offers several. The most commonly requested ones are the PHQ-9 and GAD-7 for depression and anxiety screening, the PROMIS item banks for broader quality of life measurement, and their own custom symptom burden scales. Don't pick the one that sounds impressive. Pick the one that matches what you're actually trying to measure. I've seen sites pull in entire PROMIS banks for a study that only needed three domains. That creates data management nightmares later. Step two: get your IRB approval with the right language. Subjective data often includes sensitive information — mood, substance use, suicidal ideation. Your IRB will scrutinize this more than they will a basic demographics collection. Make sure your consent language explicitly covers electronic reporting, data storage duration, and who has access. I had an IRB come back twice on a protocol because I hadn't specified that patient responses would be de-identified before entering the database. That cost me three weeks. Step three: choose your delivery method. You have roughly three options. Paper surveys at the clinic — simplest, highest dropout rate, especially with older populations. Patient portal or app-based delivery — better compliance, requires IT setup. Hybrid — paper for those who can't use tech, digital for everyone else. The hybrid approach usually gets the best completion rates but doubles your data entry work unless you use an OCR scanning tool. I found that scanning completed forms with Readiris and running them through a basic regex parser cut my data entry time from about four hours per week down to twenty minutes.
Get the Full Details
Step four: score and validate before you collect a single response. Run through each instrument yourself. Fill out a fake patient profile and score it. Check that your scoring algorithms match the published manuals. I learned this the hard way when our site's automated PHQ-9 scoring was off by one point because someone had swapped the reverse-scoring logic on two items. We'd already collected sixty-seven responses before a chart audit caught it. All sixty-seven had to be recollected and resubmitted to the sponsor.
Common pitfalls that nobody warns you about
The biggest issue I ran into repeatedly is missing data patterns. Patients skip questions. Not randomly — they skip the emotionally heavy ones. Depression scales get skipped by depressed patients. Anxiety items get skipped by anxious patients. This creates systematic bias that standard statistical handling won't fix. The workaround I use is collecting partial scores whenever possible and flagging which items were skipped, rather than dropping the entire response. Most of the published instruments allow subscale scoring even with incomplete data, but you have to check the manual for each one. Another problem is response shift. This is when a patient's internal standard for "how am I feeling" changes over time because they're adapting to their condition. A cancer patient who reports moderate pain in month three might actually be in worse absolute pain than they reported in month one, because their baseline shifted. The data looks better than it is. There's no clean fix for this. The best you can do is note it in your limitations section and consider using anchor-based change methods when you analyze the data. Then there's the technology access gap. If you're using digital surveys, about 15-20 percent of your typical patient population — especially in oncology and geriatric clinics — won't have reliable smartphone access or digital literacy. I stopped trying to push everything digital and went back to offering paper as the default with an opt-in for digital. Completion rates went up and the demographic skew in the data disappeared.
When subjective data collection isn't the right choice
Let me be direct about the limitations. Subjective data is noisy. It's influenced by language barriers, cognitive impairment, cultural differences in how symptoms are expressed, and simply having a bad day. If your study requires precise, objectively verifiable endpoints, subjective data should supplement those endpoints, not replace them. There are also situations where patient-reported data can introduce more problems than it solves — particularly in studies with small sample sizes where missing data from even a few dropouts can invalidate statistical power calculations. If you're working with populations that have significant cognitive decline, severe psychosis, or language barriers without validated translated instruments, subjective data collection will produce unreliable results. In those cases, caregiver-reported outcomes or clinician-rated scales are more appropriate, even if they're imperfect. The other constraint is regulatory. Some sponsors and regulatory bodies have specific requirements about which validated instruments they'll accept. The FDA has published guidance on patient-reported outcome measures, and if you're planning a submission, you need to use an instrument that meets their criteria. Using a non-validated custom survey for anything regulatory-facing is a quick way to get a clinical hold.
Sonia Best Subjective Data resources and next steps
The SBC website hosts their instrument library and scoring manuals. You'll need to create a researcher account to access the full item banks and scoring software. The free tier covers basic screening tools like PHQ-9 and GAD-7. The paid tier unlocks the full PROMIS suite, custom scale builders, and their data export APIs. For most academic researchers, the free tier is sufficient to start. If you're doing a multi-site study, the API access becomes necessary within the first few months. I'd also recommend joining the PSOM (Patient-Reported Outcomes Measurement) community forums. The people posting there are usually clinicians and data managers who've already made the same mistakes you're about to make. The discussions aren't glamorous, but they're more useful than any training video I've seen on the topic. One final note: keep your data cleaning pipeline documented from day one. I've lost track of how many times I've seen a dataset become unusable because someone changed a scoring rule mid-study without recording it. A simple version-controlled spreadsheet tracking every transformation you apply to the raw data will save you more headaches than any tool SBC sells.