
Getting It Done Without the Fluff
Potty training a child with special needs isn't fundamentally different from potty training any other child, but the timeline is stretched and the margins for error are thinner. You're working with a population where communication barriers, sensory processing differences, motor planning challenges, and rigid behavioral patterns can all interfere with what should be a straightforward learning process. The standard advice you find online assumes a baseline of verbal comprehension and typical sensory regulation. That assumption fails you quickly. The core mechanic is the same regardless of the disability: establish a cue, create a consistent routine, and reinforce the target behavior. Everything else is just tactical adjustment for whatever obstacles your specific child presents. I learned this the hard way with a nonverbal autistic child who could follow a twelve-step sequence to assemble a puzzle but would have a full-body shutdown if you changed the color of the potty seat by one shade.
The Framework Behind Special Needs Potty Training
Most methods fall into one of three buckets: child-led readiness approaches, structured schedule-based training, or a hybrid of the two. The child-led method works well for kids with typical cognitive processing and decent verbal skills. Schedule-based training, sometimes called timed sitting, is where you actually need to spend your time understanding the mechanics before you start. For children with developmental delays, intellectual disabilities, or autism spectrum disorder, the schedule approach almost always produces faster results because it removes the dependency on the child initiating the behavior independently. Here is how the schedule method actually functions in practice. You establish a baseline first. For roughly three days, you track every instance of urination and bowel movement with exact timestamps. No potty attempts, no pressure, just data. This baseline tells you the natural intervals between eliminations and identifies patterns. A child who typically voids every 90 to 120 minutes during the day needs to sit on the potty at those intervals, not whenever they happen to signal they need to go. The signal might never come if the child has limited interoceptive awareness, which is extremely common in this population. That's why the external schedule replaces the internal cue. You'll need a timer. A smartphone timer works fine but introduces variables like screen distraction and the noise of notifications. A dedicated kitchen timer or a vibrating watch gives you the same function without the extra sensory input. The child sits on the potty at each scheduled interval for three to five minutes. If nothing happens, you end the session calmly and return to normal activity. You do not reward empty sits. You only reinforce successful elimination. This distinction matters more than most parents realize because accidentally reinforcing non-productive sitting creates a pattern where the child learns to sit and fidget rather than sit and eliminate.
Reinforcement needs to be immediate and specific. I spent weeks trying to figure out why a nine-year-old with Down syndrome wasn't progressing despite consistent scheduling and what I thought was strong motivation. The issue turned out to be that my reinforcement was delivered three seconds after success, and for a child with processing delays, that gap was too long. The connection between the action and the reward didn't form. Dropping it to within half a second of completion completely changed the trajectory. The reinforcer itself also mattered. Stickers worked for six months and then became worthless. Switching to a small cup of Welch's grape juice immediately after each success re-engaged motivation for another eight months. You need to be willing to let go of reinforcers that lose their value rather than increasing the magnitude of the same one until it becomes unsustainable.
Get the Full Details

Concrete Steps That Actually Work
Start with the equipment. Not all potties are equivalent for children with special needs. A standard plastic potty chair can feel unstable for a child with hypotonia or balance issues. A model with armrests and a wider base provides physical security. For children with sensory sensitivities, the sound of flushing can be genuinely painful. A portable flush system that connects to your regular toilet lets you maintain the visual of a real toilet while controlling when the noise happens, or you can skip flushing entirely during the training phase and introduce it later once the behavior is established. Clothing is a practical factor that gets overlooked. Elastic waistbands are non-negotiable initially. Buttons, zippers, and belts add steps between the decision to eliminate and the ability to act. Even for a child who can independently manage clothing, removing those layers during training reduces friction points. Once the habit is solid, you can reintroduce more complex clothing as a separate skill to teach. The bathroom environment itself needs attention. Fluorescent lighting, echoing acoustics, and strong smells from cleaners or air fresheners can create avoidance behavior in sensitive children. I dealt with a case where a child with sensory processing disorder refused to sit on a potty that was otherwise perfect because the bathroom floor tiles reflected light in a way that created a visual disturbance she found distressing. We solved it by placing a mat over the tiles and switching to a bulb with a warmer color temperature. The potty and the routine hadn't changed at all. The room had been the barrier the entire time.
Acknowledging the downsides is important because this process does not scale well to multiple children in the same household. The schedule-based approach demands that at least one adult be consistently available during waking hours for anywhere from two to eight weeks depending on the child. It's not a leave-it-to-the-grandparents situation. Parents of multiple children often need to rotate shifts or bring in temporary support. The method also breaks down if the child is frequently ill, traveling, or experiencing major routine disruptions. Regression during these periods is normal and expected, not a sign that the training failed. You resume the schedule from where you were, not from zero. Another limitation is that this approach primarily addresses daytime bladder and bowel control. Nighttime dryness operates on different physiological mechanisms involving antidiuretic hormone regulation and typically develops months or years after daytime training is complete. Some children with certain genetic conditions like Down syndrome or Prader-Willi syndrome may never achieve reliable nighttime continence, and that outcome is unrelated to the quality of the daytime training. Wishing for faster progress on nighttime control won't accelerate the biological maturation required.
When Standard Approaches Fall Apart
There are scenarios where even a well-executed schedule-based method stalls or fails entirely. Children with severe physical disabilities who cannot sit unsupported need adaptive positioning equipment, which introduces another layer of complexity and often requires consultation with an occupational therapist. Children on certain medications, particularly stimulants for ADHD or antipsychotics, may experience urinary retention or constipation that physically prevents elimination on command. In those cases, the medical issue needs resolution before behavioral training can proceed effectively. For children who demonstrate extreme aggression or self-injury during potty sits, the schedule method needs modification. You don't push through aggressive episodes. You reduce the duration of sits, increase the distance between attempts, and systematically build tolerance before returning to longer sessions. This is where a board-certified behavior analyst or a therapist experienced in special needs populations becomes necessary rather than optional. The cost of attempting to manage severe behavioral escalation without training far exceeds the cost of a single consultation. One counter-intuitive point that many parents miss: bowel training should not be deferred until bladder training is complete. Constipation is the single biggest complication in special needs potty training, and it creates a vicious cycle. A child who holds stool due to pain or fear develops harder, larger stools that cause more pain, which reinforces the holding behavior. Starting bowel routines early, even if bladder control is still developing, breaks that cycle. A scheduled sitting routine that includes post-meal timing, since the gastrocolic reflex naturally stimulates bowel movement after eating, addresses both systems simultaneously.
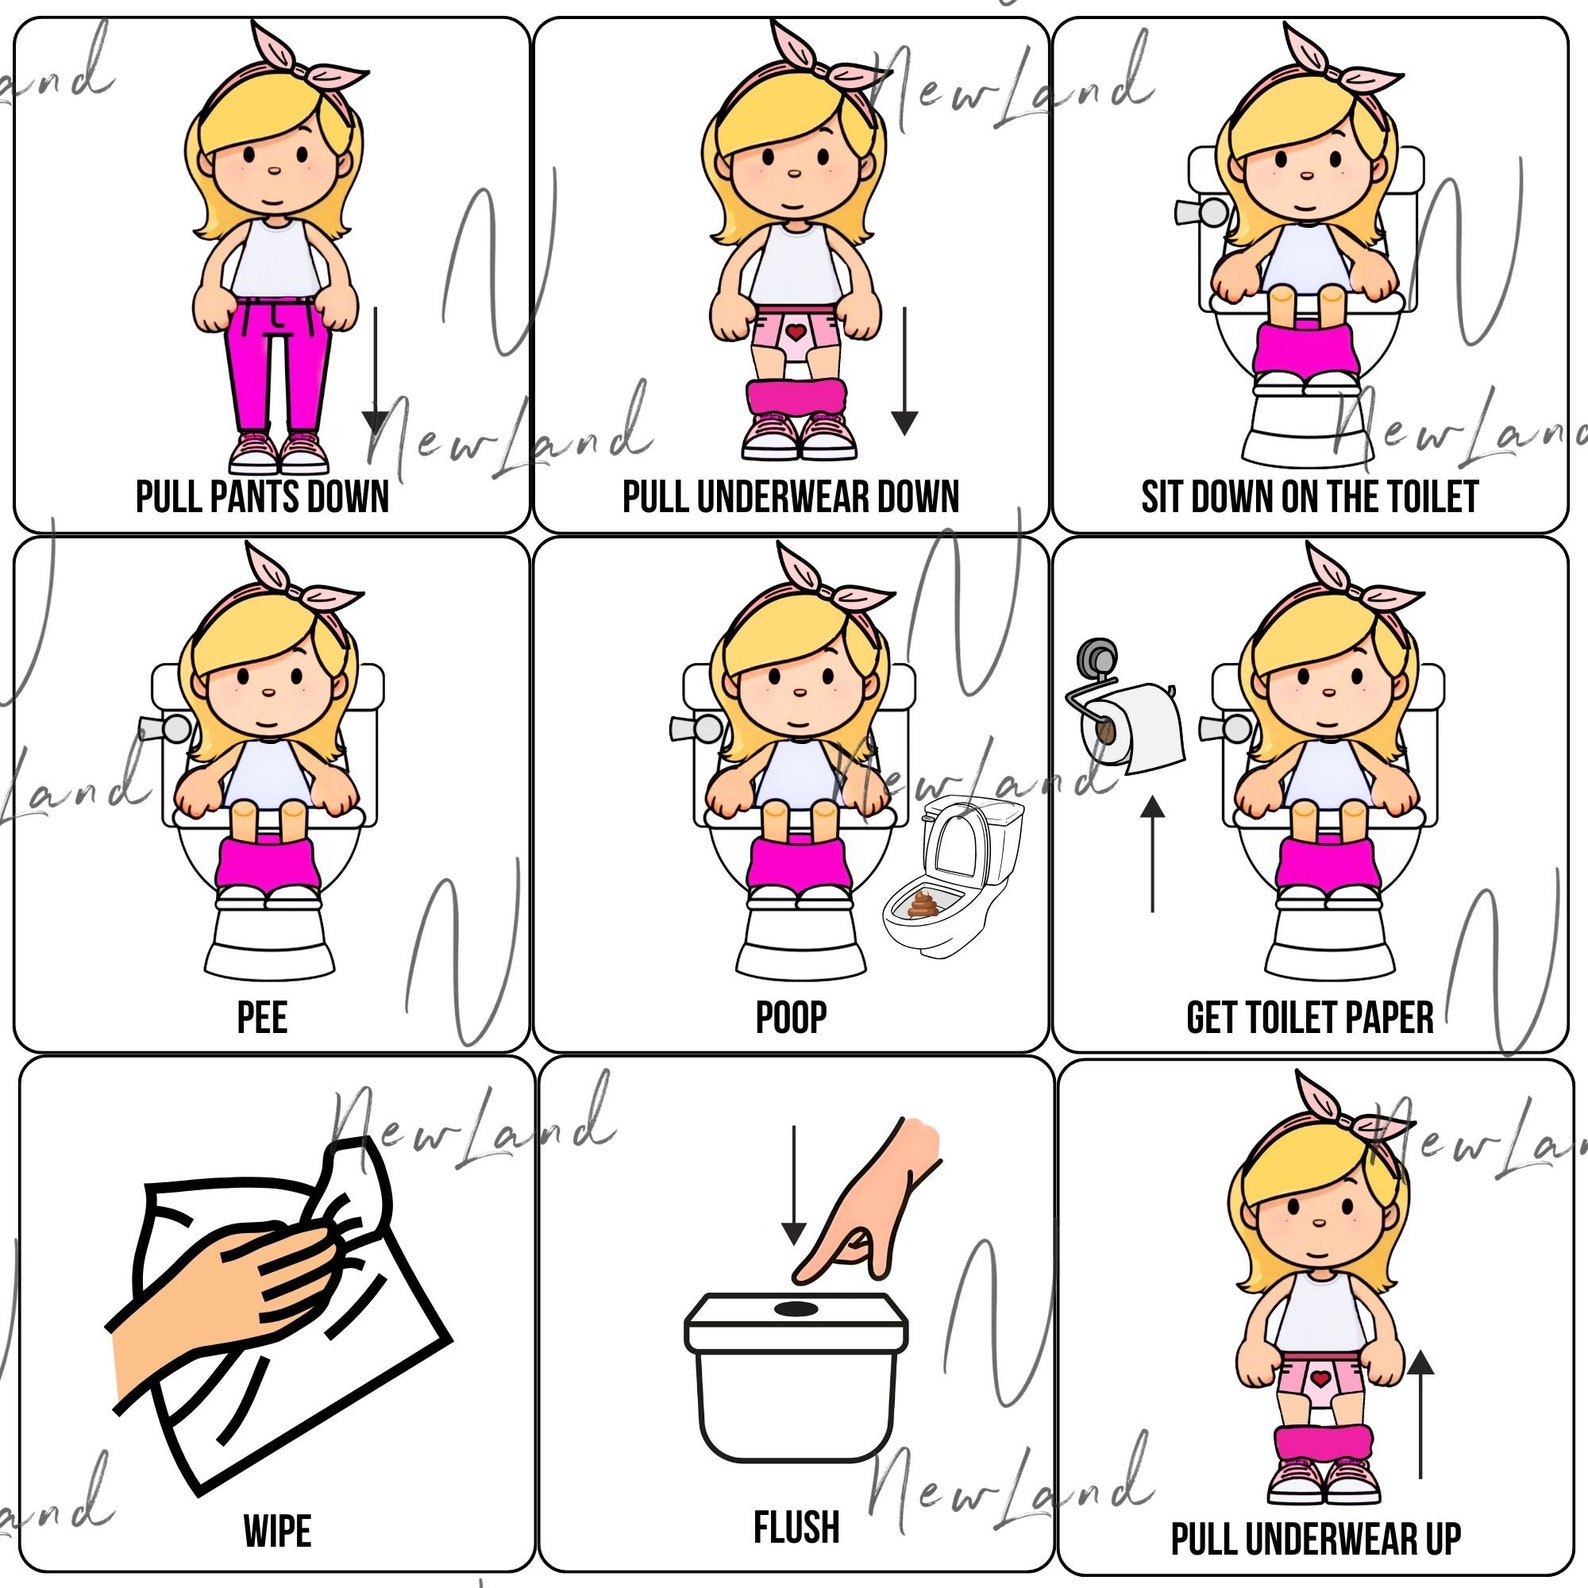
The tools available have improved but the fundamental process hasn't changed in decades. There are apps that track scheduling and provide prompts, sensor-based underwear that alerts you when elimination occurs, and weighted seating platforms for children who need deep pressure input. These are aids, not replacements for the underlying structure. The structure is what does the work.
Where to Find Reliable Resources
The Centers for Disease Control and Prevention maintains a section on potty training for children with disabilities that covers medical considerations and developmental milestones. The American Academy of Pediatrics has position statements on toileting training for children with special healthcare needs that address medication interactions and developmental variances. Several occupational therapy organizations offer downloadable visual schedule templates designed specifically for children with autism, which can be adapted for other populations. Commercial programs like the Potty Training for Children with Special Needs workbook by Dr. Wendy Magee provides a more structured curriculum for families who need step-by-step guidance rather than general principles. What separates successful outcomes from prolonged frustration usually comes down to three things: accurate baseline data before you start, consistency in the schedule without adult fatigue making excuses, and the willingness to adjust the reinforcer system when it stops working. The rest is details that vary by child.



