Shoulder Special Tests: A Practical Walkthrough
The shoulder Special Tests Shoulder Exam is a battery of provocation maneuvers designed to isolate specific structures around the glenohumeral joint and surrounding soft tissues. You won't diagnose a full rotator cuff tear with one test alone. These tests are meant to be clustered, interpreted together, and then confirmed with imaging when the clinical picture demands it. I've spent years doing these in clinic, and the biggest mistake I see people make is treating them as pass/fail checkboxes instead of pieces of a diagnostic puzzle. Let me walk you through the ones that actually matter in practice, how to perform them, and where they tend to mislead you.
Impingement Tests
The Neer impingement test is about as straightforward as it gets. You stabilize the scapula with one hand and passively forward flex the arm with the other, driving the humeral head into the coracoacromial arch. Pain between 60 and 120 degrees is a positive sign. What most guides miss is that you need to internally rotate the shoulder during this maneuver. If the arm stays neutral or externally rotated, you're not really compressing the supraspinatus tendon against the acromion. The test becomes unreliable because you're moving the whole limb without targeting the structure you care about. The Hawkins-Kennedy test compresses the supraspinatus and subscapularis under the coracoacromial ligament. You flex the elbow to 90 degrees, support the forearm, and forcefully internally rotate the shoulder. A positive test reproduces the patient's deep anterior or lateral shoulder pain. The sensitivity here is decent, around 76 percent, but specificity drops to about 55 percent. That means you'll flag people who don't actually have impingement fairly often. I had a patient last year who tested positive on both Neer and Hawkins but turned out to have early cervical radiculopathy referring pain to the deltoid insertion. The shoulder was fine. The C5 root was the problem. The empty can test, or Jobe test, isolates the supraspinatus. The patient's arms are elevated to 90 degrees in the scapular plane, about 30 degrees of forward flexion, and internally rotated so the thumbs point down. You apply downward pressure while they resist. Weakness or pain suggests supraspinatus pathology. The trap is that patients will often substitute with the upper trapezius, especially if they're nervous or genuinely weak. Watch the trap fire before you call it a positive. I've seen physical therapists give a false negative because the patient's pain inhibited their effort, not because the tendon was intact. Adding a gentle scalene or cervical spine assessment to your exam caught that misdirection more than once.
Rotator Cuff Integrity Tests
The drop arm test checks for a full-thickness supraspinatus tear. The examiner lifts the patient's arm to full abduction and asks them to lower it slowly and controlled. If the arm drops suddenly or the patient cannot hold it up against gravity, that's a positive finding. The specificity runs high at around 90 percent, but sensitivity is mediocre, somewhere in the 50s. A negative drop arm test does not rule out a significant tear. I had a case where a patient could lower the arm with a hitched, strained motion and still had a massive 3 centimeter supraspinatus tear on MRI. The hitch was the clue. Patients compensate in ways that mask the textbook presentation. The lag sign and external rotation lag sign assess the subscapularis. For the lag sign, you abduct the shoulder to 100 degrees and internally rotate the arm, then ask the patient to maintain that position as you release support. A lag means they can't hold it. The external rotation lag sign is trickier. You bring the arm into about 30 to 40 degrees of external rotation with the elbow at the side and let go. The patient should maintain that external rotation. Falling back into internal rotation indicates subscapularis dysfunction. These are not common tests in general practice, which is a shame. Subscapularis tears get overlooked constantly because most clinicians never check for them. I started routinely adding the ER lag sign after a patient kept failing rotator cuff rehabilitation and we eventually found a missed isolated subscapularis tear on MRI. The lift-off test is the classic subscapularis screen. The patient places the dorsum of their hand against the lower back and tries to lift it away from the spine. Inability to do so suggests subscapularis involvement. It has moderate sensitivity but good specificity. The limitation is body habitus. Larger patients or those with limited thoracic extension simply cannot get their hand into position regardless of tendon integrity. When that happens, switch to the belly-press test, which has better sensitivity for detecting subscapularis pathology in heavier builds.
Get the Full Details

Labral Tests
The O'Brien active compression test targets the superior labrum and SLAP lesions. The patient flexes the shoulder to 90 degrees and adducts it 10 to 15 degrees with the thumb pointing down. You apply downward pressure while they resist. Then you repeat with the palm up. More pain with the thumb down versus palm up is a positive result. Sensitivity sits around 80 percent but specificity is only about 40 percent. You will get a lot of false positives, particularly from acromioclavicular joint irritation. I learned this the hard way with a patient who had a markedly positive O'Brien but no labral pathology on MRI. The AC joint was arthritic. Adding a cross-body adduction test to the workup helped separate the source of pain. The crank test combines compression, rotation, and abduction of the shoulder to reproduce labral symptoms. You compress the humeral head into the glenoid while slowly moving the arm through circumduction. A catching or clicking sensation with pain is considered positive. This test has low reliability between examiners, which is worth noting. One clinician might call it positive while another calls it negative on the same patient. I rarely rely on it as a standalone finding. It's useful as a contextual piece when the history strongly suggests a labral injury and other tests align. The relocation test, sometimes called the jobe relocation test, is paired with the anterior apprehension test. You first assess for anterior shoulder instability by externally rotating the arm with the shoulder in slight abduction. If the patient shows apprehension, you then apply a posteriorly directed force on the humeral head. Relief of that apprehensive feeling indicates a positive relocation sign. This is more specific than the apprehension test alone. The combination of a positive apprehension and a positive relocation test gives you higher confidence for anterior instability than either test by itself.
Instability Tests
The anterior drawer test assesses glenohumeral laxity. With the patient supine and the shoulder abducted to 45 degrees, you pull the humeral head anteriorly while stabilizing the scapula. Increased translation compared to the contralateral side suggests anterior instability. The problem is that general ligamentous laxity skews results dramatically. About 15 to 20 percent of the population has inherent multi-directional laxity, and those people will test positive on almost every instability maneuver without actually being unstable in a pathological sense. I always compare to the asymptomatic side and factor in whether the patient has generalized hypermobility before calling a finding clinically significant. The sulcus sign evaluates inferior laxity. You pull the arm inferiorly while the patient is seated or standing and look for a visible gap between the acromion and the humeral head. A positive sulcus sign indicates inferior labral or capsular laxity. It correlates poorly with true multidirectional instability unless the translation is marked, more than two centimeters. Mild sulcus signs are so common in asymptomatic individuals that they have little diagnostic value on their own.
Tension Tests and Scapular Dyskinesis
The shoulder retraction test, also called the bear hug test, assesses the long head of the biceps. The patient crosses their arm across the chest and hugs the opposite shoulder while you resist. Pain over the bicipital groove is a positive finding. Biceps pathology is frequently missed when clinicians focus only on rotator cuff and labrum. I routinely include this because isolated bicipital tenosynovitis can mimic rotator cuff impingement and responds to a completely different treatment pathway. Scapular dyskinesis assessment is not a single special test but a functional observation that matters enormously. You watch the patient perform repeated shoulder flexion and note scapular positioning and motion patterns. Wingning, altered rhythm, or asymmetric movement suggests underlying muscular imbalance or nerve dysfunction. This is where I catch problems that show up nowhere in the passive stress tests. A patient with a normal MRI, negative impingement tests, and persistent shoulder pain might have significant serratus anterior weakness driving their symptoms. Strengthening the scapular stabilizers resolved their pain in six weeks where passive modalities did nothing.

Putting It Together
No single test diagnoses shoulder pathology reliably. The best you can do is build a probability based on the cluster of findings, the history, and the mechanism of injury. A positive Neer and Hawkins with a weak empty can in a 55-year-old with overhead work points strongly toward rotator cuff tendinopathy with possible impingement. A positive O'Brien and crank test in a young throwing athlete with catching symptoms points toward a SLAP lesion. But the MRI confirmation rate from these tests alone hovers around 60 to 70 percent depending on the condition being assessed. Image-guided injection can serve as both diagnostic and therapeutic. If a subacromial injection of local anesthetic eliminates pain during impingement testing, you have much stronger evidence for subacromial pathology than test clusters alone. I use this approach when the clinical picture is ambiguous and the patient is considering intervention. It takes five minutes and changes the management plan more often than you'd expect. The limitations of these tests are real. Inter-examiner reliability for most shoulder special tests falls in the fair to moderate range, with kappa values typically between 0.4 and 0.6. This means two clinicians can reasonably examine the same patient and arrive at different conclusions. Training level, experience, and even the patient's pain tolerance influence results more than people admit. That doesn't make the tests useless. It means you should report findings probabilistically rather than definitively. A positive drop arm test in the right clinical context carries more weight than the same positive result in isolation.
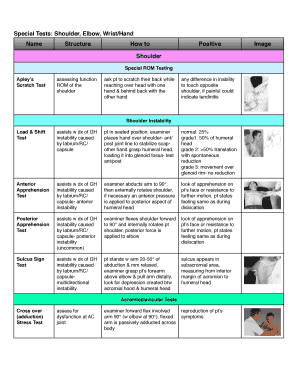
If you want a reference sheet to carry in the clinic, there are several freely available PDF versions of the Special Tests Shoulder Exam compiled by sports medicine and orthopedic groups. Search for "shoulder special tests quick reference PDF" from sources like the American Academy of Orthopaedic Surgeons or university sports medicine departments. Most are one-page laminated summaries listing the test name, structure assessed, procedure, and interpretation. Useful for quick review, not a substitute for understanding what you're actually looking for when you perform each maneuver.