Getting Past The Basics In Rehab Work
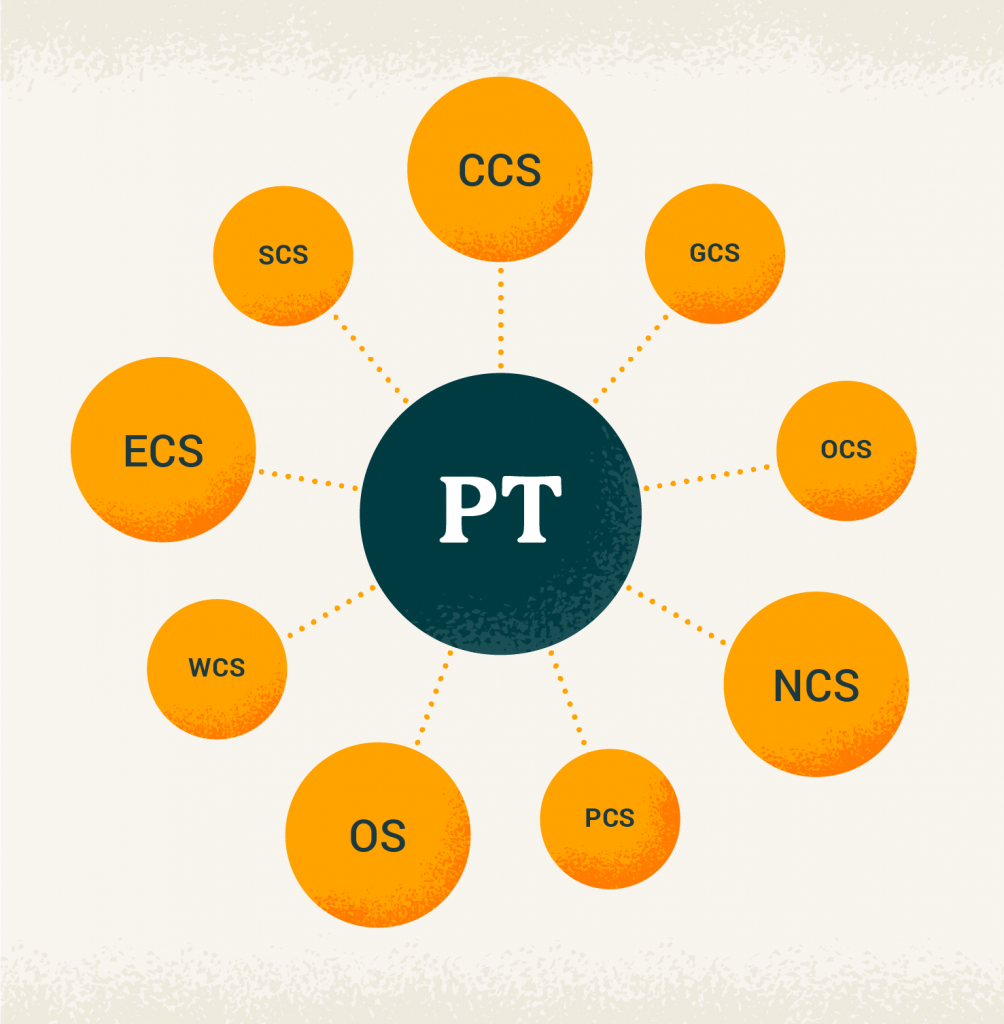
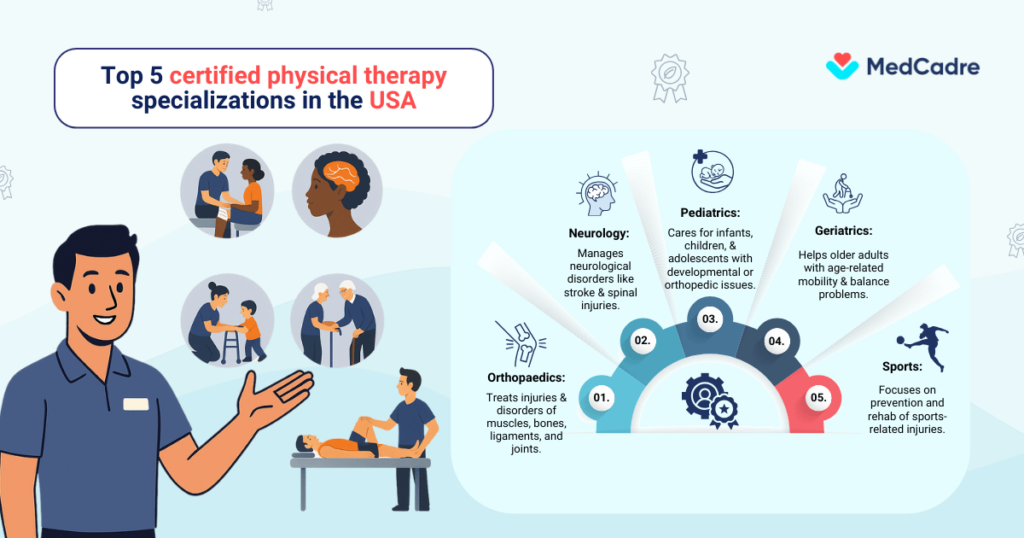
Most people thinking about physical therapy specialties see a list of six or seven options and assume the work is the same across all of them. It isn't. I spent years watching newer clinicians get handed a patient in sports and then quietly struggling because they were trying to rehab a knee the same way they'd rehab a lower back. The techniques, the timelines, the referral patterns, the insurance authorizations — they shift depending on which specialty you end up in. I learned that by making the mistake once and then fixing my approach. The official board certification path runs through the American Board of Physical Therapy Specialties. There are seven recognized areas right now: clinical electrophysiology and electrodiagnostic medicine, geriatrics, neurology, oncology, orthopedics, pediatrics, and sports. Each one has its own exam, a set number of direct patient care hours, and continuing education requirements. You don't just declare a specialty. You log hours, study for a separate exam, and maintain certification with ongoing CEUs. That process typically takes between two and four years after you pass the NPTE, depending on how many patient encounters you can accumulate in your first few years of practice. Here's what nobody tells you early on: the certification matters more in some settings than others. A hospital system hiring for an inpatient neuro program will care a lot about your neurology board certification. A private sports clinic might not ask for the credential at all and instead judge you on your clinical experience and patient outcomes. Knowing where you want to practice should come before picking a specialty, not after.
I ran into a specific problem with the sports specialty pathway that most people don't expect. I was tracking hours for a soccer player recovering from a Lachman-positive ACL reconstruction, and I had to document the exact manual grading scale, the instrumented testing if available, the return-to-sport criteria I used, and the phase-specific exercise progressions. The Board-certified Sports Clinical Specialist exam expects you to reference specific testing protocols like the IKDC score, the Tegner activity scale, and the FIFA 11+ program as part of your clinical decision-making. If your documentation doesn't show that level of specificity, you'll lose credit for those patient encounters when the board reviews your application. I learned this the hard way after losing about 40 hours of patient time because my notes said "progressed to single-leg squats" instead of "progressed to 60 degrees of knee flexion single-leg squat with contralateral hip abduction neutral on the affected side, per Brinkmann protocol phase 3 criteria." I changed my documentation template immediately and started cross-referencing each note against the ABCPTS patient contact log requirements. It added maybe three minutes per note but saved me from another rejection.
Breaking Down The Major Practice Areas
Orthopedics is the largest specialty by far. Roughly 60 to 70 percent of board-certified clinical specialists in the US hold the OCS credential. That means more competition for those certifications, but also more mentorship opportunities and more established pathways into the work. If you're in outpatient musculoskeletal practice, the OCS is essentially table stakes at many clinics. The exam itself covers differential diagnosis, diagnostic testing, pharmacology, and management across the full spine and extremity spectrum. You need at least 2,000 hours of direct orthopedic patient care, 110 of which must be in hands-on manual therapy. Pediatrics is the smallest of the seven specialties. You need 2,000 hours with patients from birth through 21 years old, and at least half of those hours need to be in direct patient care that's not supervisory. The work is completely different from adult outpatient. You're dealing with cerebral palsy, developmental delay, torticollis, post-surgical repair for clubfoot, and a range of genetic conditions. The exam tests pediatric-specific milestones, growth parameters, family-centered care models, and the legal frameworks around consent and guardianship. One counter-intuitive thing about pediatrics: your documentation needs to be extremely precise about developmental norms. Saying a 14-month-old "is meeting milestones" is not enough. You need to specify whether they're cruising, pulling to stand, or walking independently, and reference the Denver II or similar screening tool if you used one. Neurology covers stroke, traumatic brain injury, spinal cord injury, Parkinson's, MS, and peripheral neuropathies. The patient care hour requirement is the same 2,000 hours, but the clinical work demands a different kind of familiarity. You need to read neuro exams, understand Upper Motor Neuron versus Lower Motor Neuron patterns cold, and be comfortable with gait analysis using tools like the GAITRite system or even basic visual observation with timing. A pitfall I see constantly: new neuro PTs will focus too much on impairment-level interventions and forget to address participation-level outcomes. The NBCPT neurology exam will test you on community reintegration, fall risk in the home, and caregiver training. If your study plan only covers muscle length and strength, you'll fail sections you thought were easy.
Get the Full Details

Geriatrics is another area where the work is often misunderstood. People think it's just fall prevention and balance training. It's broader than that. You're managing patients with multiple comorbidities, polypharmacy interactions, advanced osteoarthritis, post-hip fracture recovery, and cognitive decline. The certification requires 2,000 hours with patients 65 and older. A practical insight here: the geriatric exam places heavy emphasis on medication review and recognizing drug side effects that affect mobility. Beta-blockers masking tachycardia during exercise, diuretics causing orthostatic hypotension, anticholinergics affecting balance — you need to know these at a clinical level, not just a memorization level. I've seen clinicians fail the geriatric exam section on pharmacology because they studied the disease processes but skipped the drug interaction chapter. Oncology PT is probably the most niche and least understood specialty. You're working with patients undergoing chemotherapy, radiation, post-surgical cancer recovery, lymphedema management, and fatigue related to cancer treatment. The certification requires 2,000 hours, and lymphedema certification or equivalent training is often expected. The work involves understanding tumor markers, surgical procedures specific to cancer types, and how treatment side effects like neuropathy from taxanes or cardiopulmonary limitation from doxorubicin change your exercise prescription. A common mistake: oncology PTs who treat post-mastectomy patients without formal lymphedema training can cause real harm. If you're in this specialty, get the certification in manual lymphatic drainage or work under a certified therapist until you are. Clinical electrophysiology and electrodiagnostic medicine is the most technical specialty. You're doing nerve conduction studies, EMG, evoked potentials, and autonomic testing. This path usually requires additional training beyond the DPT, often through a residency or fellowship program. The Board certification exam covers anatomy, physiology, pathology, and instrumentation in depth. Most people entering this field already work in neurology or physiatry and move into this as a sub-specialization. It's not something you pick up casually while working in outpatient ortho.
How To Actually Choose And Prepare
The decision about which specialty to pursue usually comes down to three factors: where you work, what patients you see most, and where the job market rewards the credential. If your clinic sees mostly orthopedic cases, the OCS makes sense. If you're in a pediatric hospital, the PCS is the path. If you're in a nursing facility, the GCS is valuable. Trying to get a sports certification when you've never worked with athletes is possible but inefficient. You'll spend more time hunting for the right patient population to log hours than you would just starting in the specialty that matches your current caseload. For exam preparation, the most reliable resources are the ABCPTS content outlines for each specialty, the relevant textbook from the APTA press, and question banks built around the exam blueprints. Don't rely solely on third-party review courses. They're useful, but they're not the primary source. The exam is written by clinicians in each specialty, and the questions reflect actual clinical decision-making, not just facts. I spent about eight to ten weeks studying for my specialty exam while working full-time, dedicating roughly two hours per night and six to eight hours on weekends. That timeline worked for me. Some people need longer. The key is consistent exposure to the material, not cramming. Documenting patient care hours is where most applications stall. The ABCPTS requires specific data points for each patient encounter: date, setting, direct versus indirect time, patient population, and the intervention provided. Vague entries like "treated lower back pain patient" won't pass review. You need to note the diagnosis, the treatment type, and your direct involvement. I kept a running spreadsheet from day one of practice. It took ten minutes per week to update and prevented a massive headache when it was time to submit my application. Without it, you'll be digging through old records months later, and half of them will be incomplete.
There are real limitations to board certification that worth being honest about. It does not guarantee better patient outcomes on its own. It signals specialized knowledge and commitment, but the actual skill comes from continued practice, supervision, and reflection. Some employers don't reimburse for the exam fee or the annual maintenance costs, which can run over a thousand dollars per year across all seven specialties combined. In some states, the scope of practice for PTs is limited enough that certain specialty skills — like ordering imaging or adjusting medications — aren't part of the job regardless of certification. And in rural or underserved areas, the specialty you trained for might not have enough patient volume to justify the credential in your current role. If board certification isn't feasible for you right now, there are other ways to build specialty-level competence. Residency programs, fellowship tracks, workshop certifications like OMT or MDT, and targeted mentorship can all bridge the gap. The certification is one route, not the only route. What matters is whether you can demonstrate specialized clinical reasoning, appropriate patient selection, and measurable outcomes in your chosen area.