Understanding the Spine Numbering System
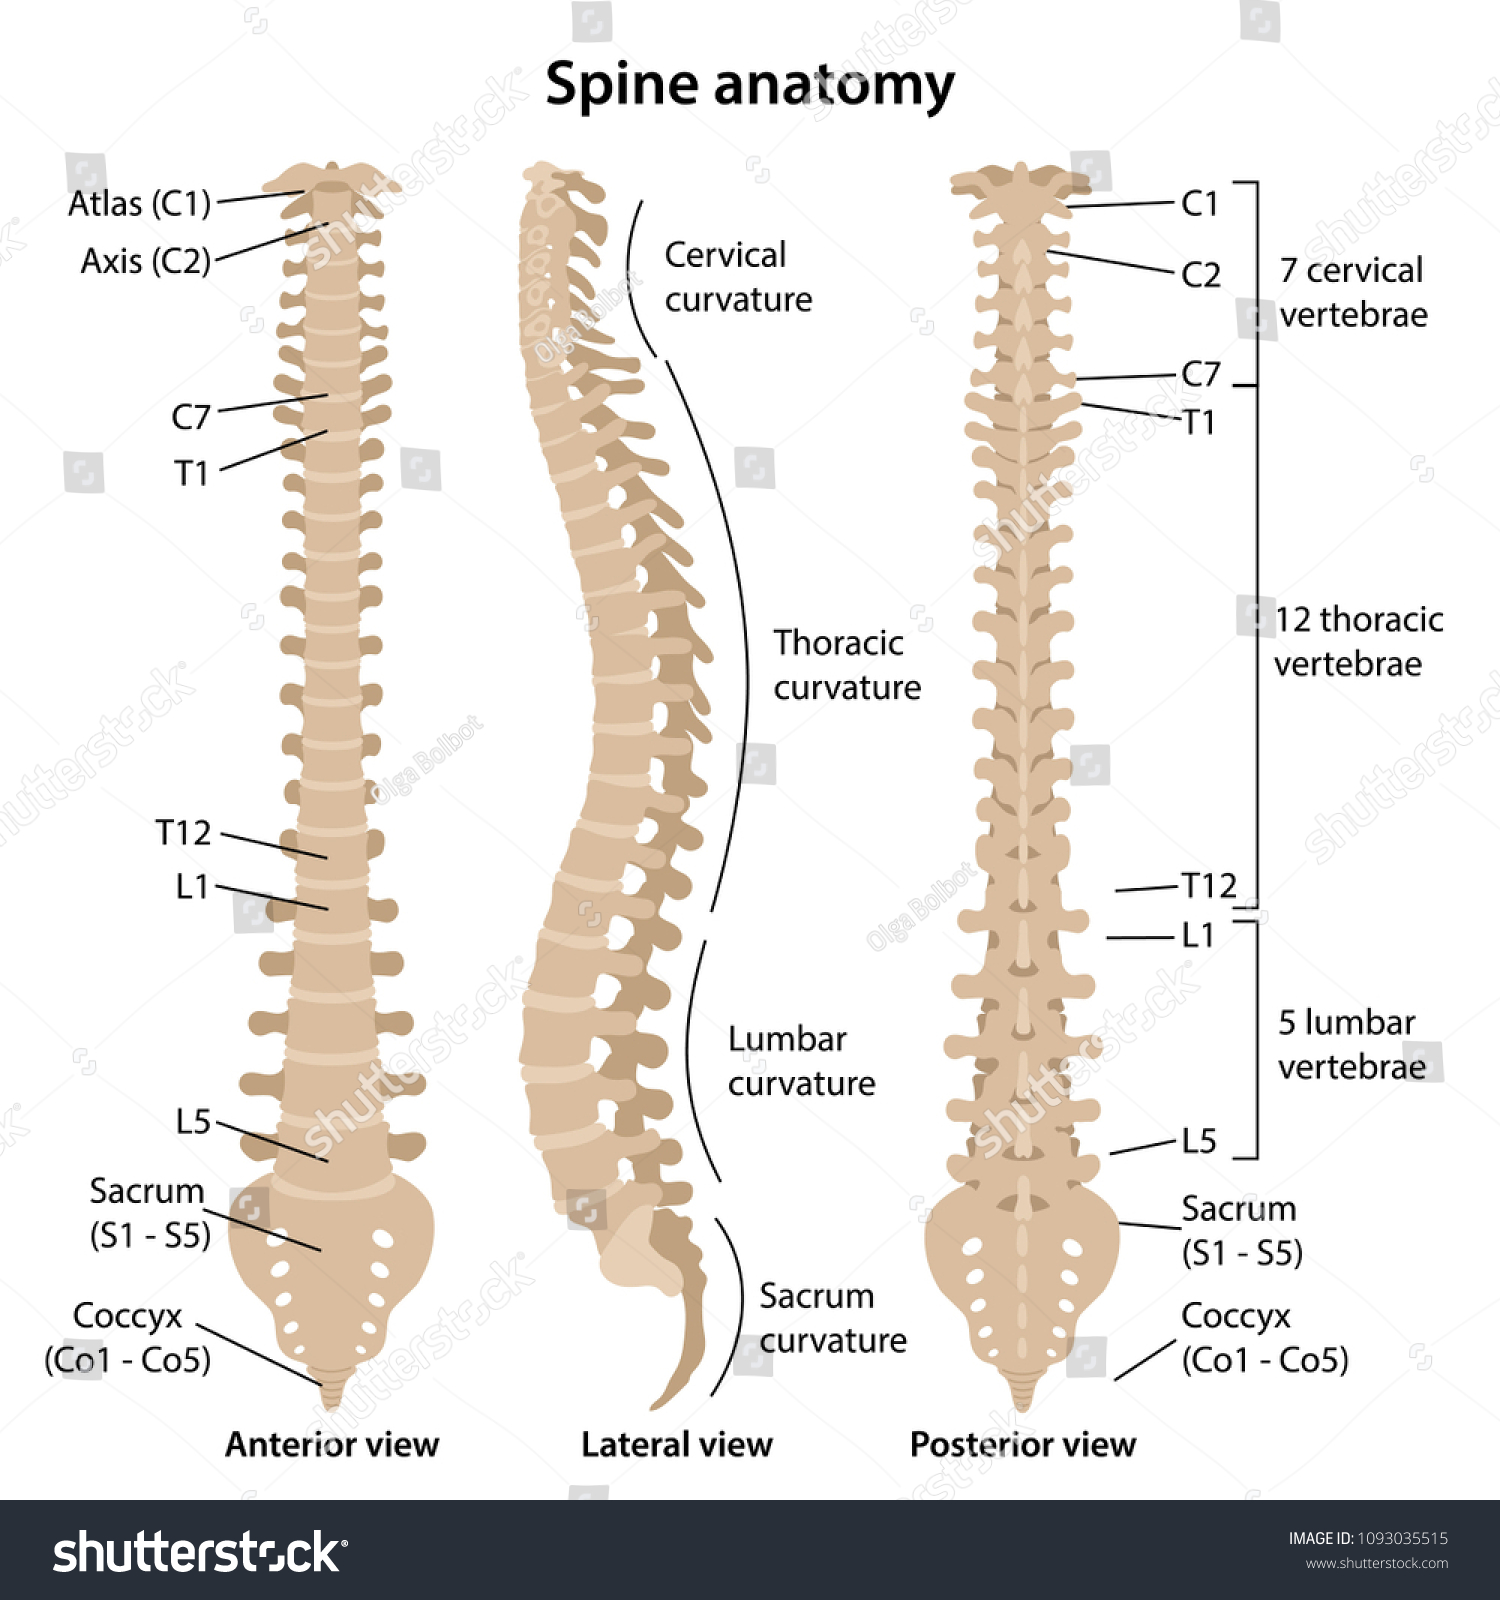
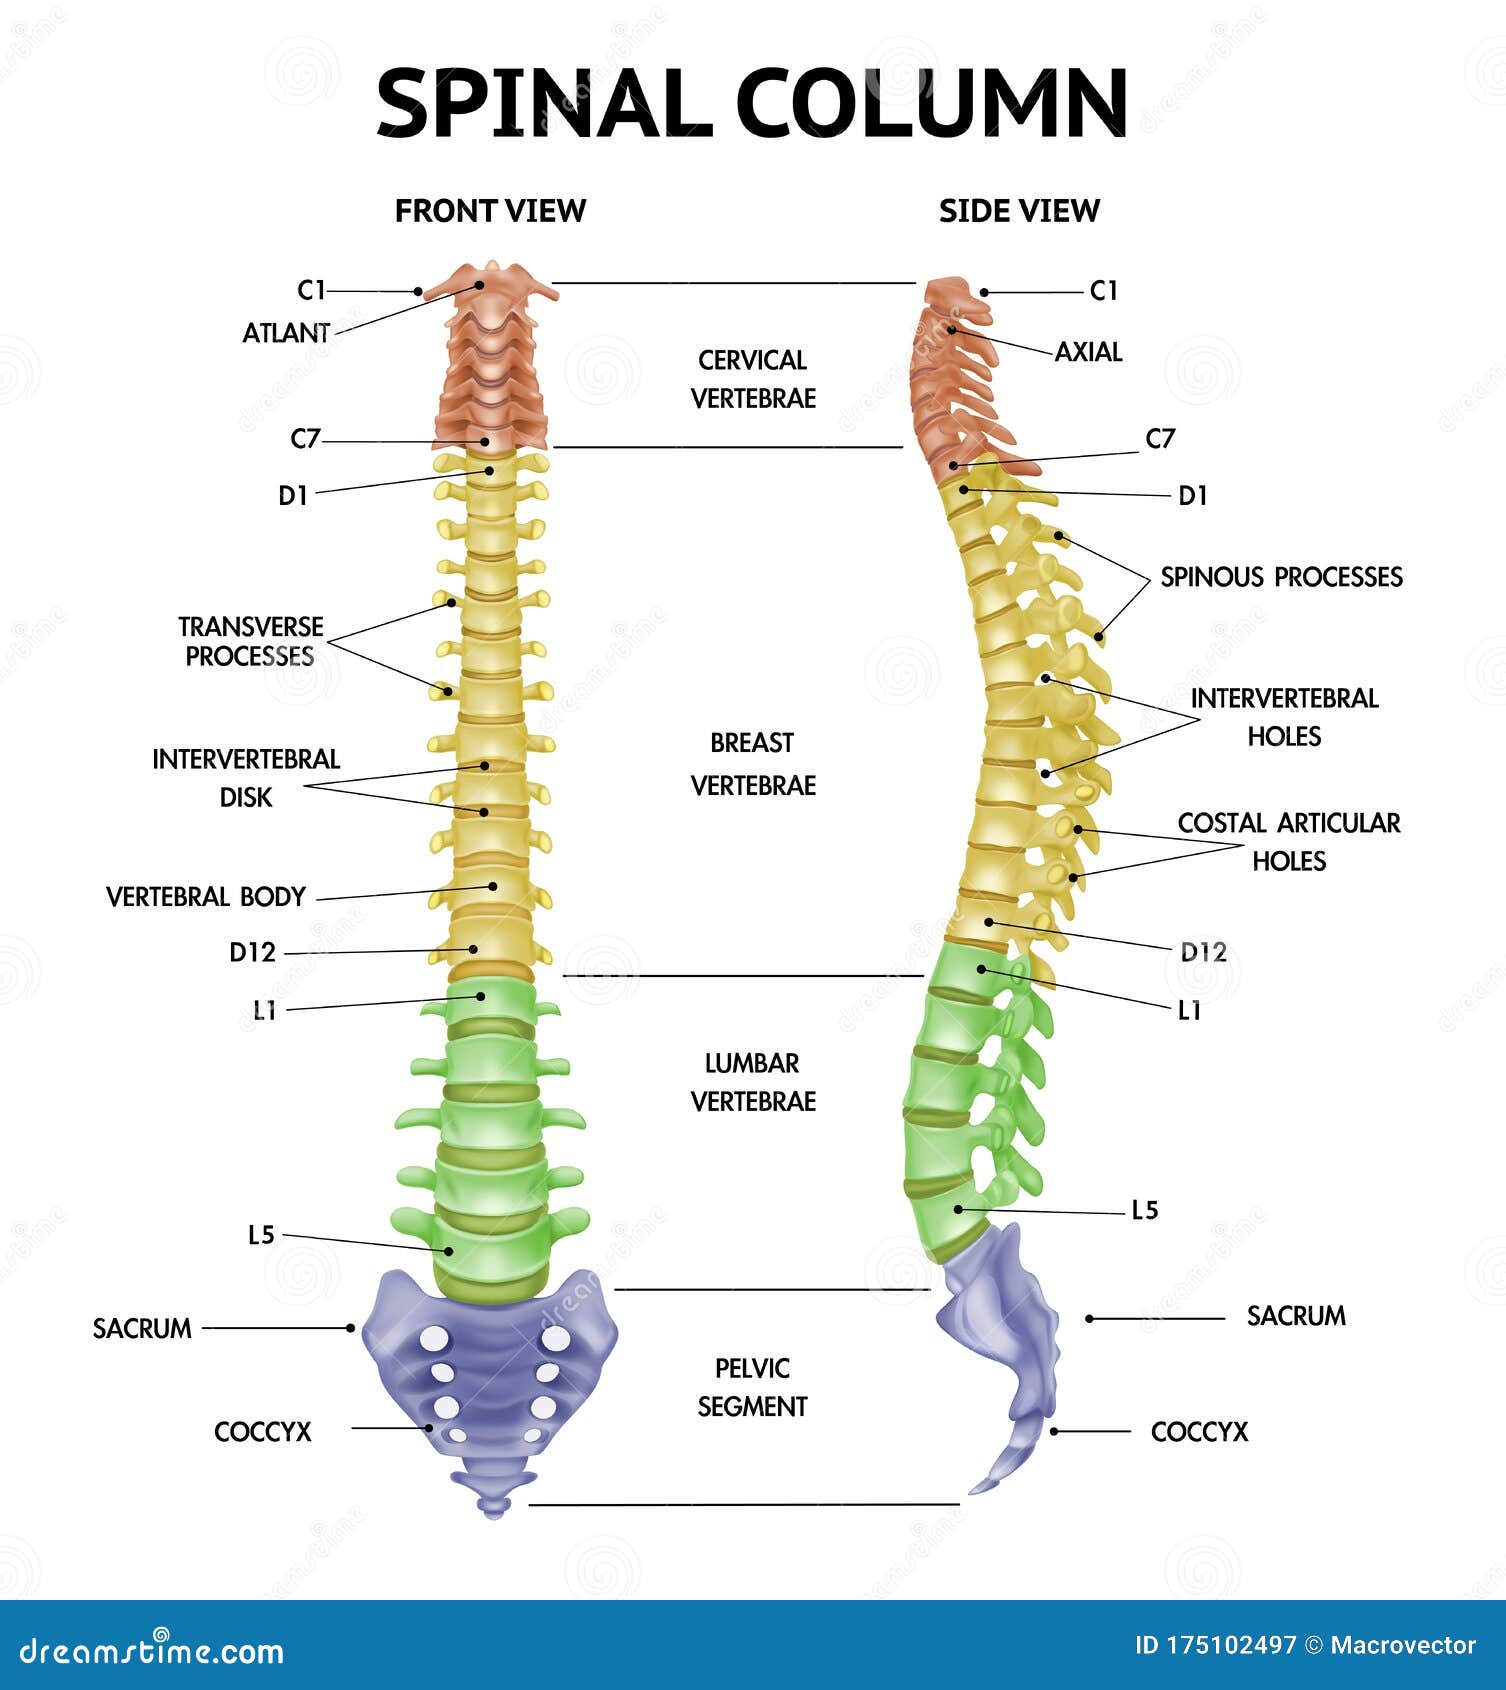
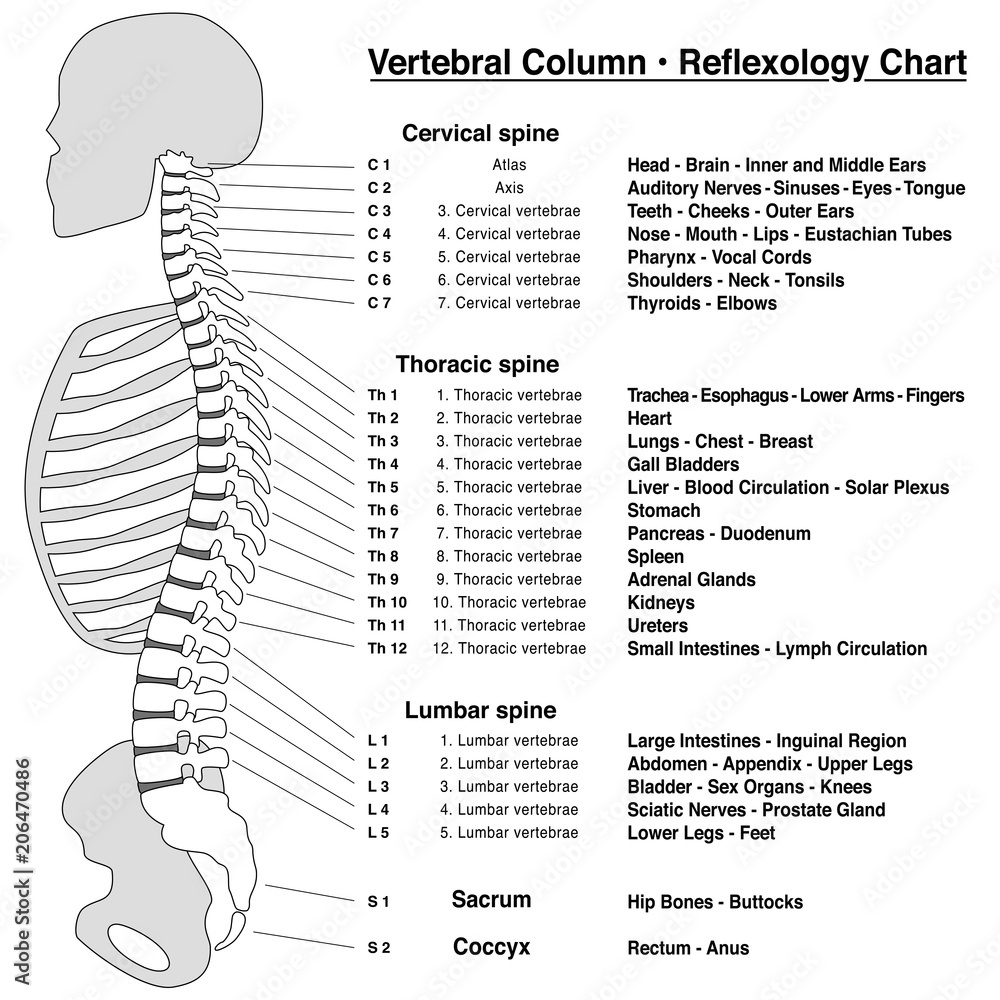
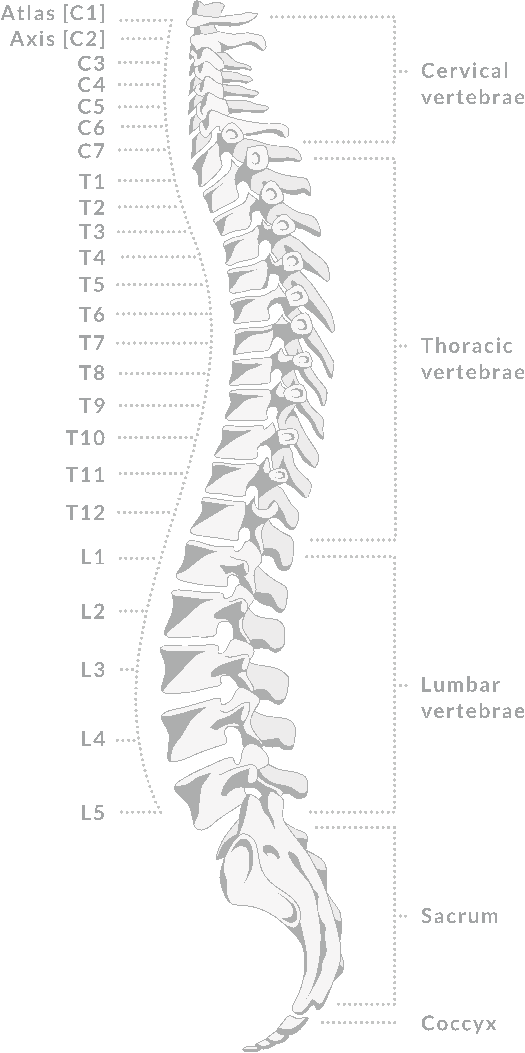
The spine has a built-in numbering scheme that most people learn in basic biology and then immediately forget after the exam. Cervical vertebrae run C1 through C7, thoracic is T1 through T12, lumbar is L1 through L5, then the sacrum and coccyx which don't use individual numbers the same way. That's the foundation. Everything else builds on knowing where you are. I've seen people spend hours trying to orient themselves on imaging studies because they never actually memorized which number corresponded to which landmark. It sounds basic but it's the single most common point of failure in clinical anatomy work. A Spine Anatomy With Numbers reference takes this and adds surface landmarks, palpable points, and cross-references to imaging so you can actually use it under pressure instead of flipping through three different textbooks.
Spine Anatomy With Numbers: What You Actually Need
Here's the thing most guides skip. The numbers alone don't help you when you're standing next to a patient or looking at an X-ray. You need to know that C7 is the vertebra prominens - the one you can feel at the base of the neck when someone bends forward. T7 sits at the level of the inferior angle of the scapula when the arms are at the sides. L4 is roughly at the level of the iliac crests, which matters because that's where you'd plan a lumbar puncture. Get those anchors wrong and everything else slides. I spent about six months working in a radiology department where we had a simplified spinal landmark chart posted at every reading station. It wasn't fancy. It showed the vertebral column with numbered levels and the key surface landmarks next to each one. What I noticed was that the people who actually used it were the residents who had already memorized the basics. The ones who were completely lost just stared at it and got more confused because they didn't have the underlying framework to hang the numbers on.
How to Use a Numbered Spine Reference in Practice
Start by learning the cervical region separately from the rest. The cervical spine has seven vertebrae but the numbering gets weird because C1 (atlas) and C2 (axis) don't look like typical vertebrae at all. C1 has no body and no spinous process - it's just a ring of bone. C2 has that odontoid process sticking up that lets your head rotate. If you try to memorize the whole spine as one continuous sequence you'll mix these up under stress. The thoracic spine is where things get predictable but also where beginners get tripped up. Twelve vertebrae, each articulating with a pair of ribs. The spinous processes angle downward significantly, which means when you're palpating from behind you're feeling the spinous process of the vertebra below, not the one at that level. I had a student once mark T6 on a patient when she was actually at T7 because she didn't account for that angulation. Took us twenty minutes to realize the mistake and reposition. For the lumbar region, the key landmark is the intercristal line connecting the top of both iliac crests. That crosses at L4 in the vast majority of adults. Sometimes it's L3, sometimes L5, but L4 is your working assumption. This matters for procedures. Puncturing at the wrong level risks hitting the spinal cord terminus, which usually ends around L1-L2 in adults. Going too high is a bad day.
Get the Full Details

Common Mistakes and How to Avoid Them
One issue I ran into repeatedly: people confuse vertebral level with spinal cord segment level. They're not the same thing. The spinal cord is shorter than the vertebral column, so the segments don't line up numerically. A T10 vertebral fracture doesn't necessarily damage the T10 spinal cord segment - it might be affecting L2 or L3 segments instead because the cord ends around L1. This distinction is critical for neurological assessment and documentation. I've seen wrong-level documentation in charts more times than I care to admit, and it's almost always this confusion. Another trap is assuming the sacrum is five separate bones. In adults it's fused into a single bone with four sacral segments. The anterior sacral foramina are still visible and correspond to nerve roots, but you won't find individual vertebral bodies between S1 and S5 unless you're looking at a pediatric specimen or someone with a rare developmental anomaly.
What a Good Reference Should Include
A solid spine anatomy reference with numbering should give you three things for each level: the bony landmarks you can feel on a living person, the corresponding surface anatomy you'd see or palpate externally, and the imaging appearance on standard X-ray and MRI views. Without all three, you're only learning one dimension of the anatomy. The version I found most useful during my time in radiology was a laminated quick-reference card that showed anterior, posterior, and lateral views of the entire column with each vertebra labeled and the key relationships noted in the margins. It fit in a lab coat pocket. The details were simplified compared to a full atlas but that was the point - when you're in a procedure you don't need every nuance, you need to know where you are right now. If you're looking to build your own reference system, start with a blank spinal column diagram and label each vertebra. Then add the surface landmarks on a second pass. Then add the imaging correlates on a third. Three separate learning cycles are more effective than trying to cram everything at once. I tracked my own progress this way and it cut my recognition time on unfamiliar imaging studies from roughly twenty minutes per case down to about four.
Where to Find a Spine Anatomy With Numbers Reference
There aren't many standalone downloadable resources that focus specifically on the numbered spine system with practical landmarks. Most anatomical atlases include the numbering but bury it under hundreds of illustrations. The Gray's Anatomy student version has a solid spinal column section with numbered diagrams if you have access. For something more practical, radiology teaching files online often have spot diagrams showing vertebral levels on X-rays with labels - those are closer to what clinicians actually use at the point of care. One resource I kept coming back to was the Radiopaedia spine articles. They don't have a single downloadable Spine Anatomy With Numbers document, but their vertebra articles are numbered systematically and include CT, MRI, and plain film correlations. You can navigate from C1 through L5 in sequence and build your own compiled reference over time. It's not a one-click download but the information is free and accurately structured. For physical copies, the Netter Atlas remains the standard even though it's expensive. The clinical anatomy books by Mark Bowen or Snell tend to have more practical landmark integration than pure illustration collections. If you're studying for boards or clinical rotations, those are worth the investment because they force you to connect the numbers to what you'd actually encounter in a hospital.
The Limits of Any Numbered Reference
No reference system handles anatomical variation well. Scoliosis changes the entire spatial relationship of the vertebrae. Prior surgery with instrumentation makes landmark-based localization unreliable. Obesity can make surface palpation nearly impossible, especially in the thoracic and lumbar regions. I had a case where a morbidly obese patient needed a lumbar puncture and we couldn't identify the iliac crests or the midline landmarks by palpation. We ended up using fluoroscopic guidance because the textbook numbering system had no answer for that situation. Age-related degeneration is another blind spot. Disc height loss, osteophyte formation, and vertebral compression fractures shift the relationships that numbered references assume are static. An elderly patient with severe degenerative changes won't match the clean diagrams in any textbook. The numbers are still useful for orientation but you can't rely on them for precision in those cases. The bottom line is that a Spine Anatomy With Numbers system is a starting framework, not a complete guide. It gives you a coordinate system to orient yourself. Everything beyond that requires clinical experience, imaging correlation, and an understanding of when the standard model doesn't apply. Learning the numbers gets you through the first layer. Knowing when those numbers stop being reliable is what separates people who can read anatomy from people who can use it.