
So You Need to Make a Splint
I have made hundreds of splints over the years, mostly for hands and wrists. The people who actually need them don't care about theory. They care about whether it fits, whether it holds, and whether they can still grab a coffee cup while wearing it. This is what I learned doing it wrong first, then right.
Getting the Basics Right in Splinting In Occupational Therapy
Splinting In Occupational Therapy involves designing, fabricating, and fitting a supportive device to immobilize or assist a body part. It sounds straightforward on paper. It isn't. The margin between a functional splint and a complaint factory is usually two centimeters of material placement or one poorly chosen buckle location.The most common mistake I see therapists make is rushing the assessment phase. They skip joint-by-joint positioning and jump straight to cutting thermoplastic. You will save time if you measure everything twice. I typically spend 15 to 20 minutes on assessment alone for a first-time hand splint. That investment usually prevents a remold session three days later.
The Materials and Tools You Actually Need
Thermoplastic sheeting comes in different thicknesses and types. Low-temperature molding sheets are standard for hand splints. They soften around 160 to 170 degrees Fahrenheit and stay workable for about 60 seconds. High-temperature sheets require more caution and experience. Stick with low-temp until you know what you are doing.You need a hot water bath or oven. A convection oven works fine but requires close monitoring. A dedicated thermoplastic heater with adjustable temperature settings is safer. I use a water bath because it gives me more control over softening. The water should be around 175 degrees. Too cold and the material won't drape properly. Too hot and you risk burns or warping.
Other essentials include trimmers, scissors, a measuring tape, a goniometer for joint angles, and a marker. Some therapists also keep a heat gun on hand for fine adjustments. I do not recommend using heat guns for beginners. They warp material fast and cause uneven stiffening.
Get the Full Details

Step-by-Step Fabrication Process
Start with a detailed assessment. Document the target joint position, skin condition, neurovascular status, and patient goals. Write these down. I still pull out my original notes six months later when a splint needs revision and I cannot remember why I chose a particular resting angle. Next, create a template or impression. For hand splints, I often use aluminum foil on the patient's hand. It molds quickly and gives a decent baseline shape. Some therapists prefer plaster wrap for impressions. Both work. Aluminum foil is cheaper and faster. Plaster holds detail better in complex cases.Once you have your template, trace it onto the thermoplastic sheet. Add two centimeters to every edge for trimming and folding. Mark the joint line clearly. This is where beginners mess up. If your hinge point does not align with the patient's anatomical joint, the splint will create pressure points and restrict motion instead of supporting it. Heat the material in your water bath. Remove it when pliable. Do not wait until it is dripping soft. It should bend easily but still hold some shape. Place it on the patient or your model quickly. Work the material into position using your palms, not your fingertips. Fingertip pressure creates indentations that become pressure sores. Hold the joint in the prescribed position. Maintain it for 30 to 45 seconds while the material cools. Check circulation and sensation before removing the splint. Ask the patient to move through available range. They should feel support, not restriction at the wrong spots.
A Real Problem I Faced
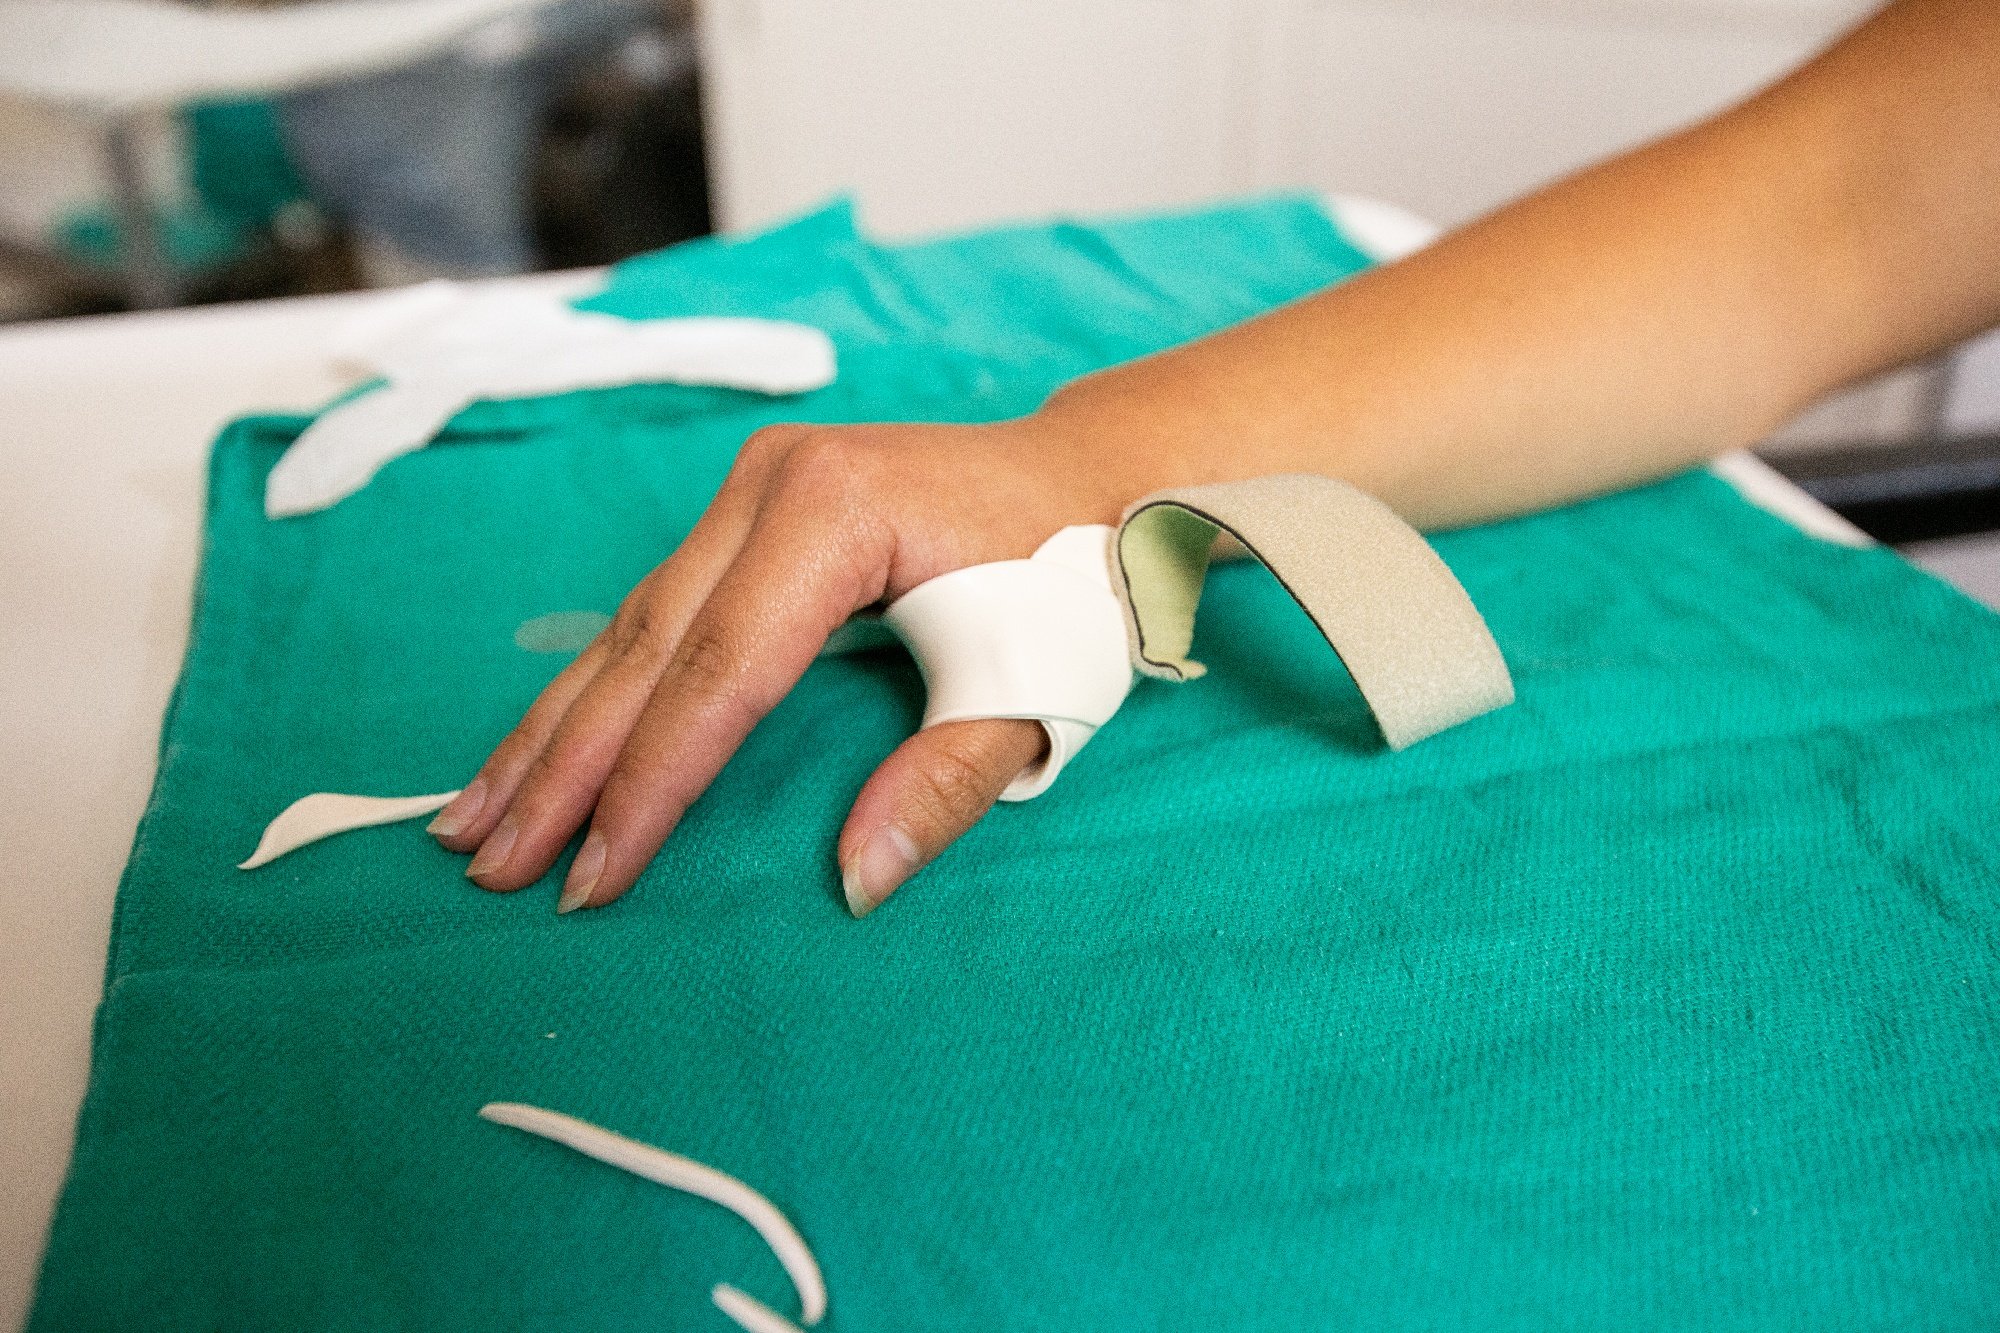
Three years ago, a patient with rheumatoid arthritis needed a rest splint for her right wrist. Standard protocol suggested a neutral position at 0 degrees. I followed that. The splint fit well initially. Two weeks later, she returned with a pressure ulcer forming at the distal radioulnar joint area. The issue was subtle. Her DRUJ had increased translation due to ligament laxity from RA. A flat dorsal splash splint pressed directly over that bony prominence with every finger movement. The workaround was simple but not obvious. I added a small cutout at the DRUJ area and reinforced the surrounding zone with an additional layer of 3mm polyester fabric backed laminate. This shifted the pressure away from the sensitive area and redistributed load across a broader surface. She wore the revised splint without issues for another eight months.Advanced Nuances Beginners Miss
One thing most introductory courses gloss over is the difference between dynamic and static splinting and when each is appropriate. Static splints maintain a position. Dynamic splints apply controlled force to encourage movement. Using a dynamic splint for acute inflammation is a common error. I once saw a therapist prototype a dynamic extension splint for a patient with active gout in the MCP joints. The controlled force aggravated the inflammation and set recovery back by weeks. Sometimes static is all you need, and pushing for dynamic motion too early causes more harm than good. Another counter-intuitive point involves material layering. More layers do not always equal better support. A single 3mm layer of polyester fabric backed laminate positioned correctly provides adequate immobilization for many conditions. Adding extra layers increases bulk, reduces comfort, and can actually impair function by limiting adjacent joint movement. The goal is minimum effective support, not maximum rigidity.Common Pitfalls and Their Fixes
Edge roughness causes skin irritation. Trim edges thoroughly and burnish them with a rounded tool or careful heat application. A sharp edge will chafe the volar crease within hours. patients remove the splint because of discomfort, not because it failed functionally. Poor strap placement is another frequent issue. Straps should cross over bony prominences, not soft tissue. A strap over the thenar eminence digs in during grip. Move it ulnarly to rest over the metacarpal shaft.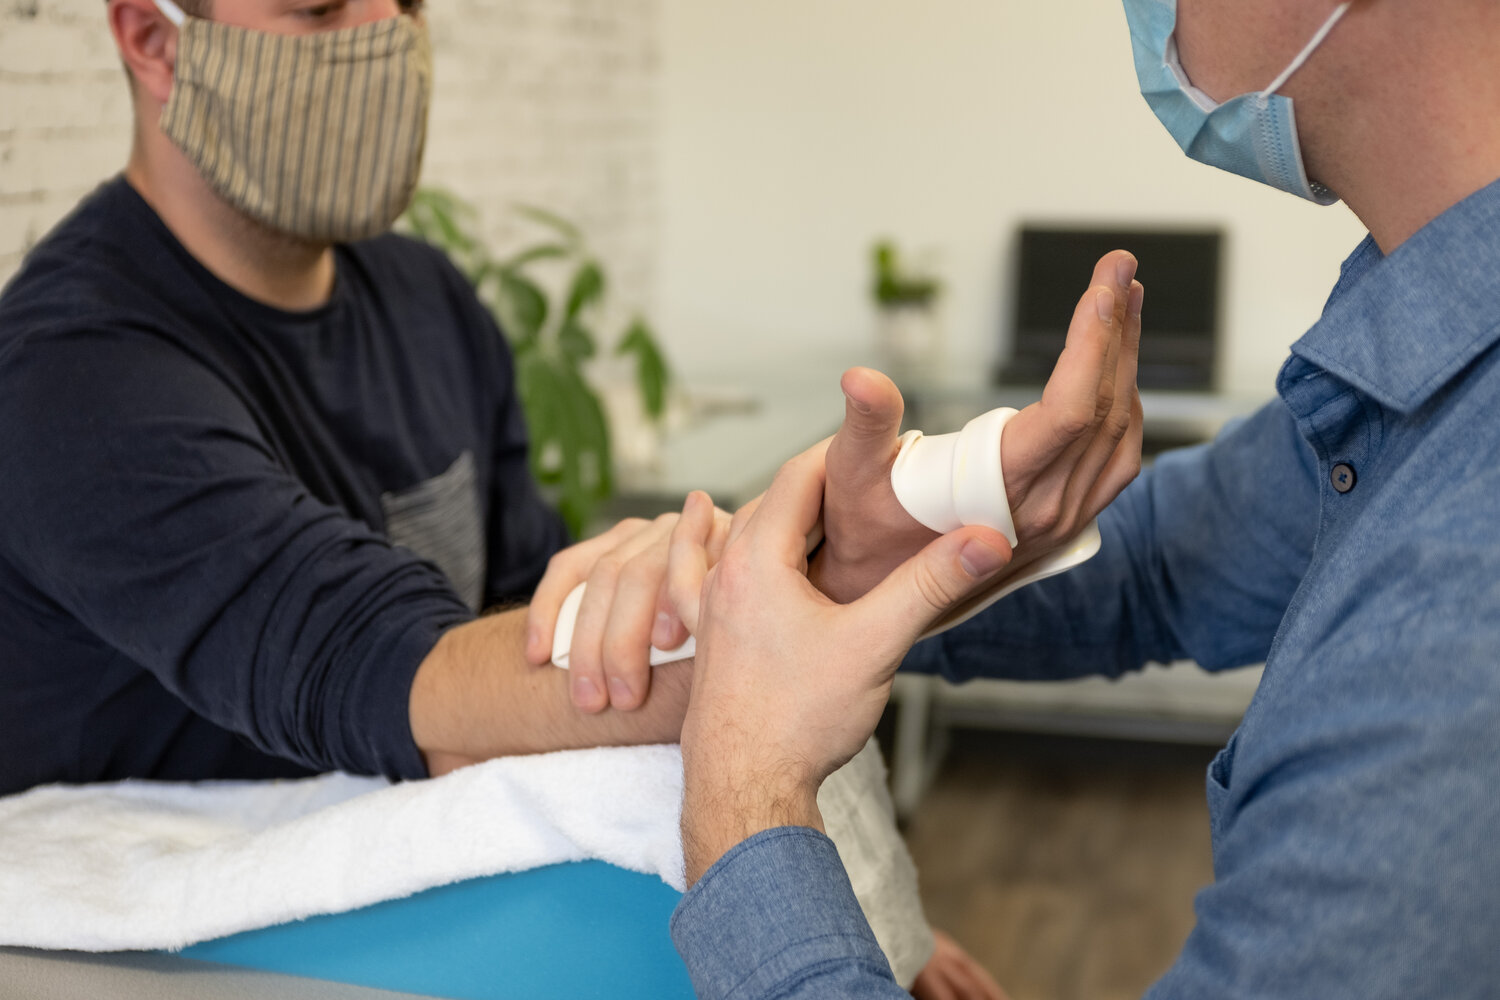
I also see therapists neglecting to educate patients on donning and doffing. A splint that fits perfectly becomes useless if the patient puts it on incorrectly. I demonstrate removal and application at least three times before the first session ends. I also write down the steps on a card they can take home.
Limitations You Should Know About
Thermoplastic splints have real limitations. They degrade over time. Heat, UV exposure, and repeated cleaning break down the material. Most splints last between 4 and 12 weeks before they lose structural integrity. You cannot assume a splint made today will perform identically in three months.They also fail in high-edema situations. If swelling changes significantly, the splint may become too tight or too loose within days. I adjust or remake splints frequently for patients with variable edema, such as those post-stroke or recovering from hand trauma. There is no workaround other than monitoring closely and being prepared to refabricate. For complex fractures or severe contractures requiring precise angular control, off-the-shelf splints or custom-molded casts may be more appropriate. Thermoplastic splints excel at functional support and mobility preservation. They are not ideal when absolute immobility is the clinical priority. Sometimes a cast is the correct choice, and insisting on a splint for the sake of patient preference is clinically unsound.
Practical Checklist Before Sending a Patient Home
Verify joint alignment. Check strap security and placement. Confirm skin integrity at all contact points. Review donning and doffing technique with the patient. Provide written care instructions including cleaning method and warning signs. Schedule a follow-up within one to two weeks for any hand splint. Earlier if the condition involves significant swelling or compromised circulation. Splinting works when the details are right. It fails when assumptions replace measurement. Take your time during fabrication and reassessment. The patient's daily function depends on the small decisions you make during those first few sessions.


