Understanding the Stages Of Tooth Development
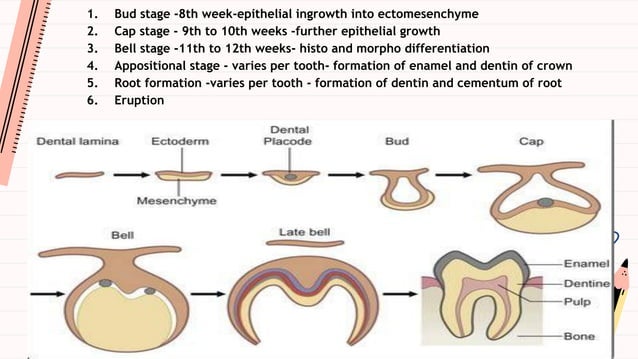
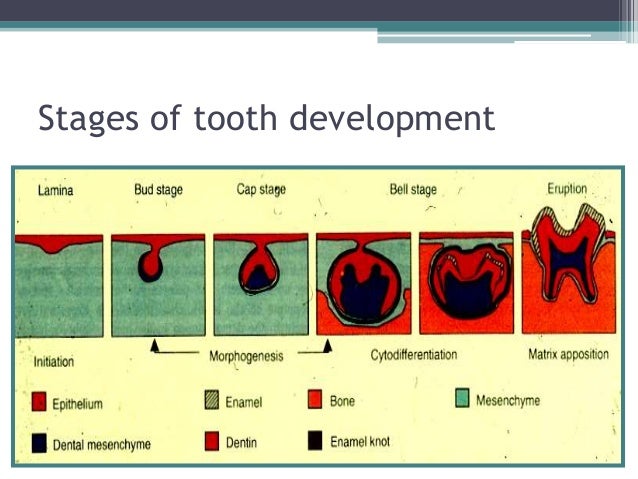
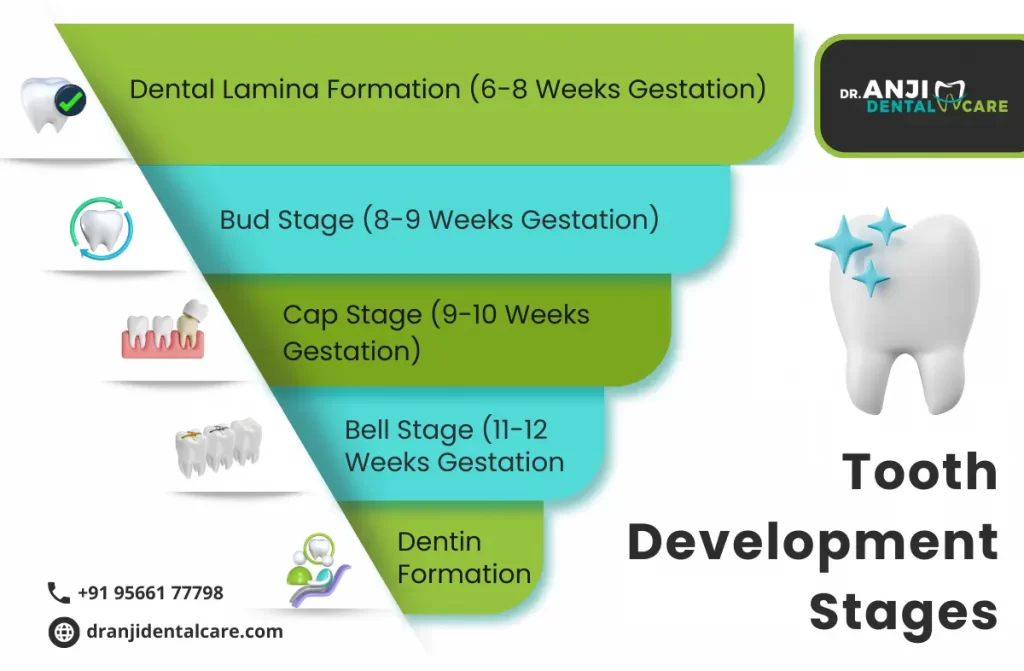
The timeline for human tooth formation is surprisingly complicated and easy to misunderstand. Most people think it starts at birth when baby teeth appear. It doesn't. The process begins around the sixth week of embryonic life, well before anyone could observe it clinically. What follows is a breakdown of the actual stages, the practical things you need to know when working with imaging or interpreting development, and where most guides get it wrong. There are four recognized phases: bud, cap, bell, and apposition. Each one takes weeks or months to complete. The bud stage is deceptively simple. It is just a cluster of epithelial cells thickening into the underlying mesenchyme. No shape exists yet. There is nothing visible on a radiograph. I spent hours trying to identify early bud-stage teeth on pediatric scans and kept confusing normal tissue densities with actual odontogenic activity. The trick is knowing what you are looking for before it becomes obvious.
The Stages Of Tooth Development in Practice
Once the bud stage progresses into the cap stage, cellular differentiation begins. The enamel organ forms a distinct cap shape over a condensed dental papilla. This is where things get technically interesting. You now have three cell populations that matter clinically: the outer enamel epithelium, the inner enamel epithelium, and the stellate reticulum in between. If you are reading histology slides, the cap stage is relatively easy to spot because of the indentation that creates the concavity. If you are reading X-rays, you still see nothing but soft tissue shadow. The bell stage is the next major transition. Here, the cells begin differentiating into ameloblasts and odontoblasts. These are the actual builders. Ameloblasts produce enamel. Odontoblasts produce dentin. The crown shape becomes determined at this point. What most people miss is that the bell stage itself has early, intermediate, and late phases. In the early bell phase, you can already predict crown morphology by looking at the outline of the epithelial dental organ. A molar looks like a molar. An incisor looks like an incisor. You do not need to wait for hard tissue to confirm what tooth is forming. Apposition is when deposition actually occurs. Dentin forms first, followed by enamel. The timing is critical and usually misunderstood. Enamel deposition follows the predentin layer. If predentin is not laid down correctly, enamel formation becomes irregular. This is a common pitfall I encounter when reviewing cases of enamel hypoplasia. The defect often originates in the dentin-predentin interface, not in the enamel-forming cells themselves. Beginners tend to blame ameloblasts for everything that goes wrong with enamel. That is not always correct.
Calcification starts in the cuspal regions of molars and at the incisal edges of anterior teeth. This is called the initiatory calcification zone. The crown completes its mineralization before the root begins to form. Root development is a separate sequence involving the Hertwig epithelial root sheath. That is a different discussion. The point here is that crown and root stages are not synchronized. A tooth can look fully formed on a radiograph with no root present. This happens frequently in trauma cases where the crown calcified normally but root formation was interrupted. One specific problem I dealt with recently involved a six-year-old patient with delayed eruption of the permanent first molars. The panoramic radiograph showed no visible root formation on those teeth. Everyone assumed the teeth were absent. They were not. The bell stage had completed but apposition had been significantly delayed, likely due to a localized infection from the overlying primary molar. The workaround was straightforward: remove the source of infection, monitor for six months, and reassess. The molars erupted on their own once the inflammatory process was resolved. Extraction was never needed. This kind of case proves that radiographic appearance alone can be misleading during the later stages of development.
Get the Full Details
Common Misconceptions and Clinical Nuances
Many dental students learn the stages as a neat sequence: bud, cap, bell, apposition, calcification, eruption. In reality, these stages overlap significantly and proceed at different rates depending on which tooth is developing. The first molar begins calcification at birth. The second molar begins around age four. The third molar may not start until age seven or later. A single radiograph of a child can show teeth at completely different developmental stages side by side. This is normal. It is also easy to misinterpret if you assume uniform timing across the dentition. Another nuance that is rarely covered adequately is the role of the dental follicle. This sac of connective tissue surrounds the developing tooth and plays an active role in resorbing overlying bone to facilitate eruption. If the follicle becomes inflamed or cystic, eruption can be blocked entirely. I have seen cases where a dentigerous cyst formed around an unerupted canine simply because of chronic follicular irritation. The tooth itself was developmentally normal. The problem was entirely extrinsic. Removing the cyst and preserving the tooth was possible in those cases, but only if the diagnosis was made early enough. Timing estimates vary by population and genetics. There is no universal standard that applies to every patient. The Demirjian method is one of the more widely used scoring systems for dental age estimation, but it was developed on a Quebec population and tends to overestimate dental age in other groups. If you are using it clinically, adjust for your patient's demographic background. Otherwise, the numbers will be off by roughly six to twelve months, which matters when you are making treatment decisions based on developmental timing.
Pathology can alter the normal progression of any stage. Systemic illness during the bell or apposition phase can cause developmental enamel defects known as milk teeth or lines of Retzius. These are permanent markers of disruption. Fluorosis, trauma, and certain medications can similarly interrupt mineralization. The damage is done at the time of the insult. No amount of corrective treatment afterward can restore the affected structure. Prevention during the developmental window is the only real solution, and that is mostly outside the control of dental clinicians.
What the Literature Gets Wrong
Textbooks present the stages in isolation. They describe the bud stage here, the cap stage there, and move on. What they do not emphasize is that transition between stages is not abrupt. There is no moment when a bud suddenly becomes a cap. It is a continuous gradient of morphological change. Same for cap to bell. The boundaries are arbitrary conveniences for teaching purposes. When you look at actual serial sections or high-resolution micro-CT data, the transitions are gradual and overlapping. Understanding this prevents you from forcing observations into neat categories that do not exist in biological reality. Another widespread error is the implication that all teeth within a dentition develop simultaneously. They do not. Within a single arch, different teeth can be several weeks or even months apart in their developmental stage. In a seven-year-old child, you might find the mandibular incisors in the late bell stage, the canines in early apposition, and the second molars just completing crown formation. All of this coexists. Radiographic interpretation requires you to account for this asynchronous development rather than treating the dentition as a uniform unit. The eruption sequence is also not part of the morphological stages but is closely linked to them. A tooth must complete crown formation and begin root development before eruption mechanisms can engage. Root length matters more than most people realize. A premolar with a root tip that is only one-third formed will not erupt on schedule even if the crown looks fully developed. This is a common source of confusion in orthodontic treatment planning. Extracting a tooth with incomplete root formation can lead to unexpected movement patterns because the anchorage value is different than expected.

Practical Considerations for Clinical and Academic Work
If you are studying histology, invest time in serial sectioning. A single slice through a developing tooth tells you very little. You need to see the progression across multiple sections to understand the three-dimensional changes. I used to rely heavily on textbook images. They are clean and simplified. Real tissue is messy and asymmetric. The actual samples I worked with in the lab rarely looked like the perfect illustrations. Accepting that variability is part of learning the material. For radiographic interpretation, use a combination of imaging modalities when possible. Panoramic radiographs give you an overview but lack detail. Periapical films provide better resolution for individual teeth. Cone-beam CT is overkill for routine assessment but invaluable when you need to see three-dimensional relationships, such as ectopic eruption paths or cyst formation around developing teeth. The radiation dose is higher, so reserve it for cases where the information genuinely changes management. When documenting developmental stages in patient records, use standardized nomenclature. The Norah and Ashcroft system or the Demirjian scoring method both work, but pick one and apply it consistently. Mixing systems in the same chart creates confusion. I have seen charts where one clinician used chronological age notation and another used developmental stage notation without any clarification. It makes follow-up analysis nearly impossible.
The biggest limitation in this field is the difficulty of direct observation. You cannot stage living tooth development non-invasively with high precision. Radiographic methods are indirect and rely on mineral density thresholds that vary between individuals. Histological staging requires extraction or biopsy, which is ethically problematic for developing teeth in living patients. Most of our detailed understanding comes from postmortem studies or animal models. This means clinical application often involves extrapolation from data that was never collected from the patients you are treating. Be aware of that gap when making diagnostic or prognostic statements. There is also the issue of individual variation that no staging system fully accounts for. Some children develop teeth months ahead of schedule. Others fall behind. Genetics, nutrition, systemic health, and local factors all play roles. The stages describe a general framework, not a rigid timetable. Using them as absolute benchmarks without considering the individual patient leads to incorrect conclusions about developmental delay or acceleration. The framework is useful, but it is not a substitute for clinical judgment.