What You Need to Know About Standardized Assessment For Tbi
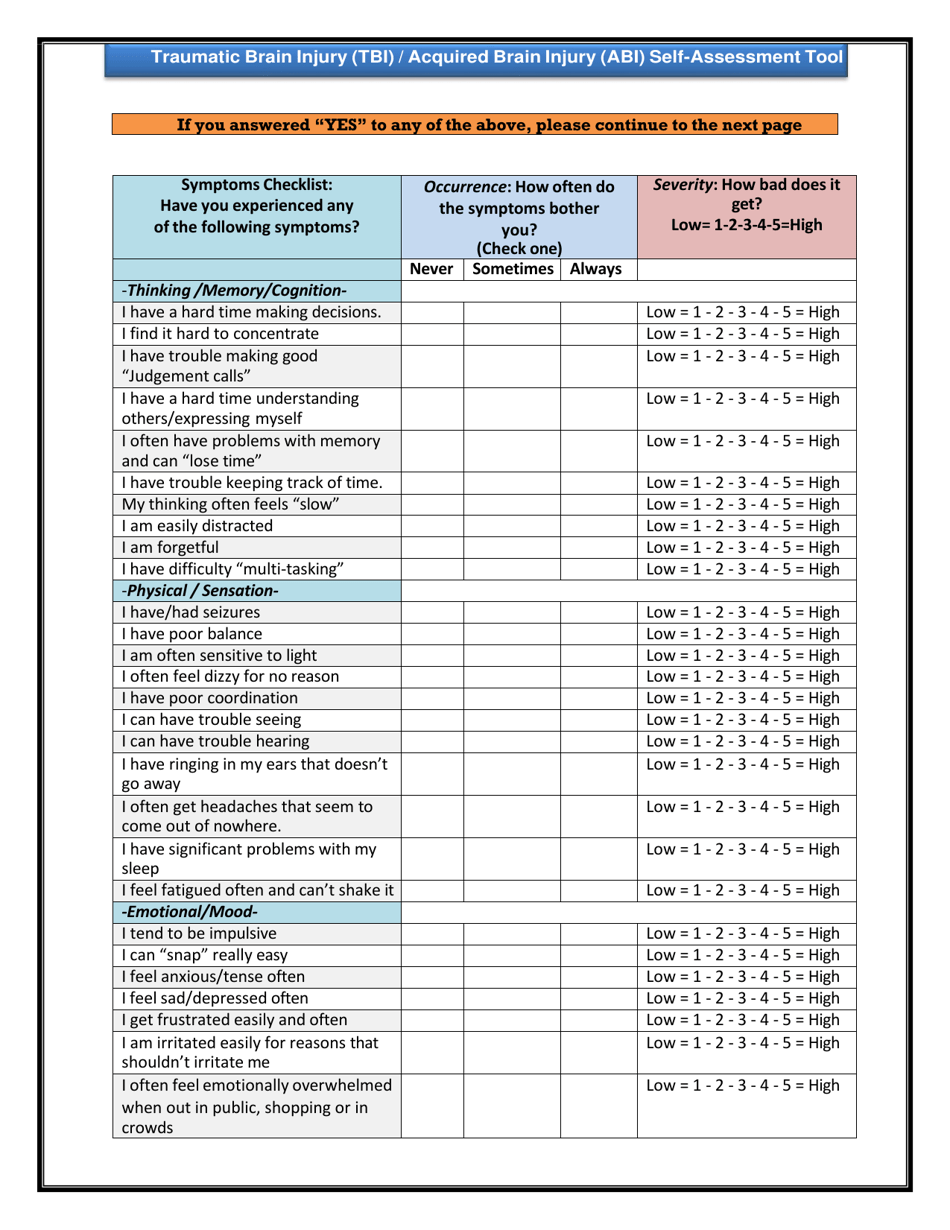
Standardized Assessment For Tbi is a framework that clinicians and researchers use to measure cognitive, emotional, and physical functioning after a traumatic brain injury. It is not one single test. It is a collection of instruments designed to produce comparable data across patients, time points, and study sites. The goal is consistency, not convenience. I have spent years administering these tools in clinical and research settings. The theory looks clean on paper. In practice, things get messy fast. People with TBI often cannot complete protocols as written. Fatigue, attention deficits, and medication effects throw off results in ways that standardized manuals do not always account for. You learn to adapt while keeping the core data as usable as possible.
The Role of Standardized Assessment For Tbi in Clinical Practice
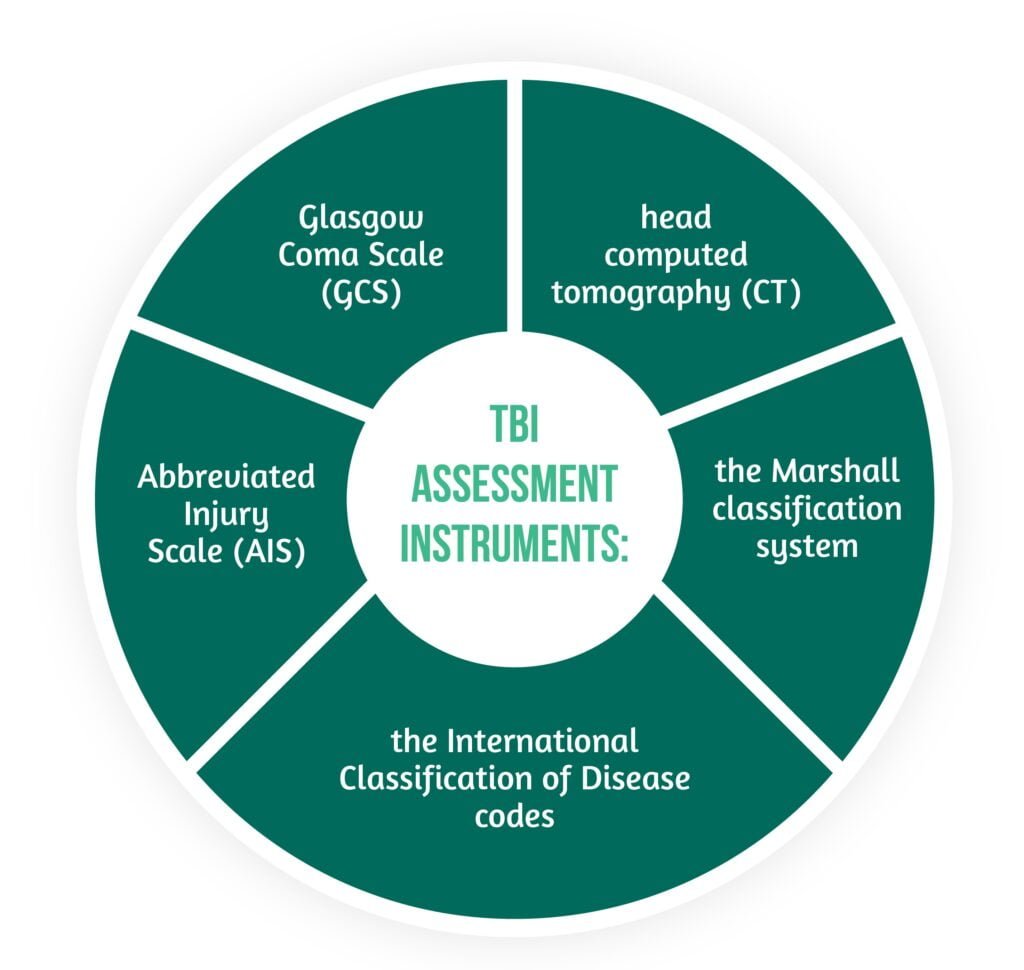
The most commonly used instruments fall into a few categories. Cognitive screening tools include the MoCA and the RBANS. Functional assessment measures include the FIM and the GOIS. Neuropsychological batteries like the NIH Toolbox or CNS Vital Signs give deeper profiles but require more time and training. Each serves a different purpose. Screening tools catch broad deficits. Detailed batteries map specific domains. Functional measures track real-world recovery. One thing people misunderstand is how much baseline data matters. Without a pre-injury reference, post-injury scores are much harder to interpret. A MoCA score of 24 means something very different for someone who tested at 30 before the injury than for someone who scored 24 a year earlier. I have seen cases where mild cognitive changes were missed because no prior assessment existed for comparison. The data looked normal in isolation. It was abnormal compared to the patient's own history. Timing is another factor that gets overlooked. Acute phase assessments, usually within the first week, tend to underestimate true impairment. Swelling, medications, and sedation suppress performance. Repeat testing at three months and twelve months gives a clearer picture. I have watched scores shift significantly between the one-month and three-month mark as patients recover enough to perform closer to their actual capacity. Early scores should never be treated as final.
Common Instruments and What They Actually Measure
The Brief Test of Adult Reading by Estimate, or BARTARE, is useful for estimating premorbid intelligence. It takes about five minutes and gives you a reference point when prior data is unavailable. The Computerized Adaptive Testing for Neurotrauma, or CAT-N, adapts question difficulty based on responses. It reduces fatigue and administration time. The Disability Rating Scale tracks functional independence over time and is sensitive to small but meaningful changes. A counter-intuitive point about these tools is that higher scores do not always mean better outcomes. On some neuropsychological measures, slower processing speed paired with higher accuracy reveals a different clinical picture than fast responses with frequent errors. I once worked with a patient whose raw scores looked decent on paper. When I checked the error patterns, there was a consistent rush-through behavior that masked significant executive dysfunction. The standardized score alone would have missed it entirely. Looking at response time distributions and error types alongside the composite score caught the real problem. Another nuance involves cultural and linguistic factors. Many standardized instruments were normed on specific populations. Applying them without adjustment can produce misleading results. I encountered a case where a bilingual patient scored well below expectations on a verbal fluency task. The issue was not cognitive impairment. It was the test format, which favored monolingual English speakers. Switching to a language-appropriate version corrected the false finding. This is not a rare issue. It happens regularly in diverse clinical settings.
Get the Full Details
Practical Issues That Arise During Administration
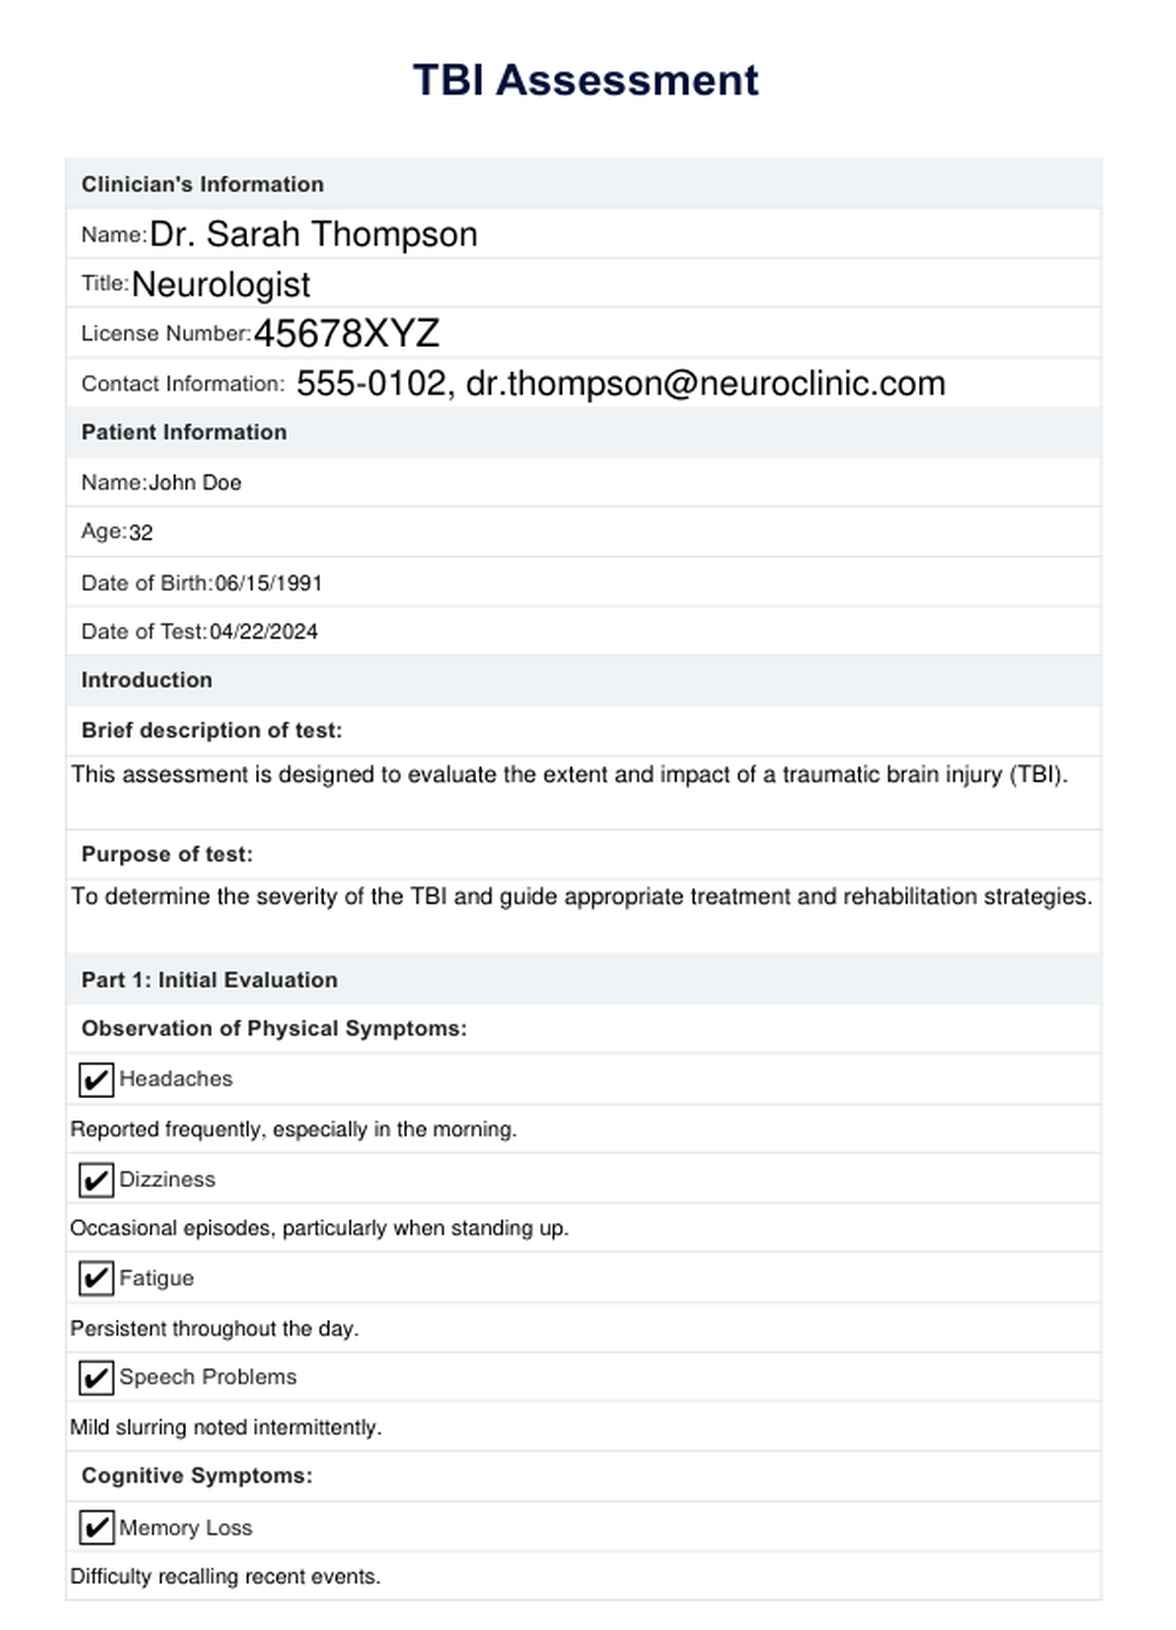
Patient fatigue is the biggest practical obstacle. Standardized protocols assume continuous attention spans that many TBI patients simply do not have. Breaking assessments into multiple shorter sessions is often necessary. I typically split longer batteries into two or three sessions spaced one to two days apart. This does not invalidate the data if you document the change. Most instrument manuals allow for split administration when noted properly. Sensory and motor complications add another layer. Vision problems, hearing loss, and limited fine motor control can interfere with performance on tests that assume intact sensory and motor function. I had a patient who could not complete a timed motor coordination subtest due to residual weakness from the injury. The standard scoring would have dragged down his overall index. I documented the motor limitation and relied on untimed alternatives for that domain. The resulting profile was less tidy but more accurate. Medication effects are frequently underestimated. Sedating medications, anticonvulsants, and psychotropic drugs can suppress cognitive performance independently of the injury itself. I always check current medications before interpreting results. A score that looks like cognitive decline may simply reflect a medication adjustment made the week before testing. Noting medication status in the report is essential for anyone reading the data later.
Limitations and When Standardized Assessment For Tbi Falls Short
No assessment battery captures the full scope of post-TBI recovery. Standardized tools measure what they were designed to measure. They miss contextual factors like home environment, social support, and pre-injury mental health history. I have seen patients with relatively high test scores struggle significantly in daily life. The gap between test performance and real-world functioning is real and well documented in the literature. Standardized scores should never be the sole basis for discharge planning or return-to-work decisions. Another hard limitation is sensitivity to mild injury. Standardized tools are better at detecting moderate to severe impairment. Mild TBI, especially concussion-level injuries, often falls below the detection threshold of most instruments. Repeat measurement matters here. Single-point assessments miss a lot of subtle changes. Serial testing improves detection but adds cost and time. There is no perfect solution, only tradeoffs. If you are looking for a comprehensive overview of available instruments and their psychometric properties, the TrackMyBrain database maintained by the National Institute of Neurological Disorders and Stroke is a reliable resource. It is freely accessible and updated regularly. Another option is the Brain Injury Model Systems National Data and Statistical Center, which publishes detailed guidelines on assessment timing and instrument selection.
What to Watch Out for When Choosing an Assessment Protocol
Match the tool to the question you are actually trying to answer. Broad screening requires different instruments than detailed neuropsychological evaluation. Administrative burden increases sharply with each additional domain measured. A focused battery of three to five well-chosen tools often produces more clinically useful data than an unfocused attempt to measure everything. I have seen programs cut assessment time in half by removing redundant instruments while maintaining diagnostic accuracy. The key is knowing which domains are essential for your specific context. Documentation quality separates useful assessments from useless ones. If you do not record administration conditions, breaks taken, medication status, and any deviations from standard protocol, the results are nearly impossible to interpret correctly later. I keep a standardized notes template that covers all of this. It takes thirty seconds to fill out and prevents major interpretive errors down the line. Most electronic health record systems allow custom note templates. Set one up and use it consistently.