Understanding the Starling Curve Beyond the Textbook Diagram
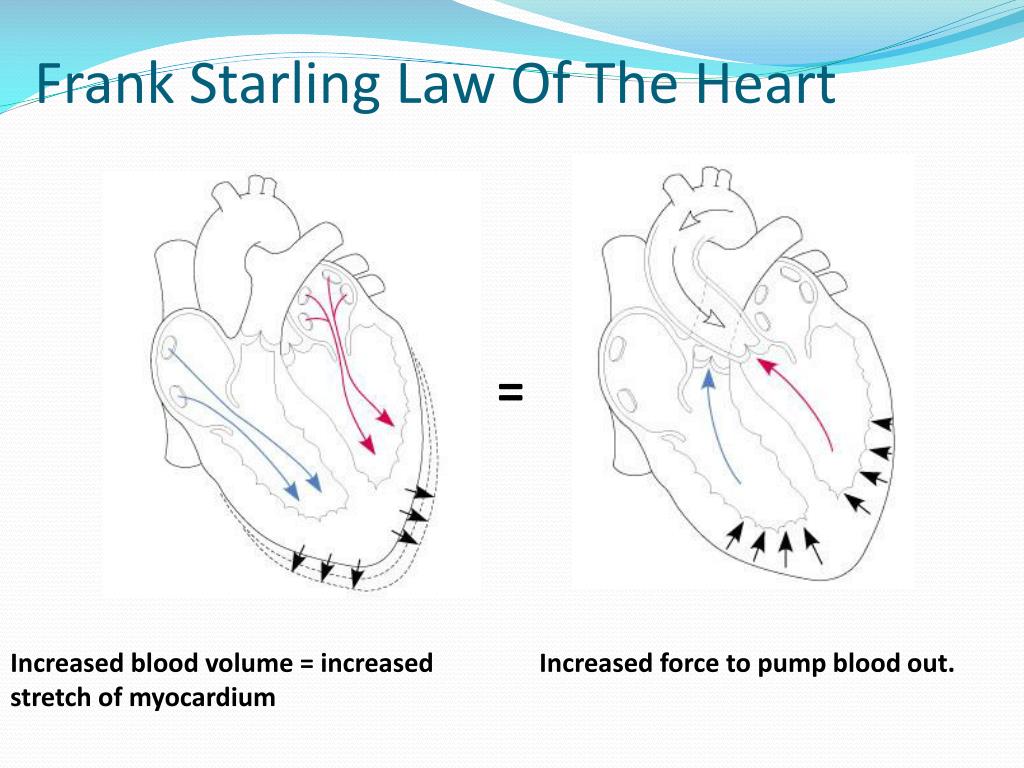
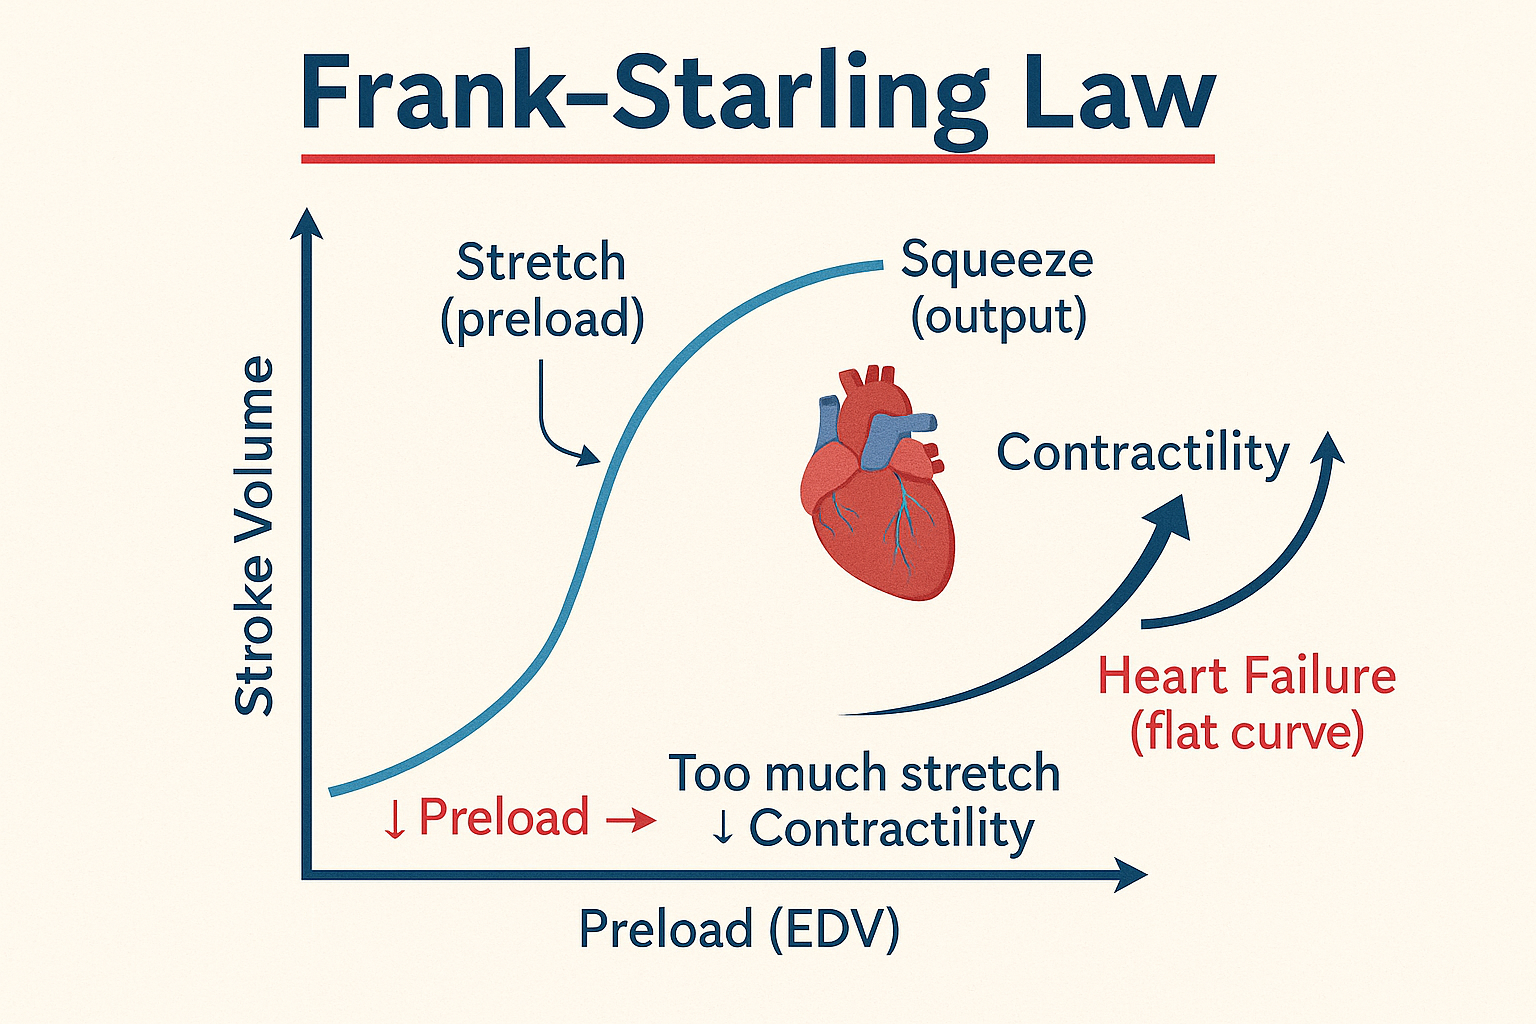
The heart pumps out whatever volume comes back to it, up to a point. That's the Starling Law of Heart in its simplest form, but the reality is more fiddly than the sweeping curve you see in any physiology textbook. I spent years managing ICU patients and trying to predict who would respond to a fluid bolus and who wouldn't. This law was my starting framework, and also the source of most of my headaches. Here's how it actually works under the hood. The left ventricle fills during diastole. The more it stretches, the more forceful the next systolic contraction becomes. This is because stretching the cardiomyocytes optimizes the overlap between actin and myosin filaments, increases calcium sensitivity at the troponin C binding site, and recruits additional cross-bridges. End-diastolic volume and pressure are the surrogates we use clinically, though they're not perfectly interchangeable. The actual driver is wall stress, which depends on radius, wall thickness, and pressure all at once according to Laplace's relation. In practice, you're looking at a relationship where stroke volume or stroke work plots against a preload parameter like LVEDP or LVEDV. The curve rises steeply at lower filling pressures and then plateaus. On the flat part, giving more fluid does very little for output and mostly just raises filling pressures further. That's where things go wrong in the ICU when someone gets another liter of crystalloid and the oxygenation drops because the is now wet.
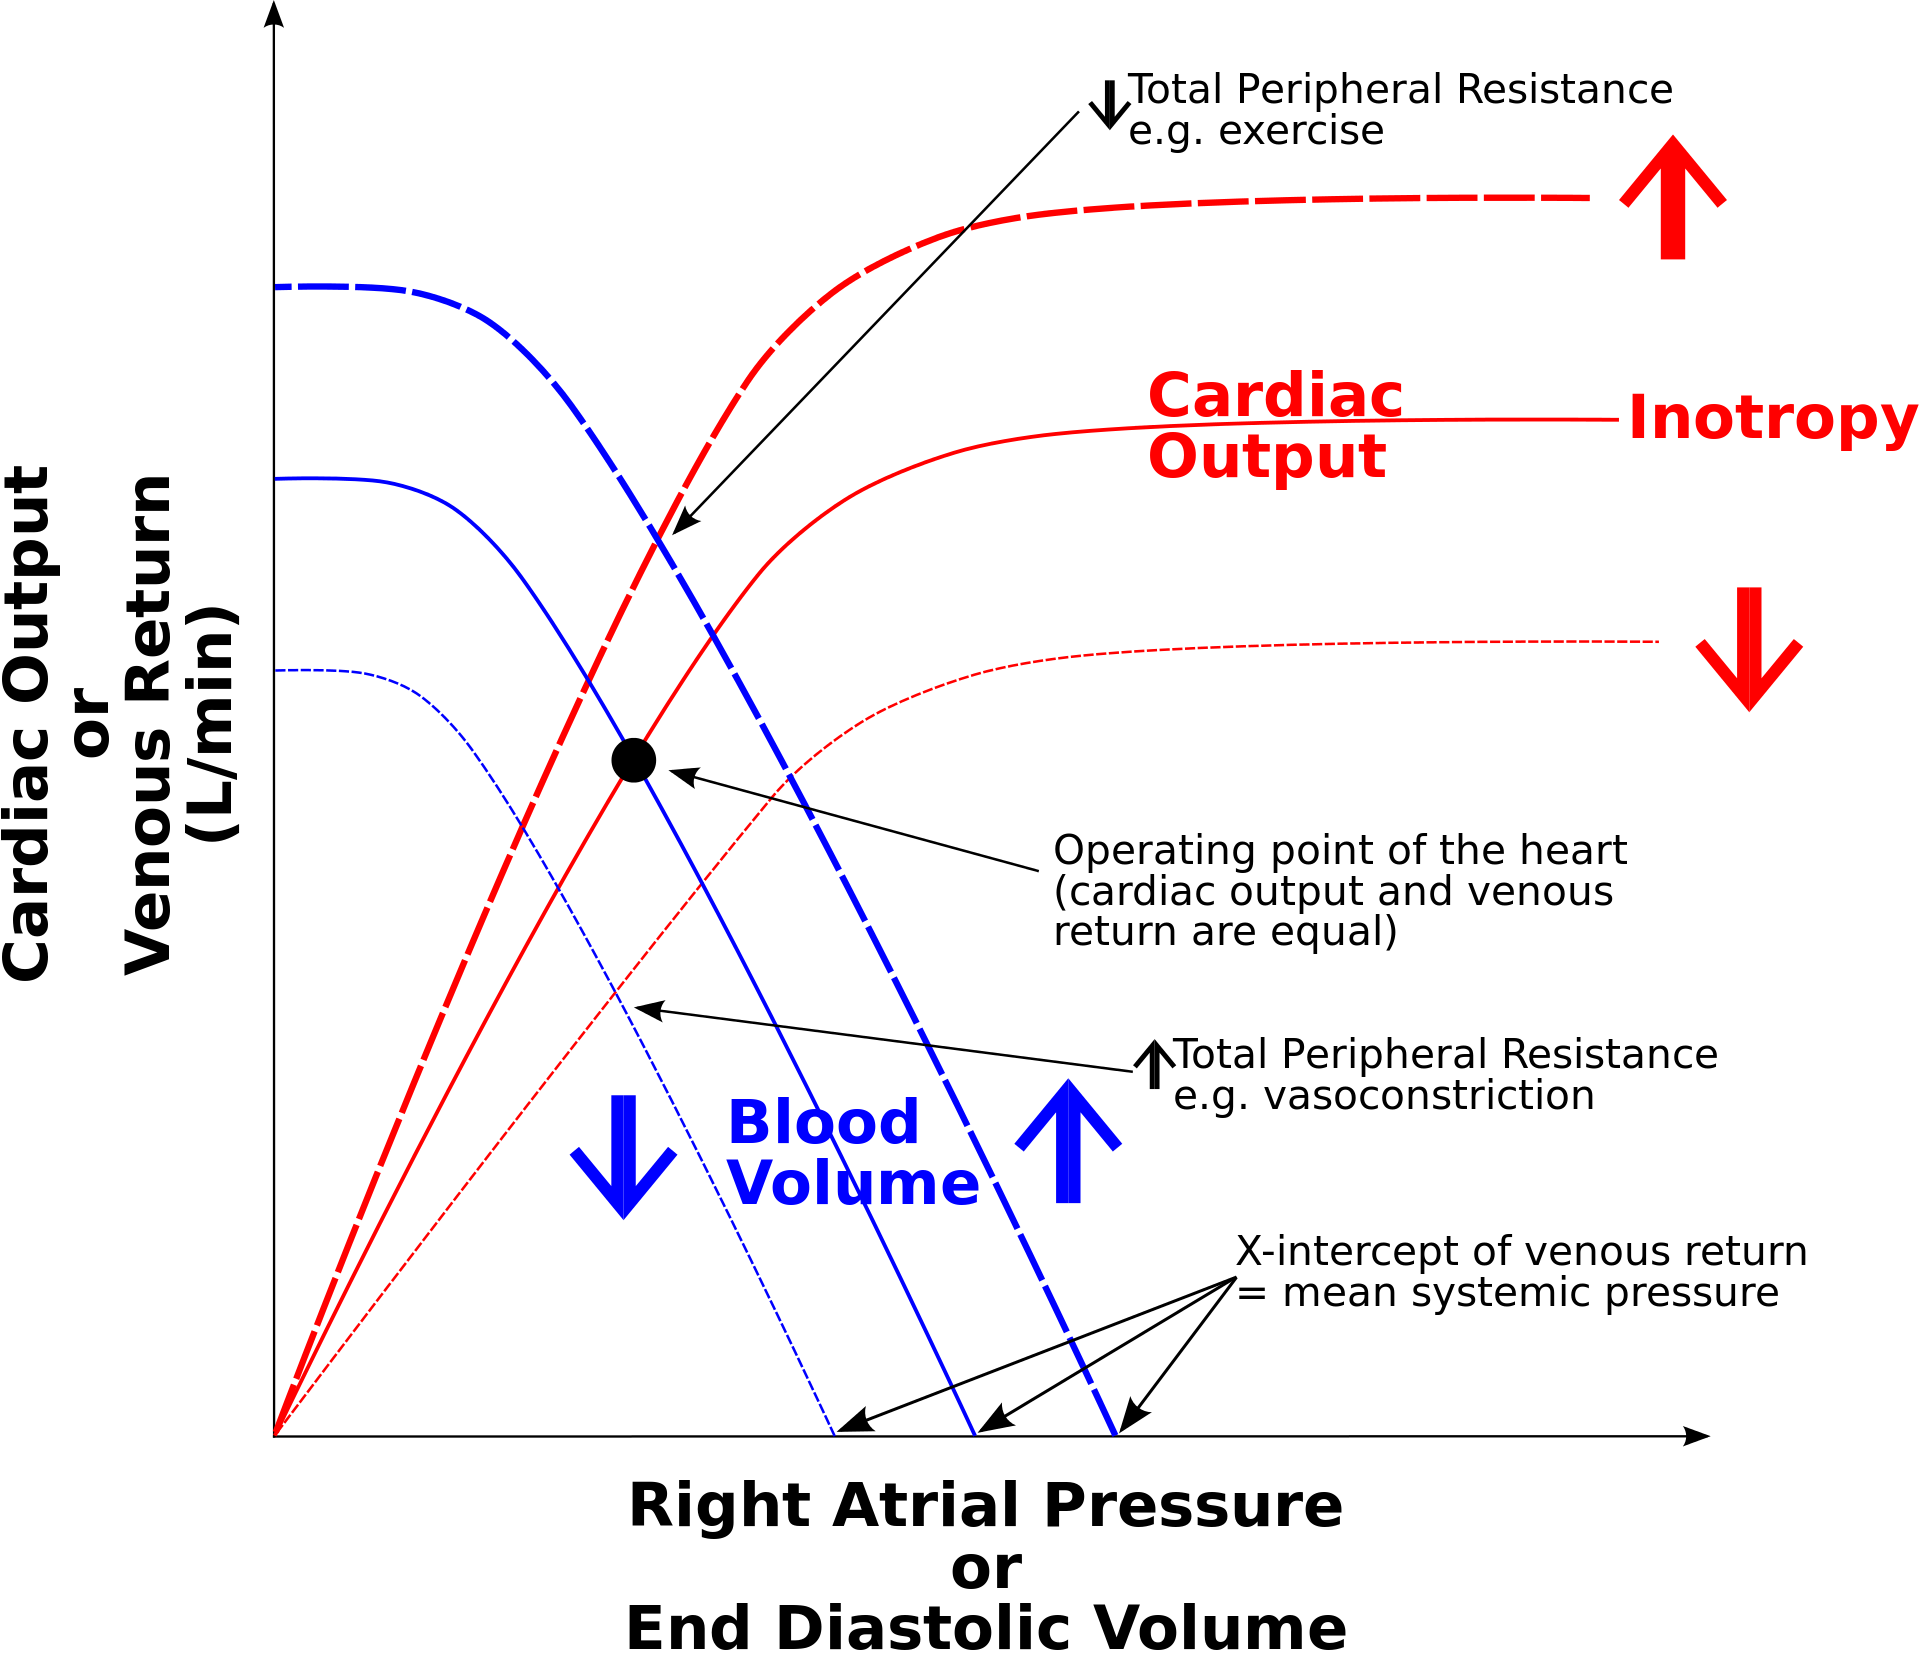
I learned the hard way that the Starling curve isn't fixed. It shifts up and down depending on contractility. Inotropes move it upward. Beta-blockers and ischemia move it downward. So two patients with the same LVEDP can have very different stroke volumes simply because one has severe systolic dysfunction and the other doesn't. I used to plot every wedge pressure against cardiac output and noticed the scatter was enormous unless you accounted for contractility state first.
Measuring What Matters
Preload isn't a single number you can grab. LVEDP requires a pulmonary artery catheter, which most people stopped placing years ago. Central venous pressure is easier to get but correlates poorly with left-sided filling pressures, especially when there's any right ventricular problem, positive pressure ventilation, or elevated intrathoracic pressure. Pulse pressure variation and stroke volume variation are dynamic measures that can predict fluid responsiveness better than static pressures, but only in controlled settings: fully sedated, mechanically ventilated patients in sinus rhythm with tidal volumes around 8 ml/kg. Get any of those conditions wrong and the numbers become noise. I found that echocardiography gave me the most reliable picture. Left ventricular end-diastolic area by echo tracks preload better than CVP in most surgical and medical ICU patients. The mitral inflow E/A ratio and tissue Doppler e' velocity let you estimate filling pressures without sticking a catheter into the pulmonary artery. Decent equipment and a competent sonographer matter a lot here. Rushed scans are worse than nothing.
Get the Full Details
When The Curve Breaks Down
This is the part nobody warns you about. The Starling mechanism assumes a normal, compliant ventricle. Once compliance changes, the whole relationship distorts. Stiff ventricles from hypertrophy, amyloidosis, or prolonged tachycardia mean that small increases in volume cause large increases in pressure. Those patients look well-filled on paper but can't tolerate even modest fluid challenges. Their curve is steep from the start, so the plateau zone arrives almost immediately. I had a patient with hypertrophic cardiomyopathy and severe diastolic dysfunction who needed surgery. Everyone kept saying his CVP was low so he was dry. His LVEDA on echo was barely above normal, but pushing fluid into him raised his LAP into pulmonary edema range within minutes. We managed him with phenylephrine and careful rate control instead. Fluid was never going to help because his problem was filling, not volume. Another failure mode is acute cor pulmonale. Right ventricular infarction or massive pulmonary embolism shifts the interventricular septum into the left ventricle during diastole. The LV can't fill properly regardless of how much volume you give it. The Starling curve for the left ventricle becomes irrelevant because the constraint is mechanical compression, not intrinsic myocardial properties. I've seen residents hang bags of saline on these patients and wonder why the blood pressure didn't budge. The answer is always the same: you're pushing against a sealed door.
Clinical Application Without the Guesswork
Fluid management is where most people use this concept incorrectly. The idea that you give fluid until the curve plateaus sounds clean until you try to find that plateau in a living person. You don't test it by giving fluids blindly. You use a trial. A 250 to 500 ml bolus over ten to fifteen minutes with repeated assessment of stroke volume or blood pressure afterward. If stroke volume rises by more than ten to fifteen percent, the patient is on the steep part of the curve and may benefit from more. If there's little change, they're near the plateau and more fluid carries risk without reward. I used a passive leg raise as a self-contained fluid challenge when I wasn't sure about volume status. It shifts about 300 ml of blood from the legs and splanchnic bed into the central circulation without introducing any actual fluid. An increase in stroke volume during the maneuver predicts fluid responsiveness with reasonable accuracy. No catheters, no assumptions about intrathoracic pressure. I relied on this constantly when the monitoring was ambiguous. The reverse application matters too. Diuretics and venodilators move the operating point down the curve. In heart failure with volume overload, reducing preload can actually improve cardiac output by shifting the heart away from the steep, congested part of the curve back toward a more favorable position. This is why patients with biventricular failure sometimes get worse when you overload them and better when you gently deplete them, even though both interventions change the same variable in opposite directions.
A Few Things That Will Surprise You
Heart rate matters more than people admit. Tachycardia shortens diastole and reduces filling time. The stroke volume per beat drops, and the Starling mechanism can't compensate because there simply isn't enough time for adequate preload to develop. I've seen patients in atrial fibrillation with rapid ventricular response appear hypovolemic on all the numbers while actually being volume overloaded. Rate control fixed the output problem faster than any fluid bolus ever could. Pericardial constraint is another trap. Constrictive pericarditis or even significant pericardial effusion limits the absolute volume the heart can hold. The Starling curve becomes compressed into a narrow range. Both filling pressures equalize across chambers during diastole. Giving fluid helps for a brief moment and then harms. The solution isn't more volume, it's drainage or pericardiectomy depending on the cause. Intercardiac dependence means the right ventricle and left ventricle are on different points of different curves at the same time. ARDS with high PEEP raises RV afterload, worsens RV function, and reduces LV filling. The LV Starling curve looks flat because the preload is being compromised from the other side. Lowering PEEP slightly, if oxygenation allows, can suddenly improve LV output without any change in total body fluid. I've watched this happen repeatedly during lung-protective ventilation adjustments.
Bottom Line
The Starling Law of Heart describes a real and important relationship, but it's not a protocol. It doesn't tell you how much fluid to give or when to stop. It tells you why some patients respond to volume and others don't. The clinical utility comes from understanding where each individual heart sits on its own curve, which requires actual measurement rather than assumption. Echocardiography, dynamic indices, and careful serial assessment beat any single number. And when the curve seems wrong, check compliance, contractility, and pericardial constraints before reaching for another bag of saline.