Setting Up Triage Practice Scenarios for Training
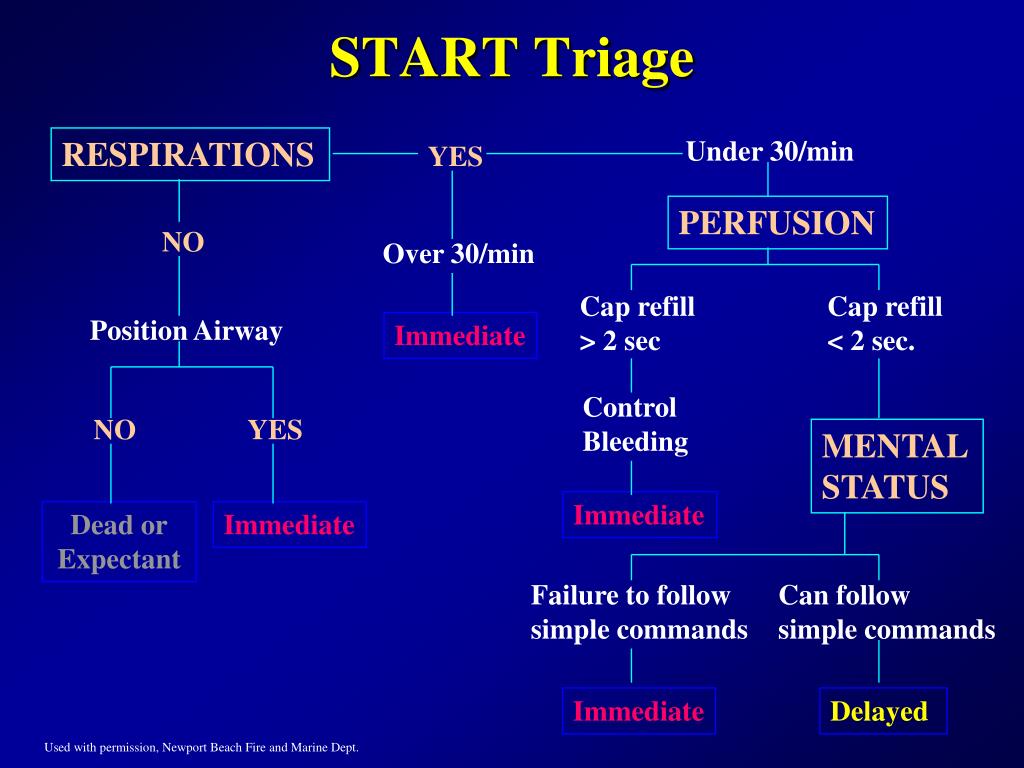
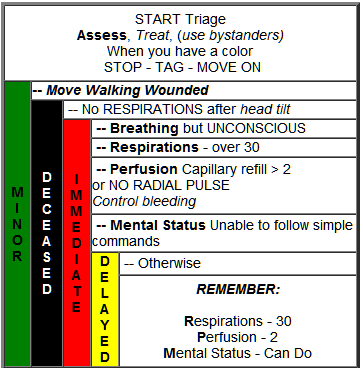
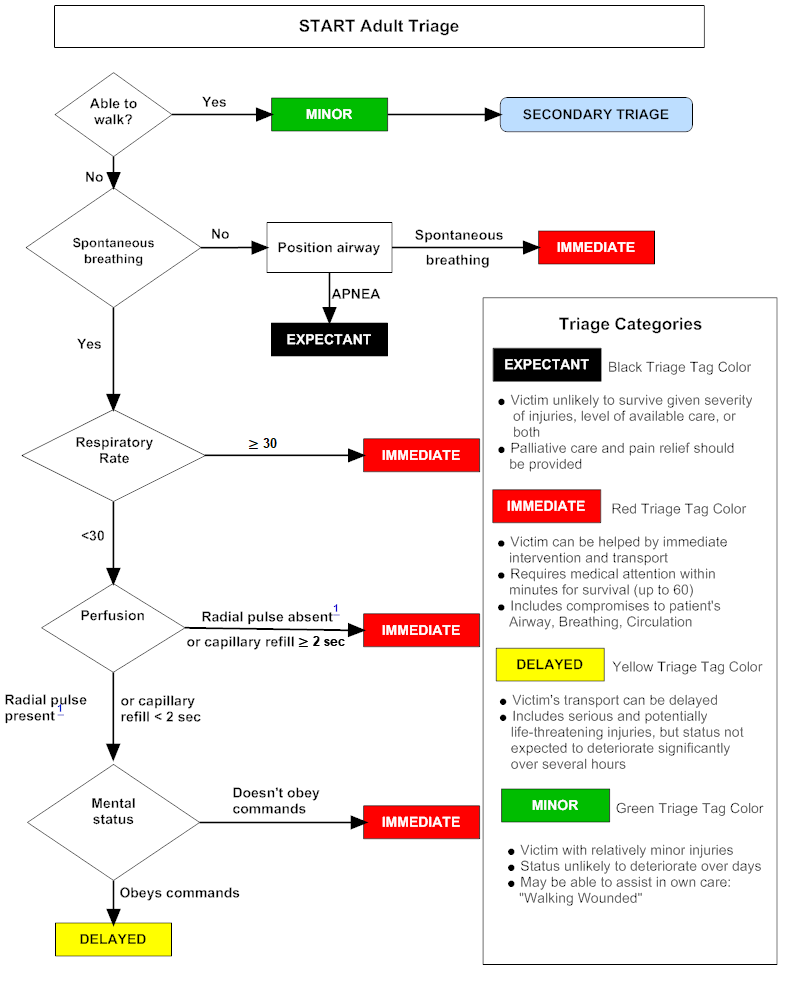
You need something better than reading case studies. It helps if your people actually walk through simulated patient flows before they handle real ones. That is where Start Triage Practice Scenarios comes in, or rather, what it should be: a structured way to run repeated, realistic triage drills with measurable outcomes. The term gets thrown around in a lot of different programs, so I will focus on how it works when you actually build and run one. Start Triage Practice Scenarios is not a single product you download. It is a framework you construct, usually around a set of scripted patient presentations designed to test whether trainees can correctly sort, prioritize, and escalate under time pressure. If someone is selling you a rigid packaged version, take it with a grain of salt. The real value is in how you design the scenarios and how you debrief afterward. I built one of these for an urgent care clinic about three years ago. We had ten standard cases covering the usual range: chest pain, pediatric fever, ankle sprains, allergic reactions, abdominal pain, lacerations, respiratory distress, back pain, dizziness, and a behavioral health crisis. Each scenario had a primary presentation, but we built in hidden complications. The person playing the patient would drop a clue at minute three that the headache was actually the worst of their life, or the ankle pain patient would mention they are on blood thinners. That forced the trainee to re-triage in real time instead of locking into a first impression.
The setup usually takes about four to six hours if you are doing it from scratch. You write the scripts, brief the actors or standardized patients, set up the triage area with the right equipment, and build a scoring rubric. The scoring part is where most programs fail. A simple pass or fail does not tell you anything useful. You need to score on specific behaviors: time to initial assessment, appropriateness of acuity level, whether red flags were caught, communication with the provider, and documentation accuracy. I use a five-point scale on each metric. It adds about ten minutes to the debrief per trainee but makes the results actually comparable across people. One edge case that caught us off guard was the low-acuity regular who showed up for a routine prescription refill but slipped in a subtle cardiac complaint. Trainees kept missing it because the patient looked and acted normal. The workaround was to add a brief pre-visit questionnaire to the waiting room tablet that asked about any new symptoms, even if the patient thought it was unrelated. After that change, we caught two actual cardiac issues in our next session that would have been sent home with a refill. If you want to find existing materials, search for triage simulation kits from organizations like the Emergency Nurses Association or the American College of Emergency Physicians. They have standardized case libraries you can license. Some hospital systems share their scenario decks through academic networks if you reach out directly. There is no single official download link because the whole thing is distributed through professional channels, not consumer websites.
A counter-intuitive thing about running these is that harder is not always better. People think you should throw the most chaotic scenario at trainees first. That just creates anxiety and bad habits. Start simple, build confidence, then layer in complexity. Run a clean, straightforward case first. Then add time pressure. Then add a second patient arriving at the same time. Then introduce the hidden complication. The progression matters more than the drama of any single scenario. Another thing beginners miss is the debrief. The scenario itself is only half the learning. The debrief is where the actual training happens. I spent too long early on rushing through the debrief to fit more scenarios in the schedule. We ended up running twelve scenarios per session with five minutes of feedback each. The results were worse than when we ran six scenarios with thirty minutes of structured debrief. The learners retained almost nothing from the fast version. Now I cap sessions at eight scenarios maximum with at least twenty minutes of debrief per person. There are real limitations to this approach. It does not replicate the emotional weight of a real Code Blue or a pediatric arrest. Your people will still freeze when it actually happens. Simulation can build competence but not necessarily composure. You need repeated exposure over time, not a single annual drill. Also, actor consistency is a problem. Different people playing the same role will give different clues at different times, which makes comparison between trainees messy. We solved this by having one or two dedicated standardized patients who stayed consistent across all sessions.
Get the Full Details
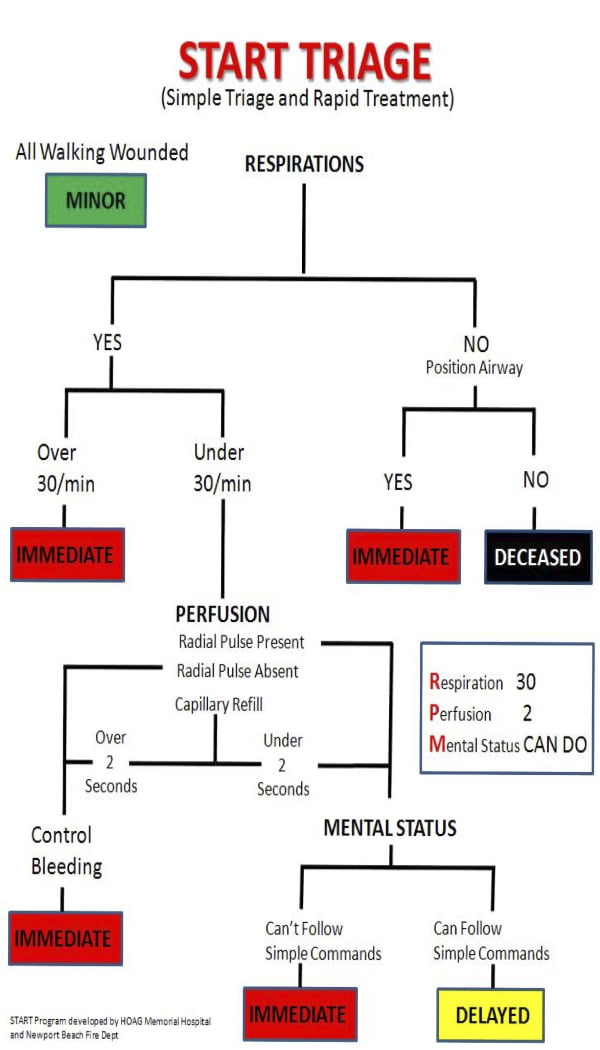
If you are working with a small team or limited budget, you can adapt this by using peer-to-peer scenarios where staff take turns being the patient. It is less polished but it still works. The key is maintaining the scoring rubric regardless of who is playing. That way the feedback stays objective instead of turning into a casual group critique. I also recommend running these scenarios quarterly instead of annually. Skills decay faster than people expect. A study we did showed that triage accuracy dropped by about twenty percent between an annual drill and the next one. Quarterly ran the decay down to under five percent. The extra time investment pays for itself in fewer missed acuity levels during actual clinical shifts.