Working With Spinal Stenosis in Clinical Practice
I spent years treating lumbar stenosis patients before I really understood what was going on. The standard textbooks tell you flexion-based exercises help, but they don't explain why some people get worse instead of better. Here's what I learned from actual practice, not theory. The core issue with spinal stenosis is that the canal narrows, putting pressure on nerves. Standing upright makes it worse. Bending forward opens things up. That's the basic mechanic behind why flexion-based exercises help most patients. But here's the thing nobody tells you: not everyone responds the same way. I had a patient, 62-year-old male, chronic lower back pain with neurogenic claudication. Standard protocol said extension-flexion balance work. After six weeks, he was worse. Not better. I changed the approach entirely and focused on nerve gliding combined with sustained flexion positioning. Took him twelve weeks, but he finally got relief.
The key insight is that stenosis isn't just about the canal narrowing. It's about how your body compensates. Most people with lumbar stenosis develop a forward-leaning posture because it opens the neural foramina. They've been doing this for years. Trying to force them back into neutral alignment without addressing the underlying mobility issues just creates more pain. I recommend starting with gentle nerve glides before any aggressive stretching. Sit on a treatment table, extend one knee while simultaneously flexing your neck. You should feel a mild tension along the back of your leg. If it hurts sharply, stop. Hold for five seconds, repeat ten times. Do this twice daily. This usually takes about three minutes total. For flexibility work, focus on hip flexor stretching rather than lumbar stretching. Tight hip flexors pull the pelvis forward, increasing lumbar lordosis, which narrows the canal further. Kneeling hip flexor stretch works well. Hold each side for thirty seconds. Three sets. Most patients see improvement within two to three weeks if they do this consistently.
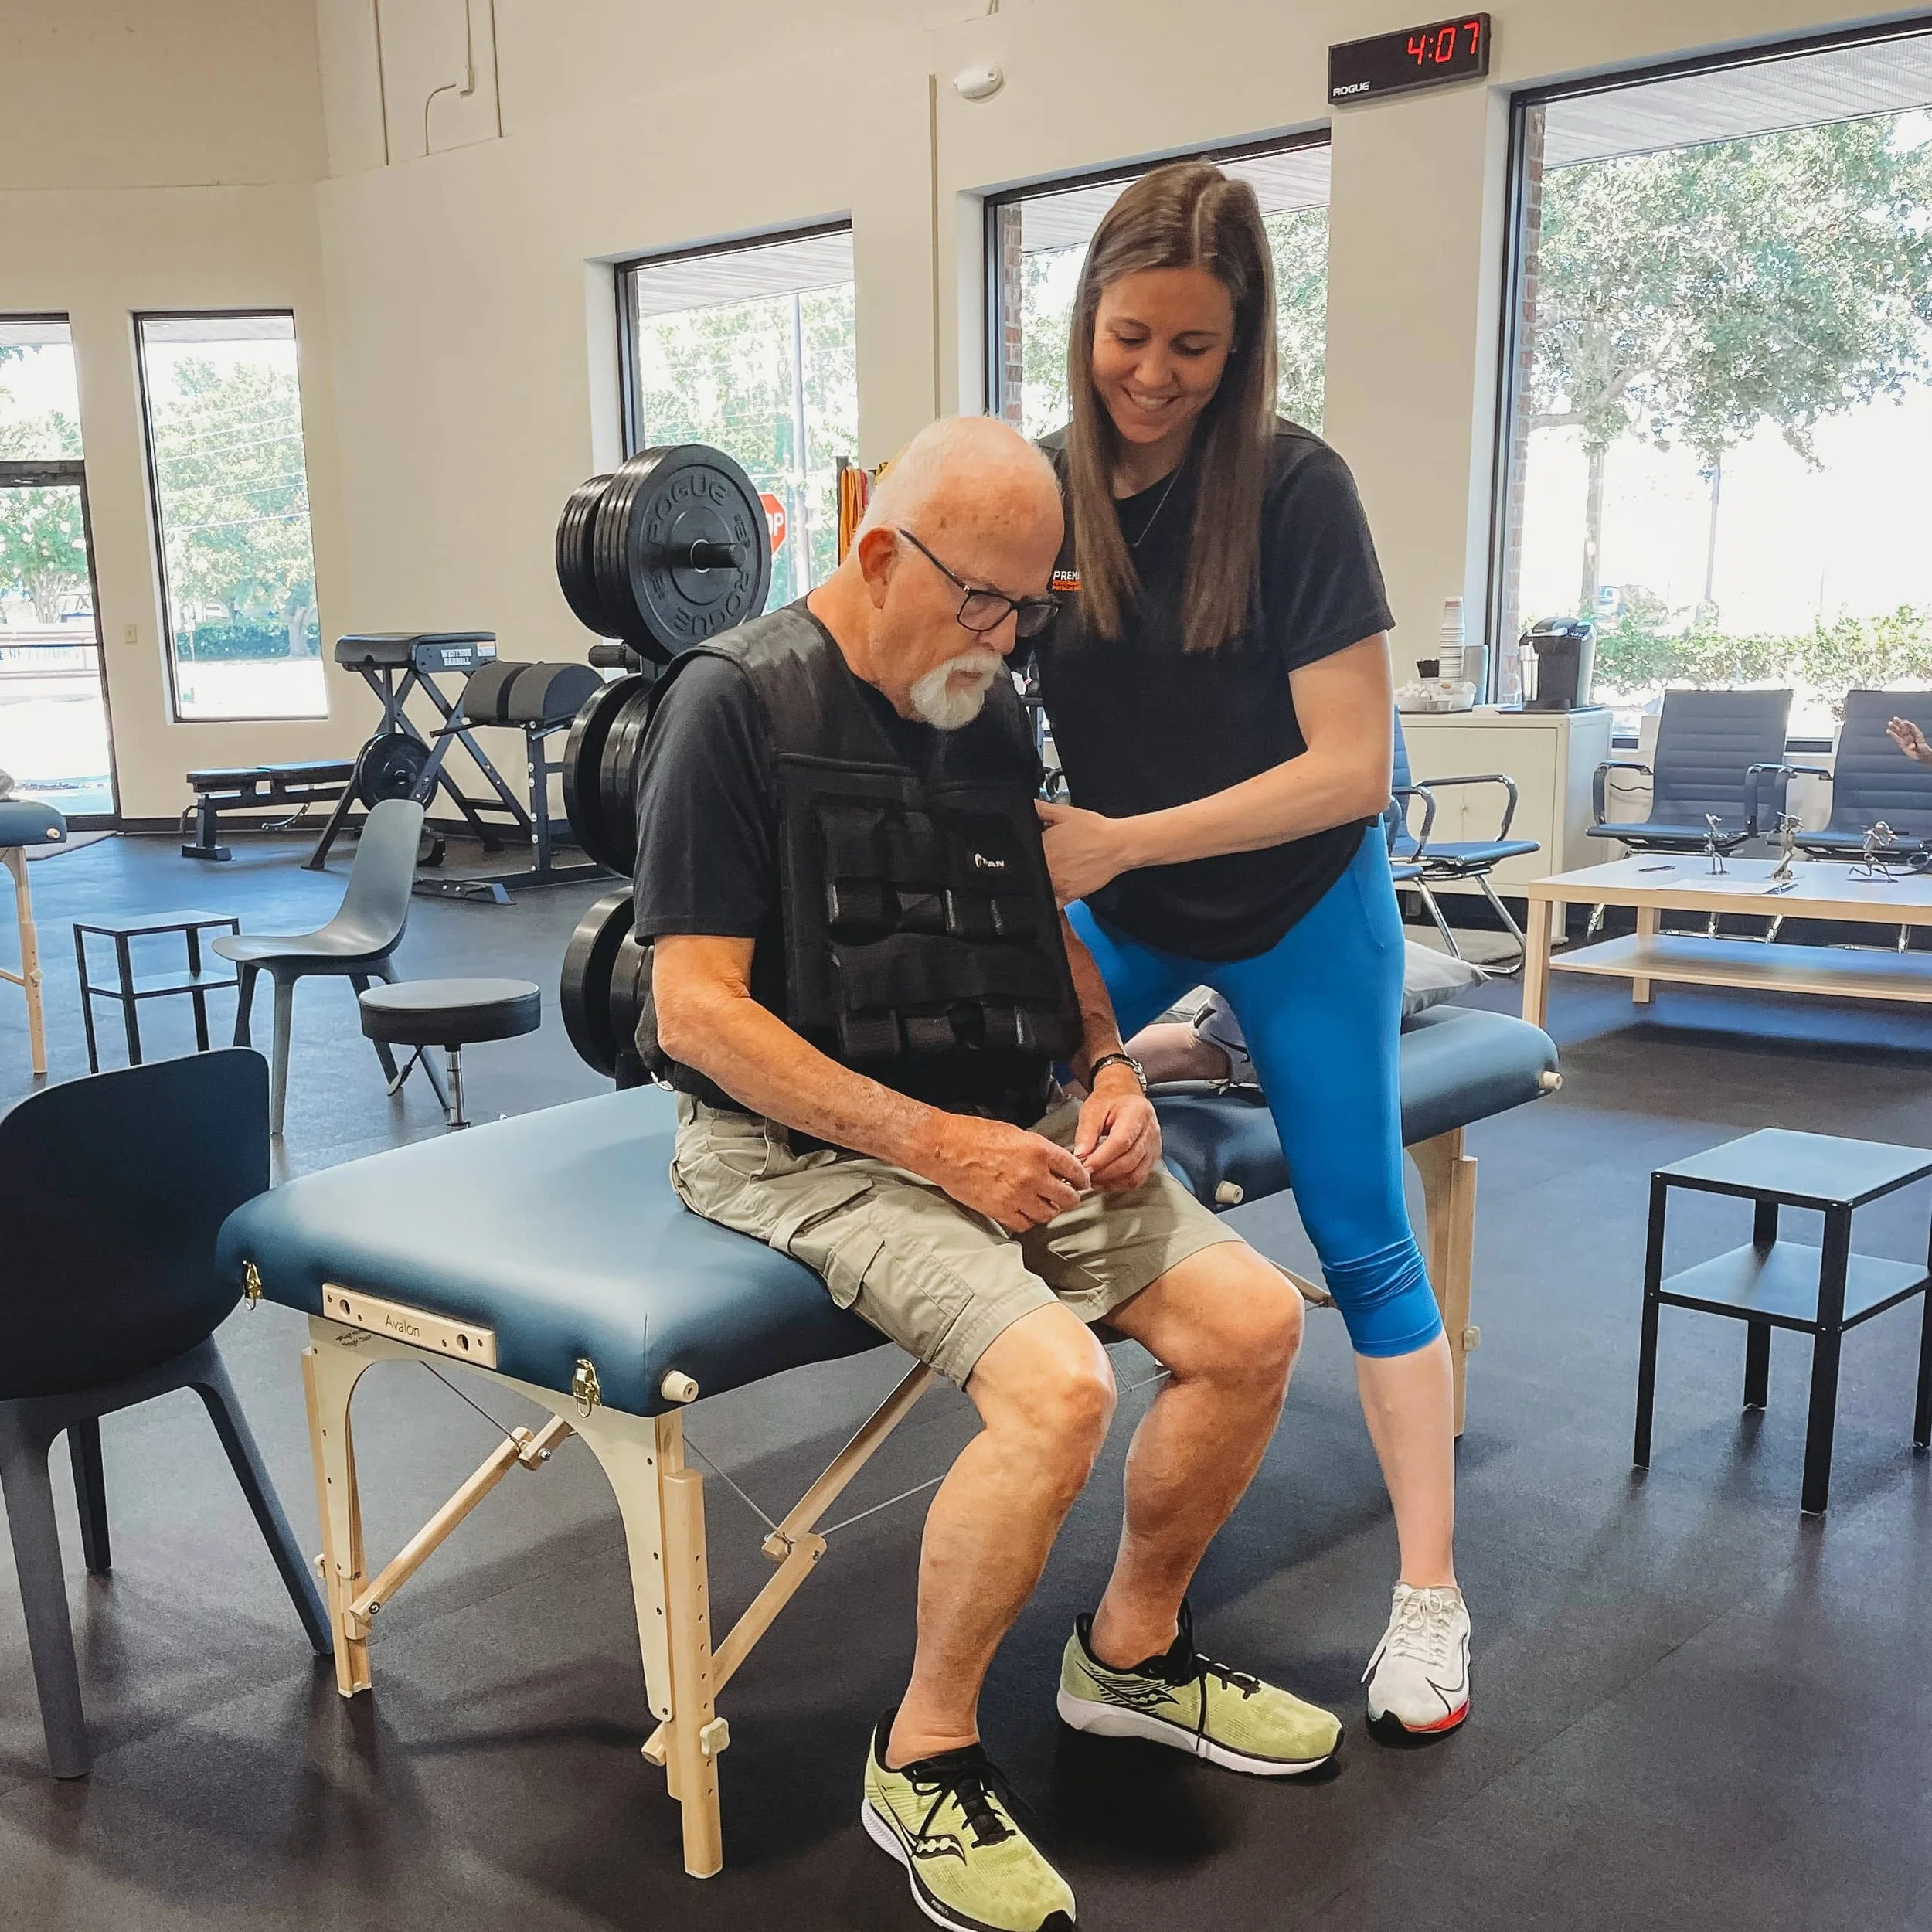
Core stabilization is important but often misunderstood. Planks can actually make stenosis worse for some people because they increase lumbar extension. Instead, focus on dead bugs and bird dogs. These maintain a neutral spine while building deep core strength. Start with five repetitions per side. Progress slowly. Aerobic conditioning matters more than most patients realize. Stationary cycling is ideal because it keeps the spine in flexion while getting the heart rate up. Twenty minutes at moderate intensity. Three times per week. This usually improves symptoms within four to six weeks.
Get the Full Details

What Most People Get Wrong
The biggest mistake I see is recommending extension-based exercises like cobra stretches. For cervical stenosis, these might help. For lumbar stenosis, they typically make things worse. I had a patient who started doing yoga based on advice from a fitness trainer. Came back in two days with significantly worse symptoms. Took another eight weeks to get her back to baseline. Another common error is focusing only on the spine. Stenosis affects walking patterns, which affects knees, hips, and even feet. I always assess the entire kinetic chain. A patient with foot pronation might have compensatory hip internal rotation, which increases lumbar lordosis. Treat the feet, improve the alignment, reduce the spinal load. Patience is essential. Spinal stenosis doesn't improve quickly. Most protocols suggest six to eight weeks before evaluating results. I usually reassess at four weeks, then eight, then twelve if needed. If there's no improvement by twelve weeks, reconsider the diagnosis or refer for imaging.
Not every case responds to physical therapy alone. Severe stenosis with progressive neurological deficits requires surgical consultation. Red flags include bowel or bladder dysfunction, saddle anesthesia, or rapidly worsening weakness. These need immediate referral. Don't try to treat these conservatively. I've found that patient education is as important as the exercises themselves. Explain the flexion preference clearly. Show them how standing upright narrows the canal versus bending forward opening it. Use simple demonstrations. Most patients understand this quickly when they see it visually. Home exercise compliance is usually the bottleneck. Patients do well in clinic but struggle at home. Give them a simple written plan. Five exercises. Two sets of ten. Twice daily. Keep it manageable. They're more likely to follow through with a shorter, clearer program than a complex routine.
The timeline for improvement varies. Some patients feel better within two weeks. Others need three to four months. I set realistic expectations upfront. Tell them this is a long-term management strategy, not a quick fix. Managing expectations early reduces frustration and dropout rates.

Practical Tips From the Clinic
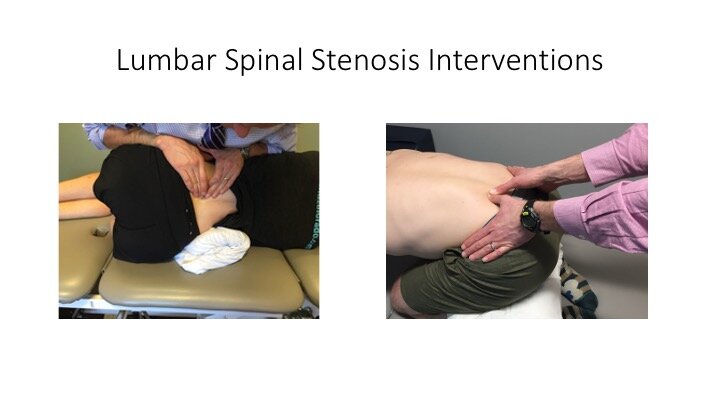
Use a gait analysis to assess walking patterns. Most stenosis patients adopt a forward-leaning posture while walking. This is their compensation. Note the degree of lean and how far they can walk before symptoms begin. Track this over time as a progress measure. Manual therapy can help but isn't a standalone solution. Mobilization techniques focusing on the hip and thoracic spine often provide better results than direct lumbar manipulation. The lumbar spine is already compromised. Work around it instead of through it. Consider referral for epidural steroid injections if conservative treatment fails after eight to twelve weeks. This isn't giving up. It's acknowledging that sometimes inflammation needs to be reduced before exercise can be effective. The injection buys time for therapy to work.
Stay updated on current research. Guidelines change. What worked five years ago might not be optimal now. I regularly review journals like Spine and Clinical Journal of Sport Medicine. Keeping current helps refine your approach and avoid outdated protocols. Document everything. Progress notes matter for insurance and for tracking outcomes. Record baseline measurements, intervention details, and response to treatment. This helps you adjust protocols based on real data rather than guesswork. Build relationships with orthopedic surgeons and pain management specialists. When you need to refer, having established connections helps patients get timely care. It also allows for collaborative treatment planning when appropriate.
Remember that stenosis treatment is individualized. Two patients with the same diagnosis may need completely different approaches. Assess thoroughly before prescribing. Don't rely on protocols alone. Clinical reasoning matters more than any textbook recommendation.