Step 2 CK: What Actually Matters for Passing
The Step 2 CK is an eight-hour, computer-based examination covering clinical knowledge across multiple specialties. It tests your ability to apply basic science and clinical data to patient care scenarios, not your memorization of isolated facts. The exam consists of eight blocks, each containing approximately 38 to 40 multiple-choice questions. You have roughly 45 minutes per block. The total content spans internal medicine, surgery, obstetrics and gynecology, pediatrics, psychiatry, neurology, geriatrics, and preventive medicine. There is no separate "clinical skills" component anymore — the CS exam was discontinued by the USMLE in 2021. Scoring is reported as a three-digit number on a scale of 1 to 300, with a passing score currently set at 214. Most match programs now use Step 2 CK as the primary screening metric, which means the pressure on this single exam is higher than ever. The raw content you need to know overlaps heavily with Step 1 material, but the context shifts from mechanism to management. You are expected to decide what to do next for a patient, not just what molecule is involved in a pathway.
What Is the Step 2 Assessment Exactly?
When people refer to the Step 2 Assessment, they are typically talking about Step 2 CK. It is a standardized licensing examination administered by the USMLE program. The question format is overwhelmingly single-best-answer multiple choice. You will see patient presentations with lab values, imaging descriptions, ECG readings, and social histories. Some questions ask for diagnosis. Some ask for the next best step in management. Some ask what finding you would expect on physical exam. A smaller but growing number integrate ethics, communication, and public health concepts directly into clinical vignettes. I ran into a specific issue during my own preparation that almost cost me a week of review. I was doing NBME practice forms and noticed my scores on the psychiatry and preventive medicine blocks were consistently five to eight points below the rest of the exam. I assumed I just needed more content review in those areas. It turned out the problem was actually question interpretation. The Step 2CK heavily weights the "next best step" framing, and psychiatry questions in particular love to trap you into picking the most definitive diagnostic test when the question is actually asking for the most appropriate initial management. I switched to reading the final sentence of every question before looking at the answer choices. That alone raised my psychiatry block scores by about six points on the scaled score. It sounds obvious in retrospect, but under fatigue at 3 PM on a practice exam, it is easy to miss.
How the Exam Actually Feels
Eight hours is long. The real challenge is not the volume of material — it is the sustained cognitive load. After block four or five, your ability to carefully parse a vignette degrades noticeably. This is why timed practice under realistic conditions matters more than doing untimed practice questions. Doing questions without a clock does not replicate the decision-making pressure you will face on exam day. The NBME forms are the closest you will get to the actual timing and difficulty curve. Use them as your primary benchmark, not random question banks. There is a common misconception that Step 2CK is easier than Step 1 because the content feels more familiar. That is only true if you are already comfortable with clinical reasoning. If your Step 1 preparation was purely fact-based memorization, Step 2CK will expose that gap quickly. The exam does not reward people who can list side effects of every drug. It rewards people who can prioritize. You will see questions where two answer choices are technically correct, but one is clearly the best next step. That distinction is the entire exam.
Get the Full Details

High-Yield Topics and What to Prioritize
Internal medicine carries the largest weight, roughly 30 to 35 percent of the exam. Within that, cardiology, pulmonary, nephrology, gastroenterology, endocrinology, and infectious disease form the core. You should be able to interpret basic ECGs, know the first-line treatment for common conditions, and recognize when to escalate care. Surgery is about preoperative optimization, postoperative complications, and when to operate. Obstetrics and gynecology covers prenatal care, labor management, and common gynecologic emergencies. Pediatrics focuses on growth milestones, vaccine schedules, and pediatric presentations of common diseases. Psychiatry and neurology are smaller but still significant. Preventive medicine and ethics questions are scattered throughout and collectively make up about 5 to 10 percent. One counter-intuitive point that most beginners miss: UWorld is excellent for building clinical reasoning, but it is not sufficient on its own for the breadth required. The actual exam draws from areas that UWorld touches lightly, like geriatrics and occupational health. You need a supplementary resource that forces you to engage with those lower-yield topics. First Aid for the Step 2 CK and Amboss have decent coverage there. Don't skip them because they feel less exciting than cardiology cases.
The NBME Forms: Why They Matter More Than Anything Else
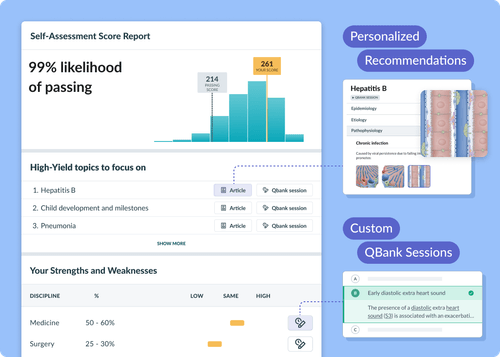
The NBME clinical science practice exams are the single most predictive tool available. They are written by the same people who write the actual exam. The scoring algorithms, question style, and difficulty distribution are nearly identical. Students often waste months doing question bank drills while ignoring these forms. Your NBME scores are your real readiness indicator. If your average NBME scaled score is below 225, you likely need more targeted review before booking the exam. If you are consistently scoring above 240, you are probably in good shape. The gap between your NBME performance and your target score should guide your study plan, not arbitrary timelines or forum advice. Here is a practical note about the NBME forms: they are not released in numerical order that matches their difficulty. NBME 26 and 27 tend to be harder than average. NBME 30 and 31 are closer to or slightly above the real exam difficulty. Form 32 is one of the most recent and is very close to current exam patterns. Take these forms in exam-like conditions — eight hours, no phone, no notes, with breaks between blocks. This builds the stamina the actual exam demands.
Common Pitfalls That Cost Students Points
The most frequent mistake is overthinking prevention questions. When a vignette describes a healthy patient coming in for a routine visit, the answer is often the screening test or counseling recommendation, not a complex diagnostic workup. Screening guidelines change, and the exam tests current recommendations. Know the USPSTF grading system and the major screening recommendations by age and risk factor. This section is low-hanging fruit for people who have actually reviewed it. Another trap is misreading the time element in the question. "Most appropriate next step" is different from "most appropriate initial step." If the patient is unstable, you resuscitate first. If the patient is stable, you diagnose first. The difference matters, and the exam writers build entire questions around whether you catch that distinction. I learned this the hard way during a practice exam when I picked a CT scan for a stable patient with suspected nephrolithiasis when the correct answer was renal ultrasound. The CT would have been appropriate in many real-world scenarios, but the question asked for the best next step in a stable patient, and ultrasound comes first to avoid radiation exposure. Those nuances add up across the exam.

Timeline and Resource Recommendations
A typical effective timeline ranges from four to eight weeks of focused study after completing the core clinical rotations. If you are studying alongside rotations, extend that to ten to twelve weeks. The standard resource stack is UWorld as the primary question source, First Aid for the Step 2 CK as the content reference, and NBME practice forms as the benchmark. Some students add Amboss or Rx for additional questions, but doing two full question banks rarely improves scores meaningfully unless you are starting from a very low baseline. Quality of review matters far more than quantity of questions. Each UWorld question should take about nine minutes including the explanation review. That means a full set of 38 questions plus explanation review takes roughly six hours. If you are doing two passes through UWorld, plan for about 40 to 50 hours total. Add NBME exam days and you are looking at six to eight weeks of dedicated effort. Trying to compress this into two weeks rarely works because the volume of review needed to absorb mistakes is substantial. The students who perform well treat question review as equally important as answering the questions themselves.
Test Day Logistics
Arrive at least thirty minutes early. Bring two forms of identification, one of which must be photo ID. The test center will provide a whiteboard and markers. You cannot bring personal items into the testing area. There are scheduled breaks between blocks, but the clock does not stop during breaks. You can use break time to eat the snack and drink you brought, but time spent in the bathroom or walking around eats into your rest period. Plan your nutrition accordingly. Bring water and high-protein snacks. Avoid heavy meals right before the exam. The exam interface lets you flag questions and return to them within a block. Use that feature. Do not linger on a difficult question for more than two minutes. Mark it and move on. You can come back at the end of the block. Running out of time at the end of a block and having to guess blindly is one of the most common reasons students underperform relative to their practice scores. Pace yourself from the beginning.
When Step 2 CK Is Not the Right Path
If you are a DO student, the equivalent exam is COMLEX Level 2-PE. It includes a performance evaluation component that tests clinical skills through simulated patient encounters. The knowledge exam is similar in scope but uses a different scoring system. Some students take both exams, but that is a significant time investment and should only be done if your career goals require it. For most IMGs and US grad students aiming for ACGME-accredited programs, Step 2 CK is the primary requirement. Check your target programs specifically before making any decision about additional exams. There is also a real limitation to relying solely on Step 2CK scores for residency applications. The exam measures clinical knowledge well, but it does not measure clinical skills, communication ability, or work ethic. Programs increasingly weight other factors after the initial screen. A high Step 2CK score gets you the interview. It does not guarantee the match. Prepare accordingly, but do not treat this exam as the sole determinant of your career trajectory.
Final Notes on Score Improvement
If your practice scores are not where you need them to be, the fastest improvement usually comes from targeted NBME review rather than more general study. Identify the blocks where you consistently lose points. Review the underlying concepts systematically. Then retest with another NBME form to confirm the improvement. Repeat this cycle. This is more efficient than randomly browsing flashcards or re-reading entire chapters. The exam rewards pattern recognition built through deliberate practice, not passive content exposure. The Step 2 CK is a marathon, not a sprint, but it is also not an insurmountable barrier. Students who approach it with a clear plan, realistic benchmarks, and honest self-assessment tend to do fine. The students who struggle are usually the ones who underestimate the clinical reasoning component or fail to simulate exam conditions during preparation. Set up your study schedule early. Take the NBME forms seriously. Trust the process. The result will follow.


