Locating the Sternal Angle of Louis in Clinical Practice
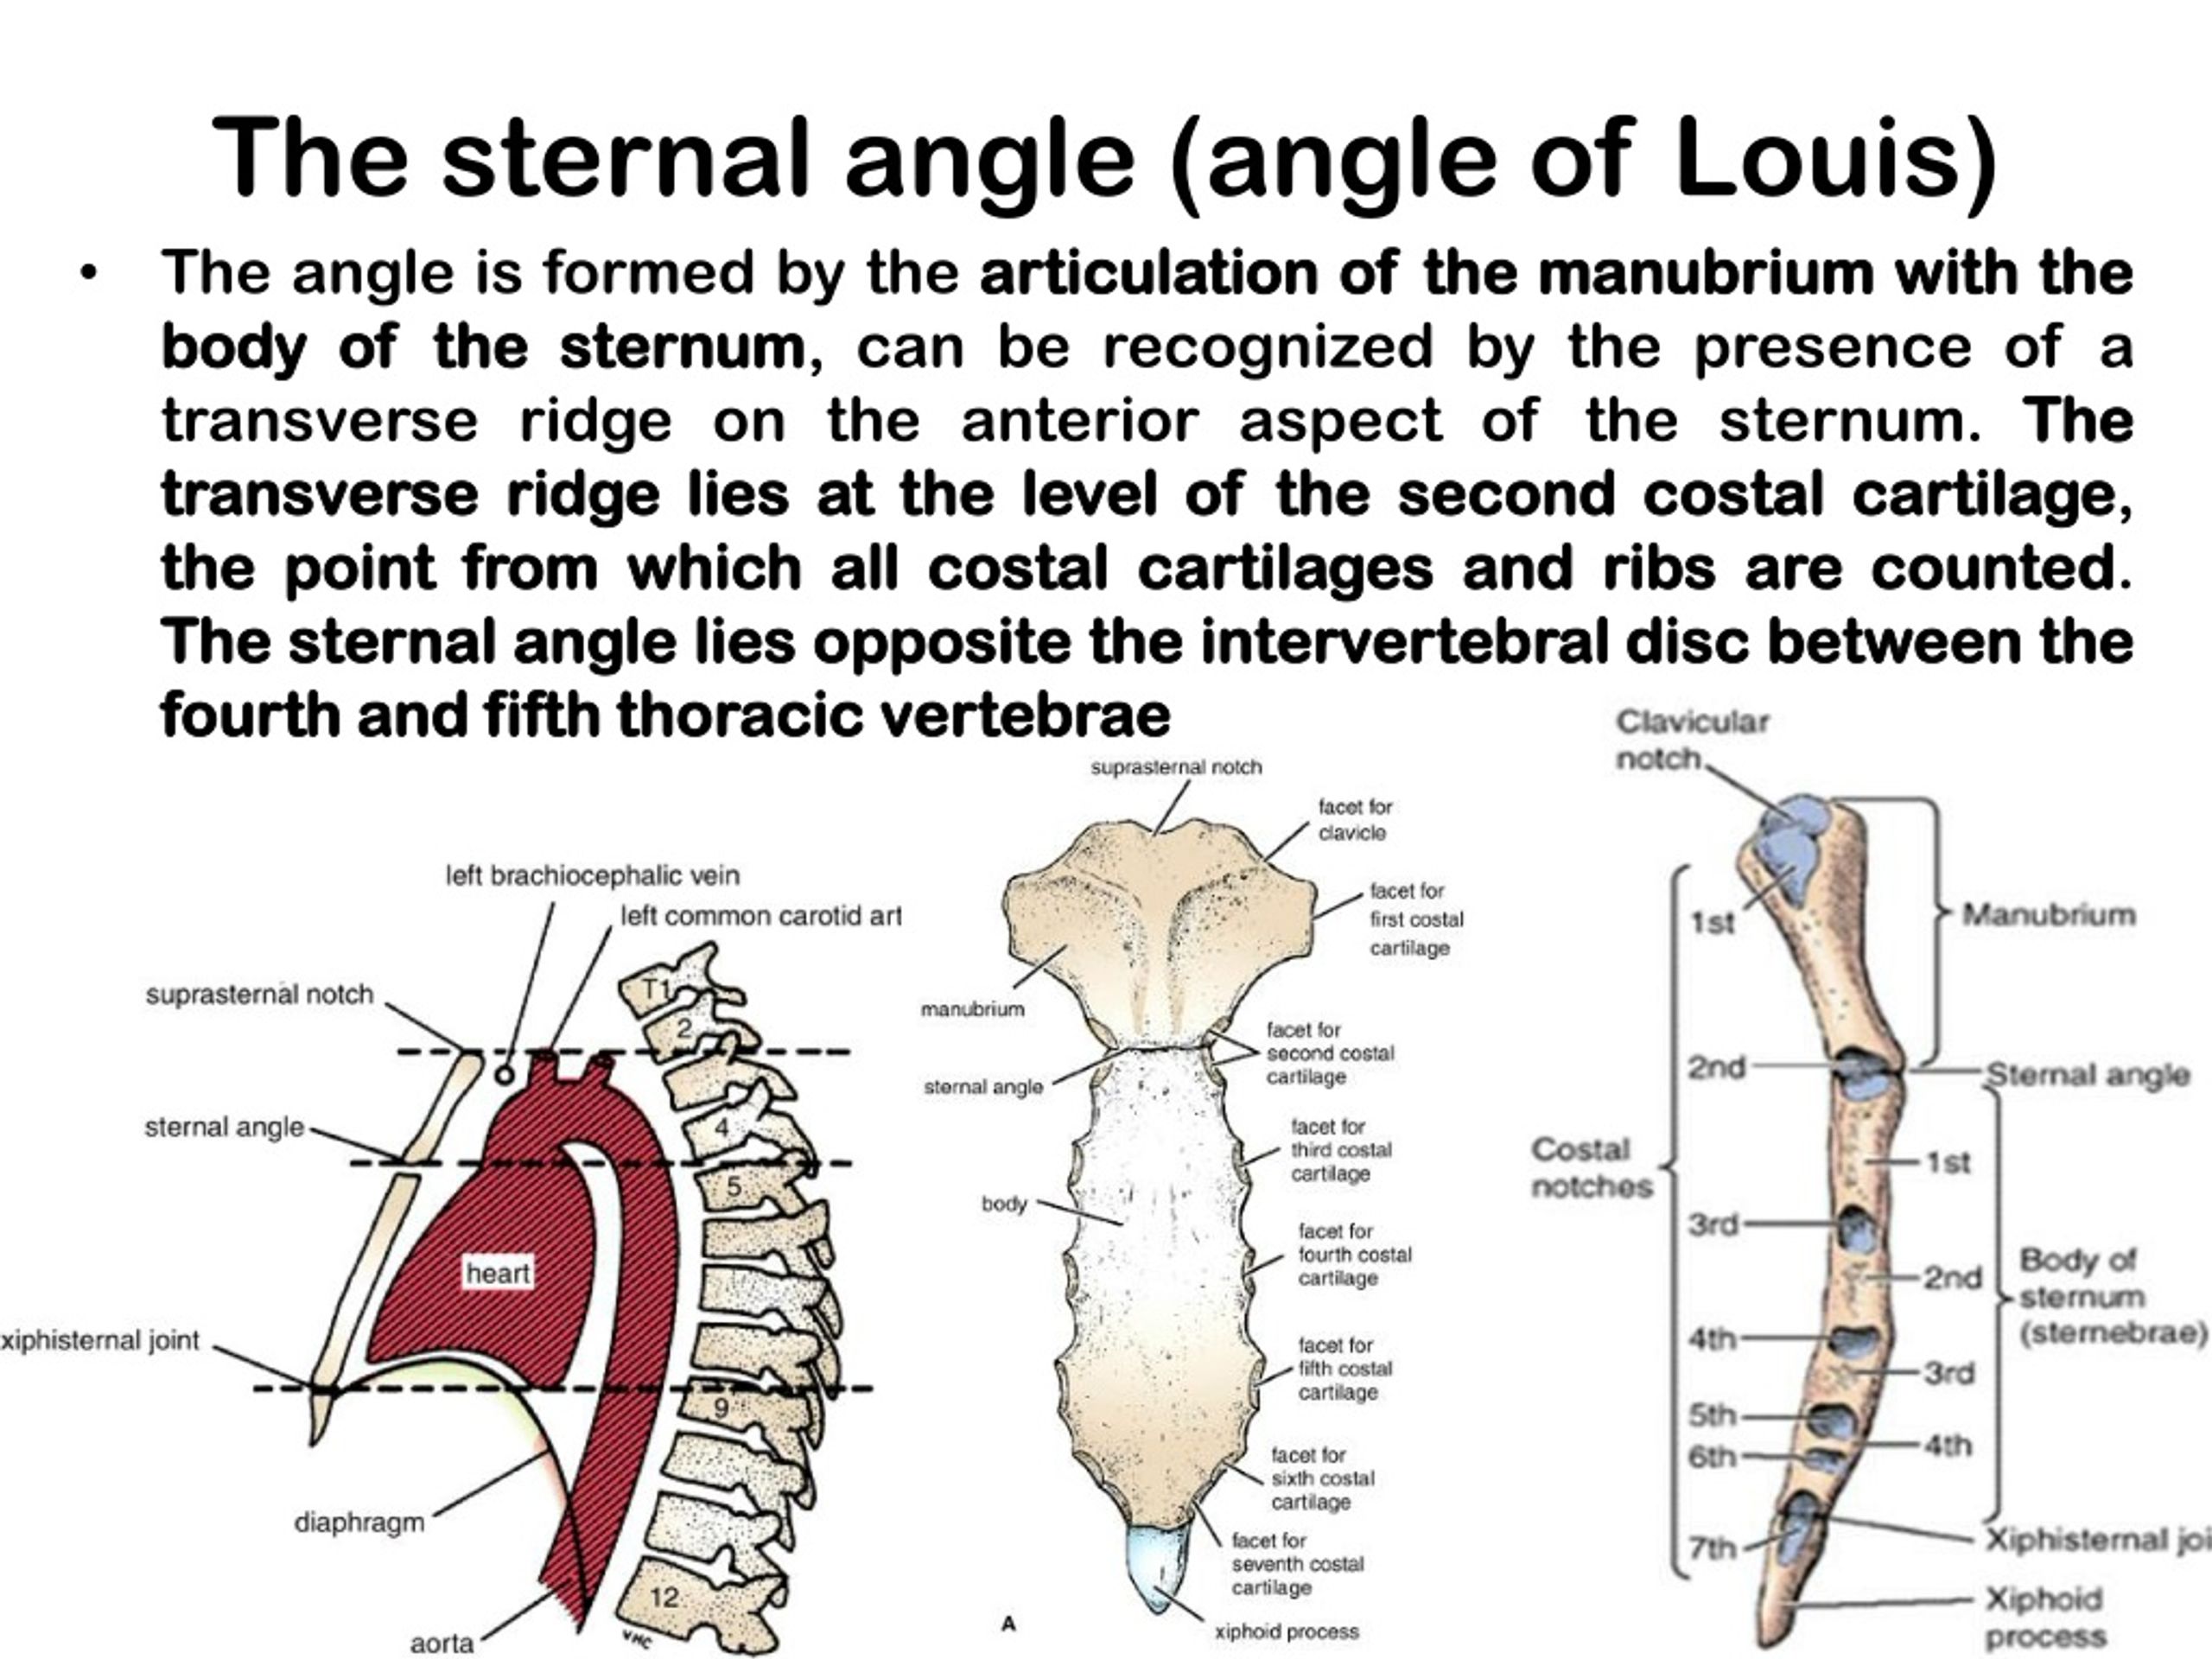
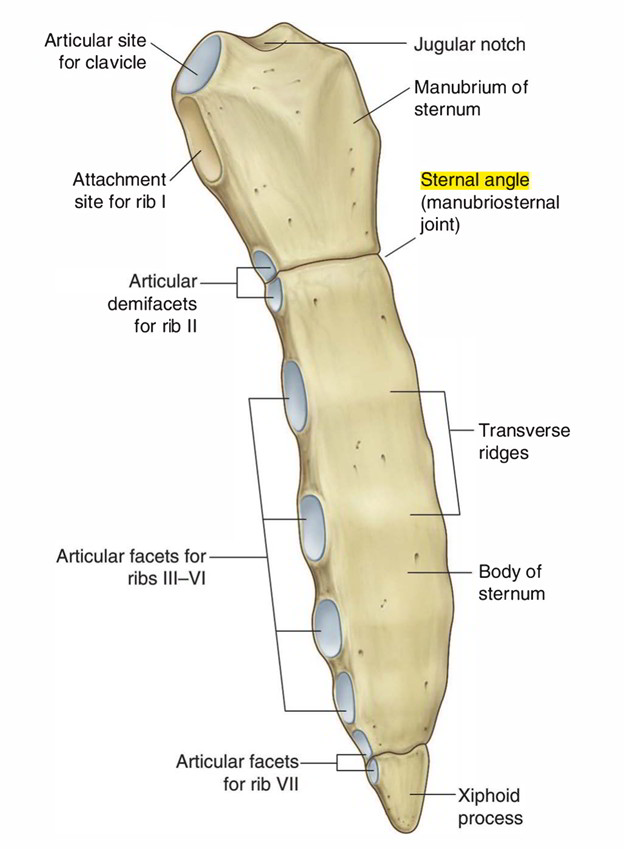
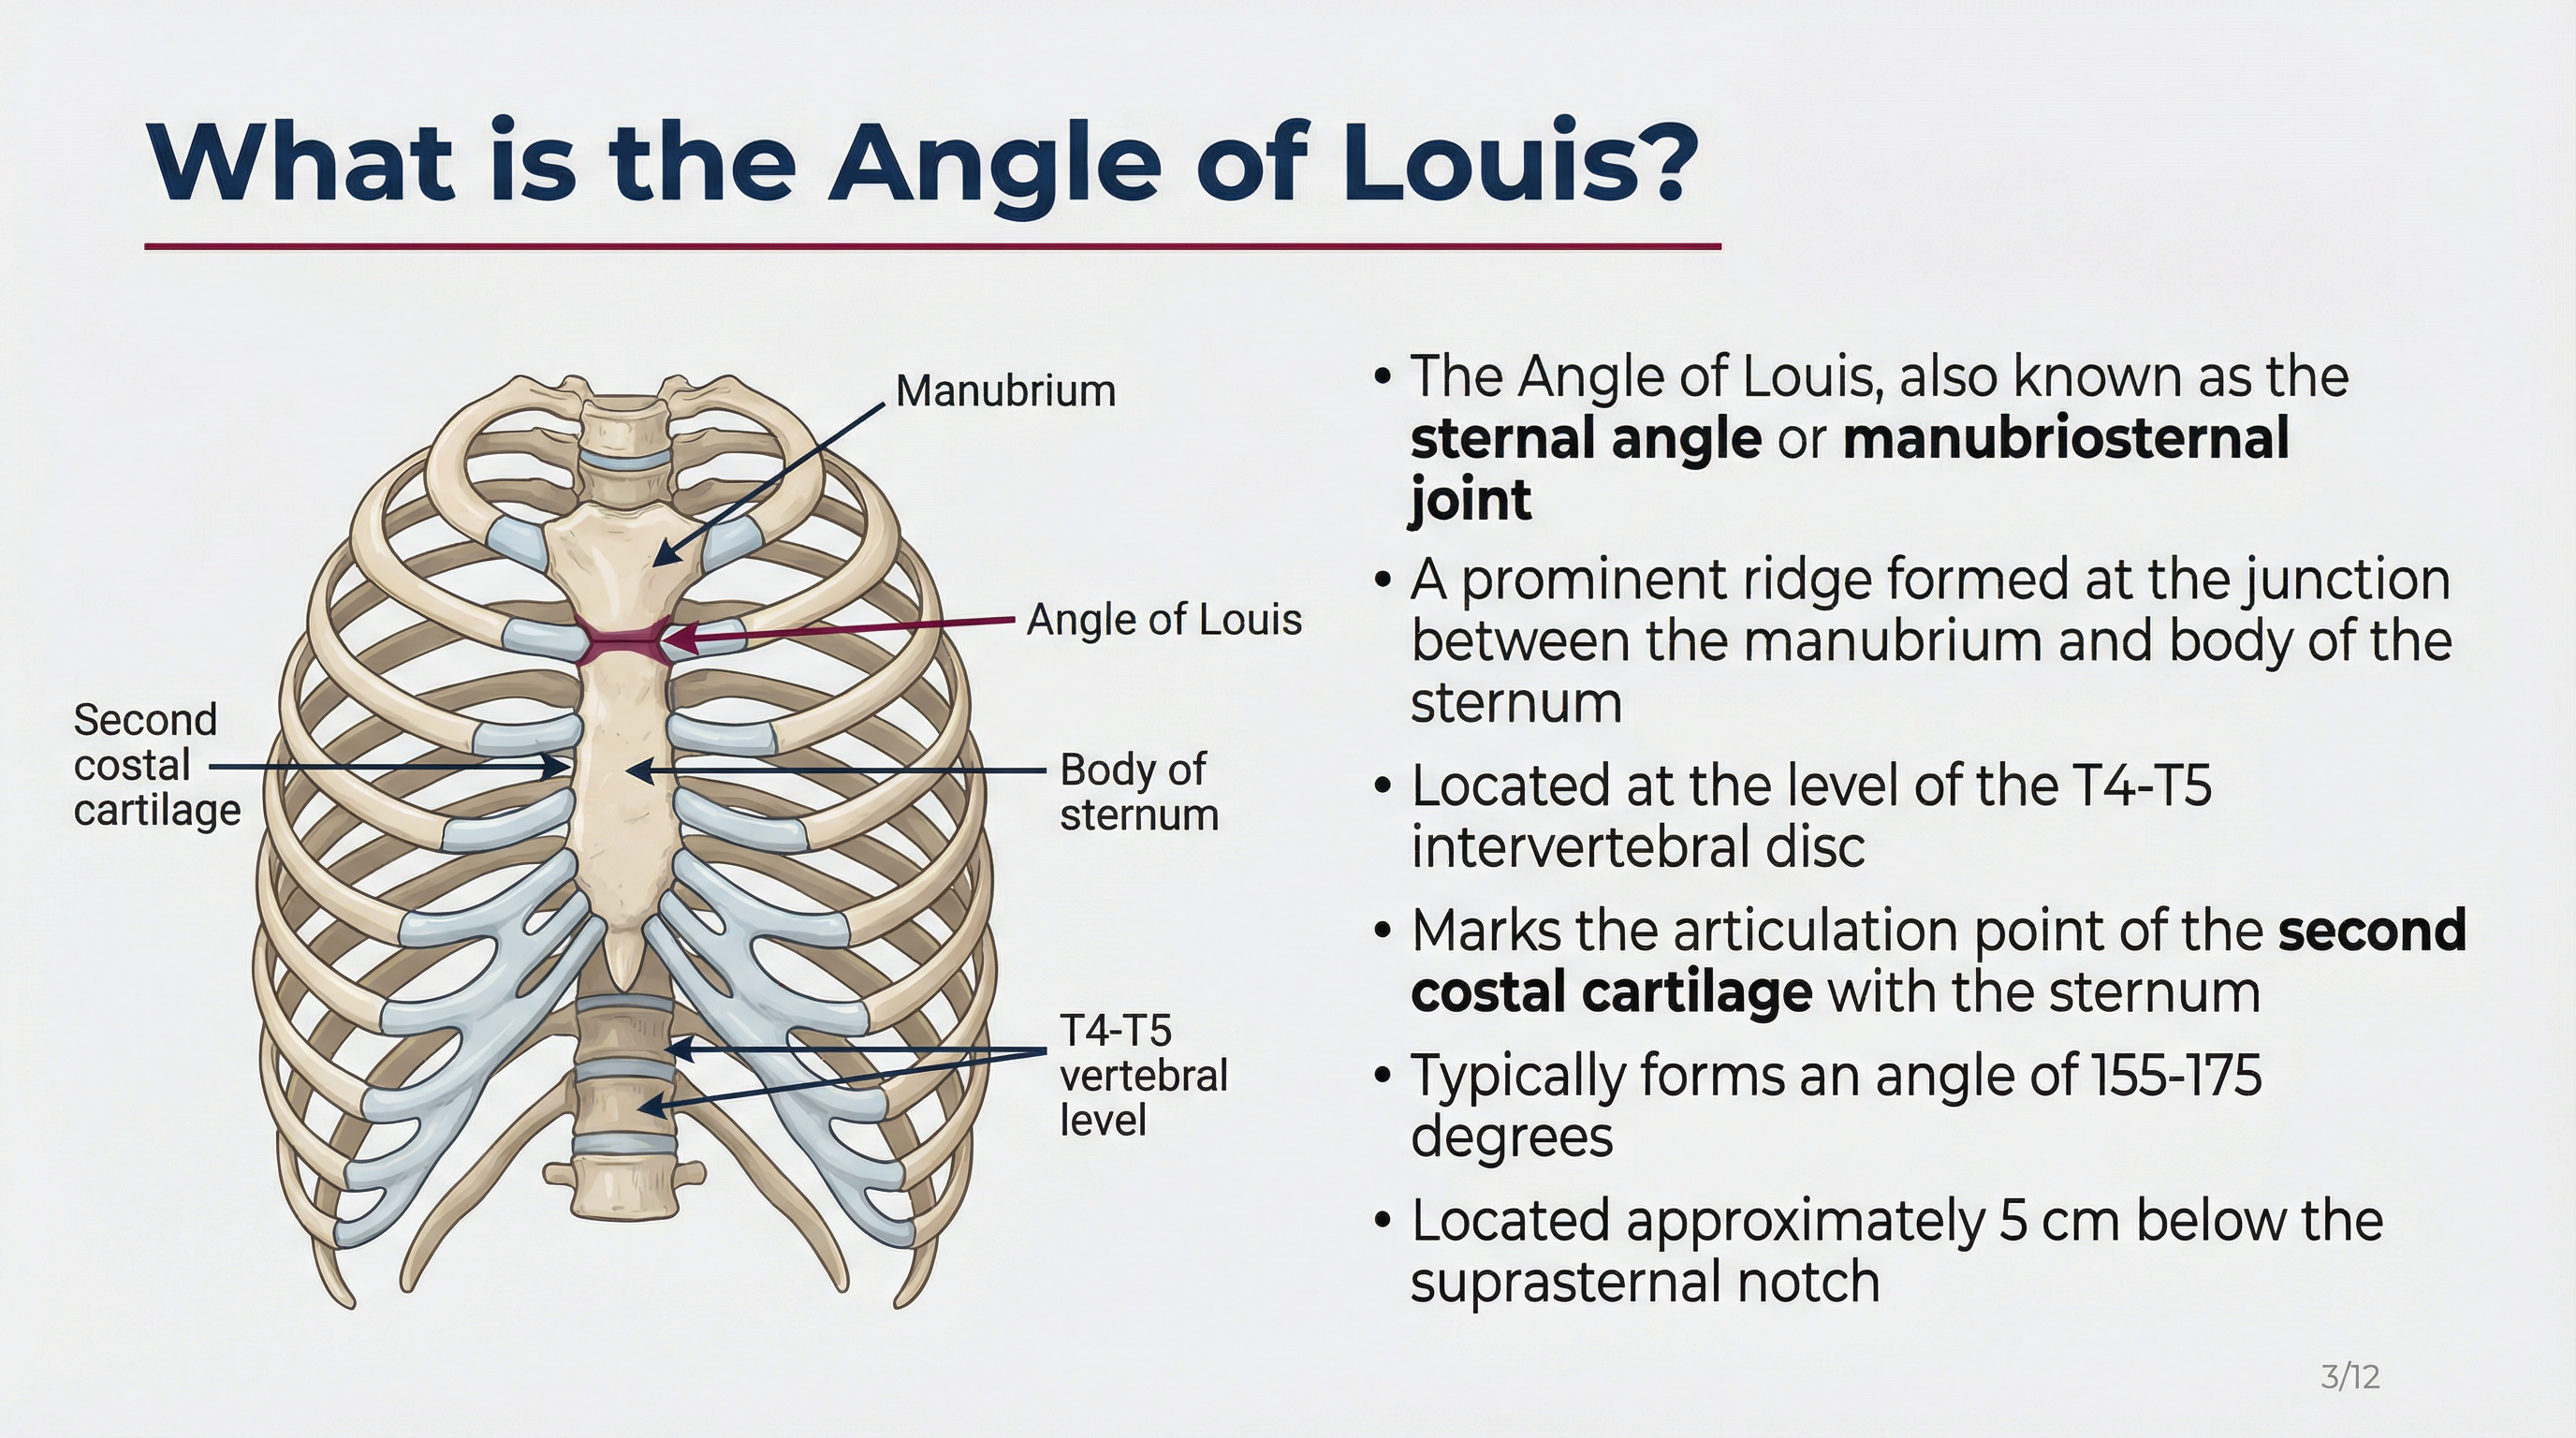
Most people learn about the sternal angle of Louis in their first year of anatomy, and then they don't think about it again until they need to use it under pressure. I've been doing this long enough that I still encounter students and junior clinicians who can name the landmark but can't find it on anything other than a perfect cadaver. The method itself is straightforward. Start at the suprasternal notch, run your fingers down the front of the manubrium, and you will feel a distinct transverse ridge about 5 cm below the notch. That ridge is the manubriosternal joint, and the angle it forms with the body of the sternum is the sternal angle of Louis. From there, follow laterally and you will immediately encounter the second rib. That is the point. Every other rib counting sequence depends on getting this right. If you start at the wrong level, you end up describing injuries and pathologies on the incorrect ribs throughout a whole case. I have seen it happen repeatedly in trauma bays where someone counted down from the fifth rib instead, which threw off their entire physical exam description and nearly led to a wrong-site decision on imaging. The sternal angle of Louis is the only reliable start point because it does not shift with body position or breathing in any meaningful way.
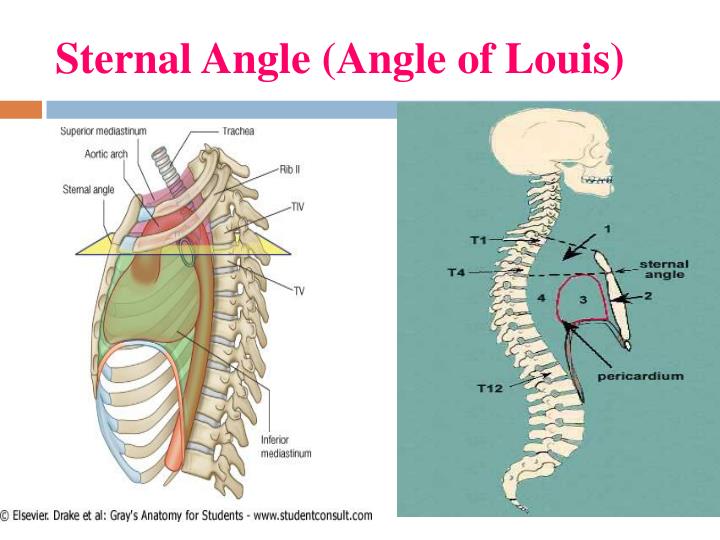
What most people miss is that the sternal angle of Louis is not just a bony bump. It is also the plane that separates the superior and inferior mediastinum on a sagittal cross-section. The aortic arch begins and ends at roughly this level. The trachea bifurcates into the left and right main bronchi at approximately T4-T5, which aligns with the sternal angle of Louis. The azygos vein arches over the right main bronchus at the same horizontal plane. These relationships matter when you are reading a chest CT or performing a thoracic procedure, not just when you are counting ribs for a percussion exam. Here is a practical nuance that never seems to get enough attention. The sternal angle of Louis is typically at the level of the intervertebral disc between T4 and T5, not the body of T4 itself. If you are correlating surface anatomy to vertebral levels on an X-ray, using T4 as your reference point will put everything half a segment too high. I ran into this specifically when I was training residents to localize a possible aortic dissection on plain film. One resident kept measuring everything off the T4 vertebral body center and was consistently locating the transverse sinus margin in the wrong anatomical window. Once we switched to using the sternal angle of Louis as the external reference and then traced that to the T4-T5 disc space on the lateral view, the measurements aligned correctly with the CT findings. It took about five minutes to fix, but it would have cost an hour of unnecessary imaging confusion if we had not caught it. Another thing worth noting is the variation in palpability. In patients with significant pectoralis hypertrophy or increased subcutaneous tissue, the sternal angle of Louis can be nearly impossible to identify by touch alone. I had a patient a while back who was moderately built and had a very deep manubriosternal angle that I could not reliably palpate for rib counting during a procedure. Instead of guessing, I used the clavicular head as a secondary landmark. The medial third of the clavicle sits at roughly the same horizontal plane as the second rib, so using both references together gave me enough accuracy to proceed without worrying about miscounting. It is not a perfect substitute, but it is functional when the primary landmark is obscured.
The sternal angle of Louis is also relevant during central venous catheterization. The internal jugular vein enters the brachiocephalic vein at approximately this level, and knowing the depth relationship helps when you are planning needle trajectory. I once watched a colleague attempt an IJ line on a patient with a pronounced sternal angle and miss the vein because they were aiming too superficially, underestimating how deep the vessel sits relative to that bony ridge. After adjusting the angle and depth, they got clean aspiration on the second pass. The landmark itself was not the problem, but their reliance on it without accounting for individual anatomical depth variation was. If you are trying to internalize this, the fastest way is to practice on live subjects rather than textbooks. Have someone lie supine, locate the suprasternal notch, slide down to the angle, and then have them take a deep breath while you keep your fingers on the second rib cartilage. You will feel it move slightly with respiration, which confirms you are on the correct structure and not just some random ridge of the manubrium. Do this on at least five different people and you will quickly understand the range of normal variation. There is one more caveat that nobody really emphasizes in textbooks. The sternal angle of Louis can be more prominent in older adults due to calcification of the manubriosternal synchondrosis. I have examined several patients in their seventies where the angle was so sharply angulated that it felt almost pathological, when in reality it was just age-related ossification. This can confuse someone who is inexperienced because they might mistake the calcified junction for a fracture callus or some other abnormality on physical exam. Knowing that this is a common age-related change prevents unnecessary panic and further workup.
Get the Full Details
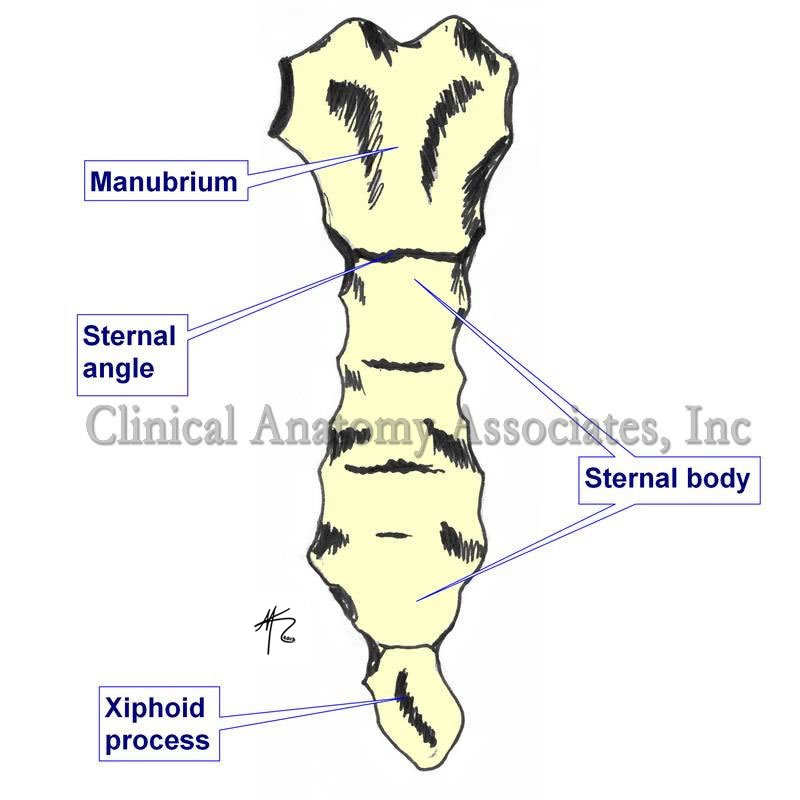
The sternal angle of Louis remains one of the most practically useful landmarks in clinical anatomy precisely because it ties together surface palpation, vertebral correlation, and mediastinal orientation in a single reference point. Spend time getting it right early, because everything else builds on it.