Setting Up and Running a Therapeutic Shockwave Device
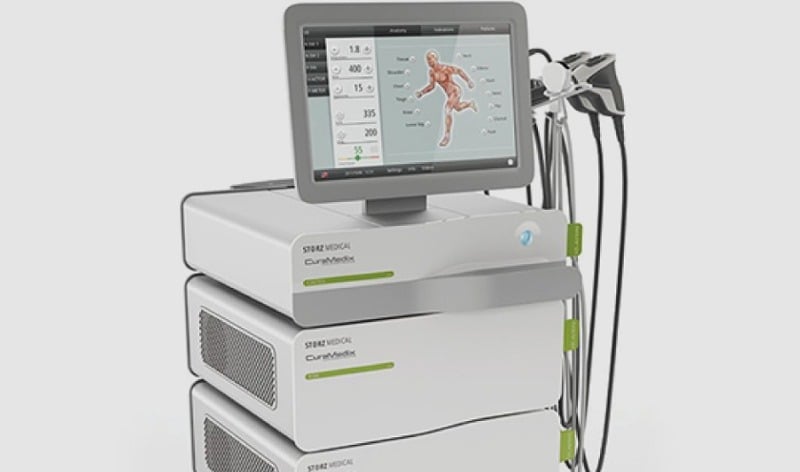
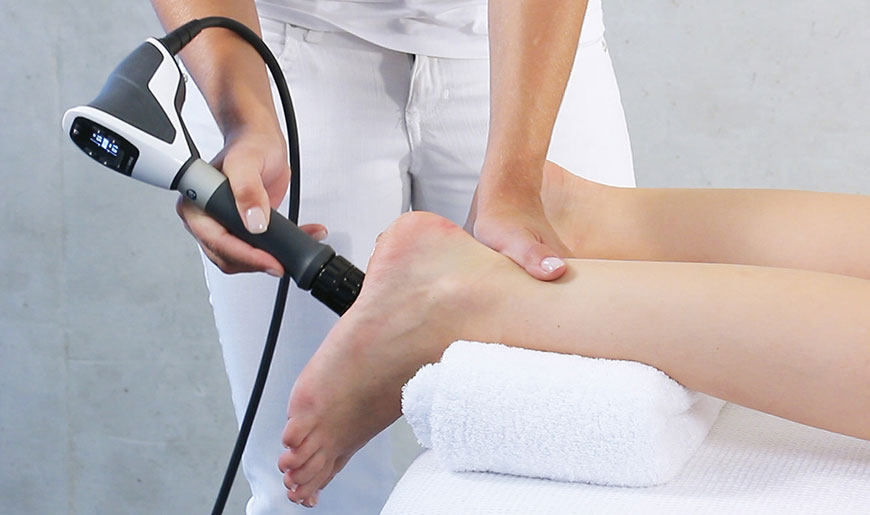
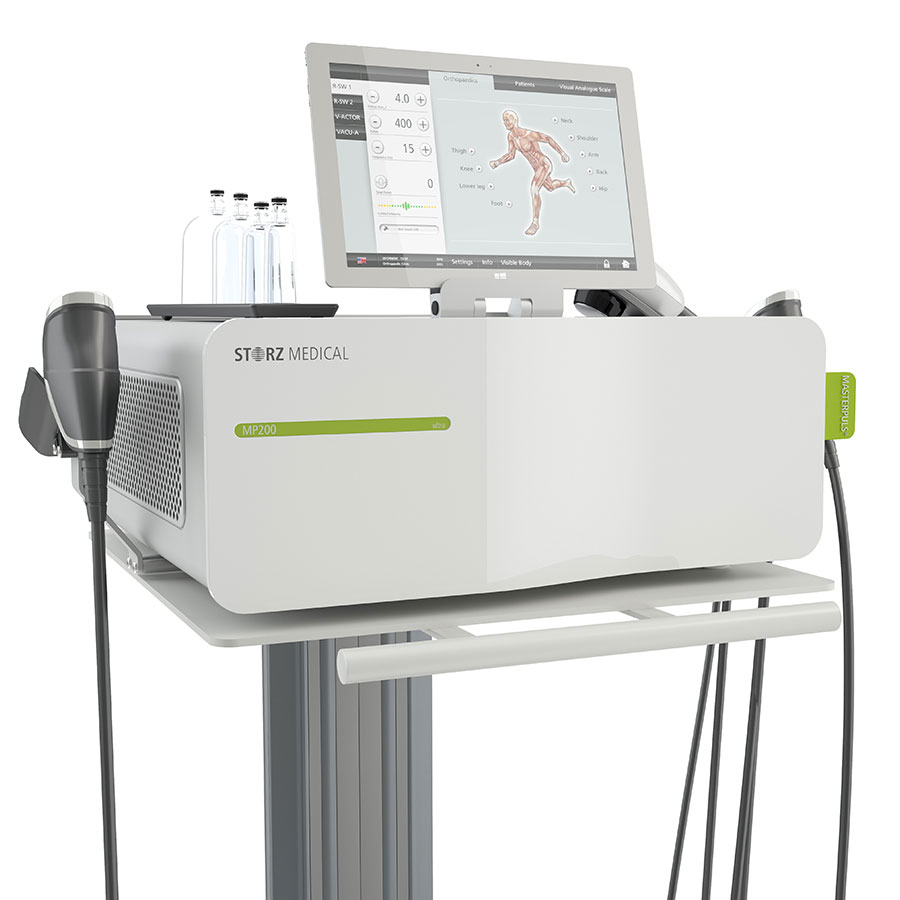
Storz Medical Shockwave Therapy covers a range of devices for extracorporeal shock wave therapy (ESWT). The line includes the Duolith SD 100 series, the STORZ, and the Piezotron units. Each serves slightly different clinical niches. I work with these machines on a regular basis and there are practical things you need to understand before you start applying them to patients. Before you even power on the device, you need to know what transducer you're working with. There are two main types: radial pressure wave applicators and focused electromagnetic or piezoelectric applicators. The radial ones deliver a broad, shallow energy field useful for surface-level soft tissue issues like Achilles tendinopathy or lateral epicondylitis. The focused units penetrate deeper and are better suited for plantar fasciitis, calcific shoulder tendonitis, or non-union fractures. The workflow starts with patient positioning. If you're treating a trigger point in the gluteal region with a radial applicator, the patient should be prone or lateral depending on which part of the muscle you're targeting. Mark the treatment area with a skin-safe marker before applying coupling gel. The gel layer needs to be generous—about 3 to 5 millimeters between the handpiece and skin. Too little gel and you get air pockets that scatter the energy and produce inconsistent results. Too much and you waste energy before it reaches the target tissue.
Energy settings are measured in millijoules per square millimeter (mJ/mm²) for focused devices or bar for radial ones. Start low. Most protocols begin at 0.08 to 0.12 mJ/mm² for focused therapy. For radial units, I typically start around 1.5 to 2.0 bar. Increase in increments of 0.02 mJ/mm² or 0.3 bar between passes. The patient should feel a deep, penetrating pressure. Sharp or stabbing pain means you're either too superficial or hitting a nerve. Back off immediately. The standard treatment duration for most musculoskeletal conditions falls between 1,500 and 3,000 impulses. That takes roughly 5 to 10 minutes depending on the frequency setting. Frequency is usually 4 to 8 Hz for acute conditions and 8 to 12 Hz for more chronic presentations. Higher frequencies increase tissue heating, which is fine for subacute cases but can be counterproductive in acute inflammatory stages where you want to minimize thermal load. After treatment, the treated area may look slightly erythematous. That's normal. Minor bruising can occur especially in patients on anticoagulants or with fragile capillary beds. Apply ice if there's significant discomfort. Most patients report immediate pain reduction after the first session, though the full therapeutic effect builds over the following 2 to 4 weeks as neovascularization and tissue remodeling take place.
I ran into a specific problem last year that I haven't seen discussed much in the literature. A patient with severe calcific tendinopathy of the supraspinatus had a dense, layered calcium deposit that was sitting just beneath the joint capsule. Standard focused ESWT at 0.15 mJ/mm² wasn't fragmenting it effectively. The energy was being reflected off the surface layer before it could break up the deeper deposit. I switched to a stepped protocol: starting at 0.08 mJ/mm² to gently disrupt the superficial calcium layer, then progressively increasing to 0.22 mJ/mm² over three separate sessions spaced one week apart. By the third session, the deposit was sufficiently fragmented for the higher energy to reach the deeper layers. A single high-energy pass on the first session would have caused significant pain and possibly microtrauma to the surrounding tissue without actually breaking up the core deposit. This stepping approach cut the total treatment sessions from what would have been four or five down to three, and the patient achieved clinical improvement faster. There are real limitations to this technology. It does not work well for osteoarthritis of the hip or knee beyond mild early-stage cases. The energy doesn't penetrate deep enough to meaningfully affect joint structures. You'll see some temporary pain relief from the neuromodulatory effects, but you're not reversing any structural degeneration. Patients with those conditions often leave with false expectations. Be clear about what the treatment can and cannot do during the consultation. Contraindications include pregnancy over the lumbar or abdominal region, coagulopathies, active infection in the treatment area, tumors or malignant lesions in the field, and proximity to the lung, heart, or central nervous system. Never treat directly over the carotid sinus or the optic nerve. These aren't edge cases—they're hard stops.
Get the Full Details
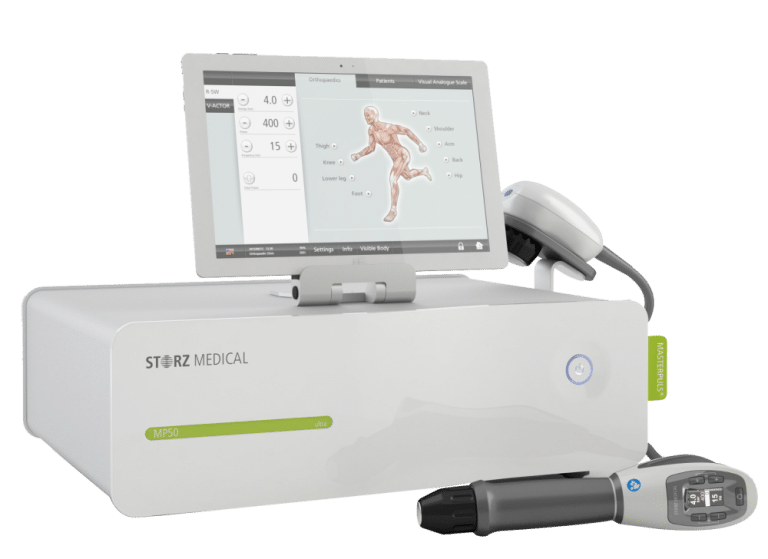
Equipment maintenance matters more than most clinics acknowledge. The coupling surface of the handpiece should be inspected before every session. Micro-scratches accumulate from repeated gel application and cleaning. Those scratches create air gaps that degrade energy transmission. Replace the transducer tip when you notice visible wear. Clean the handpiece with manufacturer-approved solutions only. Alcohol-based cleaners can degrade the acoustic matching layer over time. I use chlorhexidine-based wipes and check the transmitter surface with a magnifying lens every few weeks. The battery life on portable units like the STORZ is generally rated for 4 to 6 hours of continuous use. In practice, if you're running sessions back to back with frequent parameter changes, expect closer to 3 hours. Keep a spare battery or AC adapter on hand. There's nothing worse than a half-finished treatment because the unit died.
What to Expect Clinically
Success rates vary by condition. Plantar fasciitis responds in about 70 to 80 percent of cases after 3 to 5 sessions. Lateral epicondylitis shows similar response rates. Calcific shoulder tendinopathy has a higher success rate with focused ESWT, around 80 to 85 percent for medium to large deposits. Non-union fractures remain one of the strongest indications with success rates exceeding 90 percent in appropriate candidates. The weakest evidence base is for greater trochanteric pain syndrome and patellar tendinopathy, where outcomes are mixed and heavily dependent on operator technique and patient selection. If a patient shows no improvement after 3 sessions, reassess the diagnosis. You may be treating the wrong structure or the condition may not be responsive to shockwave therapy. Continuing with the same parameters past that point rarely produces different results. The device interfaces typically include a USB port and sometimes Bluetooth for protocol documentation and software updates. Storz Medical provides clinical management software that logs treatment parameters for each patient. Use it. Having a detailed record of energy levels, impulse counts, and frequency settings across sessions makes it easier to adjust protocols and demonstrates clinical diligence if questions arise later.
Operator safety is straightforward but often overlooked. You don't need special shielding or protective gear beyond standard clinical precautions. The shockwave energy is directional and dissipates rapidly outside the treatment field. Just keep your hands clear of the transducer face during activation. Even at low settings, direct contact with the transmitter surface can cause discomfort or minor tissue injury to the operator's fingers. The initial investment for a Storz Medical unit ranges significantly depending on the model. The radial pressure wave devices are on the lower end, while the focused electromagnetic systems like the Duolith SD 100 Sport HP represent a substantial capital outlay. Factor in ongoing costs for coupling gel, handpiece maintenance, and occasional calibration. The cost per session for the clinic typically breaks down to roughly 2 to 5 minutes of active treatment time against the equipment depreciation and consumable costs. For most outpatient clinics, the ROI becomes positive within the first year if you're running a reasonable patient volume. Training is something you shouldn't skip. Storz Medical offers hands-on workshops, but the learning curve is steeper than the manufacturer materials suggest. Understanding tissue response at different energy levels takes clinical experience. Watch experienced operators before you rely solely on the manual. The difference between a competent and a poor outcome often comes down to subtle adjustments in handpiece angle, pressure against the skin, and impulse distribution pattern that aren't covered in the documentation.