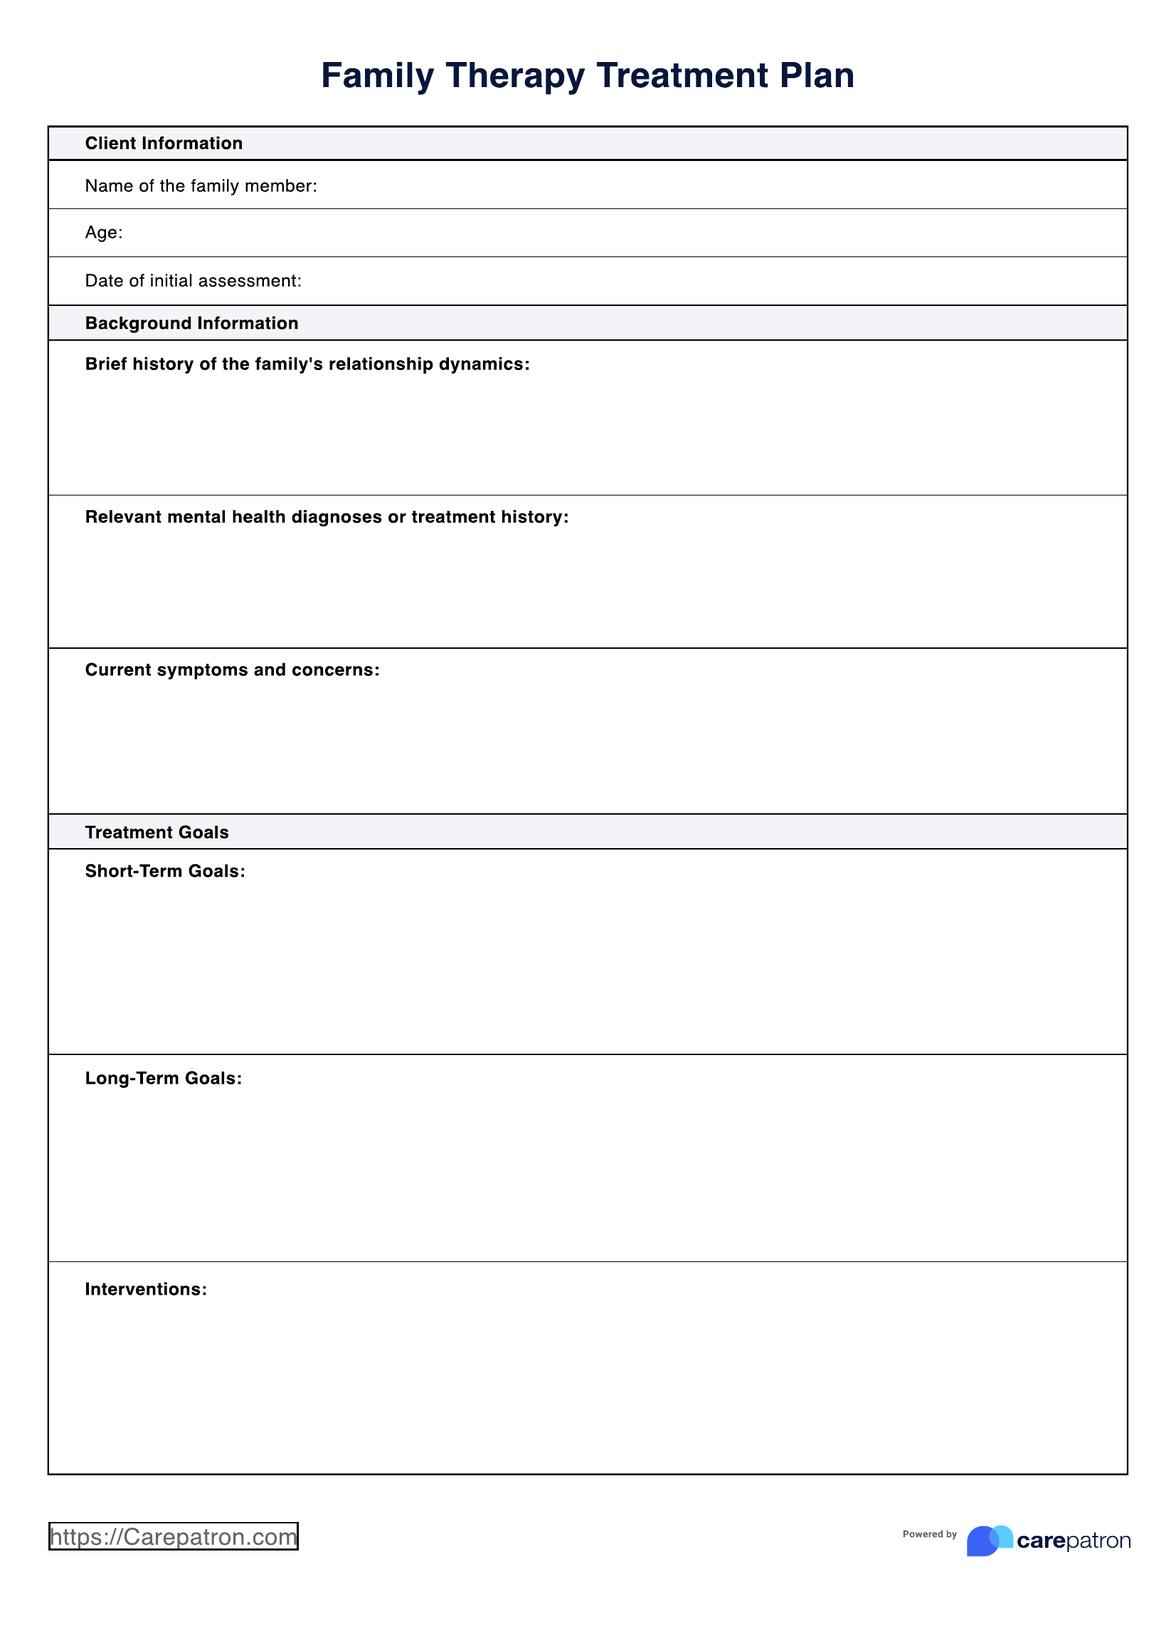
Strategic Family Therapy Treatment Plan Example
I used to work in outpatient mental health clinics where we had to produce treatment plans every single session for insurance. Strategic Family Therapy is one of those modalities where the plan looks very different from what you might expect coming from CBT or psychodynamic work. The strategy part is the hard part to pin down on paper because a lot of the actual therapeutic change happens through what gets prescribed between sessions, not just what happens in the room. A treatment plan in strategic family therapy starts the same way as other models. You gather the referral information, you identify the presenting problem, and you figure out which family subsystem is generating or maintaining it. But then you diverge quickly because the diagnosis is less about labeling internal pathology and more about mapping the interactional sequence. The problem is not inside anyone. The problem is a pattern the family is stuck in.
Building a Strategic Family Therapy Treatment Plan Example
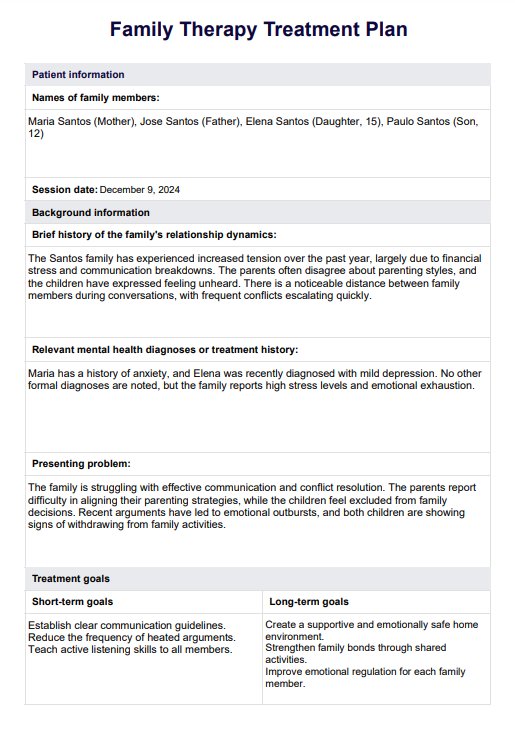
Here is how I used to actually write one, not the textbook version but the version that survived insurance review and also worked in practice. The first section is always the problem list. I would write it in behavioral terms that are observable. "Child refuses to attend school more than three days per week and engages in prolonged crying and physical resistance during morning transitions." Not "child has anxiety." Insurance doesn't pay for vague concepts and neither do strategic therapists. After the problem list comes the family interactional formulation. This is where most people mess it up. You need to describe the cycle. Who initiates, who responds, what maintains it. I usually draft something like this: "Mother expresses concern through repeated questioning and reminders. Father disengages by withdrawing to another room. Child escalates distress when left unsupervised, resulting in mother increasing monitoring and father remaining absent from the escalation. Problem behavior is reinforced by increased maternal attention and decreased parental conflict." The goals section should be specific and measurable. I wrote two or three goals maximum per session plan. Something like: "Reduce school refusal incidents from five days per week to two days per week within four weeks." and "Increase co-parental communication regarding child management from zero to three structured interactions per week." Keep them narrow enough that you can actually track them.
The interventions are the part that requires real knowledge of the model. Strategic therapy uses specific techniques. I used directive tasks, reframe, paradoxical interventions, and boundary work. In the treatment plan I would document what I actually planned to do. For example: "Prescribe the symptom. Parents instructed to have child deliberately engage in school refusal behavior for ten minutes each evening during the designated 'worry period.' Goal is to remove unintentional reinforcement and shift control of the behavior to the family system." I once dealt with a case involving a sixteen-year-old girl who had been missing school for six months. The presenting problem was the school refusal. The strategic formulation revealed that the parents were actively using the girl's symptoms to avoid confronting their own nearly-divorced relationship. Every time they tried to have a difficult conversation about finances, she would spiral into a panic episode. The cycle was self-maintaining because the symptom served a homeostatic function. The intervention was not straightforward. Standard CBT protocols for school refusal would have failed here because they treat the behavior as the target. I prescribed a paradoxical intervention where the parents were told they must send her to school every single day regardless of her state, and if she refused, they were to remain calm and neutral without discussion. I also prescribed a shift where the parents were instructed to schedule weekly meetings without her present to discuss their financial situation. The idea was to make the symptom lose its function. She had to choose: keep using the panic or let the parents deal with their own issues.
Get the Full Details
After three sessions the girl began attending school. Not perfectly. But the pattern broke. The parents reported that they had their first real argument about money without the child escalating. That was the data point that confirmed the formulation was correct. When you write the treatment plan for this kind of case, the interventions section needs to reflect that precision. I wrote: "Conduct family session to address homeostatic maintenance of symptom. Implement directive intervention requiring parents to manage school attendance without child-centered escalation. Introduce structured co-parental task unrelated to child's behavior. Monitor frequency of parental conflict avoidance and child symptom use." That is specific enough to follow and specific enough for an auditor to understand what you are doing. There are some significant limitations to this approach that nobody likes to talk about in training programs. Strategic therapy requires the therapist to be highly directive and comfortable with confrontation. Some clinicians simply cannot do it. They default to empathic reflection and the whole model collapses. I have seen many young therapists try strategic interventions while unconsciously providing warmth that undermines the directive component. The paradoxical prescriptions become recommendations and the family laughs and does nothing.
Another limitation is the time horizon. Strategic therapy is supposed to be brief. Eight to twenty sessions typically. That works well for focused interactional problems. It does not work when there is co-occurring substance abuse, untreated trauma, or significant cognitive impairment in a family member. I had a case where the strategic formulation was perfect and the intervention logic was sound, but the father had active alcohol dependence that disrupted every structured task. The family kept missing sessions. The treatment plan looked great on paper and produced no change in the living room. In those situations you either adapt the model significantly or refer out for concurrent substance abuse treatment before returning to family strategic work. The documentation side also has practical problems. Insurance reviewers often do not understand strategic terminology. When I wrote "paradoxical intervention" they wanted to know the CPT code justification. I learned to translate. "Paradoxical prescription" became "behavioral interruption technique involving structured non-compliance with symptomatic pattern." It was ridiculous but it got the plan approved. I stopped fighting the language barrier and just adapted my documentation to what the payer required while keeping the clinical logic intact. If you need a downloadable format, most clinics use the standard OASIS or ASPD treatment planning forms with a strategic addendum. I attached a simple template that covered the sections I described above: problem list with behavioral descriptors, interactional formulation, goals, interventions with technique labels, and a monitoring schedule. It took about fifteen minutes to fill out after the second session once you had the formulation locked in. Early on it took longer because I was still learning to translate the clinical observation into written form quickly.
The main thing I would tell someone just starting to use this model is to spend more time on the formulation than on the intervention design. The intervention is easy once you see the cycle. The cycle is hard. Most treatment plans fail because the formulation is wrong, not because the techniques are wrong. A wrong technique applied to a wrong formulation wastes sessions and damages the therapeutic alliance. A right technique applied to a right formulation usually produces movement within three to five sessions even if the family is resistant. I also stopped trying to document every micro-interaction in the plan itself. The formulation lives in your head and on a few pages of notes. The treatment plan is a summary document for the record. If you try to make it a complete clinical narrative you end up writing a novel that nobody reads and missing the actionable pieces. Keep it tight. There is also a nuance about which family members you include that beginners consistently overlook. Strategic therapy assumes you need the key maintainers of the problem cycle in the room. That does not always mean everyone in the household. I once had a blended family where the stepfather was the primary authority figure but he was not part of the escalation cycle. Including him diluted the intervention. I left him out of the critical sessions and brought him in later for a separate structural integration session. The treatment plan reflected that decision explicitly: "Initial sessions focus on biological mother, father, and child. Stepfather included in session four for authority boundary clarification only." That level of specificity in the plan prevented confusion when the supervisor reviewed the file.
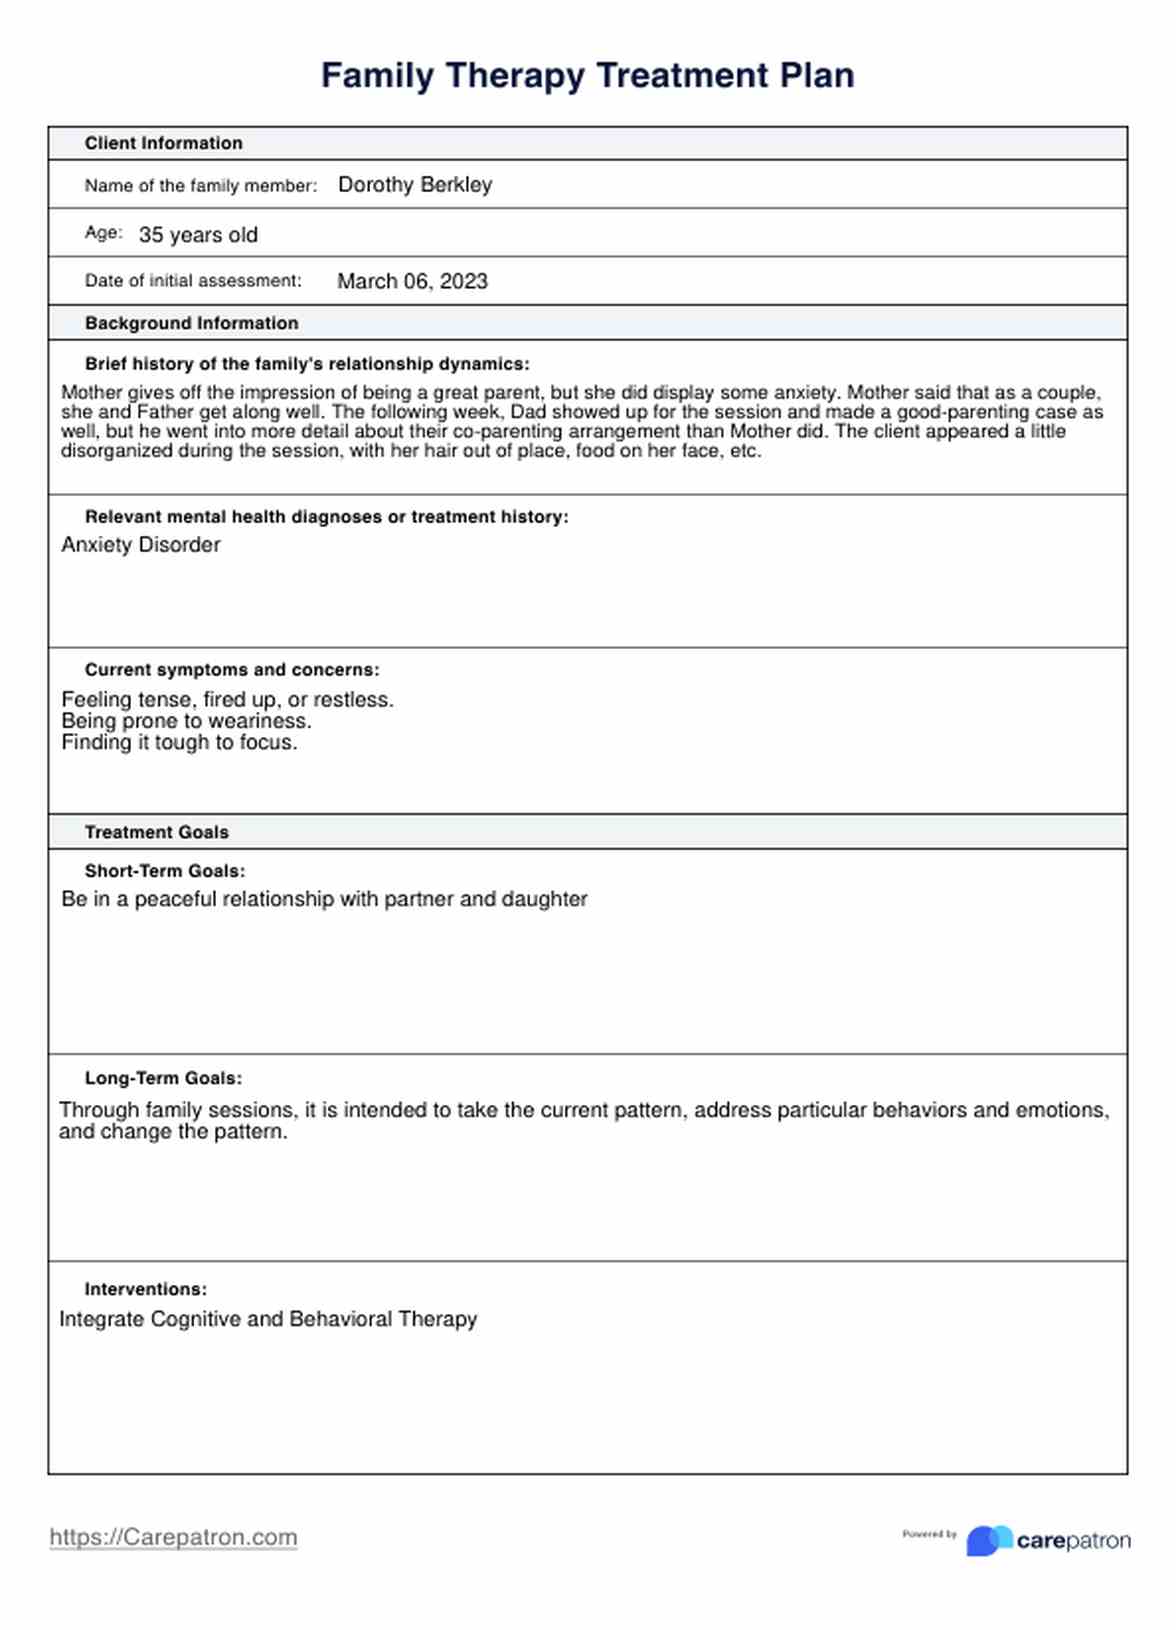
If you want to download a working version of the format I used, search for "Strategic Family Therapy Treatment Plan Example" on a few clinical resource sites. Many are free templates that you can adapt. Just remember that the template is only as useful as the formulation behind it. A blank form filled in with generic goals and vague interventions will not help anyone, and it definitely will not survive peer review or audit.