Stratified Squamous Epithelial Tissue
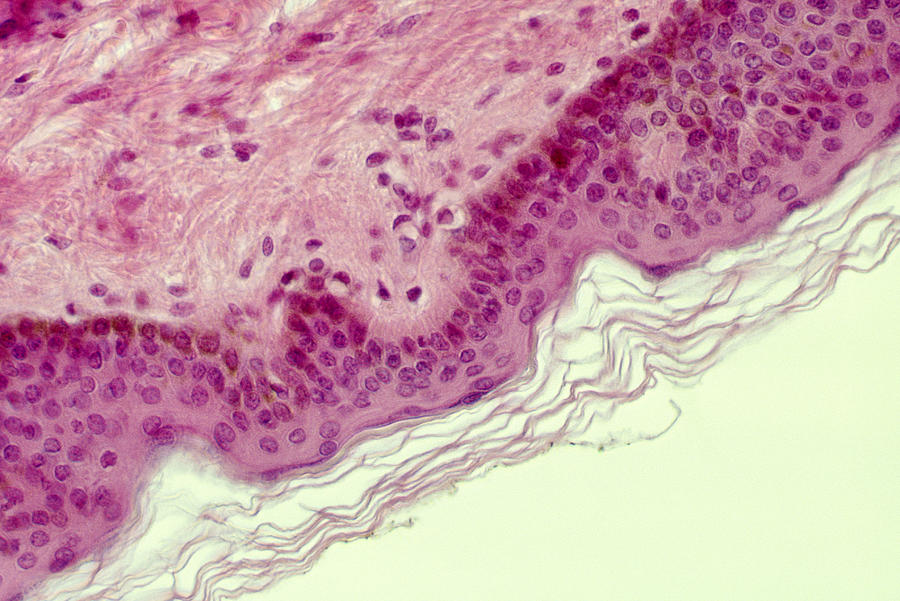
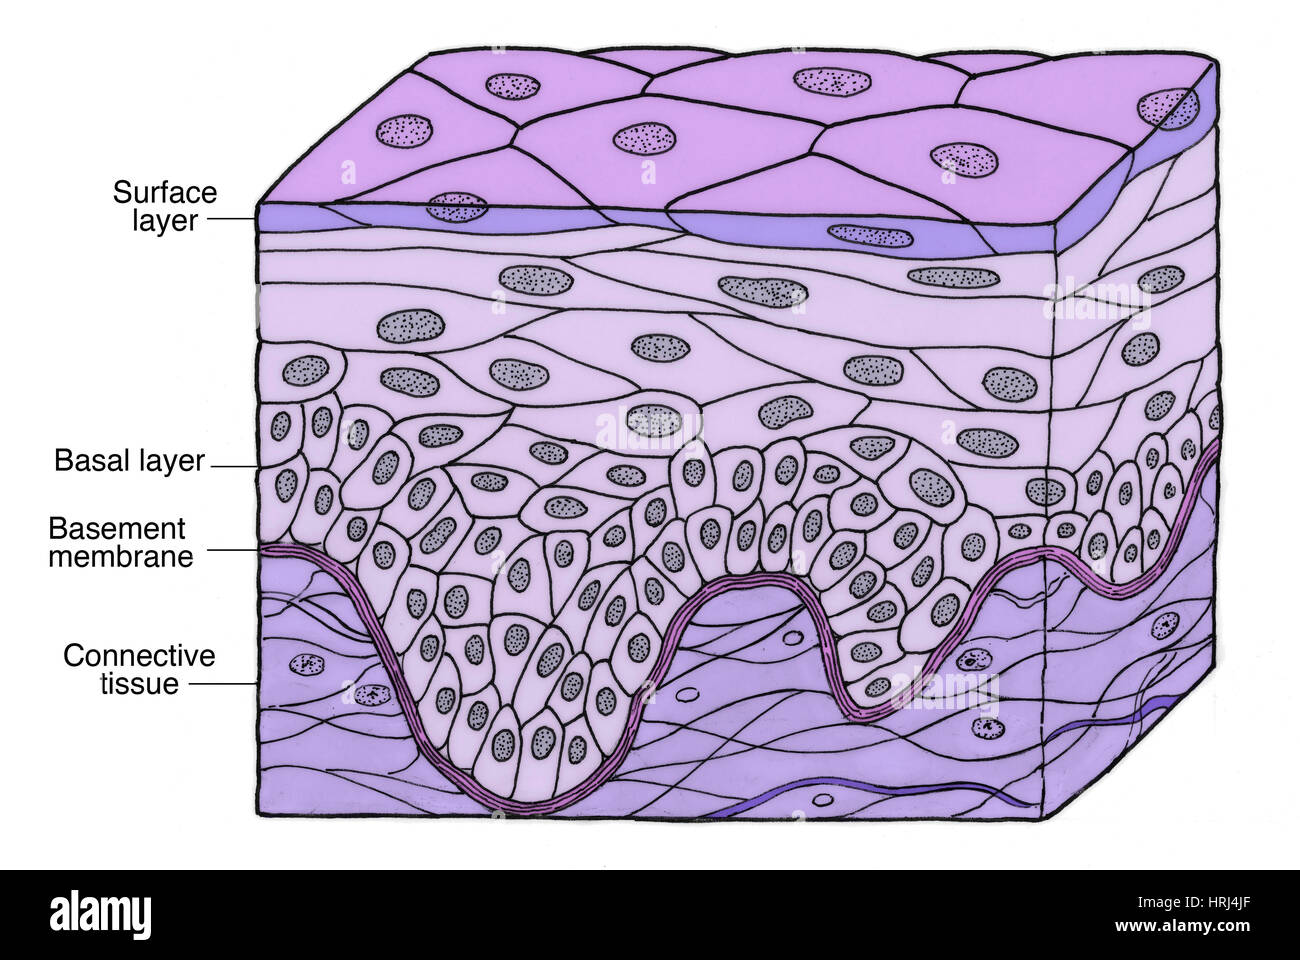
I spend most of my time looking at histology slides of this stuff. It is one of the more common tissues you will encounter in any practical lab or clinical setting, and it is also one people consistently mess up the description of. The basic definition is simple enough: multiple cell layers, with the surface cells being flattened. But the details matter more than you would think if you are actually trying to identify it under a microscope or work with it in a procedure. The tissue is made of several layers of cells stacked on top of each other. The bottom layer, called the stratum basale, contains cuboidal to columnar cells that are actively dividing. As those daughter cells get pushed upward, they change shape. They become more polygonal in the stratum spinosum, then increasingly flattened as they reach the surface. In keratinized versions, like the epidermis of your skin, the outermost cells are essentially dead, filled with keratin protein and lacking nuclei. In non-keratinized versions, like the lining of your mouth or esophagus, the surface cells are still alive but still flattened and thin. The keratinized type is what keeps you from falling apart in a dry environment. The non-keratinized type handles abrasion in wet, mucosal areas where keeping the surface moist is more important than creating a waterproof barrier. Both types provide mechanical protection, but they do it in different ways and for different reasons.
I ran into a specific issue last year when a colleague was preparing slides from a biopsy of the oral mucosa. They were trying to differentiate between hyperplasia and early dysplasia in the stratified squamous epithelial tissue, and the routine H&E stain was not giving them enough contrast at the basal layer. The problem was that the tissue had been fixed in formalin for too long before processing, which caused excessive cross-linking and made the nuclear detail harder to see. The workaround was straightforward: I had them decalcify a parallel section using a mild EDTA solution for 48 hours instead of the usual acid-based method, then re-stain with a modified PAS that highlights the basement membrane more clearly. It added about three hours to the workflow, but it made the distinction readable instead of a guess.
Things Beginners Get Wrong
The biggest mistake I see is assuming that the number of cell layers directly correlates with the level of protection. It does not. A tissue with five or six layers can be less protective than one with three layers if the surface keratinization is thicker and more continuous. What actually matters is the integrity of the terminal barrier, not the raw count of layers. You can have a thick mucosa that sheds its surface cells rapidly and still be functionally fragile if the underlying attachment to the basement membrane is compromised. Another common error is treating keratinized and non-keratinized varieties as if they respond the same way to injury. They do not. Keratinized epithelium heals by re-epithelialization from adjacent skin and hair follicle remnants. Non-keratinized mucosal epithelium heals differently because there are no adnexal structures to draw cells from. If you are working with wound models, this distinction changes everything about your timeline and your expected outcome.
Get the Full Details

Practical Identification Under the Microscope
When you are looking at a slide and need to confirm stratified squamous epithelial tissue quickly, focus on two things: the shape of the surface cells and the presence or absence of keratin. Surface cells that are clearly flattened and scale-like, with no keratin layer visible, point toward non-keratinized. If you see a distinct pink, anucleate layer on top, it is keratinized. The basal cells should be roughly uniform in size and shape, arranged in a single row along the basement membrane. If that row becomes irregular or multilayered, you are looking at a pathological change, not normal tissue. Staining choice matters. H&E works for general identification, but if you need to assess the degree of keratinization or evaluate the basement membrane zone, a trichrome stain or direct immunofluorescence for collagen IV and laminin-332 will give you cleaner data. Routine H&E can make the basement membrane look intact when it is actually fragmented, especially in early blistering conditions.
Limitations and When This Tissue Falls Short
Stratified squamous epithelial tissue is tough, but it is not indestructible. The keratinized version fails badly in chronically wet environments because the keratin layer can macerate and slough off, leaving the underlying tissue exposed. The non-keratinized version fails in dry environments because it lacks the waterproofing that prevents desiccation. Neither type regenerates efficiently once damage extends past the basal layer into the lamina propria. Scar formation replaces functional epithelium with fibrous tissue, and that scar tissue does not restore the original barrier function. If you need a tissue that can regenerate a complete, functional barrier after deep injury, stratified squamous epithelium is the wrong model. Skin grafts and engineered epithelial sheets are the practical alternative in those cases. They provide a more reliable reconstruction, though they come with their own set of complications around graft take and vascularization. The tissue is straightforward in principle but unforgiving when you ignore the differences between its variants. Knowing which variant you are dealing with and what it is actually built to handle will save you from a lot of incorrect conclusions.