Where Stratified Squamous Epithelium Actually Lives
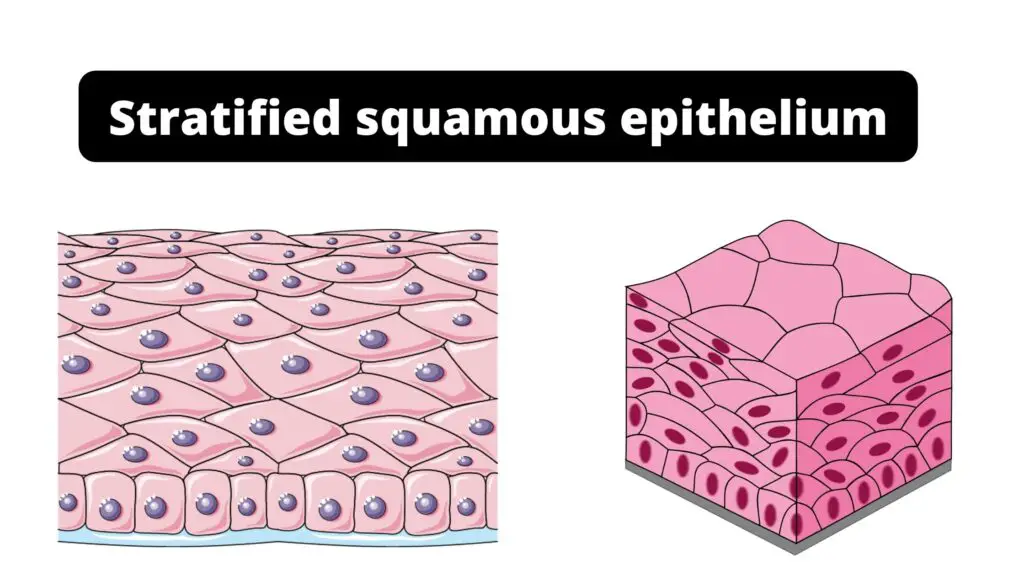
I spent three semesters grading histology slides and the number of students who couldn't tell whether a sample was from the esophagus or the trachea was genuinely staggering. Let's get this sorted once and for all. Stratified squamous epithelium Location is fundamentally tied to mechanical stress. This tissue type exists wherever the body needs a barrier that can literally rub itself into oblivion and regenerate faster than anyone notices. It lines surfaces that deal with abrasion, desiccation risk, or both simultaneously. The structural principle is simple: multiple cell layers stacked on top of each other, with flat (squamous) cells dominating at the surface. The basal layer constantly divides, pushing newer cells upward where they flatten and eventually slough off.
Understanding Stratified Squamous Epithelium Location in the Body
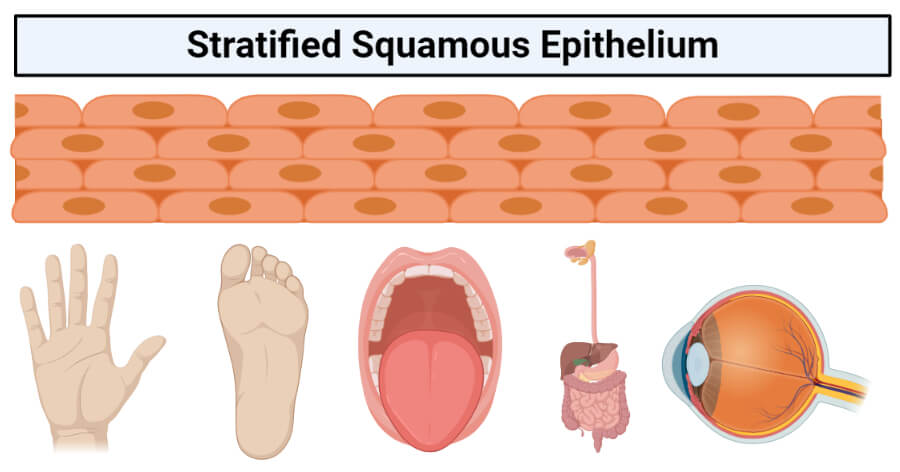
Here's the practical breakdown of where you will and won't find this tissue, organized by clinical relevance rather than textbook order. The skin (epidermis) is the most obvious location, but it's also the most misunderstood. The epidermis is keratinized stratified squamous epithelium, and the keratin layer you see under the microscope is dead cells packed with keratin filaments. This is your primary barrier against pathogens, water loss, and physical damage. The stratum corneum alone can be twenty to thirty cell layers thick on the palms and soles. On the face, it's maybe four to six. Thickness varies dramatically based on friction exposure. The oral cavity uses non-keratinized or parakeratinized stratified squamous epithelium depending on the specific region. The hard palate and gingiva are masticatory mucosa — they get chewed on, so they're orthokeratinized. The buccal mucosa (inner cheek), floor of the mouth, and ventral tongue are lining mucosa and remain non-keratinized. This distinction matters clinically because lesions present differently on keratinized versus non-keratinized surfaces. A white patch on the hard palate could be benign hyperkeratosis from thermal trauma. The same appearance on the buccal mucosa raises more concern.
The esophagus is lined with non-keratinized stratified squamous epithelium throughout its entire length. This is a common exam question and a common gastrointestinal pathology site. Gastroesophageal reflux disease causes Barrett's esophagus, where the body attempts to repair chronic acid damage by replacing the squamous epithelium with columnar epithelium — a process called intestinal metaplasia. That metaplastic change is a recognized precancerous condition. The transition zone between squamous and columnar epithelium is the Z-line, and it's visible endoscopically as an irregular jagged border. When that border becomes smooth and proximal, you're looking at Barrett's. The vagina and ectocervix share the same non-keratinized stratified squamous epithelium. Estrogen drives glycogen accumulation in the intermediate cell layers, which lactobacilli then convert to lactic acid. This creates the acidic vaginal pH that protects against pathogenic overgrowth. Postmenopausal estrogen decline thins this epithelium significantly — atrophic vaginitis is essentially a consequence of epithelial thinning. Cervical screening (Pap smears) literally samples cells from this stratified squamous lining to detect dysplasia. The anal canal above the dentate line retains non-keratinized stratified squamous epithelium. Below the dentate line, it transitions to skin with keratinized stratified squamous epithelium. This anatomical boundary has real clinical consequences because the vascular and neural supply differs on either side. Internal hemorrhoids arise above the dentate line and are typically painless because visceral innervation dominates there. External hemorrhoids below the line are painful because somatic sensation is present.
Get the Full Details
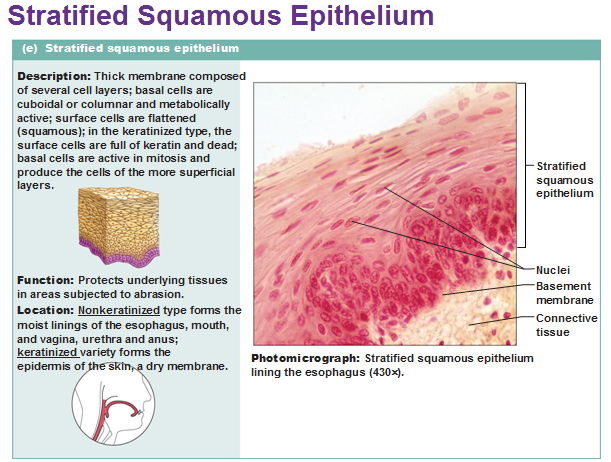
The cornea and conjunctiva of the eye use stratified squamous epithelium, though the corneal epithelium is uniquely thin — only five to six cell layers — and highly regenerative. Corneal abrasions that involve only the epithelium typically heal within twenty-four to forty-eight hours without scarring because this epithelium turns over rapidly. However, if the injury penetrates the Bowman's layer into the stroma, healing occurs through fibrosis and corneal scarring, which can permanently affect vision. The male urethra has a variable epithelial lining. The navicular fossa (distal portion near the meatus) is lined with non-keratinized stratified squamous epithelium. The rest of the urethra transitions through pseudostratified and columnar epithelium proximally. Urethral strictures can develop at any point but are most common in the bulbar and membranous segments where the epithelium differs. One thing nobody emphasizes enough: the basement membrane beneath stratified squamous epithelium is the critical boundary for staging cancers. In squamous cell carcinoma, once malignant cells breach the basement membrane and invade the underlying connective tissue, the staging changes fundamentally. An in situ carcinoma (carcinoma in situ) is confined above the basement membrane and has near-zero metastatic potential. The moment invasion occurs, lymphatic and vascular access opens up. This is why precise identification of the basement membrane on histology slides isn't academic — it determines whether a tumor is stage 0 or stage 1 or worse.
A practical detail from my own slide-grading experience: students frequently misidentified the location of lymphoid aggregates. In the esophagus and anal canal, normal lymphoid tissue can be present in the lamina propria and submucosa. I've seen multiple students flag this as pathological lymphoid infiltration when it was simply normal immune surveillance. The presence of lymphoid follicles in these regions doesn't automatically indicate chronic inflammation or lymphoma. Context matters — look for architectural preservation, lack of cytologic atypia, and absence of destructive invasion patterns before calling anything pathological. The interplay between stratified squamous epithelium Location and vitamin A deficiency is another understated point. Vitamin A maintains the integrity of all epithelial tissues, but stratified squamous epithelium is particularly sensitive. Deficiency causes keratinizing metaplasia — surfaces that should remain moist and non-keratinized begin producing keratin. The conjunctiva develops Bitot's spots. The respiratory epithelium loses cilia and becomes keratinized, impairing mucociliary clearance. This isn't just a textbook fact — it's a clinically observable sequence that reverses with vitamin A supplementation if caught before structural damage becomes permanent. So to answer the original question directly: stratified squamous epithelium Location spans from the external surface of the body (skin) to internal tubular structures subjected to friction and abrasion. The key variable is keratinization status, which correlates with the degree of exposure to the external environment and mechanical stress. Wherever you see this tissue type, ask what kind of wear and tear that particular location endures. The histology always reflects the function.