
Working with Stratified Squamous Non Keratinized Tissue Under the Microscope
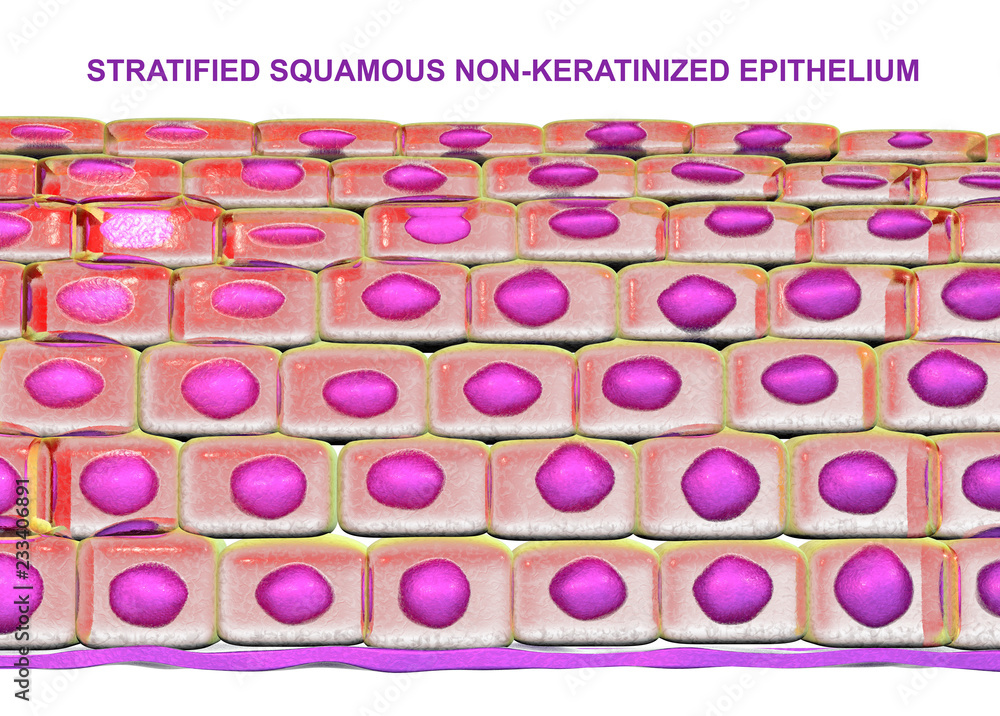
You pull a slide out of the staining rack and you're looking at stratified squamous non keratinized epithelium. It's everywhere in the body — lining the inside of your cheeks, the floor of your mouth, the esophagus, the vagina, the cornea's surface. The layers are what you'd expect: basal cells at the bottom, progressively flattening as they move up, and the topmost cells still holding onto their nuclei because there's no keratin layer killing them off. That's the textbook version. The real version is messier. The non-keratinized variant stays moist. That's the whole point. The cells at the surface don't undergo the same terminal differentiation that turns cells into flat, anucleate scales. They remain viable, nucleated, and wet. In a well-stained H&E prep, the superficial layers appear as several rows of flattened cells with distinct, dark purple nuclei. The cytoplasm is pale pink and somewhat translucent compared to the deeper layers. Under 40x magnification, you should be able to count roughly five to seven cell layers from the basement membrane to the free surface. Fewer than that and you're probably looking at atrophy or a sectioning artifact. More than ten and you might be dealing with hyperplasia or just a thick chunk of tissue that didn't get trimmed properly. I spent three days once trying to figure out why a batch of esophageal biopsies kept coming back looking weirdly pale in the superficial layers. Turned out the lab tech had been rinsing the slides under running tap water for too long after the hematoxylin step. The prolonged rinse was leaching out some of the staining complexes from those delicate superficial cells. Sixty seconds in a gentle stream is plenty. I just flagged it in the QA log and moved on. Nothing dramatic, just one of those small things that ruins a whole run if you're not watching.
How to Process and Identify It Correctly
Start with the fixation. Ten percent neutral buffered formalin for six to twelve hours is standard. Don't go longer than that on thin mucosal biopsies — over-fixation makes the cytoplasm look glassy and the nuclei hard to distinguish, which is a real pain when you're trying to tell whether those surface cells are actually still nucleated or if you've just lost contrast. Paraffin embedding at around 56 to 60 degrees Celsius works fine. Sections at four to five microns. Thinner and the superficial layers get distorted during mounting. Thicker and you're stacking too many cell layers on top of each other, making it hard to count accurately. For staining, the standard H&E protocol gets you most of the way there. Hematoxylin for three to five minutes, blue in warm water or Scott's tap water substitute for about a minute, then eosin for thirty to forty-five seconds. The key detail most people miss is the dehydration sequence. These tissue types hold water. If you rush through the alcohol series — say, skipping the 95 percent ethanol step or giving the xylene only thirty seconds — you'll end up with cloudy slides and poor nuclear detail. I use a gradual series: 70 percent for two minutes, 95 percent for two minutes, two changes of 100 percent for two minutes each, then two xylene changes for three minutes. It adds about four minutes to the protocol but the difference in clarity is night and day, especially in those thin superficial cytoplasmic borders. Here's something I wish someone had told me earlier: the boundary between keratinized and non-keratinized stratified squamous epithelium is not always as clean as the diagrams make it look. In the distal esophagus, for example, you can get zones of metaplasia where chronic acid exposure causes the normal non-keratinized lining to gradually shift toward a keratinized phenotype. On a single section, this can look like you're seeing parakeratin — cells at the surface that are flattened but still retain pyknotic nuclei. It's easy to misread this as a normal variant when it's actually Barrett's-related change. I learned this the hard way when a colleague and I spent two weeks debating whether a particular GI biopsy showed "normal esophageal mucosa with artifactual surface changes" before we finally agreed to re-cut the block at a deeper level and saw the dysplastic transition zone we'd missed. The workaround was straightforward — go back to the original block, cut serial sections every twenty microns through the lesion, and map the transition. Took about an hour but saved us from sending out a misleading report.
Common Pitfalls and What to Do About Them
Compression artifact is the big one. Stratified squamous epithelium is soft and layered. If your microtome knife is even slightly dull or your sectioning angle is off, the top layers fold over each other like a deck of cards that got dropped. You end up with what looks like massive hyperplasia — maybe fifteen to twenty layers when the tissue should only have five or six. The tell is that the folded layers look disorganized, with nuclei pointing in random directions rather than maintaining that neat perpendicular orientation you see in real hyperplasia. If you spot this, adjust your blade angle, change the knife, or accept that you need to re-section a different area of the block. It usually saves ten to fifteen minutes compared to trying to diagnose through a compressed section. Another issue specific to non-keratinized tissue: drying artifact. Unlike keratinized epithelium, which has a tough outer layer that protects it, non-keratinized superficial cells are basically unprotected. If your tissue section dries out even slightly during staining — say, if the slide sits on the rack between steps for too long — those top cells will shrink and pull away from the layers below. You get vacuolization, crenation, and nuclei that look overly dense. Some people call this "artifact" and dismiss it. But I've seen it cause real misdiagnoses, particularly in cervical cytology where the distinction between a benign processing artifact and actual koilocytic change matters. The fix is simple — keep the slides wet through the entire staining process, don't let them air dry between reagents, and mount immediately after the final xylene clear. Total extra time: maybe thirty seconds per slide. Worth it. One more thing that isn't covered in any textbook: the effect of pH on staining quality. Non-keratinized stratified squamous epithelium tends to stain slightly more basophilic in the intermediate layers than you'd expect, and this varies depending on the pH of your hematoxylin solution. If your hematoxylin has drifted alkaline — and routine tap water can push it that way within a few weeks — the cytoplasm will grab more dye than it should, making the whole tissue look artificially dark and muddy. Check your hematoxylin pH monthly. Keep it between 3.2 and 3.6 for optimal nuclear-cytoplasmic contrast. A fresh prep costs you about twenty minutes of setup but keeps your diagnostic accuracy honest.
Get the Full Details
Stratified Squamous Non Keratinized — When It Fails You
This tissue type has real limitations that nobody talks about enough. First, it's extremely difficult to do reliable immunohistochemistry on routine formalin-fixed sections of non-keratinized stratified squamous epithelium because the endogenous peroxidase activity in these cells is high and the tissue is so rich in glycogen that antigen retrieval can over-digest the architecture. If you need marker expression data, fresh frozen sections give you cleaner results, but you're trading convenience for quality. Second, thin sections of this tissue — below three microns — tend to tear at the superficial layers during deparaffinization because those cells lack the structural integrity that keratin provides. Stick to four to five microns minimum. Third, in conditions like lichen planus or chronic friction, the epithelium can become so inflamed and disorganized that distinguishing true dysplasia from reactive atypia becomes nearly impossible on H&E alone. You need special stains or molecular markers, and even then the specificity drops significantly. I've had cases where three pathologists reviewed the same slide and two called it mild dysplasia and one called it reactive — and in the end, the clinical follow-up over six months showed it was reactive. The morphology just wasn't decisive enough.


