How to Actually Use the SDQ in Practice
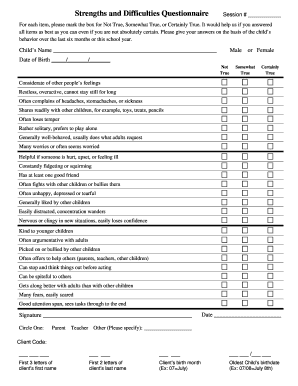
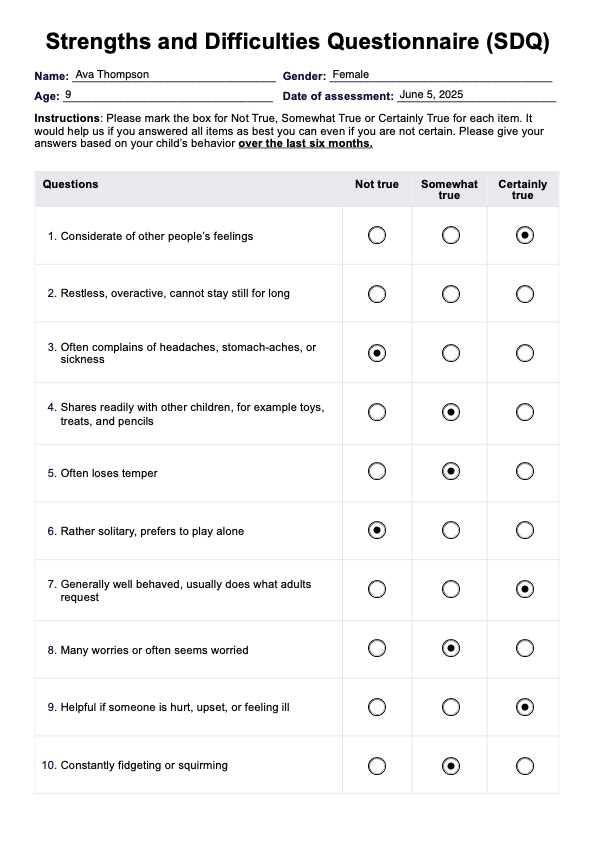
The Strengths And Difficulties Questionnaire is a brief behavioral screening tool. It has 25 items split across five subscales: emotional symptoms, conduct problems, hyperactivity/inattention, peer relationship problems, and prosocial behavior. Parents, teachers, and sometimes the children themselves fill it out. The whole thing takes roughly five minutes, gives you a total difficulty score, and flags kids who might need a deeper look. That last part is the important one — it is a screener, not a diagnosis. Each item is scored 0, 1, or 2. For most subscales, higher scores mean more difficulties. The prosocial scale is reversed — higher means better. The total difficulty score ranges from 0 to 40. The official cutoff bands are labeled borderline, abnormal, or normal, and those cutoffs shift depending on age and whether it is a parent or teacher report. That detail matters because a lot of people just plug numbers into an online calculator and treat the result like it came from a lab. It does not come from a lab. It comes from a large UK sample collected in the early 2000s. I ran into a specific edge case recently where a 14-year-old boy was referred for possible ADHD. His teacher SDQ hyperactivity score was solidly in the abnormal range, but his parent report showed borderline hyperactivity and significant emotional symptoms instead. The discrepancy alone should have been a signal. When I went back through the items, the teacher had marked nearly every hyperactivity item as "rather true," but the emotional symptoms subscale told the real story — he was struggling with social anxiety and school refusal, and the restlessness was a symptom of that, not a primary attention disorder. If I had stopped at the hyperactivity subscale score, we would have been pointing him toward the wrong pathway. The workaround was straightforward: use the discrepancy as a referral for a full clinical assessment rather than a confirmation of any single issue.
Scoring and Interpretation Nuances
One thing beginners routinely miss is that the subscale scores are not independent. High hyperactivity and high peer problems often co-occur, and high emotional symptoms frequently mask as conduct problems in boys. You cannot treat each subscale as its own little verdict. The pattern across scales is where the signal lives. A child with elevated emotional symptoms and elevated peer problems, for example, presents a very different clinical picture than a child with elevated conduct problems and hyperactivity, even if both have the same total difficulty score. Another counter-intuitive point is how informant disagreement functions. A lot of people treat parent-teacher agreement as a quality check — low agreement means unreliable data. In practice, low agreement is usually informative data in itself. It tells you the child's behavior is context-dependent. That is clinically relevant. A kid who is only difficult at home behaves differently than a kid who is difficult everywhere. The mismatch itself guides intervention planning more than either score does alone.
Where the SDQ Breaks Down
The tool has real limitations. It does not measure psychosis, trauma disorders, or autism spectrum traits. It was never designed to. If you are using it to screen for those, you are misusing it. The subscales are also fairly broad. Hyperactivity lumps together inattention and impulsivity, so a child who is primarily inattentive without hyperactivity may not stand out clearly. The conduct problems subscale includes rule-breaking and aggression but does not distinguish between oppositional defiant disorder and more severe conduct issues. Cutoff scores are normed on UK populations from 2003 to 2005. Translating those cutoffs directly to other countries or more recent cohorts can be inaccurate because prevalence rates and reporting styles have shifted. I have seen schools in other European countries use the UK cutoffs without adjusting, which inflated the abnormal category by roughly 10 to 15 percent compared to local norms. The SDQ website does publish some translated versions, but the norming data is still uneven across regions. Self-report becomes unreliable below about age 11, and even then older children sometimes game the scale, either intentionally or because they do not understand the response options. The "sometimes" and "certainly" framing helps younger kids, but it also introduces variance — two kids who actually behave similarly might land on different scores simply because one has a harder time self-assessing frequency.
Get the Full Details

Practical Download and Administration
You can get the questionnaires directly from the SDQ website at sdqinfo.com. They offer free versions in English and many other languages, along with scoring templates and detailed guidance documents. The parent and teacher versions are separate. There is a youth self-report form for ages 11 to 17. All of them follow the same 25-item structure. When you administer it, make sure the person filling it out understands they should base their answers on the past six months, not just the current week. A bad week skews the score. Make sure teachers fill out the teacher version independently — if a teacher has seen the parent version first, it introduces bias. I keep a simple policy: every report is completed separately and then scores are compared afterward, not discussed before scoring.
Scoring the Strengths And Difficulties Questionnaire Quickly
For manual scoring, you add up the relevant items per subscale. The item mapping is published in the official guidance. Parent and teacher forms are identical in item content, which makes cross-informant comparison clean. Self-report uses the same items but the response anchors feel slightly different to younger respondents, so I usually double-check the returned scores for odd patterns — a self-report with every item scored as 2, for instance, almost never reflects reality. The free SDQ website also offers an online scoring tool where you can enter responses directly and get the subscale breakdown plus the total difficulty score with the appropriate cutoff classification. It cuts the process down to under three minutes per form, compared to maybe fifteen if you are doing it by hand and cross-referencing the scoring table each time. The SDQ is useful because it is cheap, quick, and gives you something to act on. It is not useful when you treat it as a complete assessment or try to make it do work it was never built for. Use it as a starting point. Follow up the flagged scores with actual clinical evaluation when you need to know what is going on.