How to Actually Understand the Eye Without Getting Lost in Terminology
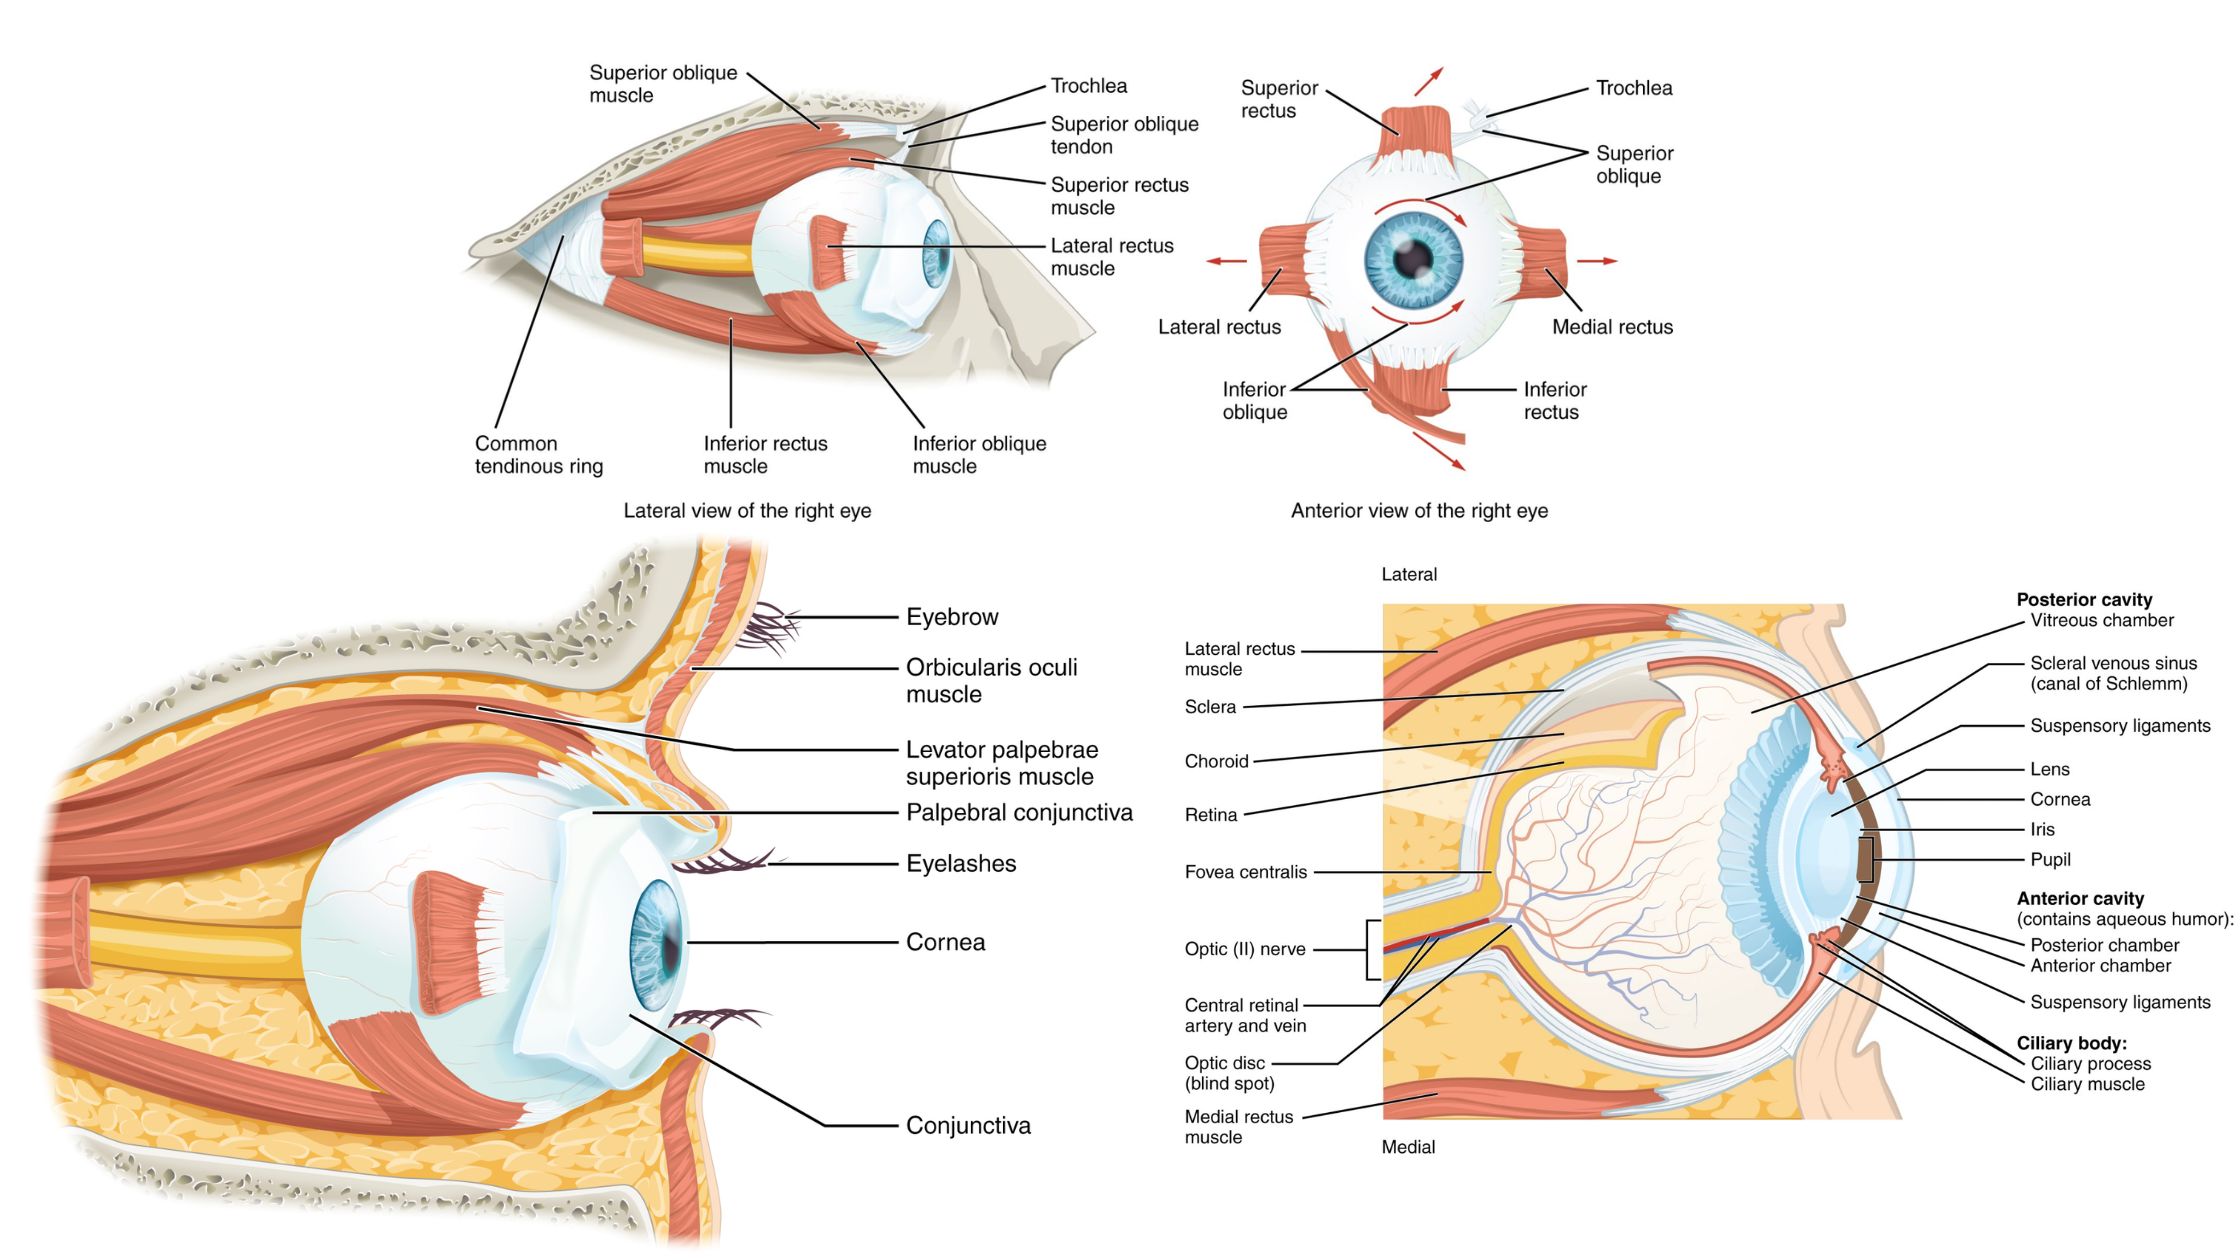
Most anatomy textbooks treat the eye like a camera, and that analogy breaks down pretty quickly once you get past the basics. A camera has a fixed lens, interchangeable glass elements, and a flat sensor. The human eye is built from living tissue that actively remodels itself, maintains its own pressure, and sends half its processing power straight back to the brain for pre-filtering before you're even consciously aware of an image. That mismatch matters when you are trying to teach Structure And Function Of The Eye to anyone who will actually need to apply this knowledge clinically or surgically. I spent about three years working with donor corneas for transplant training, and the thing that always catches people off guard is how much refractive work the cornea does before light ever reaches the lens. Roughly two-thirds of the eye's total focusing power comes from the cornea's curvature and its air-to-tissue interface. The lens provides the remaining third, but it also does the fine-tuning through accommodation. When you lose endothelial cell function and the cornea starts to swell, that refractive shift isn't linear. I once had a case where a patient's corneal edema changed their effective prescription by almost four diopters just from overnight fluid accumulation, and standard refraction couldn't stabilize it until the swelling went down over several days of hypertonic saline drops. The cornea has five layers, and only one of them regenerates predictably. The endothelium, the innermost cell layer, pumps fluid out of the stroma to keep the cornea transparent. Those cells don't divide after early adulthood. You are born with about 2,000 to 3,000 endothelial cells per square millimeter, and they drop roughly one percent per year after age forty. By seventy, you might be down to twelve hundred. Below eight hundred, corneal decompensation becomes a real risk, and that is why cataract surgeons monitor endothelial cell counts before surgery. One bad phaco session can wipe out twenty to thirty percent of your remaining endothelial budget in a single afternoon.
The Lens Hardens, It Doesn't Get Weak
Presbyopia, that age-related loss of near focus, is one of those things everyone experiences but almost nobody understands correctly. People assume the ciliary muscle weakens with age. It doesn't. The problem is the lens nucleus, the inner core of the lens, gradually becomes denser and less elastic. The accommodation mechanism still works fine, but the lens can't change shape anymore because it has literally turned into something closer to cartilage than flexible tissue. I explain it to patients using a rubber ball analogy: the ciliary muscle is still squeezing, but the ball inside is now made of cured epoxy. No amount of squeezing is going to deform it. The lens also keeps growing throughout life, adding new fiber layers like a tree adding rings. That is why cataract surgery doesn't just remove opacity, it removes a significant chunk of intraocular volume. Surgeons have to account for that when selecting the power of the artificial intraocular lens implant, or the post-op refraction will be off. A standard calculation uses axial length, keratometry readings, and a predicted lens position, but if the surgeon removes a thicker-than-average lens nucleus, the effective capsule bag position shifts forward, and the calculated IOL power needs adjustment. Missing this by even a millimeter can leave a patient at plus two or minus two after surgery, which feels brutal to someone who was emmetropic their whole life.
The Retina Is Brain Tissue, Not Film
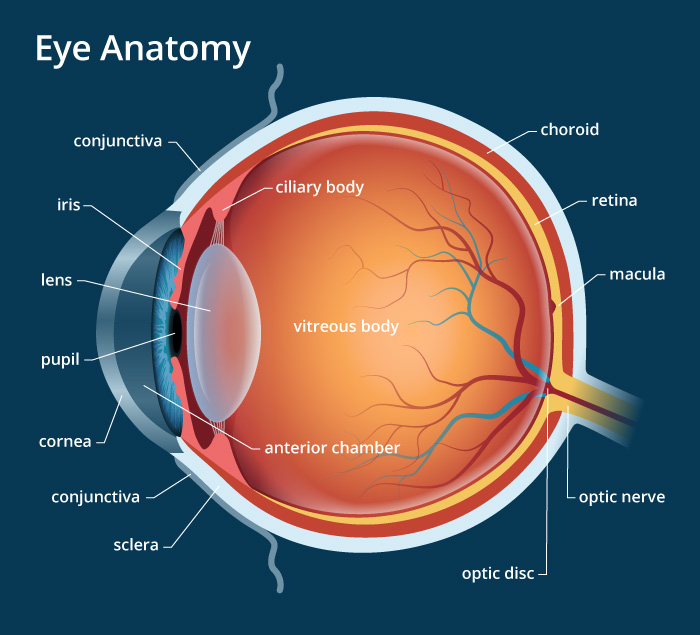
This is the biggest conceptual mistake people make, and it cascades into every misunderstanding about retinal disease. The retina is an outgrowth of the diencephalon, the same embryonic structure that becomes the thalamus and hypothalamus. It is neural tissue wrapped inside the eyeball and fed by the choroid, which sits between the retina and the sclera. The photoreceptors, rods and cones, are backward-facing. Light has to pass through the ganglion cell layer, the bipolar cell layer, and the amacrine cells before it ever hits the photoreceptor outer segments. Evolution never fixed this because the alternative would require a completely different vascular architecture, and the choroid already provides excellent metabolic support from the back side. The consequence is a blind spot where the optic nerve exits the retina, and there are no photoreceptors there at all. Everyone has one, located about fifteen degrees temporal to the fovea. Your brain fills it in using surrounding texture and pattern matching, so you never notice it in normal vision. You can demonstrate it with a simple cross-and-dot test on paper, but most people skip that step because the explanation sounds theoretical until they actually see the gap. The blind spot also means that any optic nerve pathology, glaucoma, ischemic optic neuropathy, or compressive lesion shows up as a specific visual field defect that neurologists can localize back to the nerve or chiasm. Rods and cones distribute unevenly across the retina. The fovea, a small depression about one-fifth of a millimeter across, contains almost exclusively cones packed extremely tightly. That is where your highest acuity lives, and it is also where blood vessels disappear to avoid scattering light. The rest of the macula has a mix, and beyond that peripheral retina is rod-dominated. This is why central retinal artery occlusion causes immediate profound vision loss while peripheral retinal detachments can progress for weeks before the patient notices anything. The periphery handles motion detection and low-light vision, not detail. People who lose peripheral vision from retinitis pigmentosa describe it as tunnel vision, but it is more accurate to call it loss of spatial context. They can read and drive, but they cannot navigate a crowded room without bumping into things.
Get the Full Details
Intraocular Pressure and the Fluid Cycle
The eye maintains its shape through aqueous humor circulation, a continuous production-and-drainage system that keeps pressure between ten and twenty-one millimeters of mercury in a healthy adult. The ciliary body produces about two and a half microliters per minute, and that fluid flows from the posterior chamber through the pupil into the anterior chamber, then drains through the trabecular meshwork into Schlemm's canal and into the episcleral veins. If that outflow path gets blocked, pressure rises, the optic nerve head gets compressed, and ganglion cells die. Glaucoma is essentially a plumbing problem with neurological consequences. The counter-intuitive part is that intraocular pressure varies significantly throughout the day. It is typically highest in the early morning hours, right after waking, and lowest in the late afternoon. Sleep position matters too. Lying on your side can increase pressure in the dependent eye by five to ten millimeters of mercury compared to sitting upright. I have seen patients whose glaucoma seemed well-controlled on drops during office visits at 2 PM, only to have nighttime and morning pressure spikes that were doing cumulative damage. Twenty-four hour tonography or diurnal pressure curves catch that, but most primary care offices never order them because the standard office reading is easier to schedule. Aqueous humor also nourishes the cornea and lens, which have no blood supply of their own. The cornea gets oxygen from the air directly through the tear film, and the lens gets glucose from the aqueous. That is why cataracts form where they form, and why corneal transplants have different rejection profiles than other tissue transplants. The cornea is immune-privileged to a degree because it lacks lymphatic drainage, but that privilege erodes with repeated surgical trauma or severe inflammation.
Phototransduction Happens in Microseconds
When a photon hits a rhodopsin molecule in a rod outer segment, the cis-retinal isomerizes to trans-retinal, which activates the G-protein transducin, which activates phosphodiesterase, which breaks down cGMP, which closes sodium channels, which hyperpolarizes the cell. That entire cascade takes about one hundred milliseconds from photon capture to signal output. A single photon is enough to trigger a measurable response in a rod cell, though the brain usually requires about five to seven photons within a narrow time window to register a conscious flash. Cones need more light because their photopigments regenerate faster and their amplification cascade is smaller, which is why color vision dies in low light before black-and-white vision does. The hyperpolarization response is another thing that trips people up. Most neurons fire more when stimulated. Photoreceptors do the opposite. They release glutamate continuously in the dark, and light stops that release. So darkness excites the output pathway, and light inhibits it. The bipolar cells downstream sort this out into on-center and off-center responses, creating the center-surround receptive fields that form the basis of edge detection in the visual system. Without that opponent organization, you would perceive uniform gray fields where you currently see sharp boundaries. The retina is doing significant computational work before the signal ever leaves the eye.
What the Eye Cannot Do
Regenerate functional photoreceptors. Mammalian retinas cannot regrow rods or cones after damage. Some fish and birds can, and there is active research into stem-cell-derived retinal pigment epithelium transplants and gene therapies for inherited retinal dystrophies, but as of now, once those cells are gone, they are gone. Artificial retinal implants like the Argus II provide limited signal patterns that help with basic navigation, but they do not restore meaningful vision. The interface resolution is somewhere around sixty pixels across the active area, and the brain needs months to years of training to interpret those signals at all. Compensate for axial length mismatches indefinitely. Myopia, nearsightedness, is fundamentally a problem of eyeball shape. The optical system focuses light in front of the retina because the eye is too long. No eye drop, exercise, or lens will shorten the eyeball. Progressive myopia in children is associated with genetic factors and extended near work, and the only interventions that slow progression significantly are low-dose atropine drops, orthokeratology lenses worn overnight, or specialized multifocal soft contact lenses. None of these cure the underlying elongation. Once the axial length exceeds about twenty-six millimeters, the risk of retinal detachment, myopic maculopathy, and glaucoma increases substantially and permanently.

Practical Assessment: What Actually Matters in a Room Exam
If you are learning Structure And Function Of The Eye for clinical purposes, focus on three things that take seconds to check and reveal more than most comprehensive tests. First, the pupillary light reflex. Shine a light from the side into one eye and watch for both direct and consensual constriction. A relative afferent pupillary defect, where the pupil dilates instead of constricts when light swings from the good eye to the bad eye, is the Marcus Gunn pupil and indicates optic nerve or severe retinal pathology on that side. It is one of the most sensitive bedside tests for unilateral vision loss, and it takes about ten seconds to perform. Second, cover-uncover testing for strabismus. Have the patient fixate on a distant target, cover one eye, and watch the uncovered eye for any movement. If it moves to take up fixation, there is a phoria or tropia. Then switch and repeat. This detects misalignment that the brain is either compensating for or failing to control, and it distinguishes esotropia from exotropia from hypertropia without any equipment. Third, red reflex assessment. In a dimly lit room, shine an ophthalmoscope from about thirty centimeters and look at the reflection from the retina. An absent or asymmetric red reflex suggests cataract, vitreous hemorrhage, retinal detachment, or a mass in the visual axis. It sounds primitive, but it catches pathology that patients often do not notice until it is advanced. The eye is a remarkable organ, but it is not infinitely resilient. The structural compromises, the backward-facing retina, the irreversible cell loss, the pressure-dependent nerve damage, the lens hardening that everyone experiences but few understand. Knowing how it actually works, not just how it is labeled in a diagram, makes the difference between memorizing facts and recognizing when something is failing.