Learning Bones Doesn't Require A Fancy Method
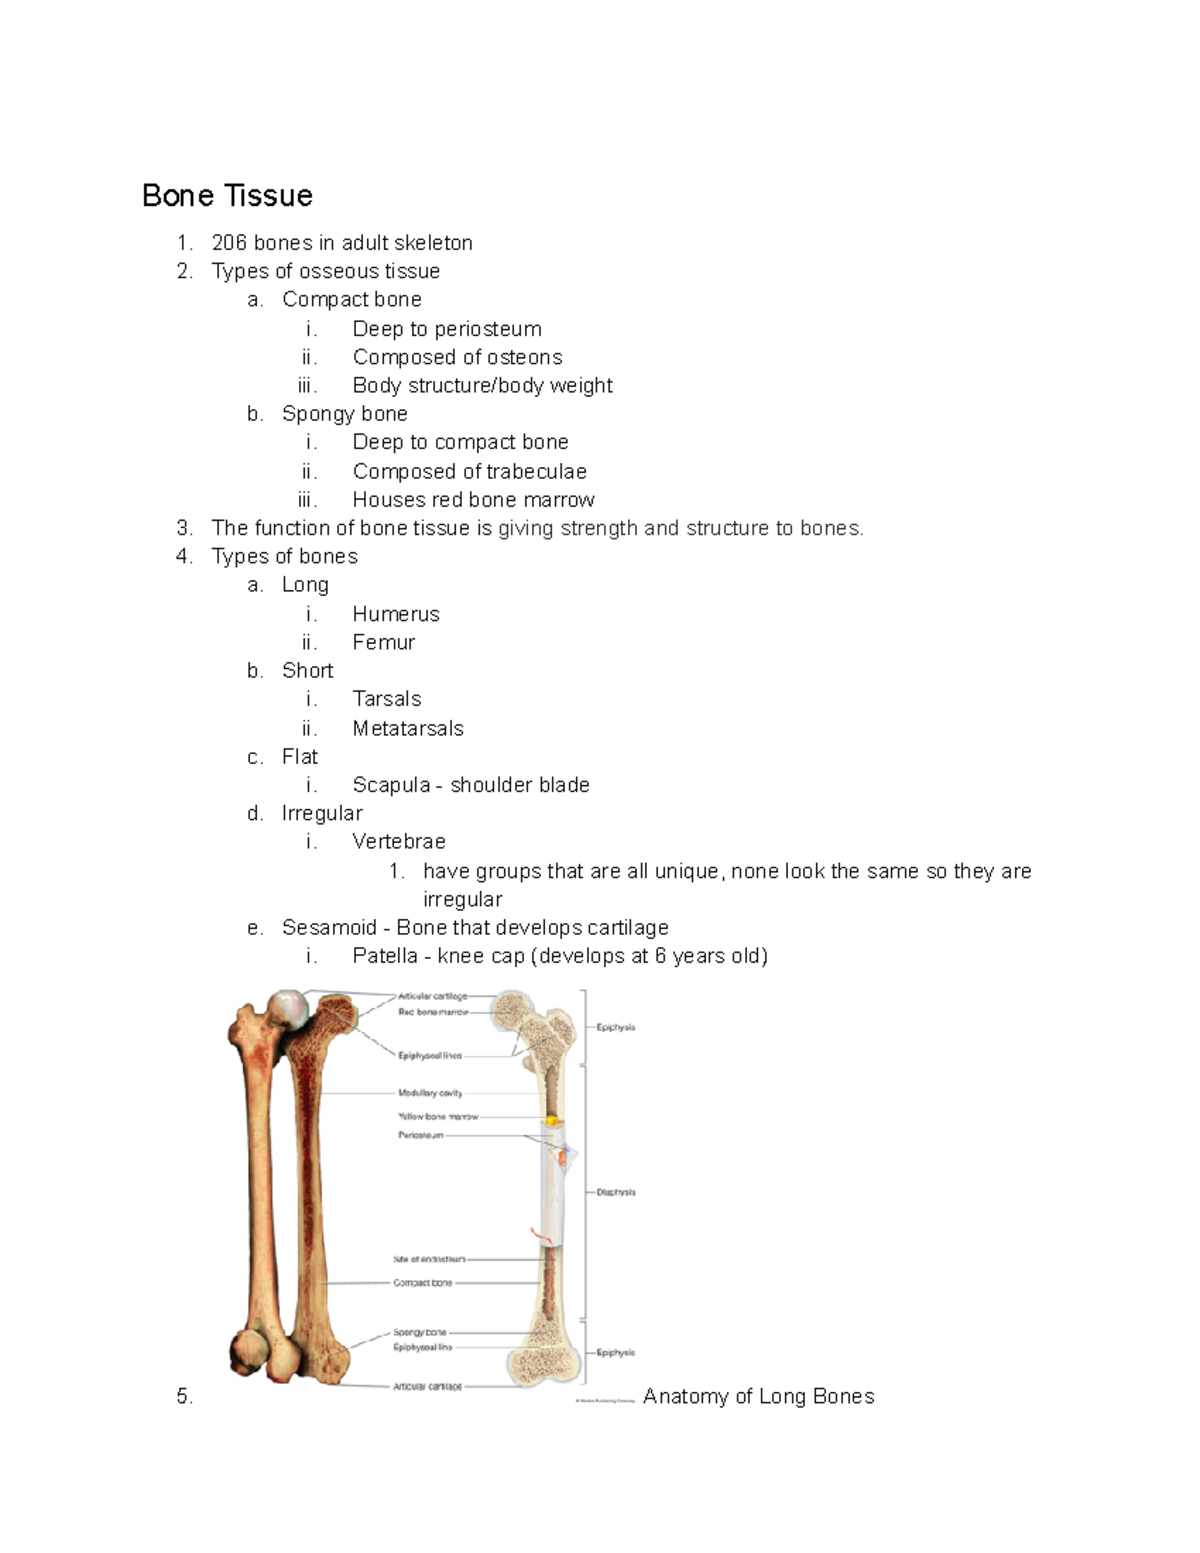
You open a textbook, you see a diagram of the skeleton with fifty labeled parts, and you immediately feel overwhelmed. That is normal. The skeletal system is large, it has roughly 206 bones in the adult human body, and most people try to memorize everything at once instead of breaking it into chunks. I spent years teaching intro anatomy and grading exams where students would confuse the triquetrum with the trapezium because they had flashcards that put both words on the same side. It was frustrating to watch, but it came down to how people organized their study material. Start with classification before you memorize names. Bones fall into five categories by shape: long, short, flat, irregular, and sesamoid. Long bones have a diaphysis and epiphyses with spongy bone inside and compact bone on the outside. Short bones are roughly cube-shaped. Flat bones are thin and curved. Irregular bones have complex shapes that don't fit the other patterns. Sesamoid bones sit inside tendons, and the patella is the classic example everyone knows. If you understand these categories first, naming individual bones becomes a labeling exercise instead of a guessing game. Here is where most people mess up. They start from the skull and work downward linearly, memorizing every bone in sequence before moving to the next region. This approach fails because the axial and appendicular skeletons overlap in function and clinical relevance. I had a student once who could name every cranial bone but could not identify the greater tubercle of the humerus. She had studied in isolation instead of grouping bones by region and function. The workaround I used with her was region-based grouping. Axial skeleton first: skull, hyoid, auditory ossicles, rib cage, vertebral column. Then appendicular: pectoral girdle, upper limb, pelvic girdle, lower limb. Within each region, you learn the major bones before the minor ones. The clavicle and scapula come before the individual carpal bones. The femur and patella come before the individual tarsals.
Skeletal tissue deserves its own section. Bone is a living organ, not a dead structural frame. Compact bone forms the dense outer layer. Spongy bone contains trabeculae and red marrow in adults. Both types contain osteons, lacunae, canaliculi, and Haversian canals. The periosteum covers the outer surface except at joint surfaces. Endosteum lines the medullary cavity. When you study histology, do not treat it as separate from gross anatomy. The structure of the osteon explains why long bones are strongest along the axis of load. This connection matters for understanding fractures and stress reactions. I ran into a specific problem with a group of students who were preparing for a practical exam. They had a list of twenty bones to identify from photographs, and they kept confusing the scaphoid with the lunate in the wrist. Standard flashcards were not helping because the two bones look nearly identical from certain angles. What worked was having them draw the proximal row of carpals from memory, then label each bone while drawing. The act of reproducing the spatial relationship forced them to notice the differences. The scaphoid is the largest bone in that row and wraps around like a boat. The lunate sits medial to it and has a more symmetrical crescent shape. Drawing took twenty minutes and fixed a problem that two weeks of flashcards had not resolved. For the Study Guide For Bones And Skeletal Tissue, I recommend building your own material rather than downloading someone else's. Your brain encodes information differently when you produce it. A blank document with regional headings is better than a pre-made PDF. Write out the regions. List the bones under each. Add a column for landmarks and articulations. Add another column for common clinical correlations. The clinical column is what turns memorization into understanding. Knowing the femoral triangle is useful. Knowing that femoral fractures can damage the profunda femoris artery changes how seriously you study the anatomy.
There is a real downside to this approach. It takes time to build your own guide. If you have a midterm in three days, making detailed notes from scratch is not practical. In that case, use a reliable existing resource and annotate it heavily. Highlight what you get wrong. Write marginal notes about why you chose the wrong answer. The annotation process still forces engagement even if the base material is not yours. Another pitfall is over-indexing on the appendicular skeleton and under-studying the axial skeleton. Exams routinely test the vertebral column in detail. Cervical, thoracic, and lumbar vertebrae differ in specific ways. Spinous process orientation, vertebral body size, and the presence of costal facets are the main distinguishing features. Students often memorize "cervical have transverse foramina" and stop there. They lose points on questions about C1 and C2, which lack typical features and instead have unique structures like the atlas ring and the dens of the axis. You need to know exceptions as well as rules. For tissue histology specifically, the common mistake is memorizing layer names without understanding the functional gradient. The outer circumferential lamellae differ from the interstitial lamellae. Volkmann canals connect Haversian canals across osteons. Trabecular bone in spongy tissue does not have osteons at all. When exam questions describe a section of bone and ask you to identify the region, knowing these differences matters more than knowing that bone contains osteocytes. If you only memorize "bone has cells," you will miss questions about lamellar arrangement and vascular supply.
Get the Full Details

A practical timeline that works for most courses is as follows. Week one covers bone classification and gross anatomy of the axial skeleton. Week two covers the appendicular skeleton with emphasis on major bones and key landmarks. Week three covers histology and microanatomy. Week four is review with practice identification. If your exam is sooner, compress weeks one and two into a single intensive pass focusing on landmarks and articulations, then spend the remaining time on histology and clinical correlations. The landmark pass should include timed self-testing. Hold up a bone image for thirty seconds. Name every part you can identify. Move on. Repeat until you can cover the images in under fifteen seconds without missing major landmarks. Most online resources treat bones as isolated facts. A proper Study Guide For Bones And Skeletal Tissue connects the facts to function and pathology. The connection is what makes the material stick during an exam and after. Without it, you will forget the majority of what you memorized within weeks. That is how the human brain works, not a reflection of effort or intelligence. Build the connections, test yourself actively, and accept that some details will fade. You do not need to remember every riblet or every lesser tubercle variant to pass. You need a working model of the skeleton that lets you reason through questions you have not seen before.