Getting Your Head Around How the Body Is Put Together
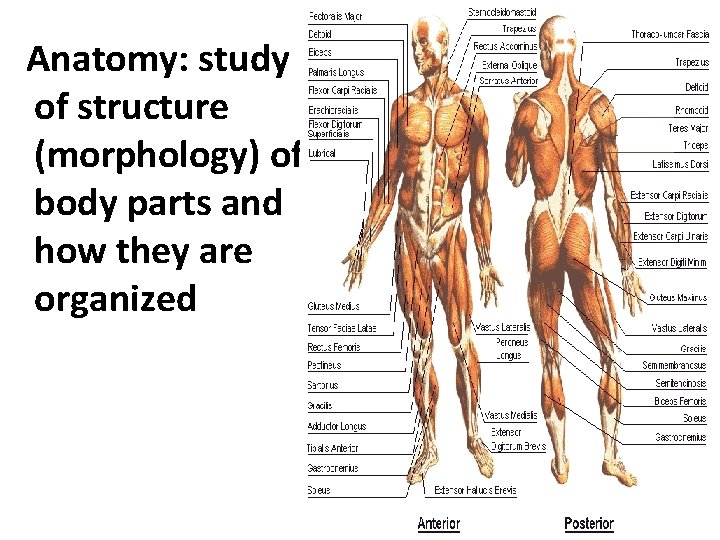
The study of structure of human body is what anatomists call gross anatomy when you are working at the scale you can see without a microscope. You learn where muscles attach, how fascia layers slide past each other, what variations show up in cadavers that textbooks pretend never exist, and why your mental map of the body keeps failing you when you actually need it under pressure. It starts with regions. You do not learn the entire body at once. You pick a region, usually the upper limb or the abdomen first, and you dissect or trace through it until the relationships stick. The standard sequence is bones, then joints, then muscles with their origins and insertions, then neurovascular bundles that run through the spaces between them, then fascial planes that tell you where a dissection tool should and should not go. I spent years in surgical prep rooms and later in anatomy labs teaching first-year med students. The people who actually retained anything did one thing differently: they traced structures in three dimensions rather than memorizing lists. A muscle origin and insertion are not facts to recite. They are geometric constraints that determine line of pull, leverage, and what happens when that muscle weakens or gets compressed.
How I Actually Approach Learning It
Here is the method that survives contact with real work. Pick a structure. Find it on a cadaver or a high-quality 3D atlas like Complete Anatomy or Anatomage. Then close the screen and draw it from memory on blank paper. Not trace. Draw it. Your hand remembers spatial relationships your eyes skip over. After that, I interrogate the structure. Where does it lie relative to the bone it sits on? What vein crosses it anteriorly? Which nerve runs in the same fascial plane? If I cut here, what am I hitting next? This interrogation takes maybe forty-five seconds per structure but it converts a name you recognized into a landmark you can use. The biggest waste of time I see is layer-by-layer reading. You open Netter, read the caption for the brachial plexus, move to the next page, repeat. By page three you have seen five labels but you could not find the lateral cord on an actual dissection. Instead, learn the brachial plexus by finding it. Palpate the clavicle. Follow the subclavian artery. Identify the trunks as they pass between the anterior and middle scalene muscles. Do that once on a real specimen and you will not confuse C5-C7 with the brachial artery for the rest of your career.
Edge Cases That Textbooks Miss
During a routine dissection of the antecubital fossa a few years back, I encountered a median antebrachial vein that did not behave. Instead of draining into the basilic or cephalic vein at the expected level, it ran straight down the midline of the forearm and emptied into the deep venous system near the elbow. A surgeon using that vein for a cutdown would have been looking for something that was not there. The workaround is simple and it applies to everything you study. When you find a variant, do not file it away as an anomaly and move on. Map it. Sketch it. Note the level, the relationship to adjacent structures, and what clinical procedure would be affected by it. I keep a small notebook of variants I have personally seen. Fifteen entries in that book have saved me from making a wrong assumption in the operating room more times than I care to count. Another thing nobody warns you about: surface anatomy is not reliable when the patient is obese, dehydrated, or edematous. The anterior superior iliac spine is a landmark you can always trust, but the iliac crest is nearly impossible to palpate in a patient with a large pannus. In those cases you fall back to bony prominences that resist soft tissue distortion. Learn those fallbacks early.
Get the Full Details
Counter-Intuitive Points That Matter
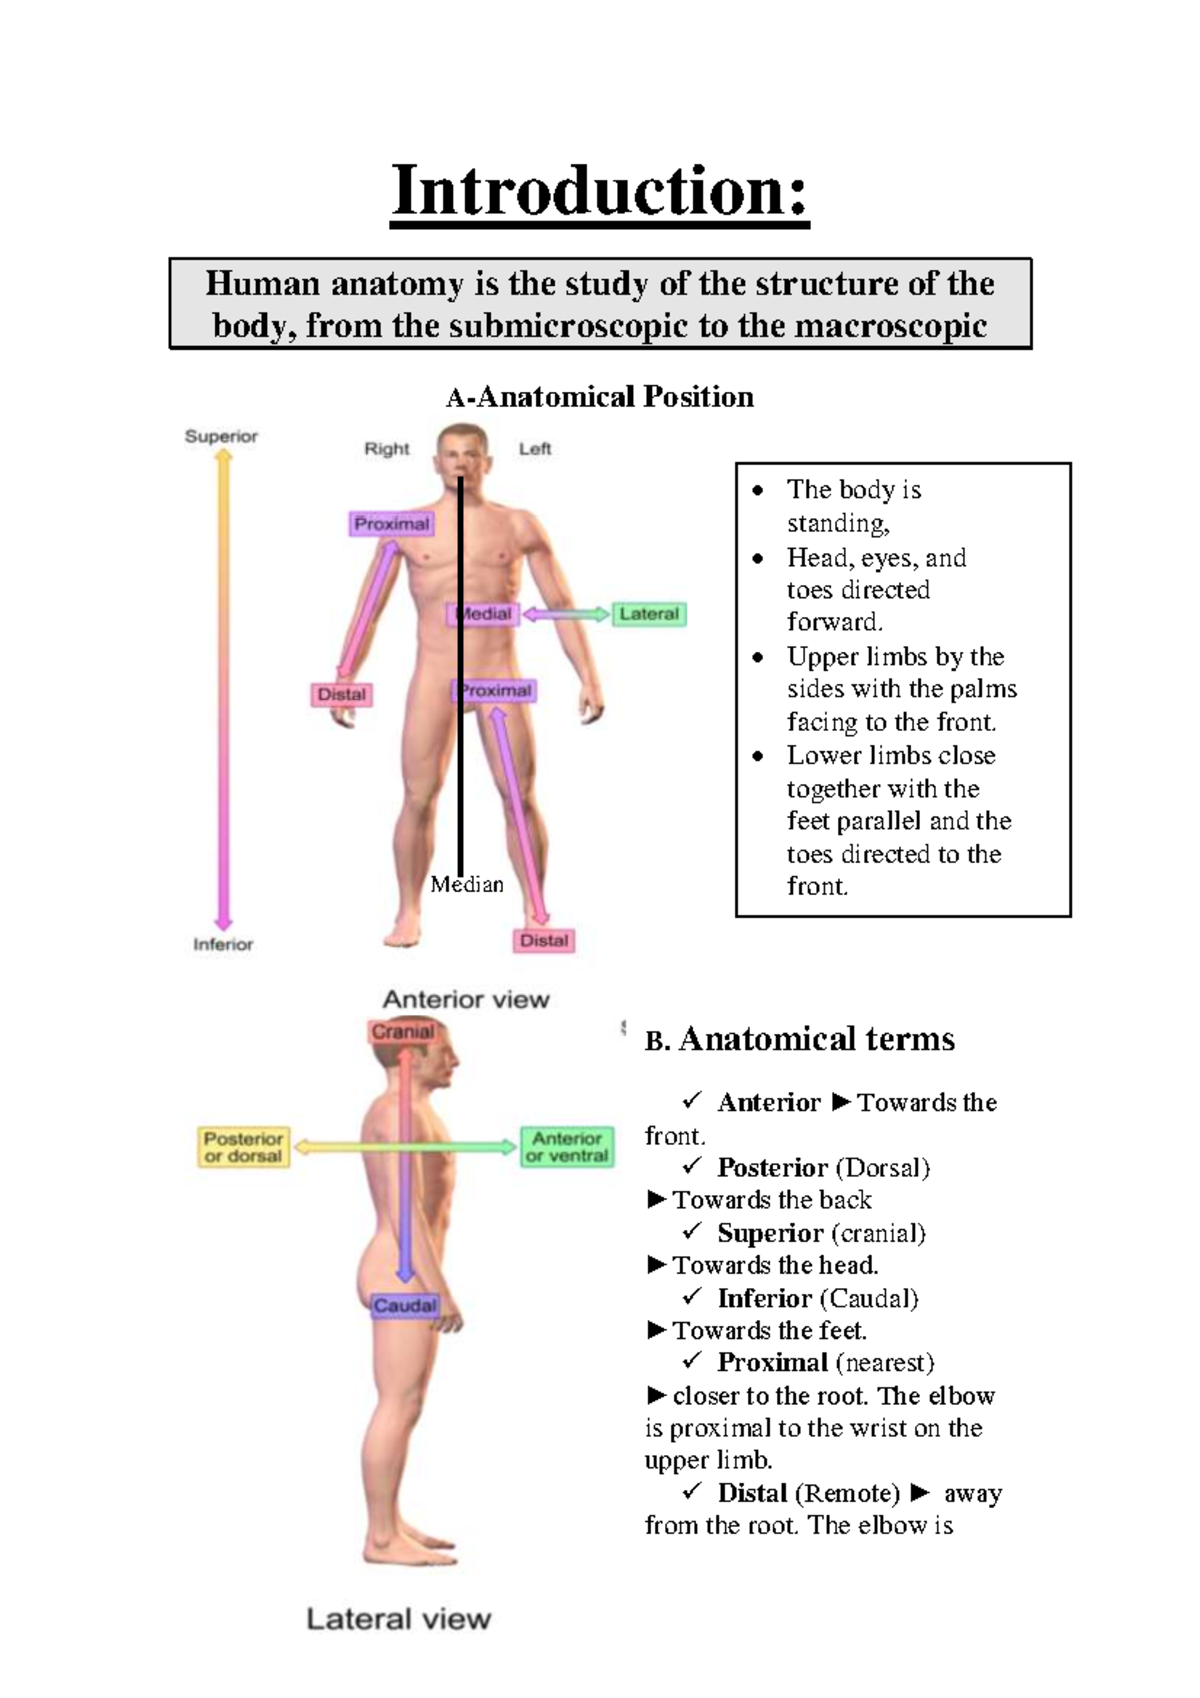
The first one is that memorizing nerve root values before understanding the peripheral course is almost useless. Knowing that the ulnar nerve comes from C8-T1 does not help you avoid it during a medial epicondyle approach. Knowing that it passes posterior to the medial epicondyle inside the cubital tunnel does. Root values matter for radiculopathy. Topographic relationships matter for everything else. The second is that fascial planes are more important than muscle borders for surgical and procedural work. Muscles tear. Fascia separates cleanly. If you learn to identify the intermuscular septa and the compartmental boundaries, you can navigate tissue with minimal damage. If you only learn muscle names, you end up cutting through bellies you did not intend to touch.
Tools That Actually Help
Primal Pictures and Complete Anatomy are the ones I reach for most often. They handle multi-planar reconstruction well, which matters when you are trying to understand a structure that runs obliquely through three different anatomical planes. For free resources, the Visible Human Project from the National Library of Medicine has cross-sectional data that is still useful despite its age. OpenFunctorhombic is excellent for brain anatomy if that is your focus. Anki works if you use it correctly. A deck that asks "what crosses anterior to structure X at level Y" is far more valuable than one that asks "name the branches of the femoral nerve." Contextual recall beats isolated fact recall every time.
Where This Approach Breaks Down
It does not replace hands-on dissection. No atlas, no app, no 3D program gives you the resistance of tissue, the variation in color and texture, the moment when your scalpel slips half a centimeter and you realize you are now looking at something you did not expect. Dissection teaches you to be wrong in a controlled environment so you do not get wrong in an uncontrolled one. The other limitation is time. A thorough regional dissection cycle for one area of the body takes roughly sixty to eighty hours of focused work if you are doing it properly. Most people compress that into two weeks of cramming and then forget sixty percent of it within six months. Spacing the same material over four to six months with repeated retrieval practice retains roughly double that amount. If you are studying for an exam and you have less than a month, stop trying to do it all. Pick the high-yield relationships: arterial supply to the organs in each region, the major nerve pathways and what function each controls, the key fascial spaces and their clinical significance. That covers probably seventy percent of what shows up on practical exams. The rest you fill in later when you need it.

What to Focus On First
Start with the skeleton as your framework. The bones tell you where everything else is going to be. Then learn the joints because they define the spaces structures have to cross. Then muscles, but only the ones that create recognizable surface landmarks or that have clinical relevance like rotator cuff muscles or the perineal muscles. Then neurovascular structures, which are the ones that actually kill or disable you when you get them wrong. Stop when you can close your eyes and trace a structure from origin to termination without looking at a diagram. That is the point where it is actually in your head rather than in the book.