So You Want to Study Sleep Apnea
I ended up looking into this because my brother started snoring at a volume that made our walls vibrate. I told him to see a doctor. He ignored me. Six months later he had a sleep study and was diagnosed with moderate obstructive sleep apnea. CPAP machine. Mask. The whole deal. He still complains about it. If you're doing this for yourself, you probably already have symptoms. Loud snoring, waking up gasping, morning headaches, daytime fatigue that coffee doesn't touch. Or maybe you just want to understand the research. Either way, the process is straightforward if you know where to look.
Study Sleep Apnea: What You Actually Need to Do
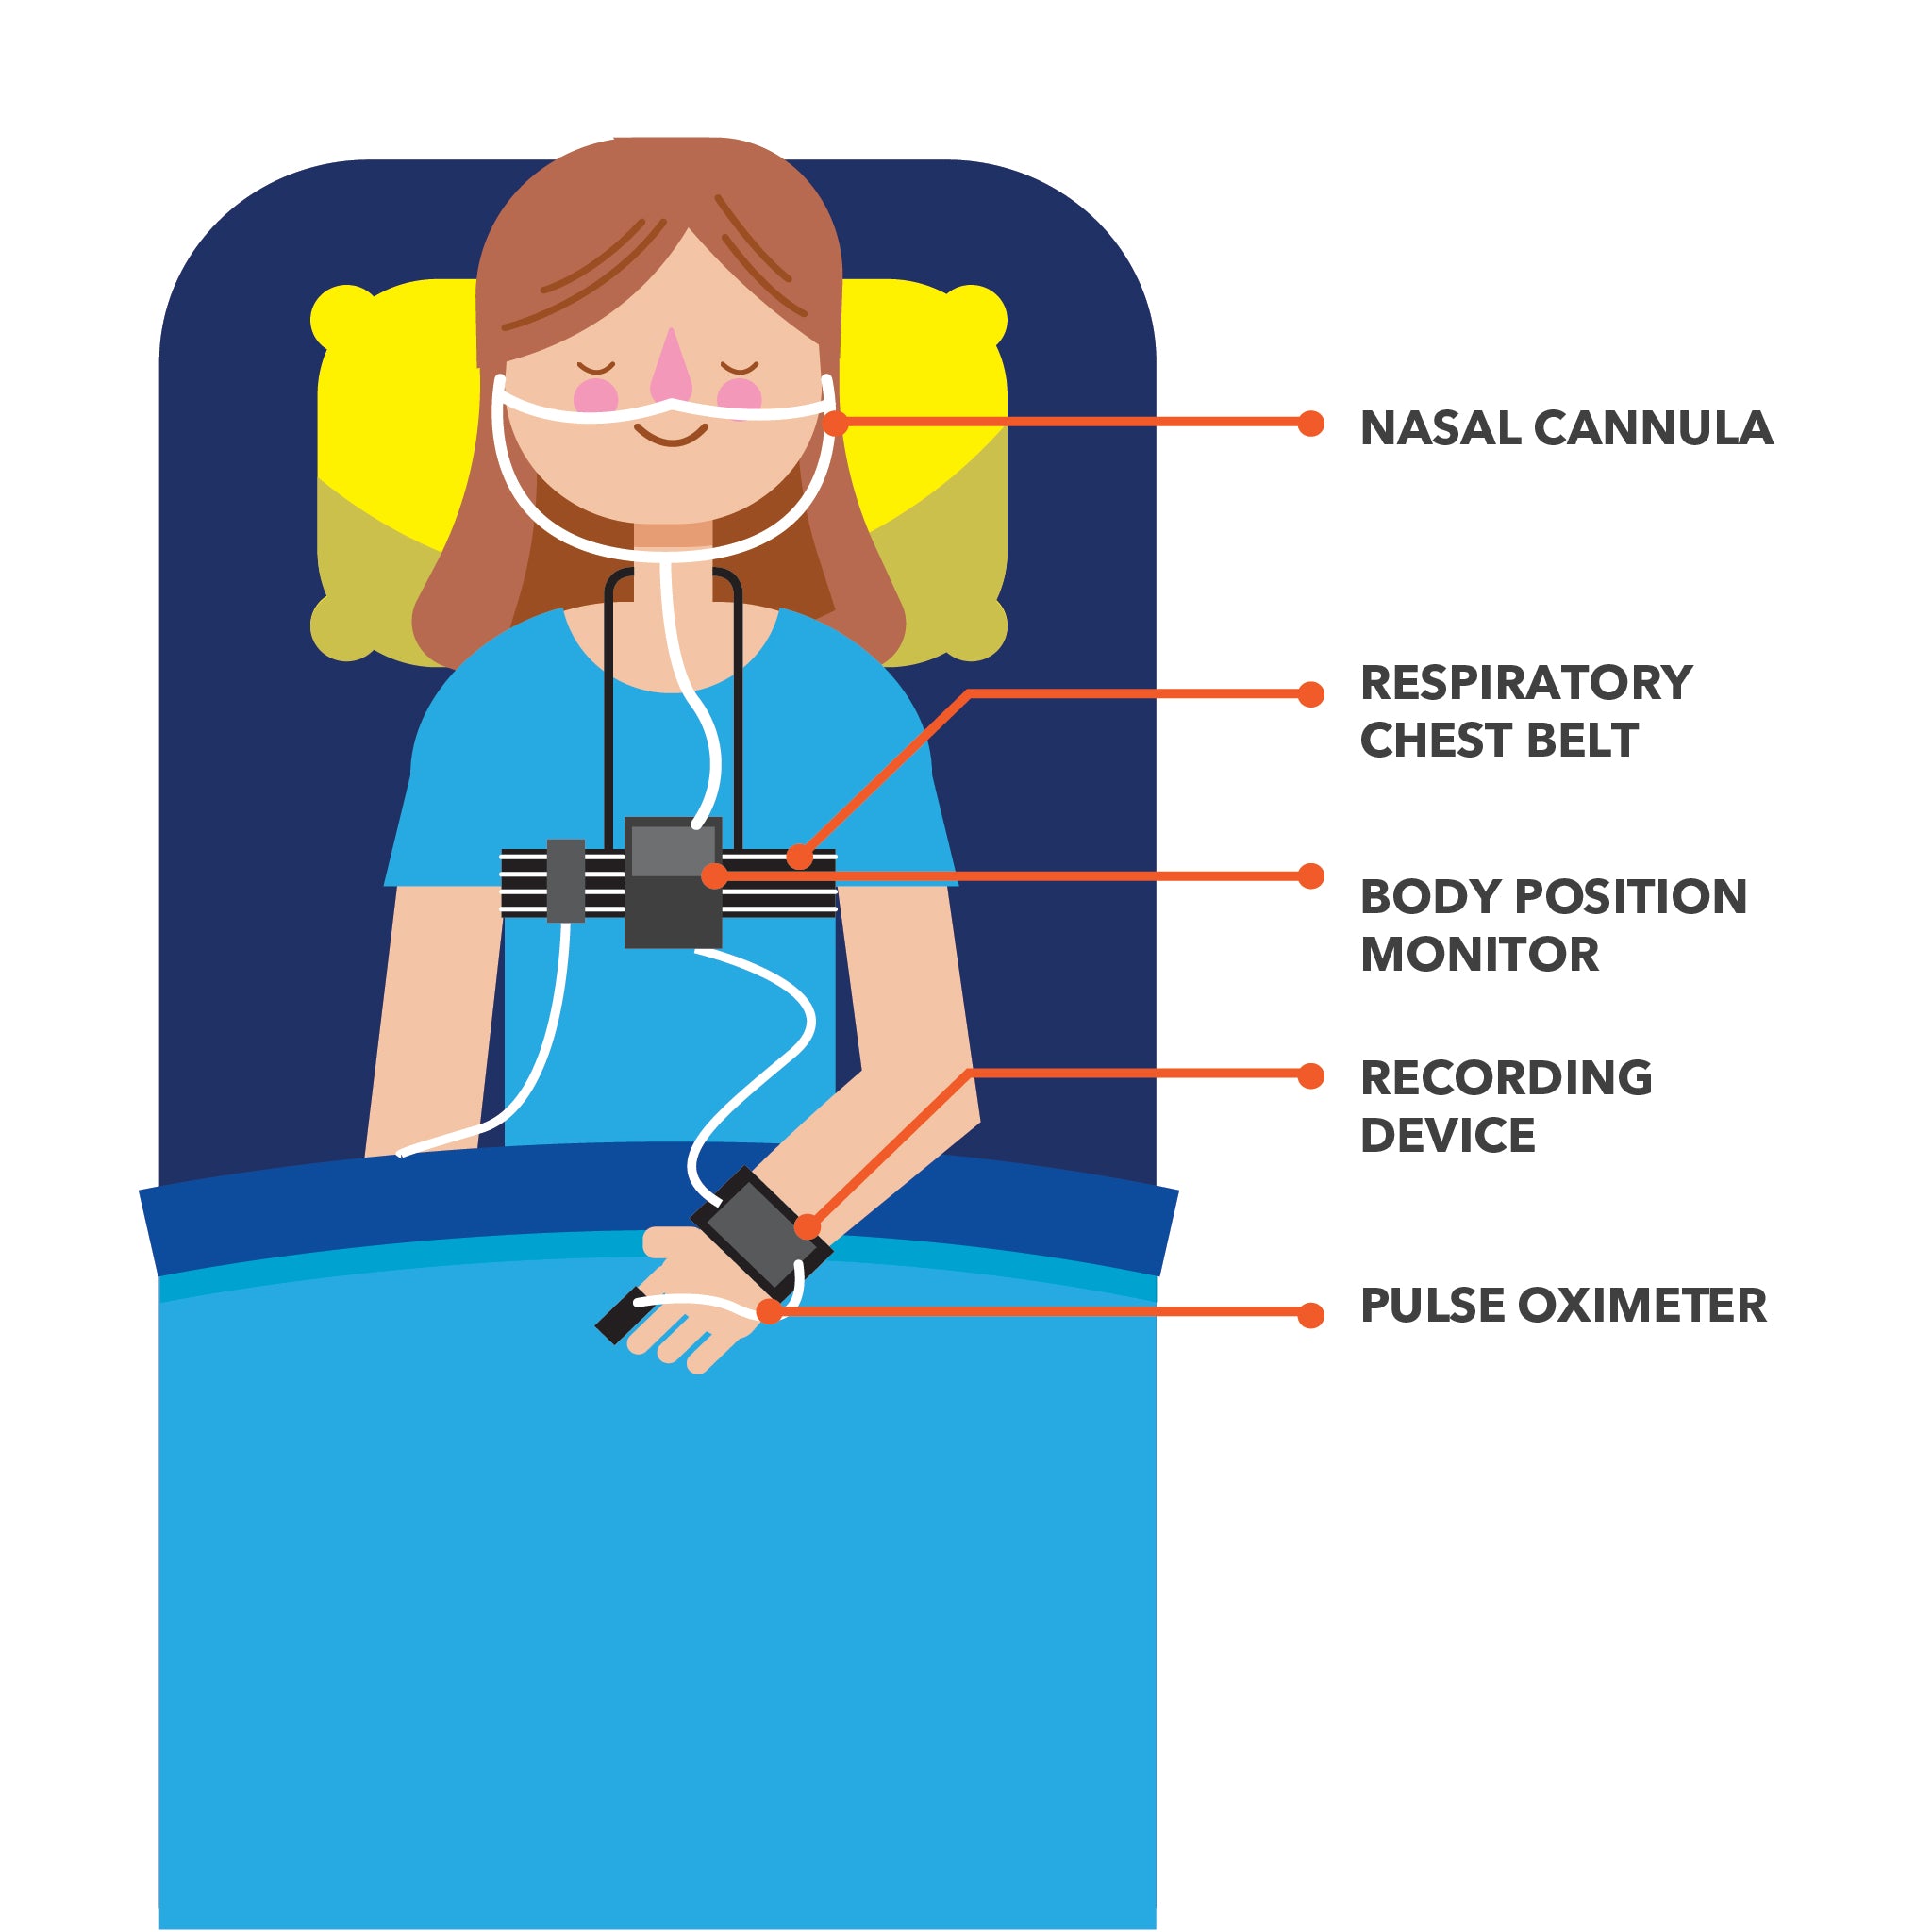
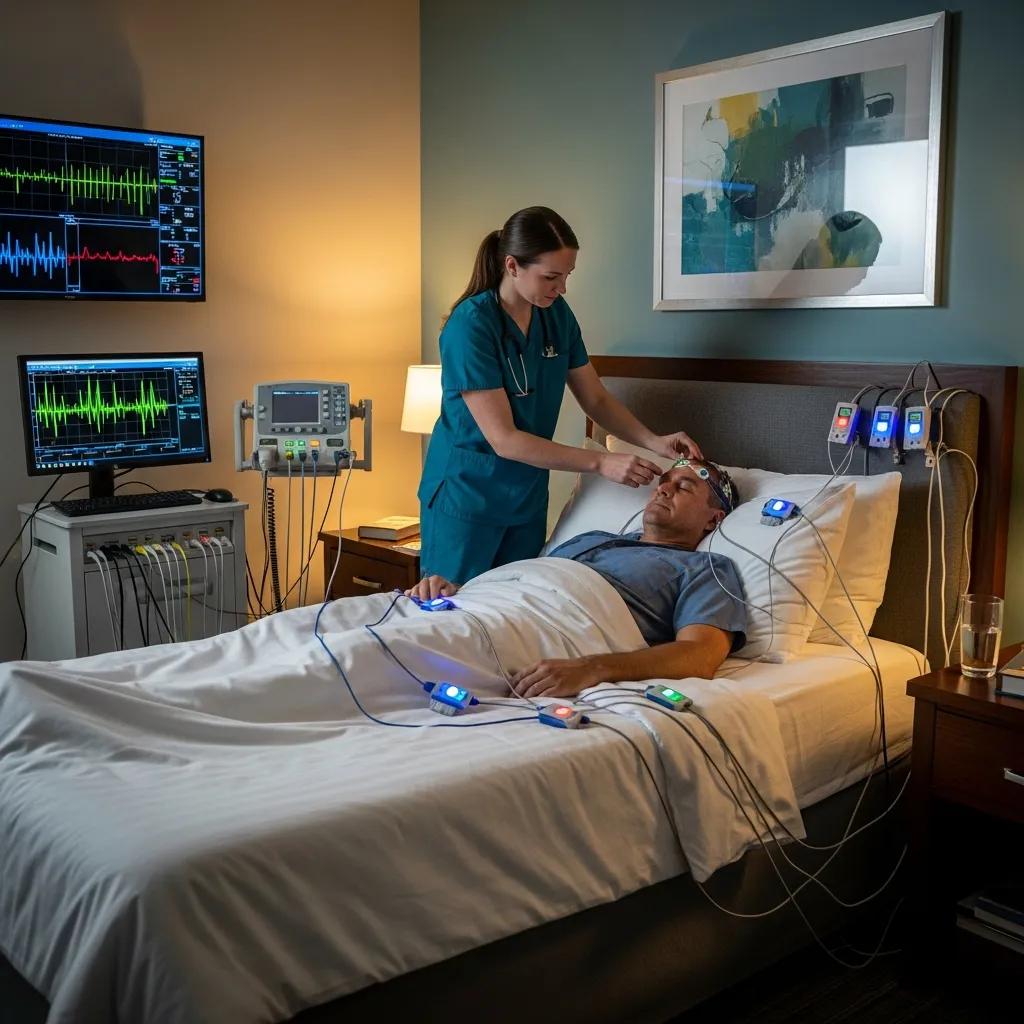
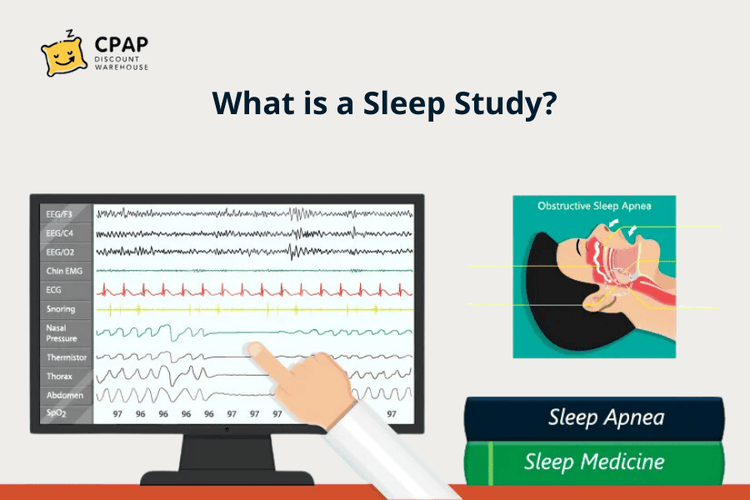
There are two paths. One goes through a doctor. The other is a home test kit. The doctor path means an overnight polysomnography in a lab. They hook you up to about twelve sensors. EEG leads on your scalp, ECG on your chest, a nasal pressure cannula, a belt around your abdomen, a pulse oximeter on your finger. They track brain waves, breathing effort, oxygen saturation, leg movements, heart rate, and body position. A trained technologist watches the entire night. The home test is much simpler. You buy or get prescribed a portable device. It measures airflow, breathing effort, and oxygen levels. Some also track heart rate. That's it. No brain waves. No position sensor on most basic models. The data gets uploaded and interpreted by a sleep specialist. I found the home test route insufficient for anyone who might have central sleep apnea or a co-existing sleep disorder. My wife used one for her initial screening and got a false negative because her oxygen desaturations were mild but her arousal index was through the roof. She had severe sleep fragmentation from repeated micro-awakenings. The home device missed most of it. She ended up doing the lab study anyway.
The Diagnosis and What Comes Next
Once you have the study, you get an AHI score. Apnea-Hypopnea Index. That's the number of breathing pauses per hour. Under 5 is normal. 5 to 15 is mild. 15 to 30 is moderate. Above 30 is severe. The severity determines treatment options. Mild cases sometimes don't need a CPAP at all. Here's something people don't expect. Being overweight is a major factor but not the only one. I read a lot of studies where researchers found that men with narrow airways and recessed chins get apnea at normal body weights. jaw structure matters more than most patients realize. A tonsillectomy, orthodontics, or a mandibular advancement device can help some of these people instead of a machine. Positional therapy is another angle that gets overlooked. Some people only sleep apnea on their back. Their tongue falls backward when supine. Sleeping on your side eliminates most of the obstruction. I tried a tennis ball sewn into the back of a t-shirt technique. It's crude but effective for positional apnea. You wake up on your side every time you roll onto your back because the ball is uncomfortably pressing into your spine.
Get the Full Details

Practical Problems I've Run Into
Insurance coverage is a nightmare. Different plans require different steps before they'll pay for a study or a CPAP. Some want a prior home test. Others skip that entirely. One of my colleagues needed a letter of medical necessity that took three emails back and forth between his pulmonologist and the insurance company before they approved the lab study. Factor in at least two weeks of delays. The CPAP mask fitting is where most people quit. You think you'll just put it on and go to sleep. That's not how it works. There are maybe eight different mask styles. Nasal pillows, nasal masks, full face masks. Each comes in small, medium, and large with adjustable headgear. The wrong mask causes leaks that ruin the therapy and create pressure sores on your nose bridge. I spent six weeks trying four different masks before finding one that worked. Here's an edge case I didn't find documented anywhere. People with claustrophobia often can't tolerate a mask that covers the nose and mouth. I suggested a nasal pillow style for a patient of mine with severe claustrophobia and the pillows were fine for airflow but she couldn't stand the sensation of something inside her nostrils. She ended up using a CPAP with a heated humidifier turned all the way up and a nasal mask with the straps loosened as far as possible without causing leaks. It was uncomfortable but workable for three years until she decided to try oral appliance therapy instead.
Research Side of Things
If you're studying sleep apnea academically, the big databases are available for free. The Sleep Heart Health Study dataset and MIMIC-IV both contain sleep-related data. MIMIC is a bit more clinical. You'll need CITI training and institutional approval to access it. The SHHS data has more population-level information and is easier to get. One thing that's easy to miss when you're analyzing sleep data. The scoring rules changed in 2012. Before that, an apnea event had to last one full respiratory cycle. After the AASM guidelines update, it only needs to be ten seconds. If you're comparing older studies to newer ones, the AHI numbers aren't directly comparable. This trips up a lot of people doing meta-analyses. Another subtlety. Orai and hypopnea are scored differently depending on the equipment. Blood oxygen drops of three percent used to be the standard threshold. Some newer protocols use four percent. Your AHI number shifts by a few points either way. It sounds minor but it can move someone from mild to moderate classification.
What This Doesn't Fix
CPAP doesn't cure sleep apnea. It manages it. You stop using the machine, the apnea comes back immediately. That's not a criticism of the treatment. It's just how it works. The airway stays open while the machine is pushing air. The moment it stops, the tissue collapses again. Weight loss helps but doesn't always eliminate apnea. A patient of mine lost sixty pounds and his AHI dropped from 42 to 18. Significant improvement but still moderate. Surgery is an option for select cases but success rates vary widely. Upper airway surgery has a rough 50 to 60 percent success rate depending on the technique and patient selection. It's not a guarantee. If you're looking into this for a project or personal health, start with a proper diagnosis. Don't self-diagnose from online questionnaires. The STOP-BANG questionnaire is useful as a screening tool but it has known sensitivity and specificity limitations. It misses about 20 to 30 percent of actual cases. A real sleep study is the only reliable way to know what you're dealing with.