Stuttering Prediction Instrument For Young Children: What It Actually Does In Practice
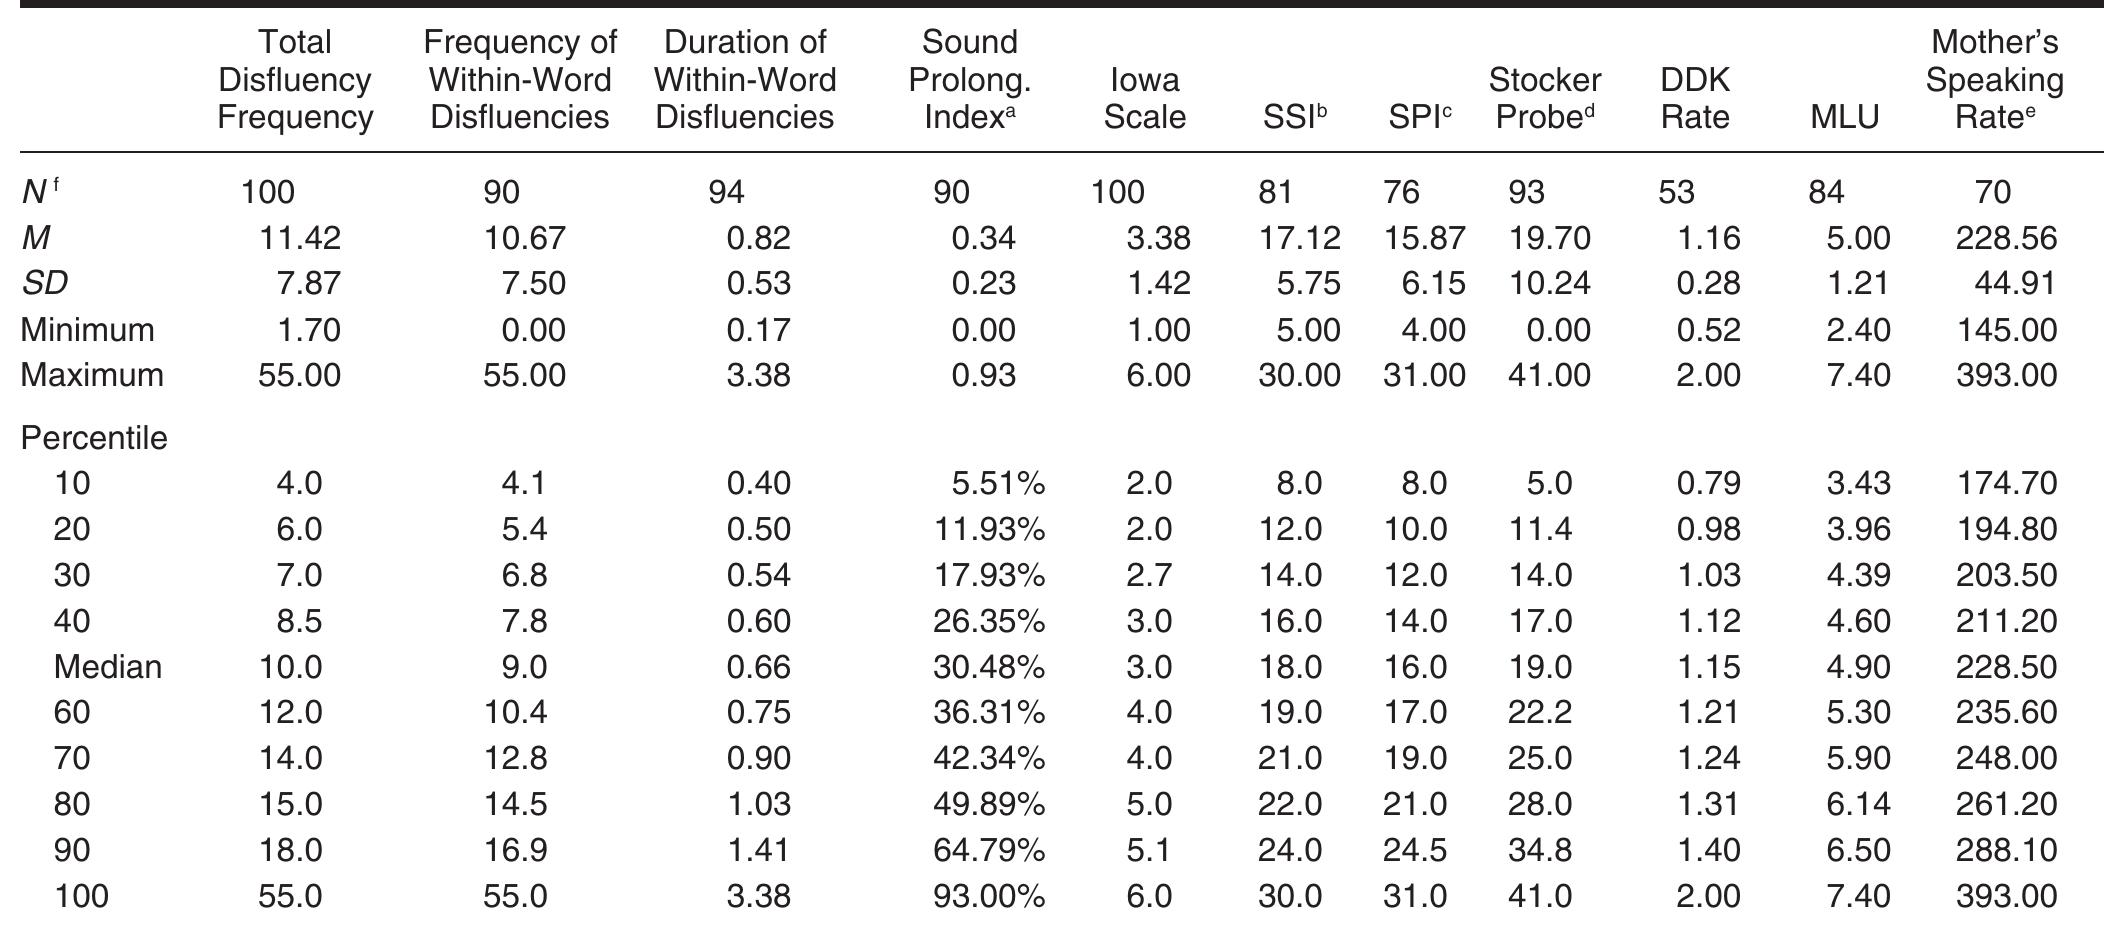
The Stuttering Prediction Instrument for Young Children (SPI) is one of those tools most speech-language pathologists and developmental specialists have heard of but rarely use correctly. It was designed to help clinicians estimate whether a young child who stutters will recover naturally or continue stuttering into adolescence. The original version came out of the work of Bruce Yairi and colleagues, and there have been updates over the years. The basic idea hasn't changed much: you administer a structured set of tasks and observations, score specific behaviors and characteristics, and plug the results into a formula that yields a probability score for persistent stuttering. The instrument doesn't just look at how often a child stutters. That would be too simple and not particularly predictive on its own. It bundles several domains together—things like duration of stuttering behavior, tension and struggle secondary behaviors, speech and language development, familial patterns of stuttering, the child's awareness and emotional reactions, and general developmental milestones. Each domain contributes a weighted score, and the combined total gives you a risk estimate. I've found that the parts people get wrong most often are the tension/scanning items and the language sample coding. The instrument asks you to rate the degree of co-occurring motor tension during disfluencies, not just count repetitions. A child who has frequent syllable repetitions but zero facial grimacing, eye blinking, or body rocking will score differently than a child with less frequent repetitions but clear straining and physical effort. Similarly, the language sample requirement trips up a lot of people. You need a 15-to-30-minute sample, transcribed and analyzed for mean length of utterance and other structural measures, not a quick question-and-answer exchange at the end of an intake form.
One thing beginners consistently miss: the instrument isn't a diagnosis. It's a predictive screening tool with documented sensitivity and specificity ranges from the original research, but those numbers are population-level statistics. They don't tell you anything definite about a single child. I've seen clinicians present a score of 0.78 to a parent as if it means the child will definitely persist, and that's not how the data works. The same score could just as easily mean the child will recover. The tool narrows the odds, nothing more.
How to Administer It Without Ruining the Results
The administration itself is straightforward in theory. You're looking at a combination of direct observation, standardized subtests where specified, language sampling, and parent interview. The SPI manual lays out the exact procedures. Here's what the manual doesn't always make obvious about the actual feel of running through it with a real child. Young children under five, especially, won't sit through a formal assessment without some engagement strategy. I built in toy play and pretend scenarios for the observation portion rather than trying to keep the child focused on a worksheet or picture description. The data you need comes from how the child communicates across multiple contexts, not from one structured task. A child who stutters heavily during free play but not during a practiced recitation gives you very different information than the reverse. The parent interview component is where you capture family history of stuttering and the child's reactions to disfluency. I've had parents initially insist their child never shows frustration about speech, only to pull out a video from six months earlier showing the exact kind of avoidance behavior the instrument is looking for. Don't accept a surface-level answer on that one. Ask specific questions about whether the child pauses before speaking, switches words mid-sentence, or avoids certain situations like being called on in preschool. These behavioral markers carry weight in the scoring.
Get the Full Details
Here's an edge case I ran into that I don't think the manual adequately addresses: bilingual children. The language sample analysis expects norms based on monolingual English development. A two-year-old who is acquiring Spanish and English simultaneously will naturally produce shorter utterances in each language during a single session, which can artificially deflate the MLU score. I started collecting separate samples in each language when possible and used the dominant language sample for the MLU calculation. If you don't have enough data in one language to meet the sample size requirement, you note that as a limitation rather than forcing a score. The instrument won't break, but your interpretation has to be honest about it.
Scoring and Interpreting the Results
Scoring requires going through each item and assigning the appropriate value based on your observations and the standardized measures. The weighting scheme favors certain predictors more heavily than others. Duration and frequency of stuttering moments, presence of tension, family history, and delayed language development typically carry the most weight. The exact point values and cutoffs for risk categories are in the manual, and they differ slightly between versions. When I first started using this instrument regularly, I made the mistake of treating the risk categories as harder boundaries than they actually are. The original studies report ranges and confidence intervals, not pass/fail lines. A child landing right at the boundary between low and moderate risk isn't meaningfully different from a child a few points above it. I stopped presenting categories to parents and started talking in terms of relative probability and what the numbers actually mean in plain language. It makes the conversation more accurate and less anxiety-inducing. The instrument also has limitations that deserve to be stated plainly. It was normed on specific populations, primarily monolingual English-speaking children in the United States. Its predictive accuracy drops when applied to populations that differ from those norms. It doesn't account for environmental factors like pressure to speak quickly at home or in school, which can influence both the severity of stuttering and the trajectory. And it doesn't replace a full clinical evaluation—it's one piece of data among many.
For families who want to move forward after an SPI administration, the usual next step is discussing intervention options like Lidcombe or less-direct approaches, depending on the child's profile and the family's preferences. The prediction score can help frame the conversation about urgency, but it shouldn't drive the decision entirely. Some children with elevated scores benefit from early intervention regardless of where they might land long-term, and some children with lower scores still benefit from monitoring and support.

Where to Get the Instrument
The Stuttering Prediction Instrument is a proprietary assessment tool. You can't just download it from a public website. It's distributed through the same channels that handle most clinical assessment instruments—typically through publishers or professional organizations in the speech-language pathology field. You'll need to verify your credentials as a licensed or certified speech-language pathologist or a graduate student working under supervision, since the instrument is intended for professional use. The cost and availability can vary, so checking with the publisher directly or through your professional association's resource list is the practical route. If cost or access is a barrier, some programs and clinics have shared copies, and graduate-level supervising clinicians often carry their own. There are also published papers that describe the instrument's items in enough detail that clinicians familiar with the original research can administer comparable procedures without the commercial packet, though you lose the standardized scoring sheets and normative comparisons that come with it. That's a trade-off worth considering if you're working in an under-resourced setting.