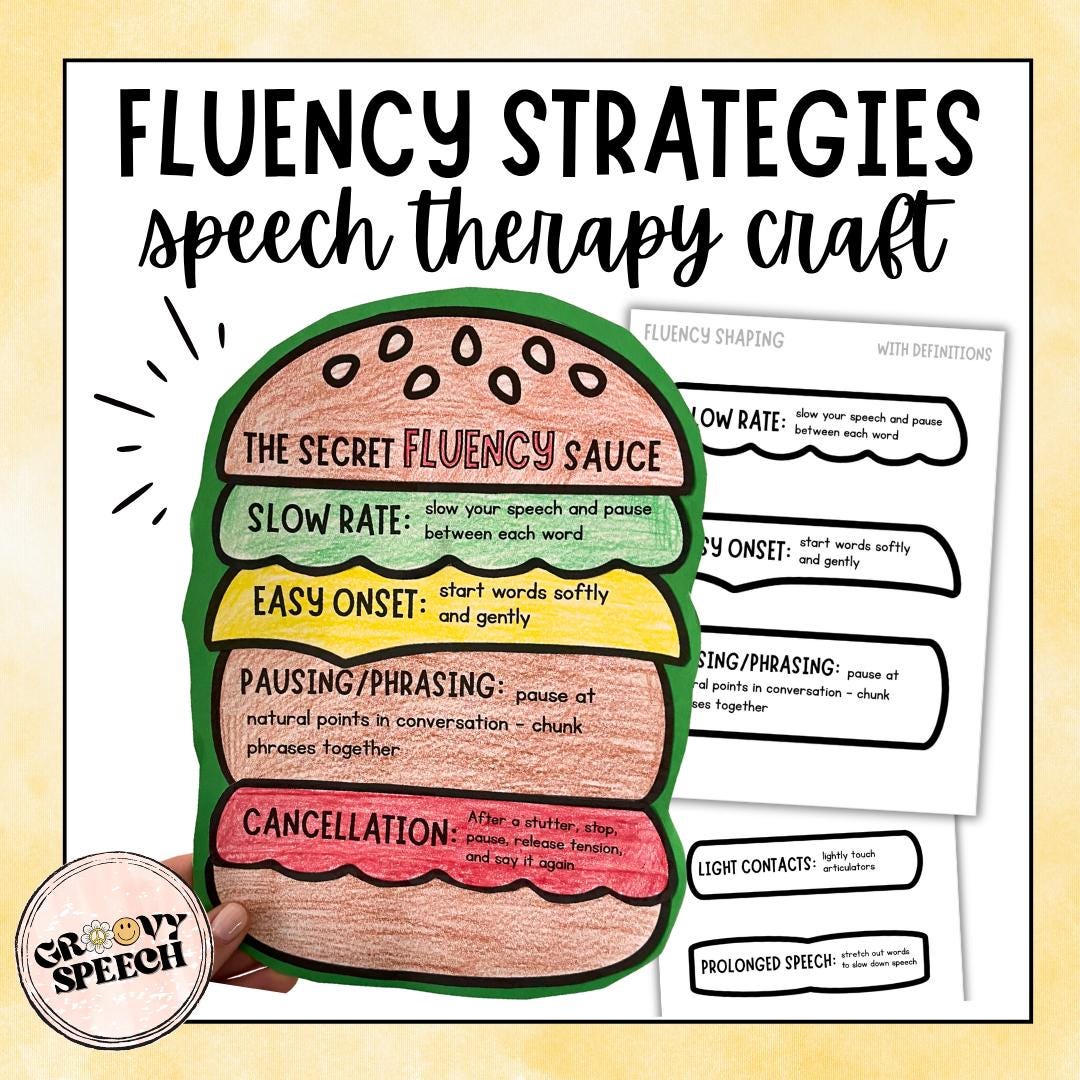
Setting Actual Targets for Fluency Work
Most people I see online are either speech therapists who need to document measurable objectives for a new caseload, or parents who want to understand what reasonable progress looks like when their kid is doing stuttering therapy. The problem isn't that there's no guidance. The problem is that the existing goal templates are so generic they're almost useless. "Client will decrease stuttering frequency by 50 percent" doesn't tell you much if you don't know what baseline measurement tool was used, what conditions were tested, or whether 50 percent was chosen because it's arbitrary or because it maps to something clinically meaningful. I'll walk through how I construct these goals for my own clients, including the ones that actually fail and what we do instead.
Stuttering Speech Therapy Goals
The framework I use is built around three axes: frequency, severity, and functional impact. Frequency is the easiest to measure because you can count dysfluent moments on a recording. Severity is harder but more important — a client who stutters once per minute but with a 15-second tension-filled escape isn't the same person as someone who stutters five times per minute with quick, easy repetitions and zero visible struggle. Functional impact is where most goal-writing goes wrong. It's what the client actually experiences in real life: avoiding phone calls, finishing other people's sentences, anxiety before reading aloud in class. The counter-intuitive part that nobody talks about enough is that lowering frequency alone often makes things worse if you don't also address the secondary behaviors. I had a kid one time who was doing great in the clinic. His SSRI scores dropped from 28 down to about 9 over six weeks of fluent shaping. He sounded smooth. Then his mother called me because he'd started tensing up so badly during those few remaining moments of stuttering that he'd freeze mid-sentence for five, six seconds at a time. We'd optimized the wrong variable. We went back to working on ease of onset and voluntary stuttering for another month before trying to push frequency lower again. That cut the whole regression from months to about two weeks.
How to Write a Measurable Stuttering Goal
Start with a baseline measurement taken under real conditions, not just during a quiet play session in the therapy room. A client who stutters at 3 percent in a one-on-one warm-up is a completely different starting point than one who stutters at 8 percent in unstructured classroom participation. I usually have parents or teachers log brief samples over a 48-hour period using a simple tally sheet — mark each moment of dysfluency, note whether it's a repetition, prolongation, or block, and mark context (phone, reading, casual conversation, nervous situation). Once you have the baseline, the SMART format still works if you fill it in properly. Here's what a real one looks like from my notes: Client will produce an average of fewer than 5 dysfluent moments per 100 syllables during structured conversational tasks with a familiar partner, as measured by weekly SSI-4 administration, across four consecutive sessions.
Get the Full Details

That's specific, measurable, and tied to a validated instrument. The four-consecutive-sessions requirement prevents the kind of week-to-week variance that makes progress look bigger or smaller than it actually is. Stuttering fluctuates day to day. What matters is the trend line.
The Goals Most Therapists Skip
Everyone writes goals about speech output. Almost nobody writes goals about the stuff that actually determines long-term outcomes. Avoidance behavior, emotional response, self-perception, and communication attitude are the predictors of whether a client will maintain gains after therapy ends. If you skip them, you're building a house on a foundation you didn't pour. Here are examples that actually move the needle: Avoidance goal: Client will initiate three previously avoided speaking situations per week for four consecutive weeks, defined as phone calls to unfamiliar businesses, reading aloud in front of a small group, or introducing themselves to a new person, documented through a self-monitoring log reviewed biweekly.
Emotional response goal: Client will rate anxiety level during speaking situations on a 0-to-10 scale within one minute of the interaction, and will demonstrate a reduction in average pre- and post-task anxiety ratings from 7 or above to 5 or below in four out of five tracked sessions. Self-perception goal: Client will identify and verbalize two positive aspects of their own communication in a given conversation before the next scheduled session, across four consecutive weeks, as observed during a brief check-in. These sound soft until you look at the data. Clients who work on avoidance early tend to generalize fluency techniques faster because they're getting more practice in real environments. Clients who drop out of therapy usually do so because the speech improved but their fear didn't, and they feel like the therapy wasn't helping anymore. You can prevent that by building these into the treatment plan from week one, not as an afterthought.

Progress Monitoring That Actually Works
Don't re-administer the SSI-4 every week. It's not sensitive enough to small changes and it takes too long to be practical. Use a combination of short-form metrics for weekly tracking and the full instrument monthly. A 60-second speech sample analyzed for percent syllables stuttered gives you a quick read on trajectory without the administrative overhead. Record it on your phone, transcribe the syllables, count the moments of dysfluency, divide. Takes about ten minutes if you're familiar with the process. Here's a realistic timeline I've seen hold up: moderate stuttering severity with consistent therapy twice a week. Expect the first measurable improvement in frequency within three to four weeks. Expect meaningful change in severity and avoidance patterns within eight to twelve weeks. If you're not seeing any directional movement after six weeks, reassess the technique or the client's readiness, don't just keep running the same drill.
What Doesn't Work and Why
A goal like "client will achieve 90 percent fluency in all situations" is a fantasy that sets everyone up for failure. Fluency is not a stable state. It's a moment-to-moment negotiation between the client's speech motor system and the demands of the communicative environment. Even clients who achieve near-complete fluency in therapy will have bad days. I've never had a client maintain 90 percent fluency across three months of unrestricted daily speaking, and I've had plenty of good technicians. The goal should be functional improvement, not elimination. Another common failure is writing goals that only measure success in the clinic. If the target is only met during sessions with the therapist present, the goal is measuring compliance, not skill acquisition. The transfer problem is real and it's why I build generalization trials into the goal framework from the start — not as a separate phase but as part of the target condition itself. If you're working with an adult client where the primary barrier is social and professional impact rather than speech mechanics, consider pairing conventional fluency shaping with a cognitive-behavioral component. The evidence for CBT adjuncts in stuttering treatment is solid enough that skipping it entirely feels negligent, not conservative. I refer to a specialist when the anxiety and avoidance are driving the clinical picture more than the disfluencies are. The therapy goals change in that scenario, and the S-scores matter less than the communication attitude inventory scores.