How to Actually Build a Substance Abuse Assessment That Doesn't Collapse Under Scrutiny
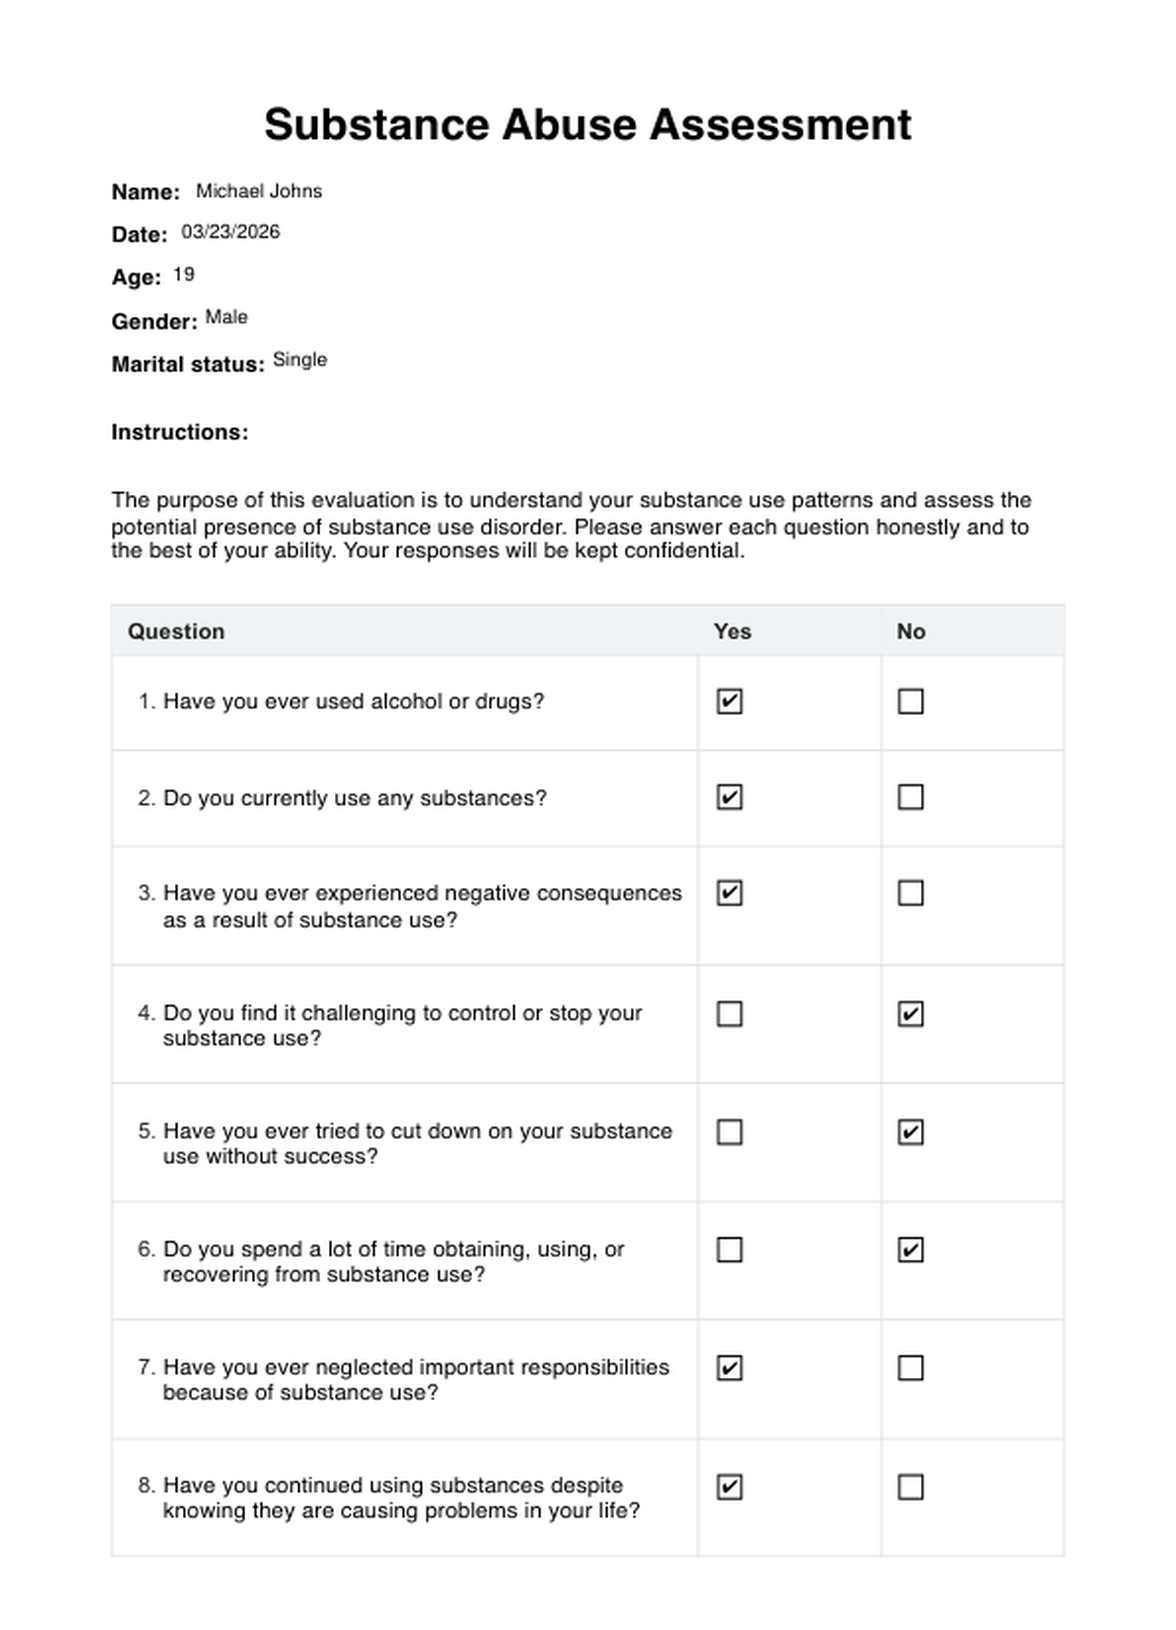
Most assessments I see floating around online are either copy-pasted from SAMHSA templates without any adaptation or they're built by people who've never sat through a real intake interview. Either way, they fall apart the moment you need to defend them to a court or a licensing board. I've been building and reviewing these tools for clinical and forensic settings for long enough that I can spot the difference in about thirty seconds.The first thing most people get wrong is assuming an assessment is the same as a screening tool. They're not. A screening like the CAGE-AID or AUDIT is a quick yes/no filter. An actual Substance Abuse Assessment Example needs to go much deeper. It should cover lifetime and current use patterns, routes of administration, frequency, quantity, age of first use, consequences across life domains, co-occurring conditions, withdrawal history, motivation, and protective factors. If your document doesn't touch at least six of those areas, it's still a screening disguised as something heavier.
Why Your First Substance Abuse Assessment Example Probably Misses the Mark
I spent two years working in a county behavioral health department where we had to standardize assessments across three different providers who absolutely hated each other. The first round of document reviews was brutal. Two out of three providers were using versions of the ASAM Criteria but had rewritten the questions so heavily that the scoring system didn't actually match the diagnostic language anymore. You'd get a Level 3.1 placement on paper and then the clinician's narrative would describe someone who clearly belonged at 2.1. Auditors noticed. Patients noticed. Everyone knew something was broken.The fix wasn't dramatic. It was just going back to the original ASAM Dimension scores and mapping every question directly to a dimension instead of letting individual clinicians invent their own categories. We also added a mandatory cross-reference field where the numeric score had to appear alongside the narrative justification. That single change cut our audit findings by about sixty percent over the next fiscal year.
What a Functional Assessment Actually Looks Like in Practice
A working assessment starts with demographic and consent documentation, then moves into the substance use timeline. The timeline matters more than people realize. You want dates, not approximations. "Last year" and "about six months ago" are useless when you're trying to establish a pattern or defend a placement decision. I started requiring month and year for onset and relapse dates, and if a client genuinely couldn't recall, we'd document it as unknown with a note about how that uncertainty affected the clinical judgment. That honesty is worth more than a fabricated timeline filled with plausible-sounding numbers.Next comes the actual use history. Type of substance, route, frequency, quantity, last use, and method of detection. The last use date and detection method are where most people rush. If you're relying on self-report, note that clearly. If you have a negative tox screen, document the date, the type of test, and the cutoff levels. Urine immunoassay screens at standard cutoffs miss a lot of synthetic opioids and emerging stimulants. I learned that the hard way when a client tested negative on a standard twelve-panel for five consecutive visits while clearly showing signs of fentanyl use. We switched to a panel that included fentanyl and synthetic cathinones and caught what we'd been missing for months. Not everyone has the lab budget for expanded panels, but at minimum you should document what your screening tool can and cannot detect.
Co-Occurring Conditions and Context
Untangling addiction from mental health issues is one of the trickiest parts of this work, and the literature is still arguing about which came first in most cases. What matters practically is that you document both independently before you start linking them. Screen for depression, anxiety, PTSD, bipolar disorder, and ADHD using validated instruments where possible. PHQ-9, GAD-7, PCL-5, and the MDQ are common choices. The point isn't that you need every single one. The point is that you need to show you looked, and you should record the instrument name, the score, and the interpretation.I once worked with a client who had been assessed six times across different clinics over eighteen months and every single assessment had missed the bipolar diagnosis. He'd been treated as a pure substance use case, put through detox three times, and each time he relapsed within two weeks because the underlying mania was driving the self-medication. When we finally ran the MDQ properly and caught the hypomanic episodes, the treatment plan changed entirely and his outcomes improved dramatically. Assessments that skip co-occurring screening aren't just incomplete, they're actively dangerous. Section 1: Demographics and Consent Name, DOB, ID number, date of assessment, assessor name and credentials, consent status, referral source.
Section 2: Substance Use Timeline Substance: [specific drug class and name] First use: [month/year]
Heaviest use period: [dates] Last use: [date with supporting evidence type] Routes of administration: [list all]
Get the Full Details

Frequency over past 90 days: [specific count] Quantity per use episode: [measured amount or description] Section 3: Consequence Domains
Physical health: [documented conditions] Legal: [charges, dispositions, dates] Employment: [status, duration of last employment]
Family/social: [support network status, relationships affected] Psychiatric: [diagnoses with dates and sources] Section 4: Withdrawal History
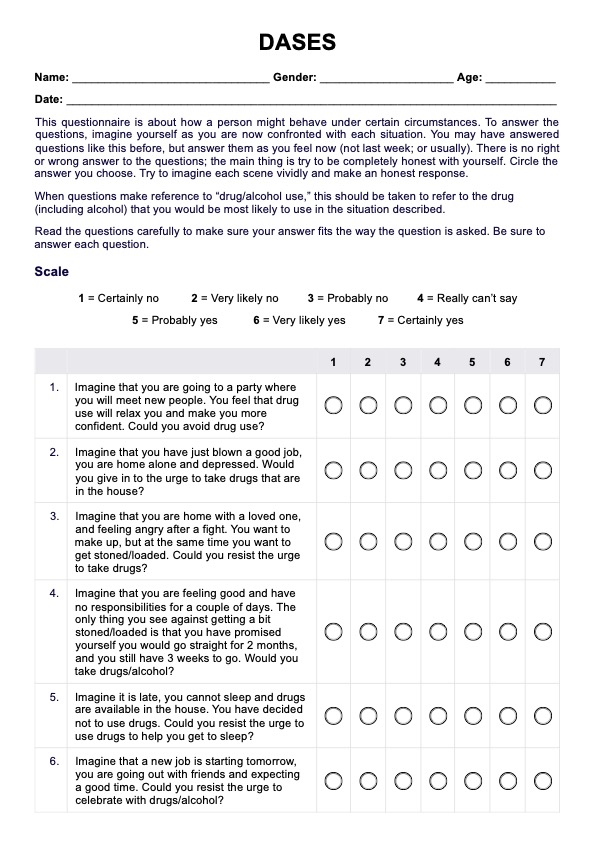
Previous withdrawals: [count, substances, complications, medical involvement] Seizures or DTs: [yes/no with dates] Section 5: Co-Occurring Screening Results
Instrument: [name], Score: [result], Interpretation: [classification] Note: [clinical observation supporting or qualifying the result] Section 6: Readiness and Motivation
Stage of change: [stage] Rationale: [brief clinical observation] Barriers to change: [documented factors]
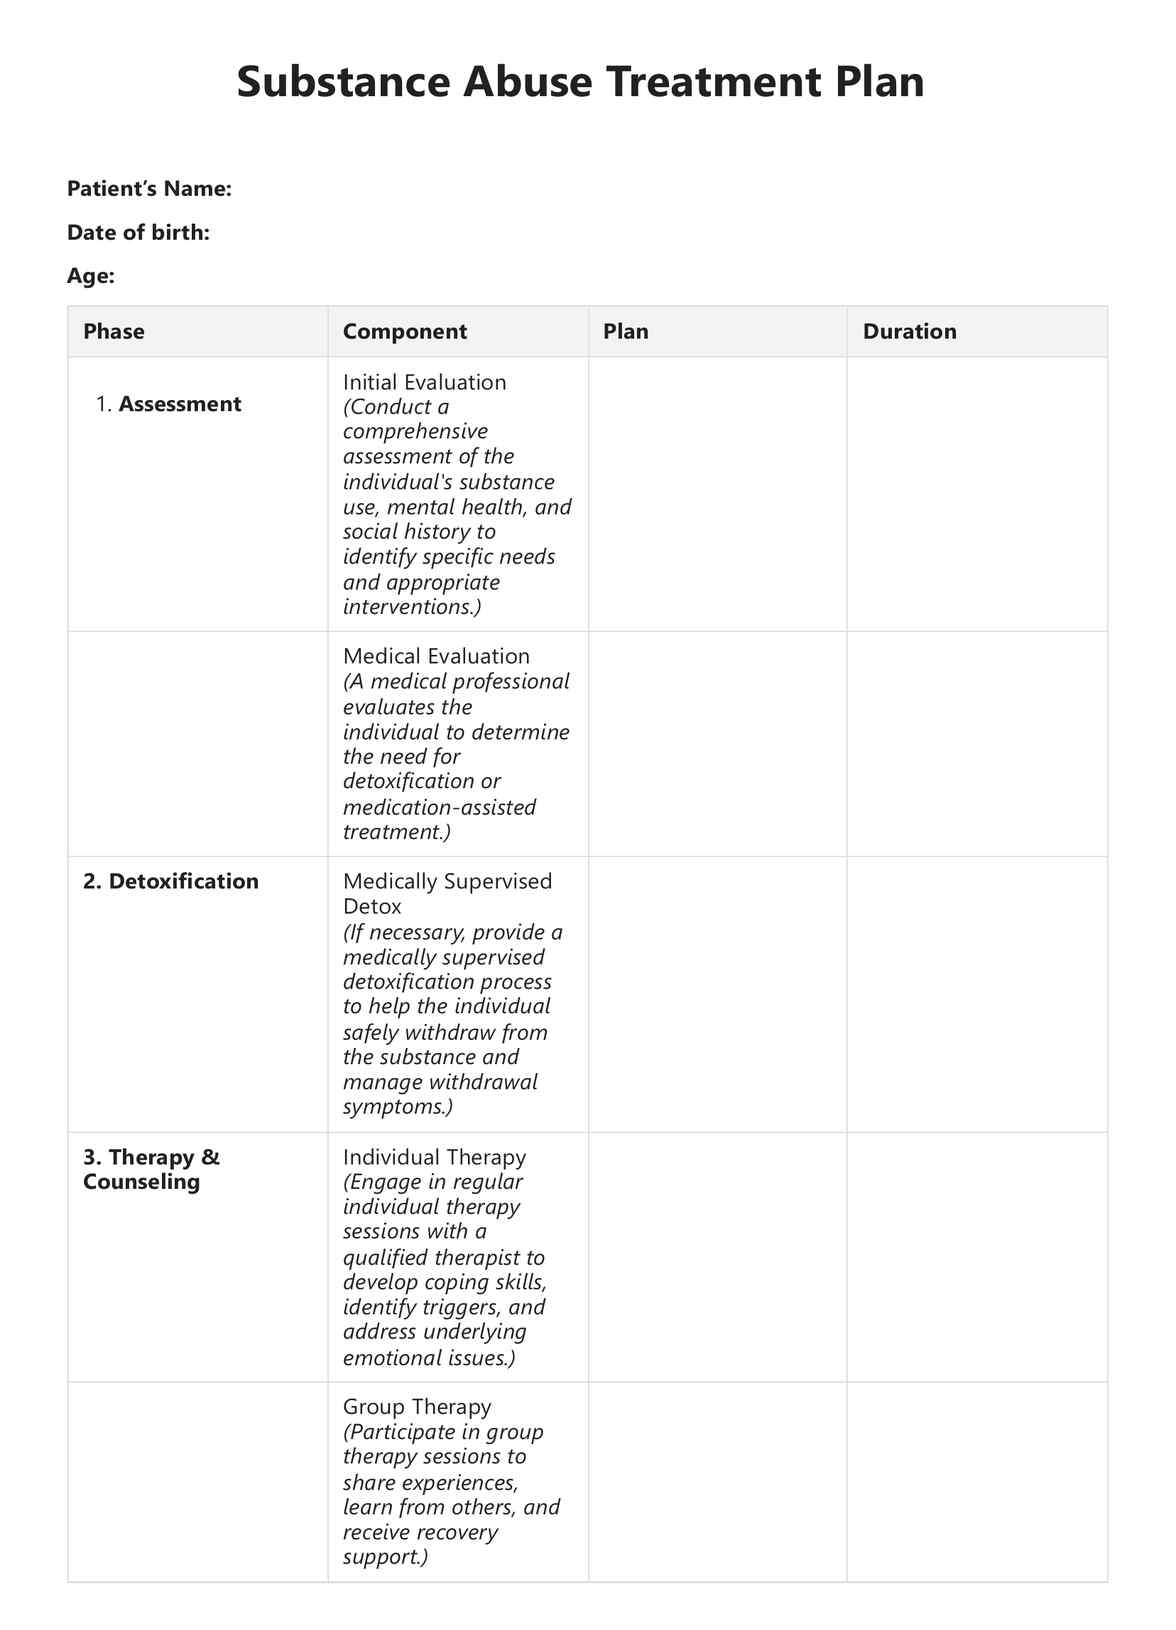
Section 7: ASAM Placement Recommendation Dimension 1 (withdrawal): [score] Dimension 2 (engagement): [score]
Dimension 3 (medical): [score] Dimension 4 (conditioning): [score] Dimension 5 (relapse): [score]
Dimension 6 (recovery environment): [score] Recommended level: [ASAM level with justification] Section 8: Treatment Plan Summary

Diagnosis: [DSM-5 code and specifier] Goals: [2-3 measurable objectives] Interventions: [specific modalities with frequency]
Referrals: [services needed with contact info if available]
What Breaks These Assessments
The biggest issue I encounter is when assessors treat the ASAM dimensions as an afterthought. They write a detailed narrative and then assign placement levels based on gut feeling instead of actually scoring each dimension. That creates the exact mismatch I described earlier. Every dimension needs a score, and the score needs to be consistent with what the narrative says. If the narrative describes a person with no social support and active homelessness, but Dimension 6 gets a score of one, something is wrong. Either the narrative is lying or the scoring is wrong, and an auditor will spot that in seconds.
Another common failure is using outdated diagnostic criteria. The DSM-5 merged alcohol abuse and alcohol dependence into a single alcohol use disorder with severity specifiers, and the same happened with substance use disorders generally. I still see assessments referencing DSM-IV categories like "abuse" and "dependence" as separate diagnoses. That's not just sloppy, it's professionally embarrassing if anyone outside your immediate team reviews the document. If you're working in a setting where high-stakes decisions depend on accurate identification of co-occurring disorders, consider pairing your assessment with structured clinical interviews like the SCID-5 or MINI instead of relying solely on questionnaire scores. The tradeoff is time. A full SCID-5 takes about forty-five minutes to an hour compared to ten minutes for a PHQ-9. But if you've ever watched someone get misdiagnosed because a ten-minute screen missed a complex presentation, the extra time is justified.
Finally, if your organization is building an assessment from scratch and doesn't have the clinical staff to validate it properly, don't. Use an established instrument, adapt it minimally, and document every change you make. Starting from zero and calling it a validated tool is how people lose their licenses.
