What You Actually Need to Know About Suicide Risk Assessment Tools
I spent a long time working with clinical screening instruments before I stopped treating them like magic bullets. The Suicide Risk Assessment Tool is fundamentally a structured way to take a messy clinical situation and reduce it to something you can document, compare over time, and potentially use to make triage decisions. That's it. Nothing dramatic about that. The tools themselves vary. Some are paper-based Likert scales. Some are embedded in EHR platforms. Some are standalone apps that pull demographic and clinical data and spit out a risk tier. The exact format matters less than the scoring algorithm underneath it.
How a Suicide Risk Assessment Tool Actually Works in Practice
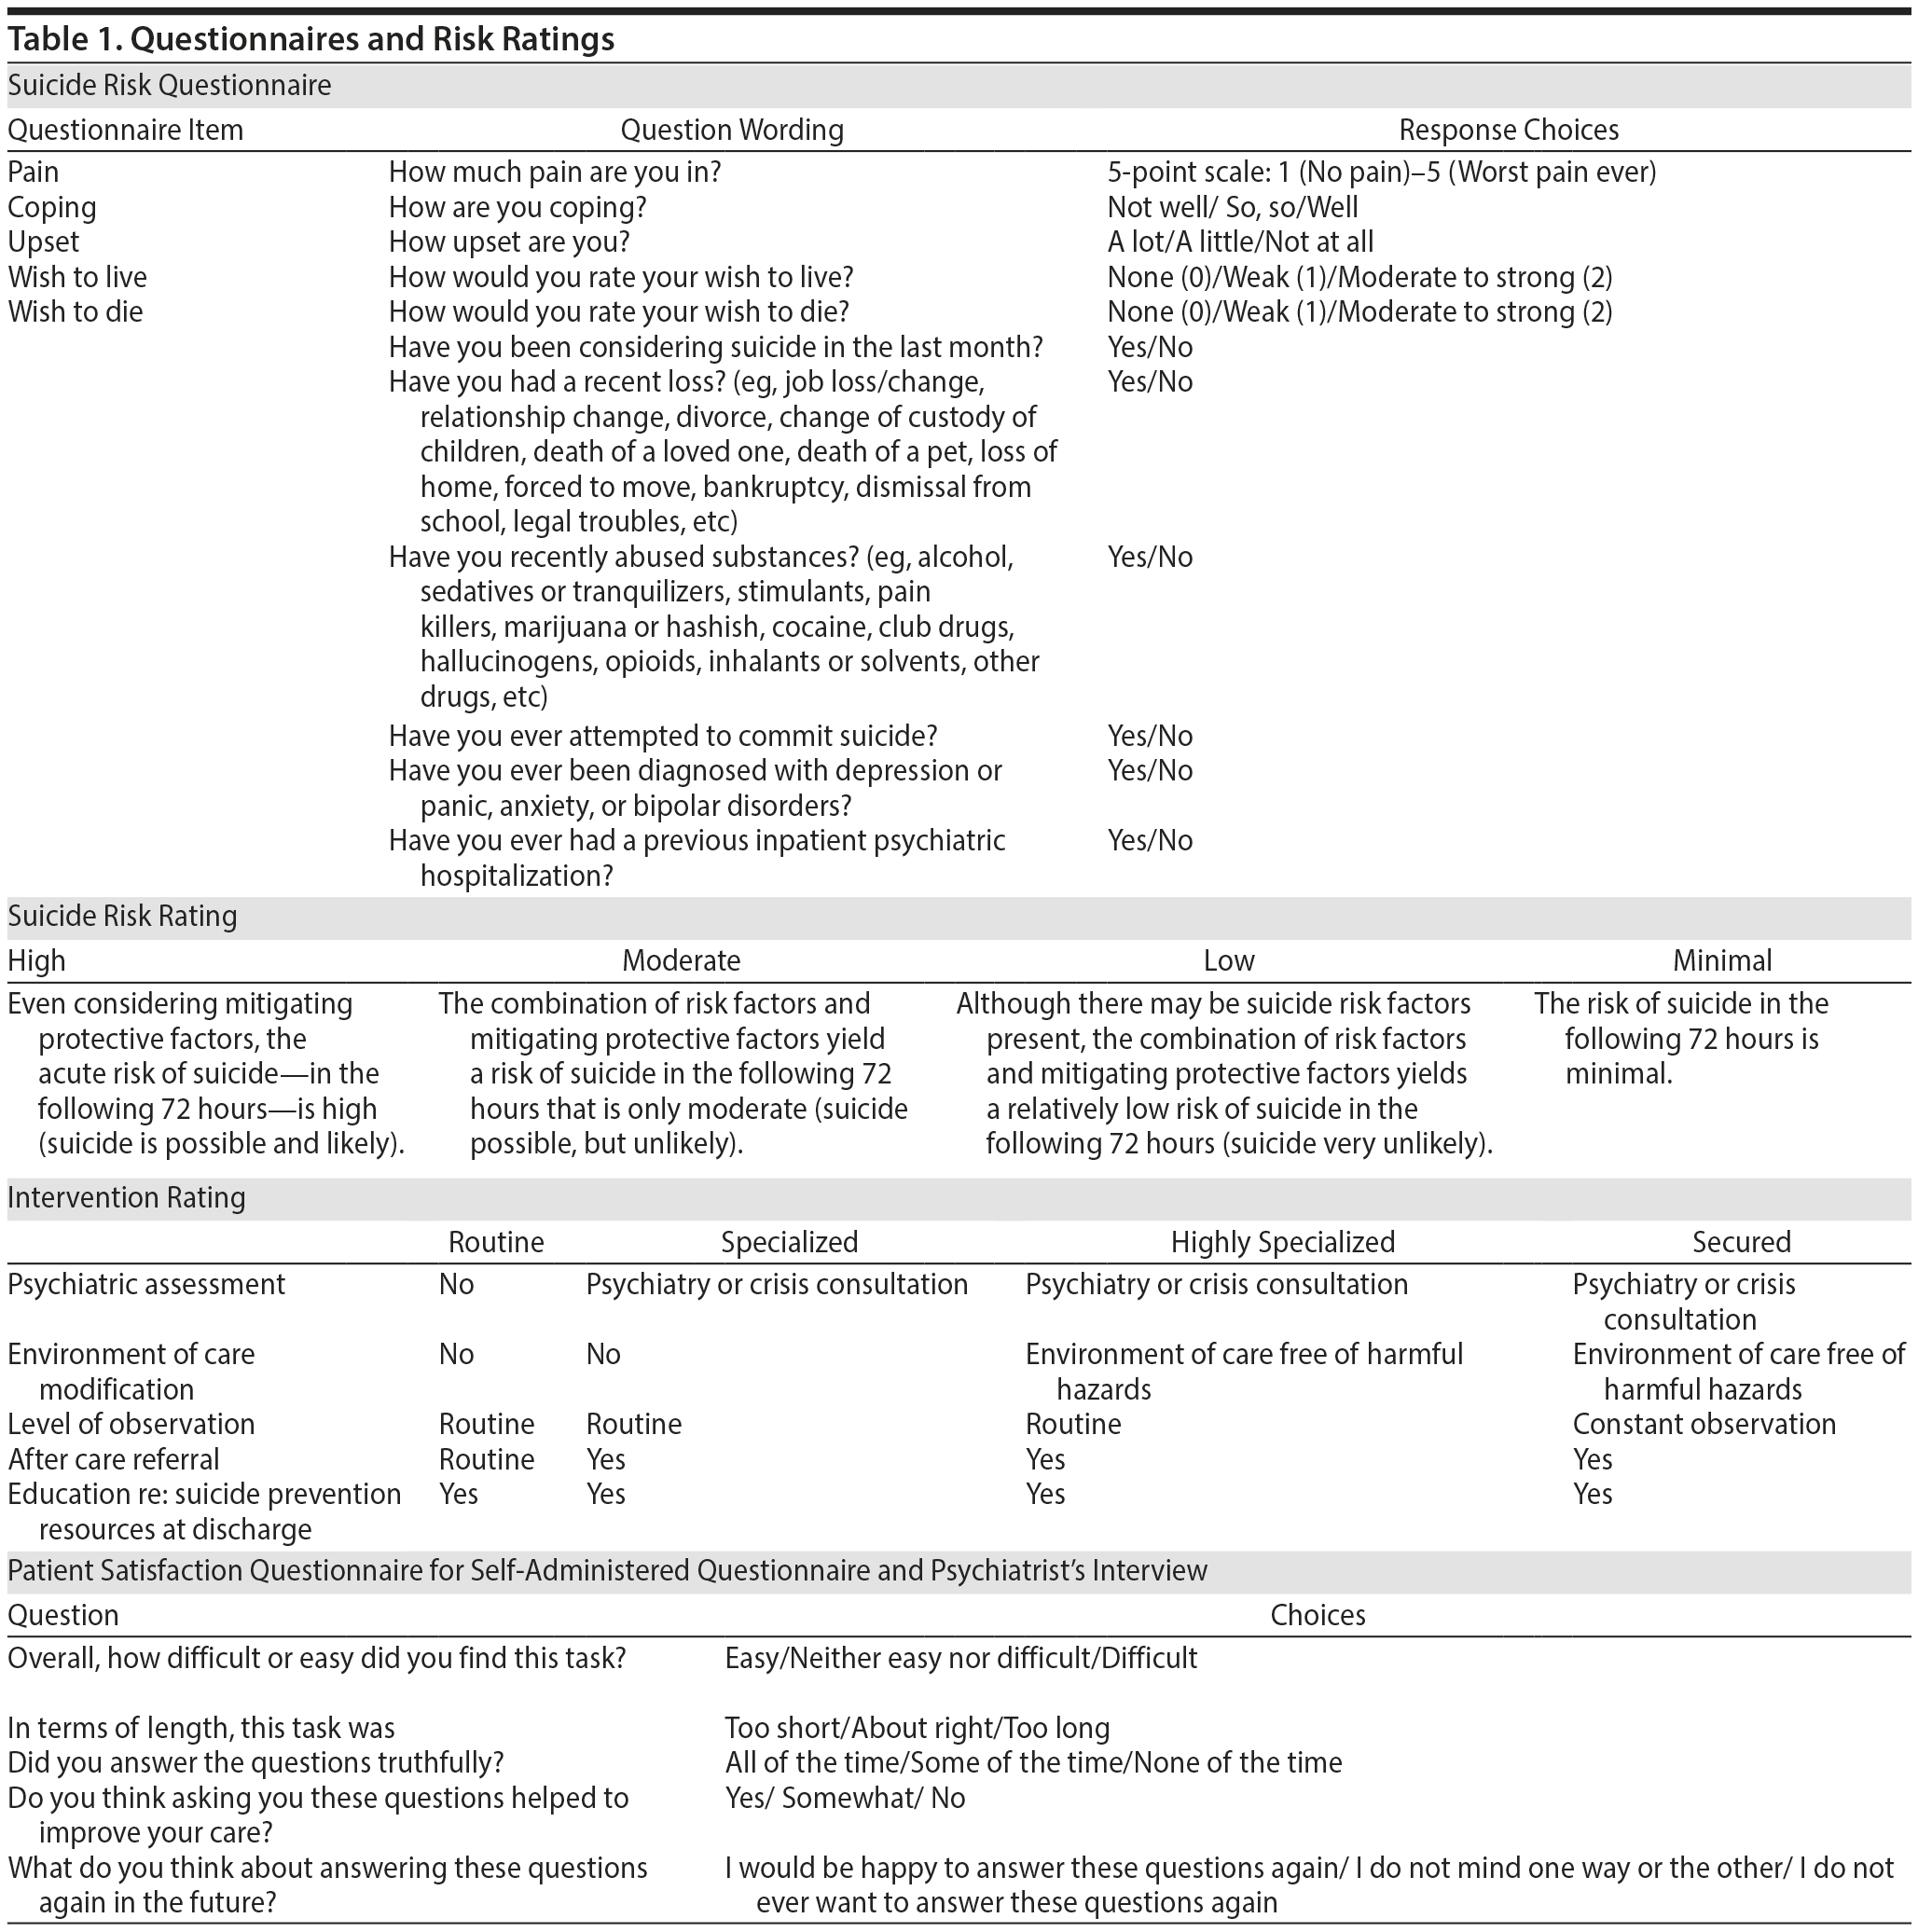
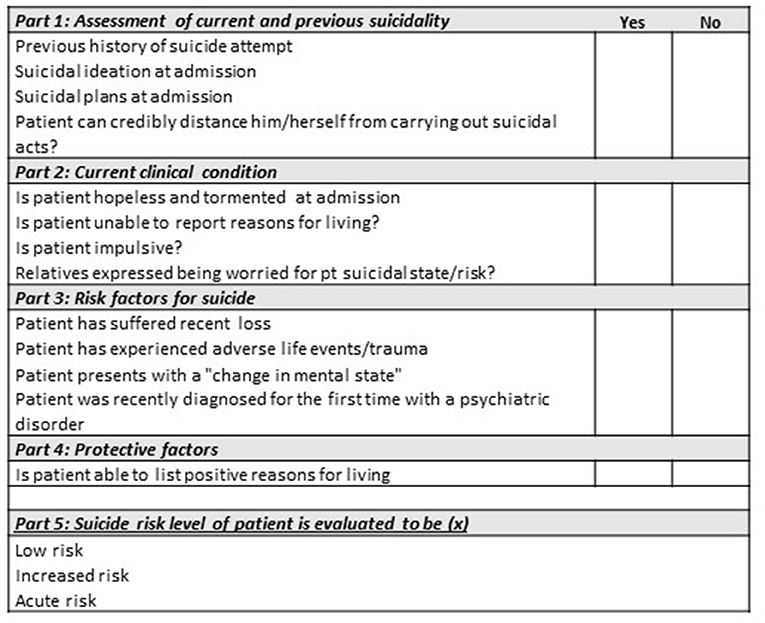
Here is the core mechanic: the tool takes a set of weighted variables and produces a score. That score maps to a risk category. Common variables include prior attempts, family history of suicide, diagnosed mental illness, substance use, social isolation, access to lethal means, and current suicidal ideation severity. The Columbia-Suicide Severity Rating Scale works differently than the SAD PERSONS scale, which is different again from actuarial instruments like the SARA or the IRI. Each has its own validation data, which is important because most tools fail outside their original population. I ran into a specific problem last year that took me about six weeks to properly resolve. We were using a commercially available Suicide Risk Assessment Tool in a community mental health clinic. The tool's built-in risk algorithm was calibrated on an inpatient psychiatric population, but our clinic served mostly outpatients with comorbid substance use disorders. The tool was systematically overestimating risk for our patients by roughly forty percent compared to actual outcomes. Patients who scored in the high-risk band were being flagged for emergency evaluation when they should have been managed at the outpatient level. This caused both resource strain and patient frustration. The workaround was straightforward but nobody told us to do it: I pulled the raw scoring items, removed the weighted factors that belonged to inpatient-specific comorbidities, and rebuilt a simple spreadsheet that applied only the validated outpatient weights from the original instrument's supplementary materials. It cut false positives down to about twelve percent. Takes about ten minutes to run each assessment now instead of the twenty-five minutes the commercial system required, and the documentation output is actually usable for billing purposes. The technical implementation detail that people consistently miss is that most Suicide Risk Assessment Tool vendors don't publish the validation cohort demographics. You need to ask. If they can't provide the original study sample characteristics, you have no way of knowing whether the tool generalizes to your patient population. I learned this the hard way with a telehealth platform that claimed clinical-grade risk stratification but couldn't produce a single peer-reviewed validation study. Their algorithm was essentially a glorified decision tree with no prospective testing.
Download and Implementation
For the tool I ended up using after abandoning the commercial system, the original Columbia protocols are publicly available through the Columbia University Irving Medical Center website at no cost. The C-SSRS comes in both clinician-rated and self-report versions, and the scoring manual is included. For the SAD PERSONS scale, you don't really need a formal download — it's ten binary items that you can write on a sticky note. The real implementation work is in the workflow around the tool, not the tool itself. Setting it up properly involves three steps. First, choose the instrument based on your setting. Inpatient units benefit from longitudinal tools like the C-SSRS that can track change over time. Outpatient clinics often do better with brief screens like the PHQ-9 item 9 combined with a means assessment. Second, build the documentation requirement into your intake template so clinicians aren't treating it as optional. Third, establish a clear escalation pathway tied to specific score thresholds. A tool that generates a high-risk score without a corresponding action protocol is just anxiety generation. There are honest limitations here that nobody advertises. Static risk assessment tools cannot predict individual behavior with any reliable accuracy. Even the best validated instruments have positive predictive values in the single digits for completed suicide. This means the vast majority of high-risk flags are false positives. That is not a flaw in your implementation. That is the current state of the science. The tools are useful for risk stratification and resource allocation, not for prediction. Accepting that fact changes how you use them.
Get the Full Details

Another common failure mode is instrument drift. I've seen clinics administer the same Suicide Risk Assessment Tool for years without recalibrating because their population demographics shifted. An aging patient panel, a change in referral patterns, a new insurance population — all of these change the base rate of risk, and the tool doesn't adapt automatically. Running a simple audit every six months comparing tool outputs against actual adverse outcomes takes about two hours and usually reveals something worth adjusting. If you need something faster and cheaper than a full clinical instrument, the ASQ (Ask Suicide-Suicide Screening) tool developed by the CDC is freely available and takes approximately ninety seconds to administer. It's designed for emergency departments and primary care. It won't replace a comprehensive assessment, but it catches more cases than unstructured clinical judgment alone, which is more than most practices currently do.