Closure Techniques and Terminology You Actually Need to Know
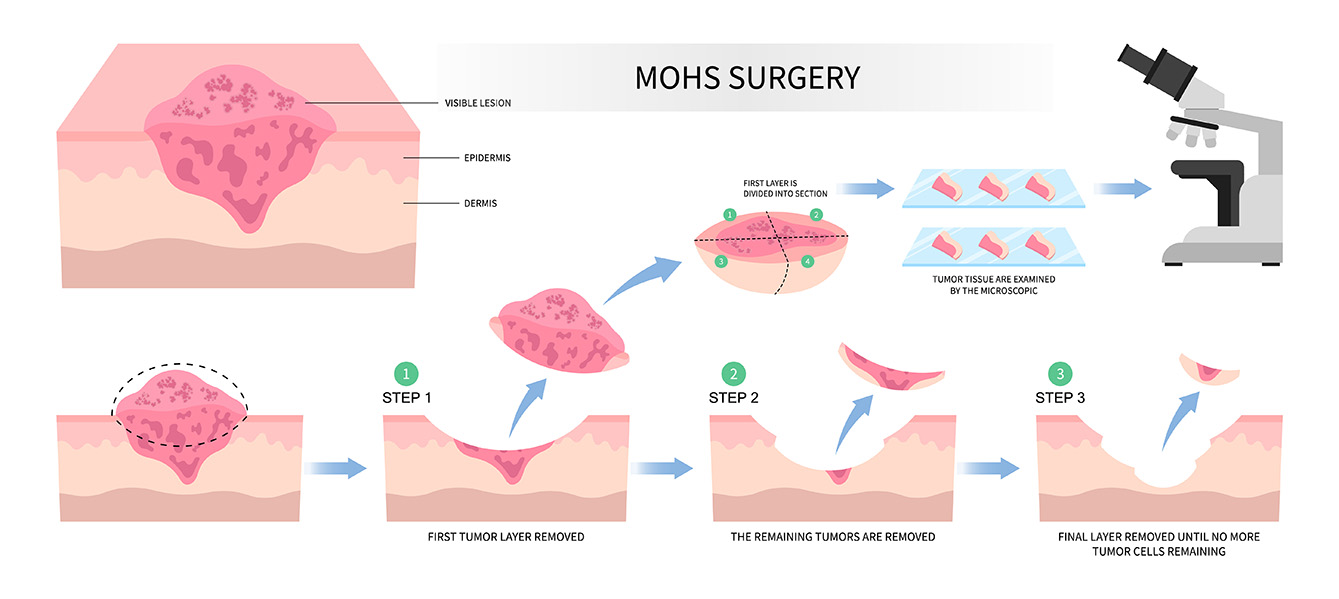
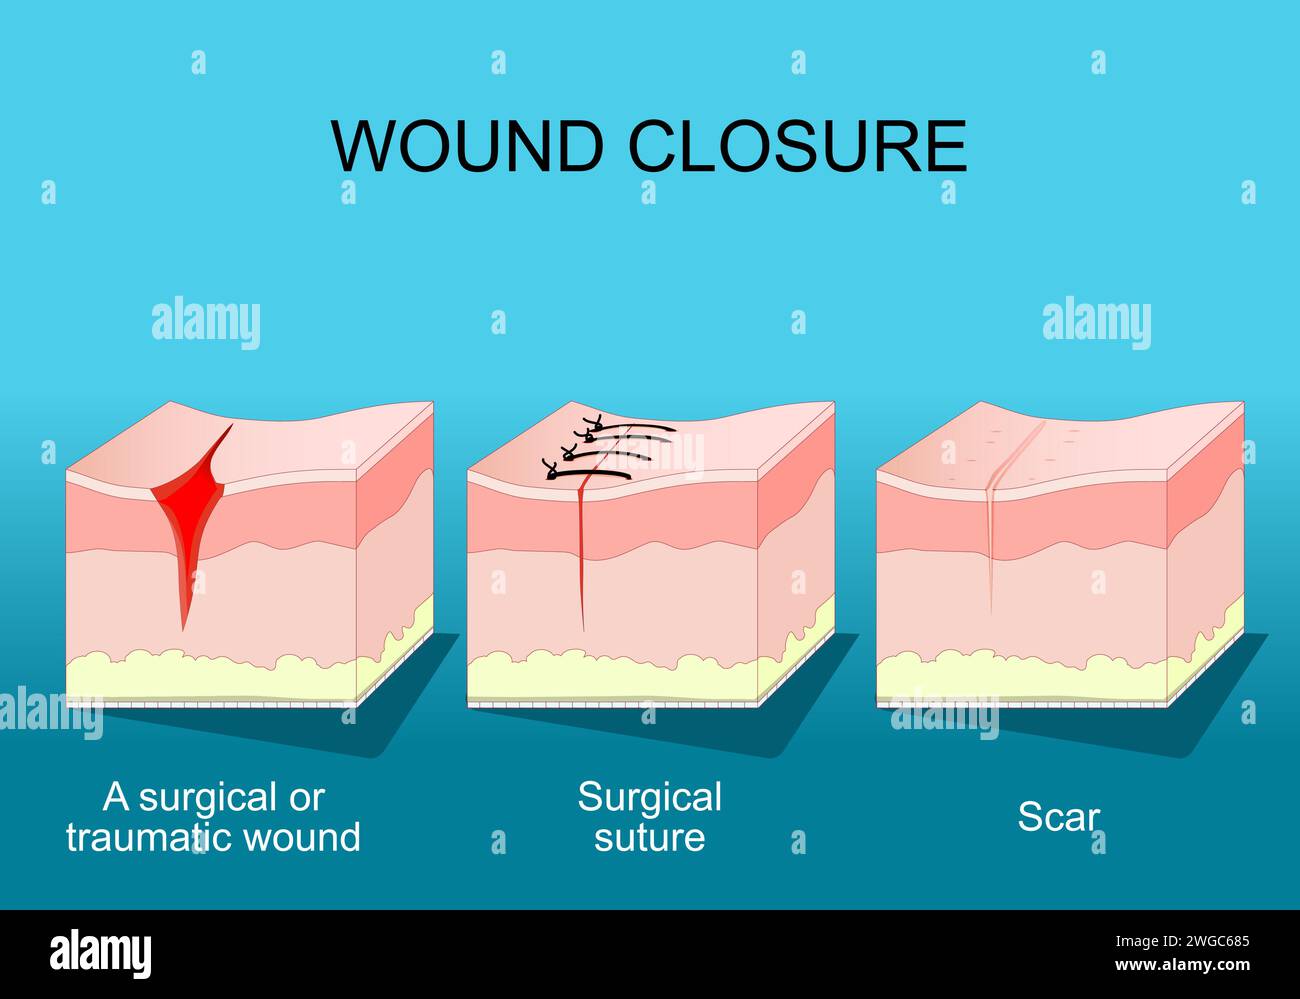
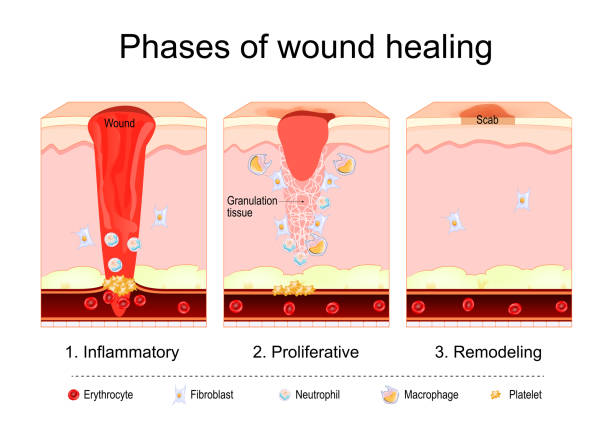
Most people searching for the surgical repair of the skin medical term are trying to decode a procedure note or understand post-op instructions. The reality is that the field is far more granular than a single word covers. What you're looking at usually falls into categories defined by the geometry of the closure, not just the incision itself. Let me break down what matters in practice. The broad umbrella term is "plastic surgical closure" or "wound closure," but that's almost never what appears on a chart. You'll see more specific terminology depending on technique. Primary intention closure means the wound edges are approximated directly—sutures, staples, or adhesive strips pull the skin together and it heals from the inside out. This is what happens with a clean surgical incision. Secondary intention is when you leave the wound open and let granulation tissue fill it from the base. Third intention, or delayed primary closure, sits between the two. You pack the wound open for a few days to control contamination or edema, then close it surgically once the field is cleaner. I've used this approach on contaminated extremity lacerations where the tissue was swollen enough that closing immediately would have compromised perfusion.
Wound Classification and What It Dictates
The Class I through IV system determines whether elective closure is even appropriate. A Class I clean wound—a hernia repair, for instance—has less than a 2 percent infection rate with primary closure. A Class III contaminated wound, like an open fracture or a bowel perforation, carries upwards of a 10 to 15 percent risk. Closing those primarily without a strong reason is how you get wound dehiscence and necrotizing soft tissue infections. The type of tissue you're working with changes the terminology too. Dermis versus epidermis matters for suture depth. Subcutaneous closures use running vertical mattress sutures or subcuticular techniques, while the dermal layer takes the tension. If you're placing sutures only in the epidermis on a high-tension area, the wound will dehisce within days regardless of how careful you were initially. The old teaching was that subcutaneous closure was optional. In facial surgery especially, leaving it out increases tension on the epidermal line and widens the scar significantly.
Suture Selection That People Get Wrong
Absorbable versus non-absorbable is the basic split, but the real decisions come down to tissue reaction and pull-through resistance. Monocryl absorbs by hydrolysis and causes minimal tissue reaction, which is why it's standard for subcuticular facial closures. Vicryl, on the other hand, is braided and elicits more inflammation. I've seen practitioners use Vicryl in the subcutaneous layer of a face lift and end up with suture granulomas weeks later. Switch to PDS or Monocryl in facial planes and that problem essentially disappears. Nylon and polypropylene are the non-absorbable choices. Prolene is smoother and slips through tissue more easily, which matters when you're doing fine work around the eyelid. Nylon holds its knot better but is more rigid. For a lip repair, I prefer 5-0 or 6-0 Prolene for the superficial layer and 4-0 Vicryl Rapide for the deeper dermal sutures because Rapide loses tensile strength predictably within two weeks, which is exactly when facial wounds have enough inherent strength to stand on their own.
Get the Full Details

Grafts and Flaps: When Approximation Isn't an Option
Full-thickness skin grafts take a punch of donor tissue and transplant it directly. The classic donor site is the postauricular sulcus or the supraclavicular region. These heal with minimal contour change and match color better than split-thickness grafts. Split-thickness grafts are harvested with a dermatome and include epidermis plus a portion of the dermis. They survive on imbibition and inosculation in the first forty-eight hours, then revascularize from the wound bed. The trade-off is that STSG contracts significantly more than FTSG over time, which is problematic around the eyes or mouth. Local flaps move adjacent tissue without severing blood supply. Rotation flaps, advancement flaps, and transposition flaps each have geometric constraints. A Limberg rhomboid flap is elegant on paper but fails when the tissue is tense or the patient has significant subcutaneous fat in the area. I've had to abandon a planned rotation flap on a pretragonal scalp defect because the hair-bearing skin simply wouldn't mobilize without causing traction alopecia along the incision line. I switched to a delayed primary closure with serial excisions instead, which added two procedures but preserved the hairline.
Common Pitfalls That Cause Revisions
Evert the wound edges. If you approximate skin with the edges inverted, the healing scar will be depressed and more noticeable. This sounds obvious until you're working under magnification with fine instruments and the edge rolls under anyway. Using a few interrupted vertical mattress sutures as your foundation everts the edges before you place the final epidermal bites. They leave their own marks, but those resolve within six to eight weeks while the eversion persists during the critical early healing phase. Tension is the silent scar killer. A wide, relaxed scar is often better than a narrow, tensioned one. I've seen this repeatedly on lower leg closures where the practitioner chased perfect alignment and ignored the lateral pressure. The wound didn't fail acutely, but six months later the scar was three millimeters wide and hyperpigmented. Leaving the wound partially open for secondary intention on that same leg would have healed faster with a better cosmetic result because the lower leg has poor vascularity and heals predictably slower under any tension. Z-plasty and W-plasty are revision tools, not first-pass techniques. Placing a Z-plasty to break up a straight-line contracture makes sense when the original scar is already mature and causing functional limitation. Doing it preemptively during initial closure rarely improves outcomes and adds complexity that introduces more potential points of failure. The same applies to geometric broken-line closures. They work when planned carefully from the start, but adding them after the fact because you're worried about a linear scar usually looks worse than the original straight line would have.
Adhesive and Staple Options Worth Considering
Dermabond and similar cyanoacrylate adhesives have a legitimate place in low-tension, straight-line incisions on the face and trunk. They provide a moisture barrier, don't require removal, and produce less track-mark scarring than sutures when used appropriately. The downside is that they offer zero tensile strength. On a joint area or any wound under movement, adhesive alone is inadequate. I've used it for simple facial lacerations under 2 centimeters and combined it with deeper dermal sutures for anything longer or in higher-tension zones. Staples are fast but leave distinctive linear scarring. They're reasonable for scalp closures where speed matters and cosmetic outcome is less critical, but they're not the right choice for facial work. The staple marks themselves can persist as permanent dots along the incision line if left in too long. Removing scalp staples after seven to ten days minimizes this, and transitioning to adhesive strip support for another week reduces tension while the wound gains strength.
What Good Wound Closure Actually Looks Like
The goal isn't invisibility. Skin has Langer's lines and tension vectors that dictate where scars naturally form. Aligning an incision with these lines does more for the final appearance than any suture technique ever will. A well-placed incision along the nasolabial fold or the preauricular crease will remain nearly imperceptible even with basic closure. A perpendicular incision across the forehead will always show something, regardless of how carefully it's sutured. Suture removal timing matters more than most people realize. Face at five to seven days. Scalp at seven to ten. Extremities at ten to fourteen. Trunk at fourteen to twenty-one. Leaving sutures in past these windows increases the risk of track marks and cross-hatch scarring. I've lost count of the number of patients who came back months later complaining about visible puncture marks, only to discover the sutures had been left in for three weeks on the chest because of scheduling delays. Taping the incision after suture removal with 3M Micropore or silicon-based strips for another four to six weeks reduces tension on the healing wound. This is one of the most underutilized steps. The adhesive provides continuous low-level support as the collagen remodels, and the silicone component of certain tapes also helps with hypertrophic scar prevention. It's a cheap, low-effort intervention that changes the trajectory of the final scar significantly.