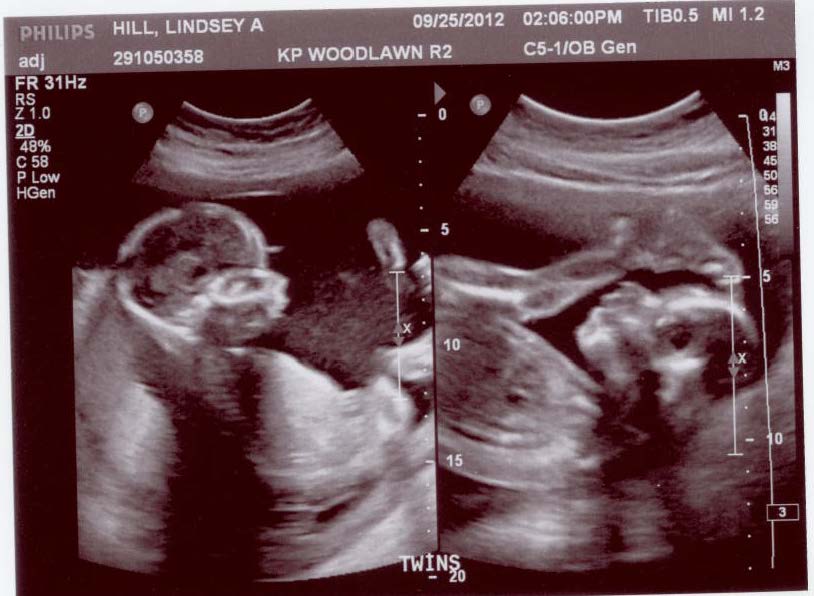
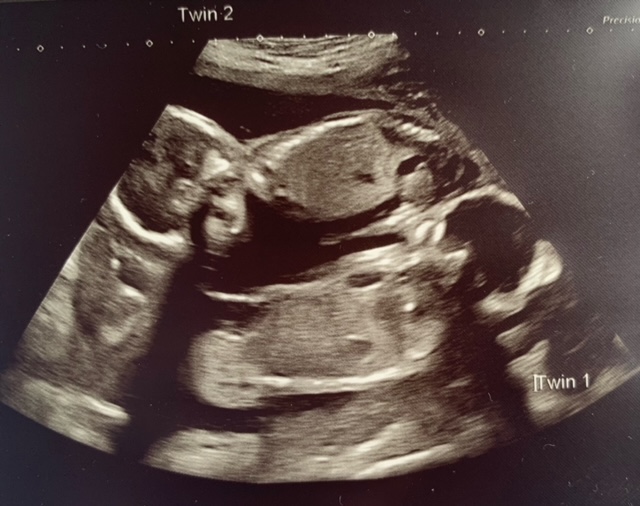
What Actually Happens When You Find Twins Mid-Scan
The anatomy scan is usually scheduled around 18 to 22 weeks, and most sonographers go in expecting one fetus. I have been running scans for over a decade, and I have lost count of how many times the probe hits the uterus and suddenly there are two distinct cardiac rhythms playing at once. The room goes quiet for about three seconds. Everyone freezes. Then the real work starts. When you find surprise twins during an anatomy scan, you are not just looking at two babies. You are suddenly responsible for determining chorionicity and amnionicity on the fly. That means figuring out whether they share a placenta, whether they share a sac, and whether anything looks immediately wrong. You cannot just report "twins" and send the patient home. The dating might be off. The first-trimester scan that should have caught this might never have happened. Now you are working without a baseline.
Why Surprise Twins At Anatomy Scan Is Different From Planned Twin Monitoring
Planned twin pregnancies get serial growth scans, early anatomy surveys, and a clear management pathway because everyone knows what to expect. Surprise twins at anatomy scan means you are doing the diagnostic work in real time while the patient is still on the table. There is no pre-scheduled follow-up. There is no maternal-fetal medicine specialist waiting in the wings. You are the one who has to determine viability, estimate gestational age for both fetuses, map the intertwin membrane if it exists, and flag anything abnormal before the patient leaves the room. The biggest practical problem is time pressure. A standard single-fetus anatomy scan takes about 30 to 45 minutes. A surprise twin anatomy scan needs at least double that. You need to image both cardiac systems, both stomachs, both kidneys, both bladder fills, and both spines. You need to measure both head circumferences and femur lengths independently. You need to examine the placental mass and the membrane insertion point carefully. Most clinics do not block enough time for this, so you end up rushing through critical structures or skipping them entirely because the next patient is already checking in. I ran into a specific case where the twins were monochorionic but the shared placenta was positioned posteriorly against the maternal spine, and the anterior twin was compressing the posterior one significantly. The acoustic window was terrible because of fetal positioning and maternal body habitus. What I ended up doing was having the patient roll onto her left side and hold that position for about ten minutes while I swept slowly through the intertwin space with a lower-frequency transducer. That shift in position freed up enough space to visualize the dichorionic membrane insertion point and confirm we were dealing with monochorionic diamniotic twins rather than a misinterpreted single sac. Without that maneuver, I would have underestimated the chorionicity and missed the higher-risk classification entirely.
The Practical Steps I Follow After the Initial Discovery
First, I confirm cardiac activity in both fetuses separately. You count the beats independently. You do not assume two heart tones from one fetus. I then switch to measurement mode and record the crown-rump length or biparietal diameter for each one. If the measurements differ by more than five to seven millimeters at this stage, that is a red flag for discordant growth, and I note it immediately rather than waiting for a later scan to discover it. Next, I determine chorionicity. This is the single most important clinical question. I look for the lambda sign, which indicates a dichorionic pregnancy, or the T-sign, which points toward monochorionic. I examine the placental mass to see if it is truly one shared structure or two distinct placentae that may be fused. If I can clearly identify two separate placentae with intervening myometrium between them, that is dichorionic. If it is one consolidated mass with no myometrial bridge, that is monochorionic. Getting this wrong has serious downstream consequences because monochorionic twins carry risks like twin-twin transfusion syndrome that require close monitoring every two weeks starting around 16 weeks. After establishing chorionicity, I move through the standard anatomy survey for each fetus. Heart four-chamber view. Outflow tracts. Brain structures including the ventricles and cisterna magna. Spine in both longitudinal and transverse planes. Abdominal wall. Kidneys and bladder. Extremities. This takes longer than the single-fetus protocol because I cannot rely on the same sweep patterns. Each fetus needs its own dedicated pass through every organ system. I usually complete this portion in about 20 to 25 minutes after the initial discovery, but if either fetus is in a poor position, that time can stretch considerably.
Get the Full Details

Finally, I document everything with images of both hearts beating, a measurement comparison, the membrane or placental assessment, and notes on amniotic fluid volume around each fetus. Monochorionic pregnancies should have roughly equal fluid, and significant imbalance between the two sacs is another warning sign I flag immediately.
Common Pitfalls That Trip People Up
The most frequent error I see is assuming a single placenta means monochorionic without actually checking the membrane insertion. Fused dichorionic placentae look almost identical to a single monochorionic placenta on a quick glance. The difference is in how the membrane attaches. A true T-sign means the membrane meets the placental surface at a right angle with no visible supporting tissue, while a lambda sign shows a triangular projection of placental tissue between the membrane layers. Missing this distinction at the anatomy scan level can delay the referral pathway by weeks. Another issue is gestational age dating. When twins are found incidentally, the first-trimester dating scan was likely performed on the assumption of a singleton pregnancy. The measured crown-rump length from that earlier scan may only reflect one of the fetuses. The second fetus could be slightly smaller or slightly larger and the discrepancy went unnoticed because the sonographer was not looking for a second gestational sac. I have seen cases where the second twin was several days off in dating simply because the initial scan only imaged one fetus adequately. This matters for scheduling follow-up scans and timing any interventions. There is also a tendency to rush the cardiac assessment because the sonographer assumes both hearts look fine if they both appear to be beating. But in monochorionic pregnancies, structural cardiac anomalies run at a higher rate. I make a point of spending extra time on the four-chamber view and the outflow tracts for each twin separately, even when the rhythm looks normal. The extra five minutes upfront prevents a missed anomaly that would otherwise show up much later.
What Patients Need To Know After The Scan
The emotional component is real and it should not be minimized. A patient who walked in thinking she was carrying one baby and left knowing she is carrying two is processing a significant shift. The medical details matter, but so does giving them a clear explanation of what happens next. Monochorionic twins need biweekly monitoring starting at 16 weeks. Dichorionic twins need growth scans every four weeks beginning around 24 weeks. Both types need a detailed anatomy review if the initial surprise scan was limited by positioning or other factors. I always provide a written summary with the chorionicity determination, the measurements for each fetus, and the referral recommendations. Without that documentation, patients often leave confused about what the findings actually mean and what the next appointment will involve. They also tend to forget the clinical distinctions between mono and dichorionic during the conversation, so the paper trail becomes their reference point going forward. The surprise itself is usually resolved within minutes of the scan. The follow-up uncertainty lasts much longer. Making sure the clinical pathway is clear from the moment the patient leaves the exam room is what separates a competent response from a rushed one.