Understanding Systemic Arterial Blood Pressure in Clinical Practice
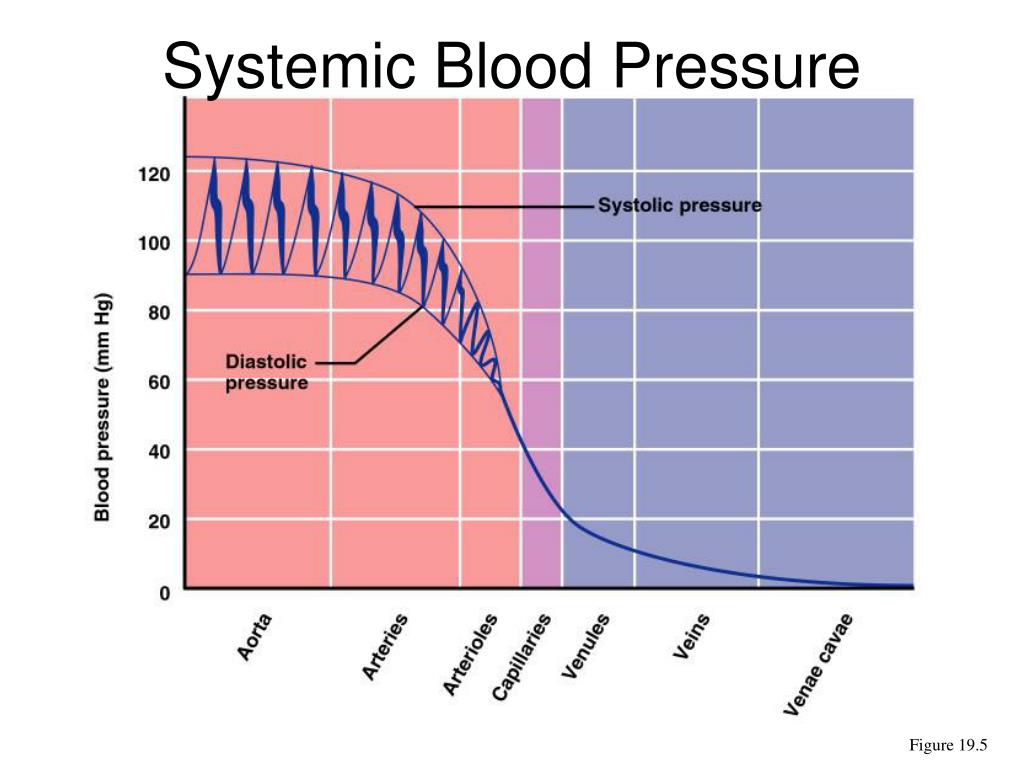
Most people treat blood pressure as a single number you grab from a cuff reading and move on. That approach works fine for routine checkups, but it breaks down the moment you're dealing with anything beyond a healthy outpatient clinic. The gap between what a standard auscultatory measurement tells you and what systemic arterial blood pressure actually represents is where a lot of misdiagnoses happen. I learned this the hard way during residency when a hypertensive emergency case was initially missed because we were reading the wrong part of the waveform. Systemic arterial blood pressure refers to the force exerted by circulating blood against the walls of the systemic arteries, specifically the arterial system that delivers oxygenated blood from the left ventricle to the rest of the body. It is not a single static value but rather a dynamic pressure profile that fluctuates with every cardiac cycle. The standard numbers clinicians quote — systolic over diastolic — represent just two points on a continuous pressure curve.
What Systemic Arterial Blood Pressure Actually Measures
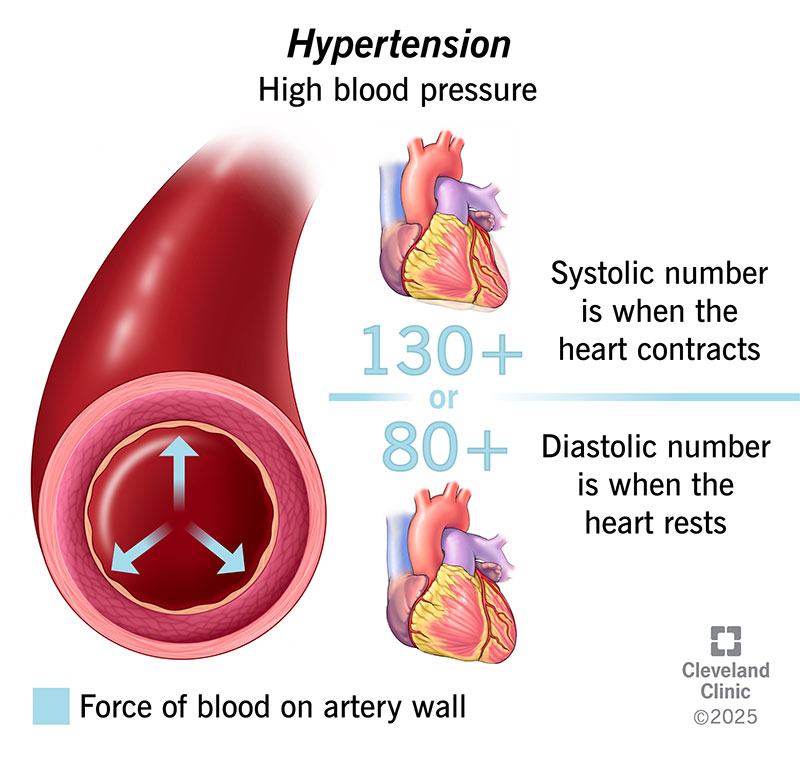
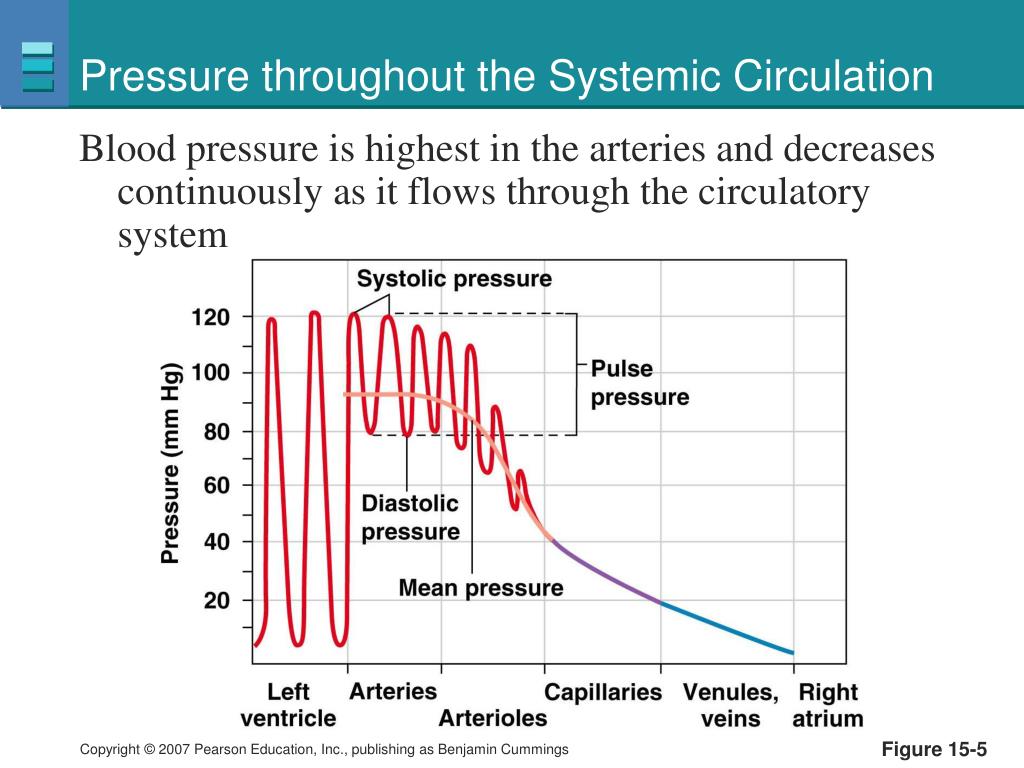
The systolic reading captures the peak pressure generated when the left ventricle contracts and ejects blood into the aorta. The diastolic reading reflects the minimum pressure in the arterial system during ventricular relaxation, maintained primarily by arterial tone and peripheral resistance. Between those two numbers lies the mean arterial pressure, which is what actually drives organ perfusion. A common calculation puts MAP at approximately one-third of the pulse pressure added to the diastolic value, though in practice it sits closer to the formula: MAP = diastolic + (systolic - diastolic) / 3. The waveform itself has characteristic features. The upstroke, or anacrotic limb, rises rapidly during systolic ejection. The dicrotic notch appears on the downstroke and marks the closure of the aortic valve. Beyond that notch lies the diastolic runoff, which slopes gradually toward the next systolic peak. The shape of this waveform tells you more than the numbers alone — it reveals information about stroke volume, arterial compliance, and systemic vascular resistance.
Why Non-Invasive Measurements Miss Critical Details
The oscillometric cuff method, which is what nearly everyone encounters, has well-documented limitations. It estimates blood pressure by detecting oscillations in the cuff's air pressure as the artery opens and closes beneath the compression. These oscillations peak somewhere between systolic and diastolic, which is why automated cuffs often report a mean arterial pressure rather than true systolic and diastolic values. The device then applies proprietary algorithms to guess the systolic and diastolic readings from that waveform. This creates problems in specific clinical situations. Patients with severe peripheral arterial disease frequently have inaccurate cuff readings because their arteries are stiff and non-compliant. Atrial fibrillation produces irregular heartbeats that confuse the averaging algorithms in automated devices. Hypothermia causes peripheral vasoconstriction that makes distal pulses nearly undetectable and cuff readings unreliable. I once had a patient with end-stage renal disease whose cuff readings suggested stage two hypertension, but an arterial line placement revealed a mean arterial pressure of 48 — dangerously low for someone with chronic renal insufficiency. The discrepancy existed because the auscultatory gap, a silent interval between the true systolic sound and the first audible Korotkoff sound, caused the cuff method to significantly underestimate the actual systolic pressure.
Get the Full Details
Invasive Monitoring and What It Reveals
Direct intra-arterial catheterization provides continuous, real-time pressure data that non-invasive methods simply cannot match. A catheter placed in the radial artery and connected to a pressure transducer converts mechanical pressure into electrical signals that display as a waveform on a monitor. The radial artery is the preferred site because it is superficial, relatively accessible, and its waveform closely mirrors central aortic pressure in healthy individuals. The waveform gained from an arterial line shows you pulse pressure variation, which is useful for assessing fluid responsiveness in critically ill patients. It reveals an elevated dicrotic notch position in conditions like aortic stenosis. It shows dampened waveforms when there is an air bubble in the tubing or when the catheter tip presses against the vessel wall. A falsely elevated reading can occur if the transducer is positioned above the level of the right atrium, while a reading positioned below will overestimate the true pressure. Leveling the transducer to the phlebostatic axis — roughly the fourth intercostal space at the mid-axillary line — remains essential for accuracy. I encountered a situation where a septic shock patient appeared to be maintaining adequate blood pressure by cuff standards, but the arterial line showed a severely dampened waveform with a narrow pulse pressure. The mean arterial pressure looked acceptable on the monitor, but the dampening artifact was hiding a collapsing cardiac output. Flushing the line and checking for air bubbles resolved the dampening, and the corrected waveform revealed a MAP that was actually 20 mmHg lower than the initial reading suggested. That corrected value changed the entire resuscitation plan.
Factors That Alter Systemic Arterial Pressure Readings
Age dramatically affects arterial compliance. Young patients with elastic arteries tend to have wider pulse pressures during exercise because their vessels distend readily. Older patients with stiff, arteriosclerotic vessels show isolated systolic hypertension — high systolic pressure with normal or even low diastolic pressure. This decoupling of systolic and diastolic values is increasingly common in patients over sixty-five and requires different treatment considerations than combined systolic-diastolic hypertension. White coat hypertension affects approximately twenty to thirty percent of patients who present with elevated office readings but normal ambulatory measurements. Conversely, masked hypertension occurs in patients whose clinic readings are normal but who have elevated blood pressure throughout the day. Ambulatory blood pressure monitoring over twenty-four hours remains the gold standard for distinguishing these patterns. Home monitoring protocols can also help, though patients must be instructed properly on cuff placement, rest periods, and measurement timing to get usable data. Medications interact with blood pressure measurement in ways that are easy to overlook. Beta-blockers blunt the systolic rise during activity, making resting measurements seem more reassuring than they should be. Vasodilators can cause postural hypotension that only appears after standing for several minutes. I found that a patient on clonidine had deceptively stable readings at rest, but the medication was masking orthostatic drops that only became apparent during active physical examination. Checking blood pressure in supine, sitting, and standing positions within the first three minutes of standing remains an inexpensive diagnostic step that catches these issues.
When Systemic Arterial Pressure Numbers Lie
Certain conditions produce readings that are technically accurate but clinically misleading. In severe aortic regurgitation, the wide pulse pressure reflects both a high systolic value and a characteristically low diastolic pressure due to backward flow into the left ventricle. The mean arterial pressure may appear normal, but tissue perfusion can still be compromised because the low diastolic pressure limits coronary artery filling. Treating the numbers without understanding the underlying hemodynamics leads to poor decisions. Pulse pressure amplification is another factor that beginners miss. Peripheral arterial pressure systolic values are typically higher than central aortic systolic pressure due to wave reflection and arterial tree properties. The radial artery systolic pressure can be ten to twenty mmHg higher than the aortic systolic pressure in younger patients. This amplification decreases with age as arterial stiffness increases. If you are comparing a radial arterial line reading to a central venous pressure trend or making treatment decisions based on peripheral waveforms, understanding this gradient matters. Extremis hemodynamic states present their own challenges. Patients in profound shock may have non-compressible arteries that make cuff measurement impossible. In cardiogenic shock, the combination of low cardiac output and high systemic vascular resistance can produce deceptively normal blood pressure readings while the patient is actually in severe distress. The term normotensive shock describes this exact scenario — adequate blood pressure numbers paired with signs of end-organ hypoperfusion such as altered mental status, cool extremities, and rising lactate levels.
Practical Approach to Evaluating Systemic Arterial Blood Pressure
A focused assessment starts with confirming the measurement technique and device accuracy before trusting any number. Verify cuff size against arm circumference — a too-small cuff artificially elevates readings by as much as twenty to thirty mmHg. Allow the patient to rest quietly for five minutes before measuring. Take multiple readings and average them rather than relying on a single value. When possible, correlate non-invasive readings with direct measurement in unstable patients. Review the waveform morphology whenever you have access to arterial line data. A sharp upstroke with a prominent dicrotic notch suggests normal ventricular function and adequate valve closure. A delayed upstroke indicates outflow obstruction or reduced contractility. A bisferiens pulse, with two systolic peaks, suggests combined aortic stenosis and regurgitation or hypertrophic cardiomyopathy. Each pattern carries therapeutic implications that a single systolic-diastolic pair cannot convey. Consider the full clinical context before acting on any blood pressure reading. A hypertensive crisis demands treatment regardless of how the measurement was obtained. An asymptomatic patient with moderately elevated readings needs evaluation for secondary causes and target organ damage before medication decisions are made. The numbers guide the workup but rarely replace it.