Getting T Scan Bite Analysis Working Without Losing Your Mind
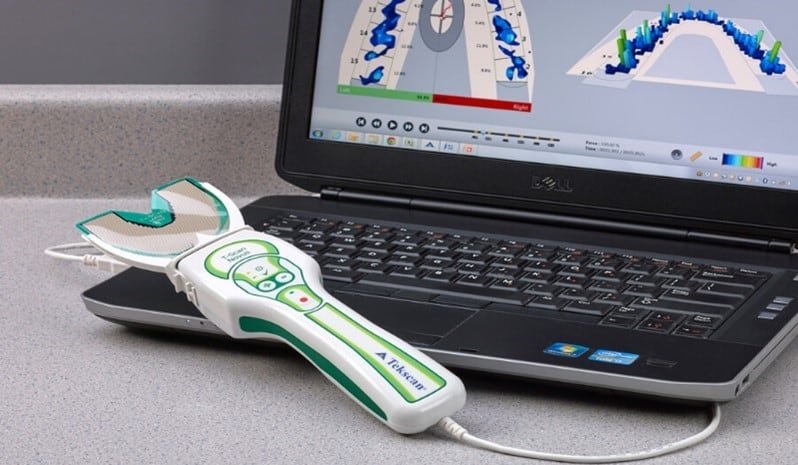
T Scan Bite Analysis is a digital occlusal force mapping system. It replaces articulating paper and wax with pressure-sensitive sensors and software that quantify how teeth contact during closure. The hardware is a thin sensor strip or sheet placed between the arches. Software then captures timing and force data across the bite cycle. The workflow starts with the sensor. Depending on which version you have, that means either the T-Sense single-use strips or the T-Scan III sensor pad. Clean the patient's teeth first, because plaque, saliva, and any residual luting cement will throw off readings. A quick prophylaxis paste clean and a dry field matter more than people admit. Load the sensor into the handheld scanner unit or the benchtop system, then open the T-Scan software. Create a new patient record. The software walks you through sensor calibration, which usually takes thirty seconds. If the calibration fails, check the connector pins for debris and make sure the sensor isn't folded or creased. Even a small wrinkle causes phantom contact points in the data.
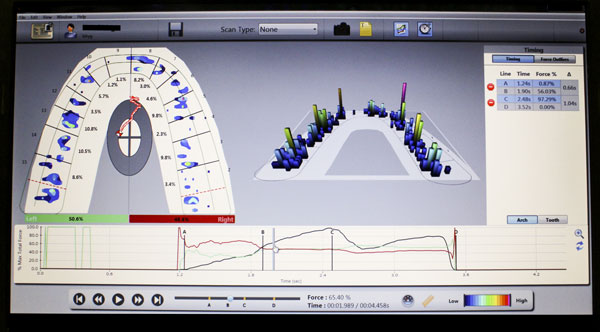
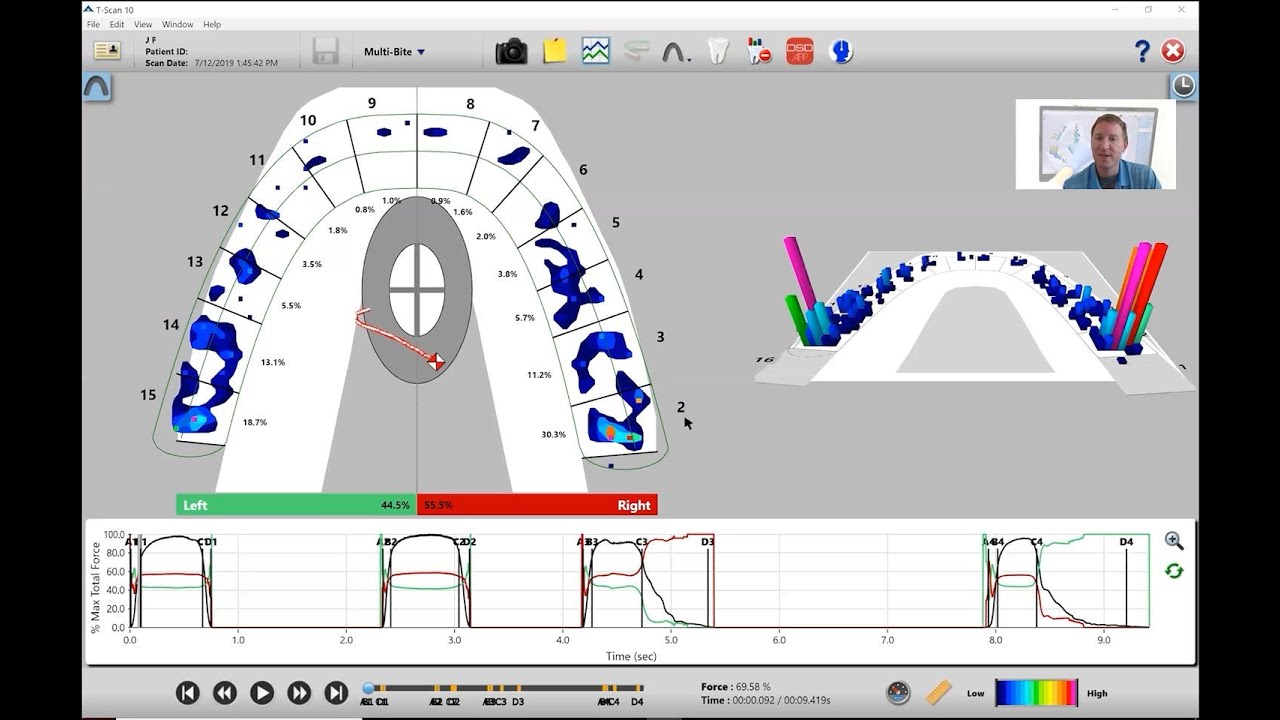
For the actual bite registration, the patient closes gently into centric relation or their intended occlusion, then performs excursive movements if you're running a dynamic analysis. Each input type generates a different dataset. I run static registrations for equilibration cases and dynamic cycles for full reconstruction planning. The software displays contacts as colored bars on a timeline, with force values in Newtons and timing in milliseconds. Save the data before anything else. The software has been known to crash mid-session, especially on older machines running Windows 10 legacy systems. I learned that the hard way after a three-hour crown case when a power flicker wiped an un saved registration.
Reading the Output Correctly
The force-time graph is the core of the analysis. Peak force tells you where the heaviest load hits. Timing tells you whether contacts are simultaneous or sequential. A delayed contact shows up as a later bar on the timeline. Early contacts appear on the left side of the window. If you see scattered, low-force contacts across the board, the sensor may be slipping or the patient isn't guiding properly through closure. One thing beginners consistently miss: the software reports relative force distribution, not absolute occlusal force. A reading showing 30 percent on a first molar means it bears 30 percent of the total recorded load in that specific closure attempt. It does not tell you the patient's actual maximum intercuspation force unless you've calibrated with a known reference load. That distinction matters when you're deciding whether to adjust a high spot or leave it alone. Another nuance is the difference between C-point and ICC point. C-point is the first point of contact during closure. ICC is the intercuspal position where the teeth nestle together. In an ideal bite they overlap nearly perfectly. When they diverge significantly, you're looking at slide or guidance issues that the sensor alone won't fix. The numbers will show you the discrepancy, but interpreting it requires knowing whether the patient has muscle hyperactivity, joint pathology, or just a restorative mistake.
Get the Full Details

A Real Problem I Ran Into
During a posterior equilibrium case on a bruxer, the T Scan kept showing bilateral posterior contacts that looked perfect on screen. Fine distribution, good timing. But the patient kept complaining of tenderness on the right side after adjustment. I spent two sessions grinding based on the readings and made the occlusion worse. The breakthrough came when I stopped trusting the static registration and ran a phonation test while watching the live feed. The moment the patient said "mississippi," a single premature contact popped up on the right second molar that the gentle closure test never revealed. That contact was invisible in the standard static protocol because the bruxer's muscles were protecting it by shifting the closure path. Once I adjusted that one spot using the dynamic tracking, the patient's symptoms resolved within a week. The moral is that static T Scan Bite Analysis misses pathologically protected contacts in hyperfunctional patients. Sensor thickness is a real issue. The T-Sense strip adds roughly 50 to 80 microns of separation between the arches. In a patient with a thin enamel bite plane or minimal occlusal vertical dimension, that extra material can shift contacts enough to change your interpretation. Some clinicians compensate by having the patient bite down harder, but that introduces variable muscle force and makes comparisons meaningless across different visits. If you need sub-50 micron accuracy, consider pairing the T Scan with a silicone bite registration for verification. Take a polyvinyl siloxane bite at the tooth positions the software suggests, pour a model, and check the contacts on thearticulator. The silicone won't show force distribution, but it confirms whether the teeth actually meet where the screen says they do. I use this verification step on all full-arch cases and on any case where the software and my clinical judgment disagree.
Software version mismatches are another quiet source of bad data. Older T-Scan IV firmware doesn't handle certain sensor types the same way as newer releases. If your force numbers seem inconsistently low across multiple patients on the same day, check the firmware version against the sensor batch number. Den Mat's support site has a compatibility chart, but it's not always up to date. Calling the technical line and confirming the pairing is faster than troubleshooting blind.
When This Method Fails Completely
T Scan Bite Analysis struggles in edentulous patients with complete dentures. The sensor needs tooth structure to register meaningful contact. With implants alone, you get minimal data because implant-supported prosthetics don't have the same periodontal ligament feedback, so the force distribution reads flat and uninformative. In those cases, go back to traditional methods: articulating paper, shim stock, and clinical judgment based on the prosthetic design. Severe Temporomandibular Joint disorders also limit reliability. Patients who can't close consistently into a repeatable position produce noisy data that looks like a random scatter plot. The software tries to interpolate, but interpolation on bad input is just a prettier version of garbage. In these scenarios, the T Scan gives you numbers, but those numbers don't correlate with clinical outcomes. Referral to a TMD specialist and conservative management before re-evaluating occlusion is the appropriate path. The system also can't distinguish between muscular and dental sources of occlusal trauma. A high force reading on a premolar might be a true occlusal interference or it might be the patient clenching due to anxiety in the chair. The sensor reports the force, not the cause. Context from the patient history and a clinical examination remains essential.

Practical Takeaways
The T Scan Bite Analysis workflow typically cuts registration and adjustment time from forty-five minutes down to about twelve minutes per session once you're proficient. Calibration and patient education add a few minutes upfront, but the time savings accumulate over a week of cases. The biggest drain isn't the technology itself, it's the learning curve for reading the output without second-guessing every data point. Buy the latest sensor batch available. Older lots sometimes have adhesive degradation that causes peeling during closure. Store sensors at room temperature, not in a hot car or a drawer next to a curing light. Humidity affects the resistive elements inside the strip. Keep a logbook of your cases with before and after T Scan data. After twenty or so cases, you'll start recognizing patterns in your own work and your own errors. That experience filter is what separates useful data from noise.