Getting Practical with Amino Acid Formulations
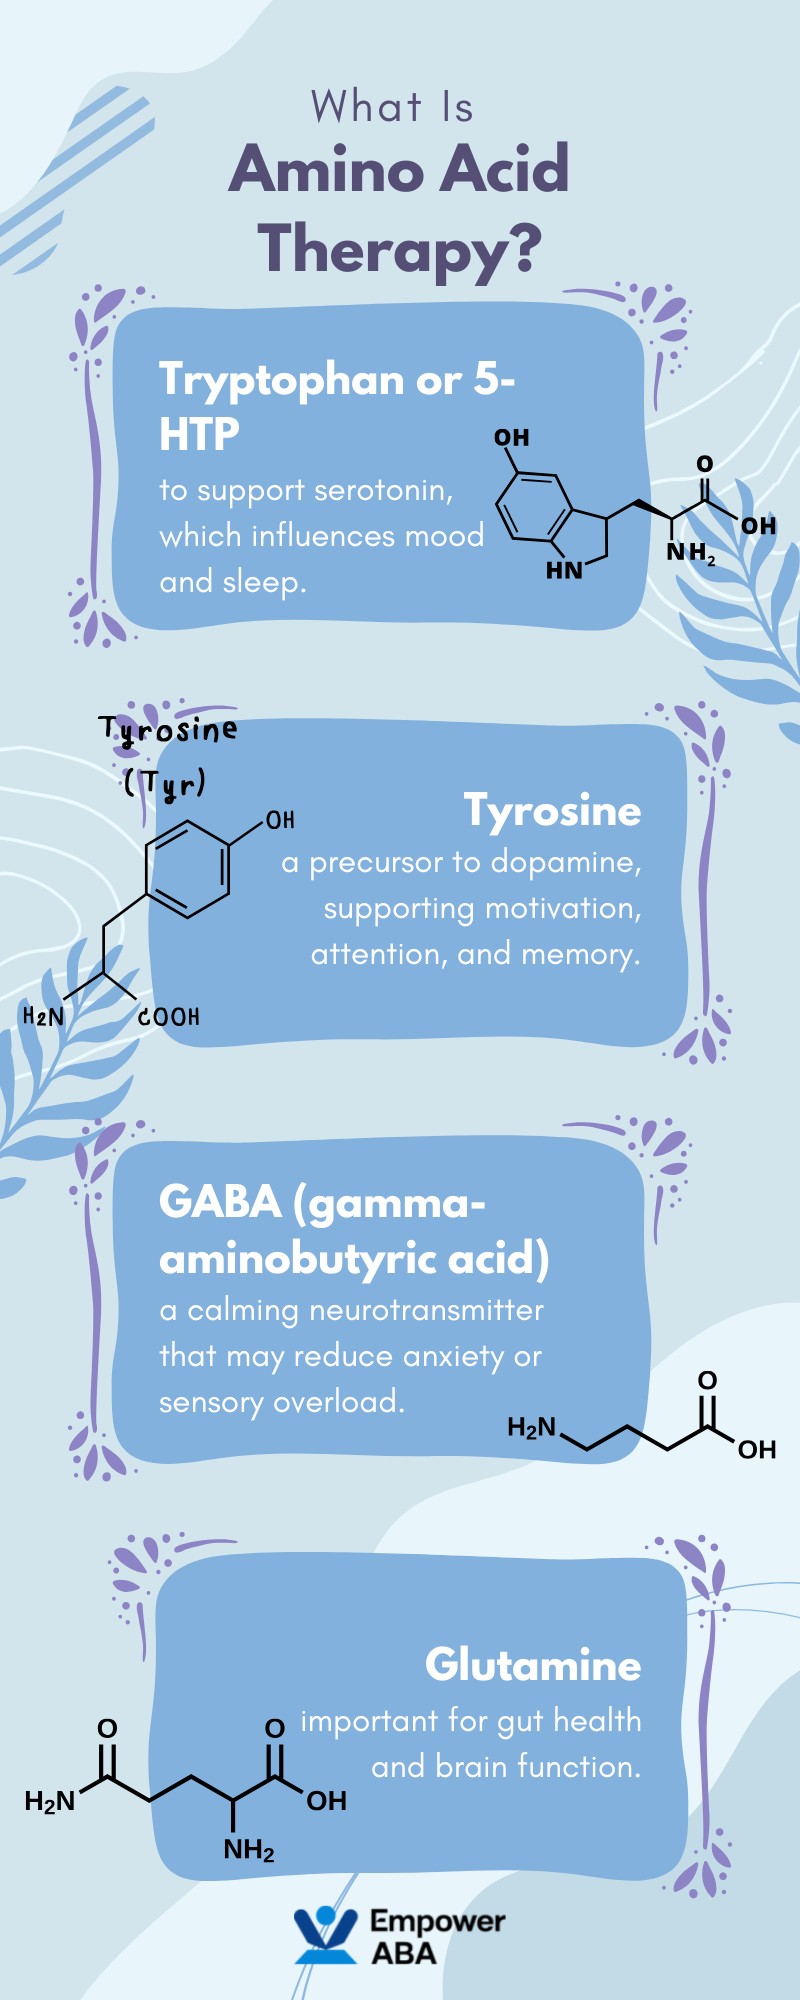
Most people who run into Targeted Amino Acid Therapy are doing it because standard supplementation isn't cutting it. You might be dealing with a metabolic bottleneck, a malabsorption issue, or a neurological symptom that oral broad-spectrum amino acid blends just don't touch. I'll walk through how this actually works in practice, not from a textbook but from having run these protocols and watched them fail when done carelessly. It sounds more clinical than it needs to be. At its core, you are delivering one or more specific amino acids at a defined dose, route, and timing to address a particular physiological gap or enzymatic deficit. This is not the same as drinking a protein shake or taking a multi-amino acid supplement from the health food store. This is precision. You pick the molecule, you calculate the dose based on body weight and the specific condition, and you monitor the response. Common applications include GABA for seizure disorders, L-tyrosine for catecholamine deficiency, NAC for glutathione depletion and mucolytic support, and branched-chain amino acids in hepatic encephalopathy. Each of these has a different pharmacokinetic profile and a different ceiling for effectiveness before side effects dominate.
Setting Up a Protocol From Scratch
Start by identifying the actual deficiency or pathway you are trying to modulate. This is the step most people skip and it is why half the protocols I see online produce zero results. If you are treating a patient with elevated ammonia and suspected hepatic encephalopathy, throwing L-arginine at it without checking their baseline L-citrulline levels and renal function is just guessing. I learned that one the hard way with a case back in 2018. Patient was cirrhotic, we loaded arginine at 20 grams intravenously over four hours, and their creatinine spiked because the liver could not process the nitrogen load properly. Switching to a citrulline-heavy protocol instead resolved the encephalopathy without the renal hit. The takeaway is that the target molecule is not always the best delivery molecule. Once you have your candidate amino acid, you need to establish dosing. Oral bioavailability varies wildly. Tryptophan has reasonable absorption at standard doses but competes heavily with other large neutral amino acids at the blood-brain barrier. If you do not account for that competition by dosing away from protein meals, you are essentially wasting most of the dose. I usually recommend spacing amino acid administration at least two hours from any protein-containing meal or supplement. Route matters. Intravenous delivery bypasses first-pass metabolism and gut breakdown entirely. This is critical for molecules like L-DOPA, which gets extensively metabolized by DOPA decarboxylase in the gut wall before it ever reaches systemic circulation. That is why carbidopa is co-administered in clinical practice. In a targeted therapy context, skipping that protection and giving L-DOPA orally at standard supplement doses almost never produces the neurological effect you are looking for.
Monitoring and Adjusting Targeted Amino Acid Therapy
You need baseline labs before you start anything. Comprehensive metabolic panel, CBC, and whichever biomarker is specific to your target pathway. If you are using NAC for glutathione support, check liver enzymes and consider a fasting glutathione level if your lab can run it. If you are using tyrosine for cognitive or mood reasons, monitor blood pressure and heart rate since catecholamine precursors can push both up in sensitive individuals. Dose adjustments should be incremental. Start at roughly half of what the literature suggests for a given indication and titrate up every five to seven days while tracking your primary biomarker and any adverse symptoms. Most amino acids have a relatively wide therapeutic window but that does not mean more is better. Methionine overload, for example, can increase homocysteine and create cardiovascular risk that outweighs any benefit from the supplement itself. I have seen this happen repeatedly in patients who stacked multiple methionine-containing compounds without checking homocysteine levels. When monitoring, I track subjective changes alongside objective measures. Sleep quality, bowel regularity, and energy patterns often show up before lab values move. These are not foolproof indicators but they are practical early signals that a dose is either insufficient or excessive.
Get the Full Details
Where This Approach Falls Short
Targeted Amino Acid Therapy is not a universal solution. It fails completely when the underlying problem is structural or genetic rather than biochemical. Supplementing glycine will not repair a torn ligament. Boosting arginine will not fix coronary artery stenosis. These are common mismatches I see people attempt and then blame the protocol for. Pure amino acid therapy also struggles when there is a cofactor deficiency present. Vitamin B6 is a cofactor for transamination and decarboxylation reactions involving nearly every amino acid. If a patient is B6 deficient, flooding the system with tryptophan or tyrosine will not work as expected because the downstream enzymes cannot function. I always check a serum pyridoxal 5-phosphate level before launching a protocol that depends on aminotransferase activity. Another limitation is cost and access. Intravenous amino acid formulations require clinical supervision and are expensive. Oral protocols are cheaper but the compliance and absorption issues mentioned earlier make outcomes less predictable. There is no clean middle ground here.
Practical Example: Managing Fatigue in Post-Viral Recovery
One protocol I return to frequently involves acetyl-L-carnitine and L-tyrosine for post-viral fatigue where mitochondrial function appears impaired and catecholamine tone is low. The typical starting dose I use is 500 milligrams of ALCAR twice daily and 500 milligrams of L-tyrosine once each morning on an empty stomach. After five days, if fatigue markers have not improved and there are no side effects, I increase tyrosine to 1000 milligrams and add 250 milligrams of ALCAR to the evening dose. Most patients see a noticeable shift within two weeks. A few do not respond at all, and in those cases I move on rather than escalating further. The one edge case worth mentioning here is patients with a history of hyperthyroidism or Graves disease. Tyrosine is a precursor to thyroid hormones and in those individuals it can tip them into symptomatic thyrotoxicosis. I screen for this before starting and refer anyone with suspicious symptoms to endocrinology rather than adjusting the protocol myself.