Targeted Therapy For Small Cell Lung Cancer: What Actually Works Now
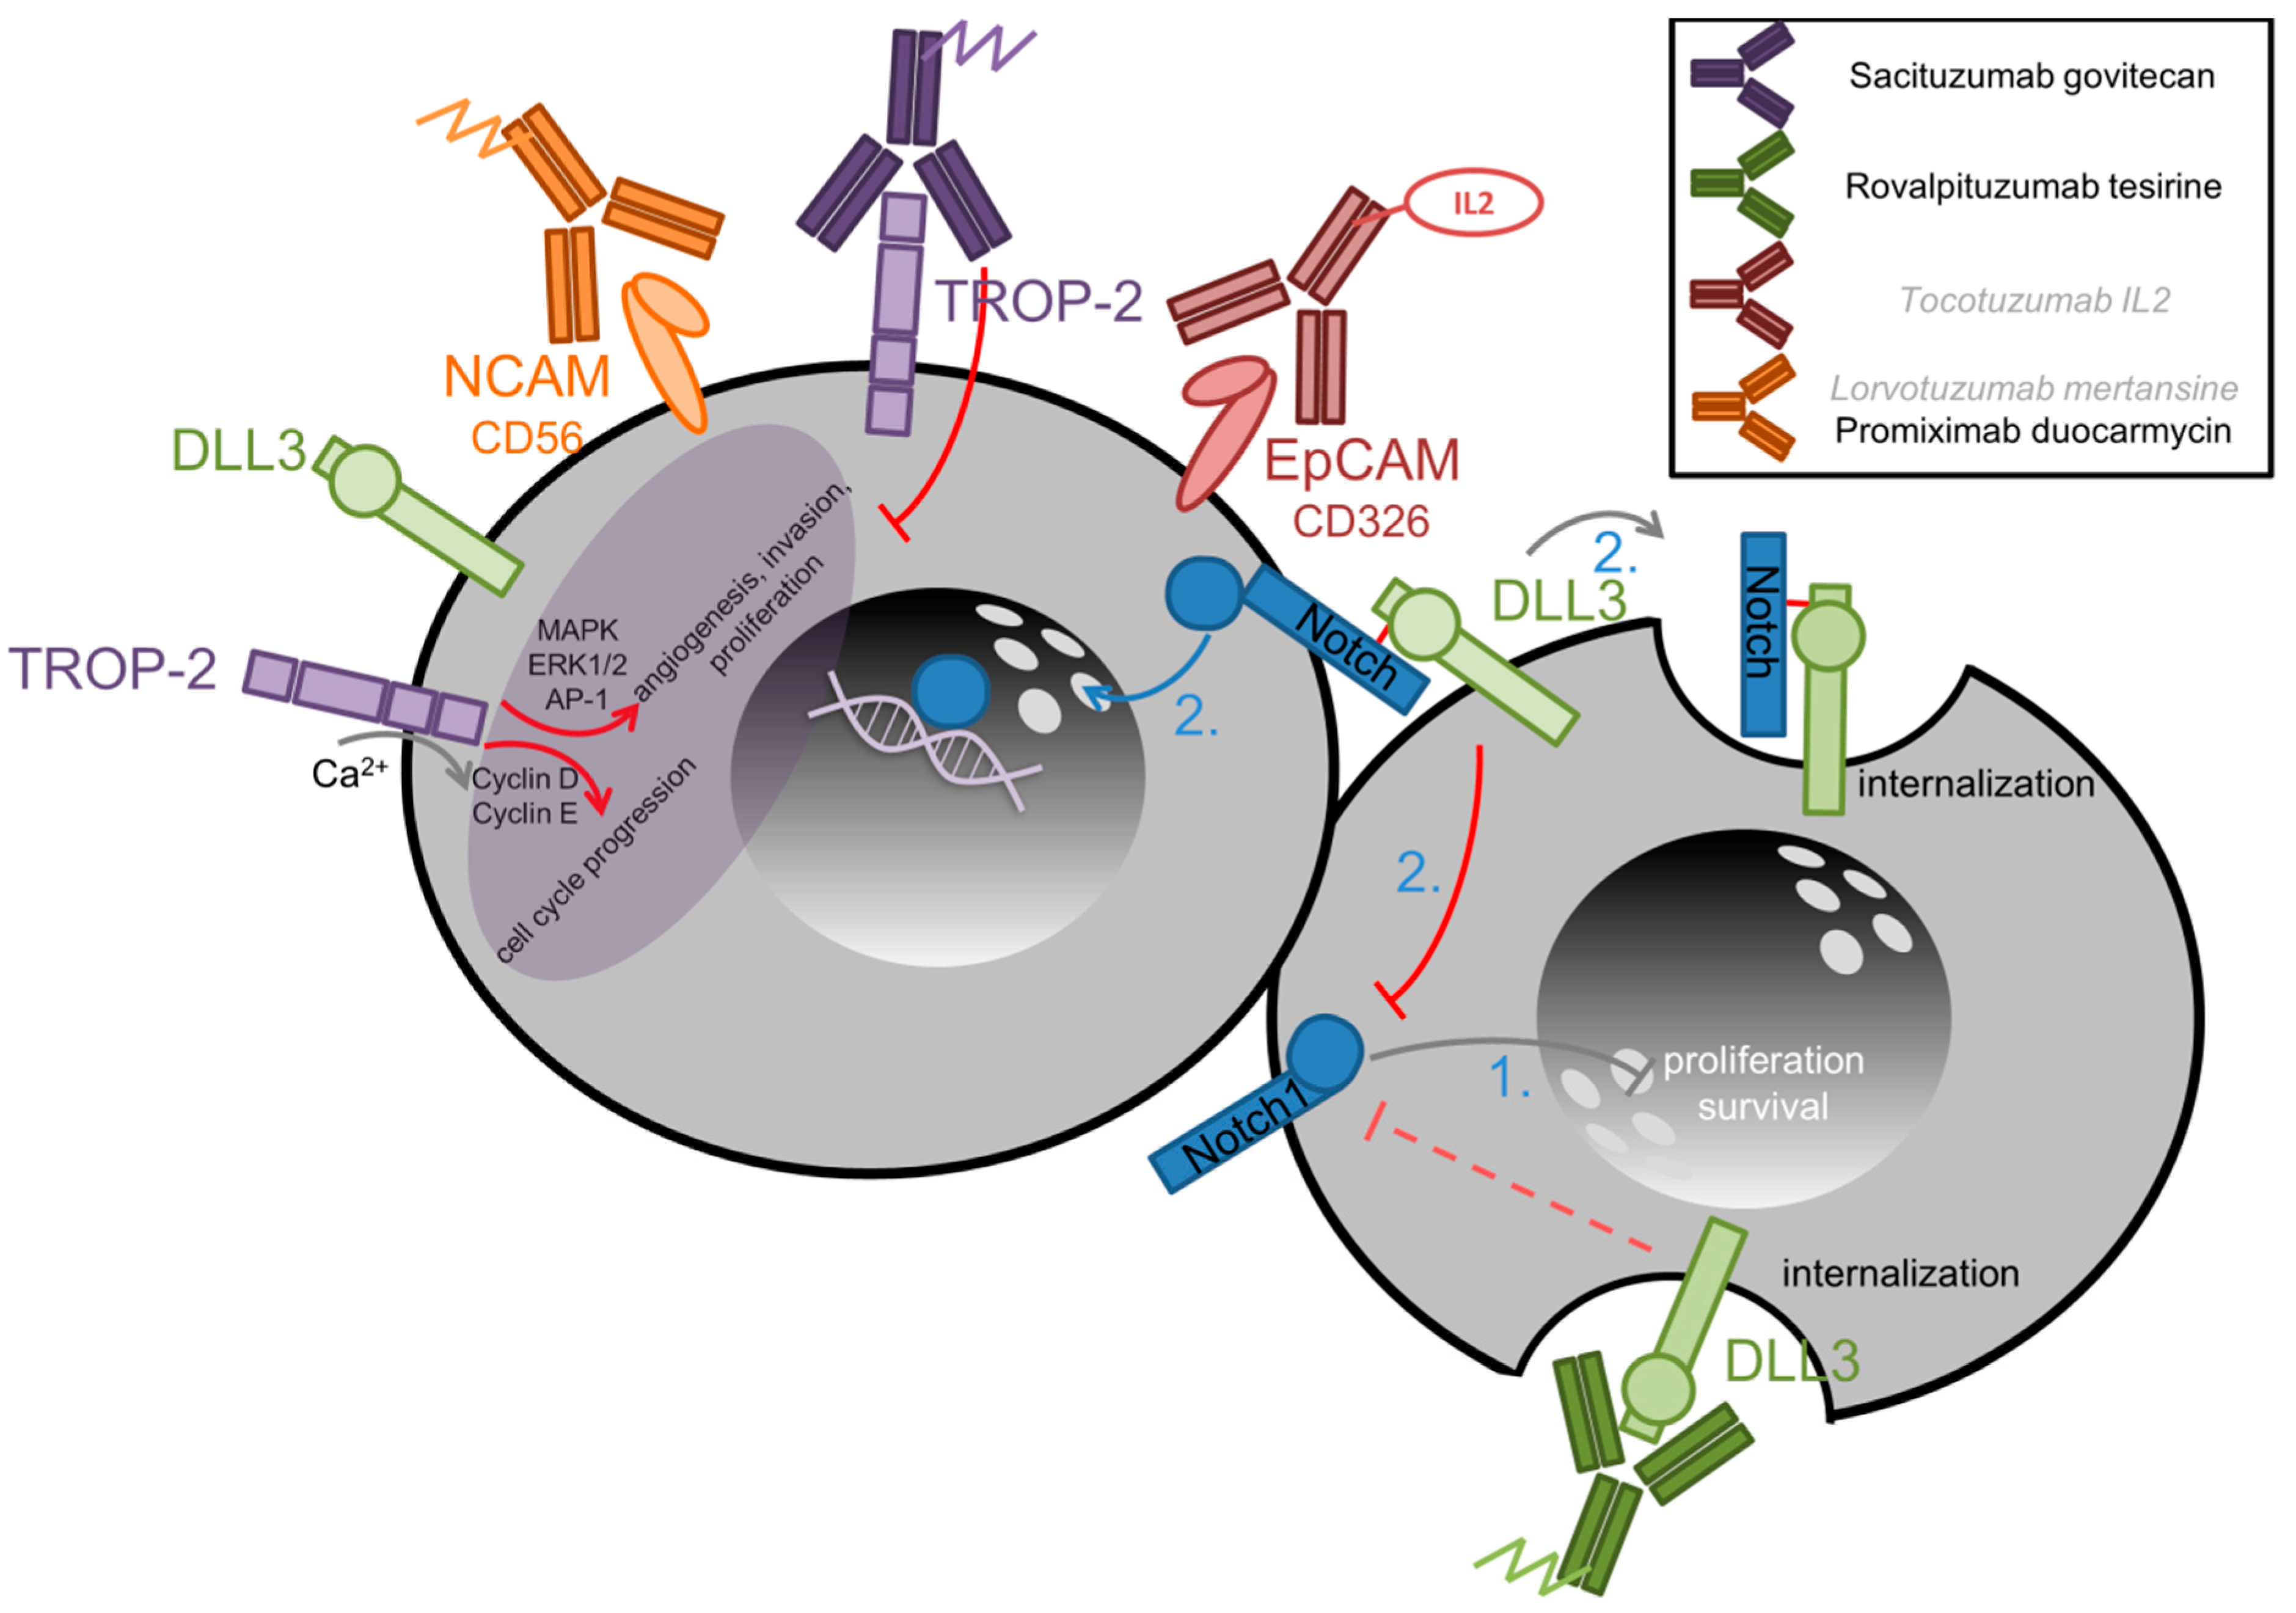
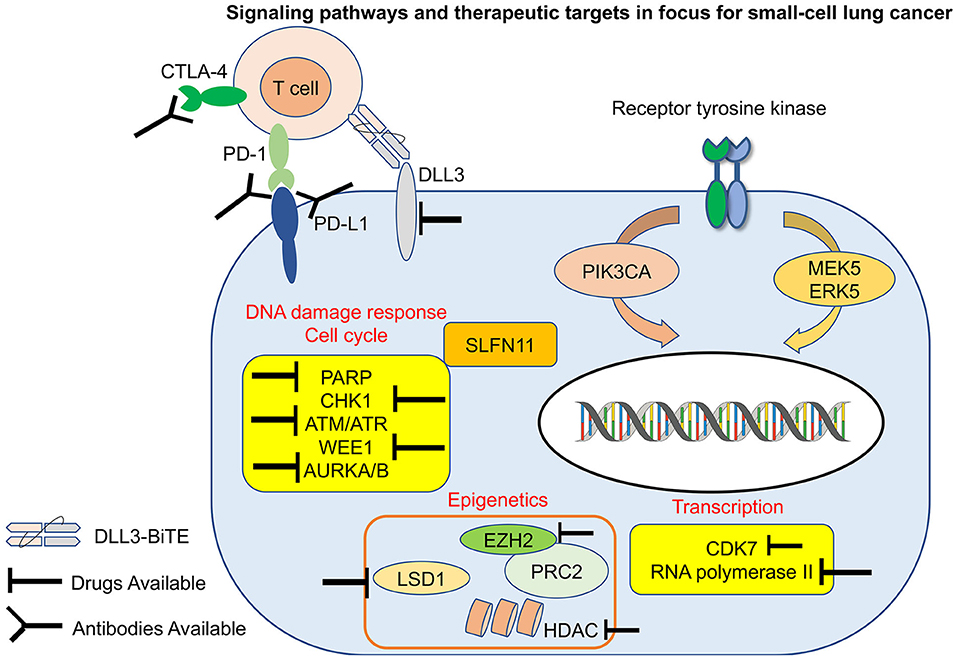
Small cell lung cancer has historically been one of the hardest oncology indications to crack with targeted agents. You spend years learning that the biology simply doesn't cooperate the way it does in non-small cell lung cancer. The classic driver mutations — EGFR, ALK, ROS1 — are essentially absent. What you get instead are TP53 and RB1 loss in nearly every tumor, along with amplifications in MYC family genes and other copy-number alterations that don't lend themselves cleanly to a single inhibitable target. That's why the conversation around Targeted Therapy For Small Cell Lung Cancer has been frustratingly limited for so long. The landscape shifted a bit with the approval of tarlatamab. This is a bispecific T-cell engager that targets DLL3 on the tumor cell and CD3 on T cells. DLL3 expression is found in roughly 80-90% of SCLC tumors, which is unusually high for a surface antigen target. The phase III trial data showed a meaningful overall response rate in patients who had already progressed on platinum-based chemotherapy and a second-line agent like lurbinectedin or topotecan. Not everyone responds, but the ones who do sometimes have durable responses, which was previously rare in this setting.
Targeted Therapy For Small Cell Lung Cancer: Practical Considerations
When I started managing patients on tarlatamab, the biggest practical issue wasn't the drug mechanism itself — it was cytokine release syndrome. Grade 1 and 2 CRS happens in a large majority of patients. Fever, chills, tachycardia, hypotension. The dosing schedule is step-up: week 1 gets a low dose, week 2 a higher dose, and then you're on the full maintenance dose. Each escalation is where you watch the patient most carefully. I've seen patients who tolerated the first cycle fine and then hit significant CRS on the dose escalation in cycle 2. The workaround was straightforward — hold the next dose, give steroids, and restart at a lower level once it resolved rather than pushing through. It's not in every protocol upfront, but it's something you learn from experience. Another issue nobody talks about enough is the timing of immune-related adverse events. With bispecifics like this, you're essentially reprogramming the immune system to attack the tumor, and that immune activation doesn't always stay localized. I had a patient who developed thyroiditis about six weeks into treatment, well after the CRS had resolved. It presented as fatigue and weight changes that were easy to dismiss as cancer progression or just general decline. A basic TSH panel caught it. This isn't unique to SCLC targeted therapy, but the population of patients we're treating is already so fragile that endocrine toxicity can be the difference between a manageable side effect and a serious complication. There's a common misconception that DLL3 positivity alone guarantees response. It doesn't. The level of expression matters, the tumor mutational burden interacts with the microenvironment, and the baseline immune status of the patient all play roles. I've seen DLL3-high tumors that didn't respond and DLL3-medium tumors that did. The assay itself also varies between laboratories — some use different clones, different scoring criteria. If you're relying on a pathology report that says "positive" without knowing the method, you're flying partially blind. I always ask my pathologists which antibody clone they use and what the approximate percentage of positive cells is, not just a binary readout.
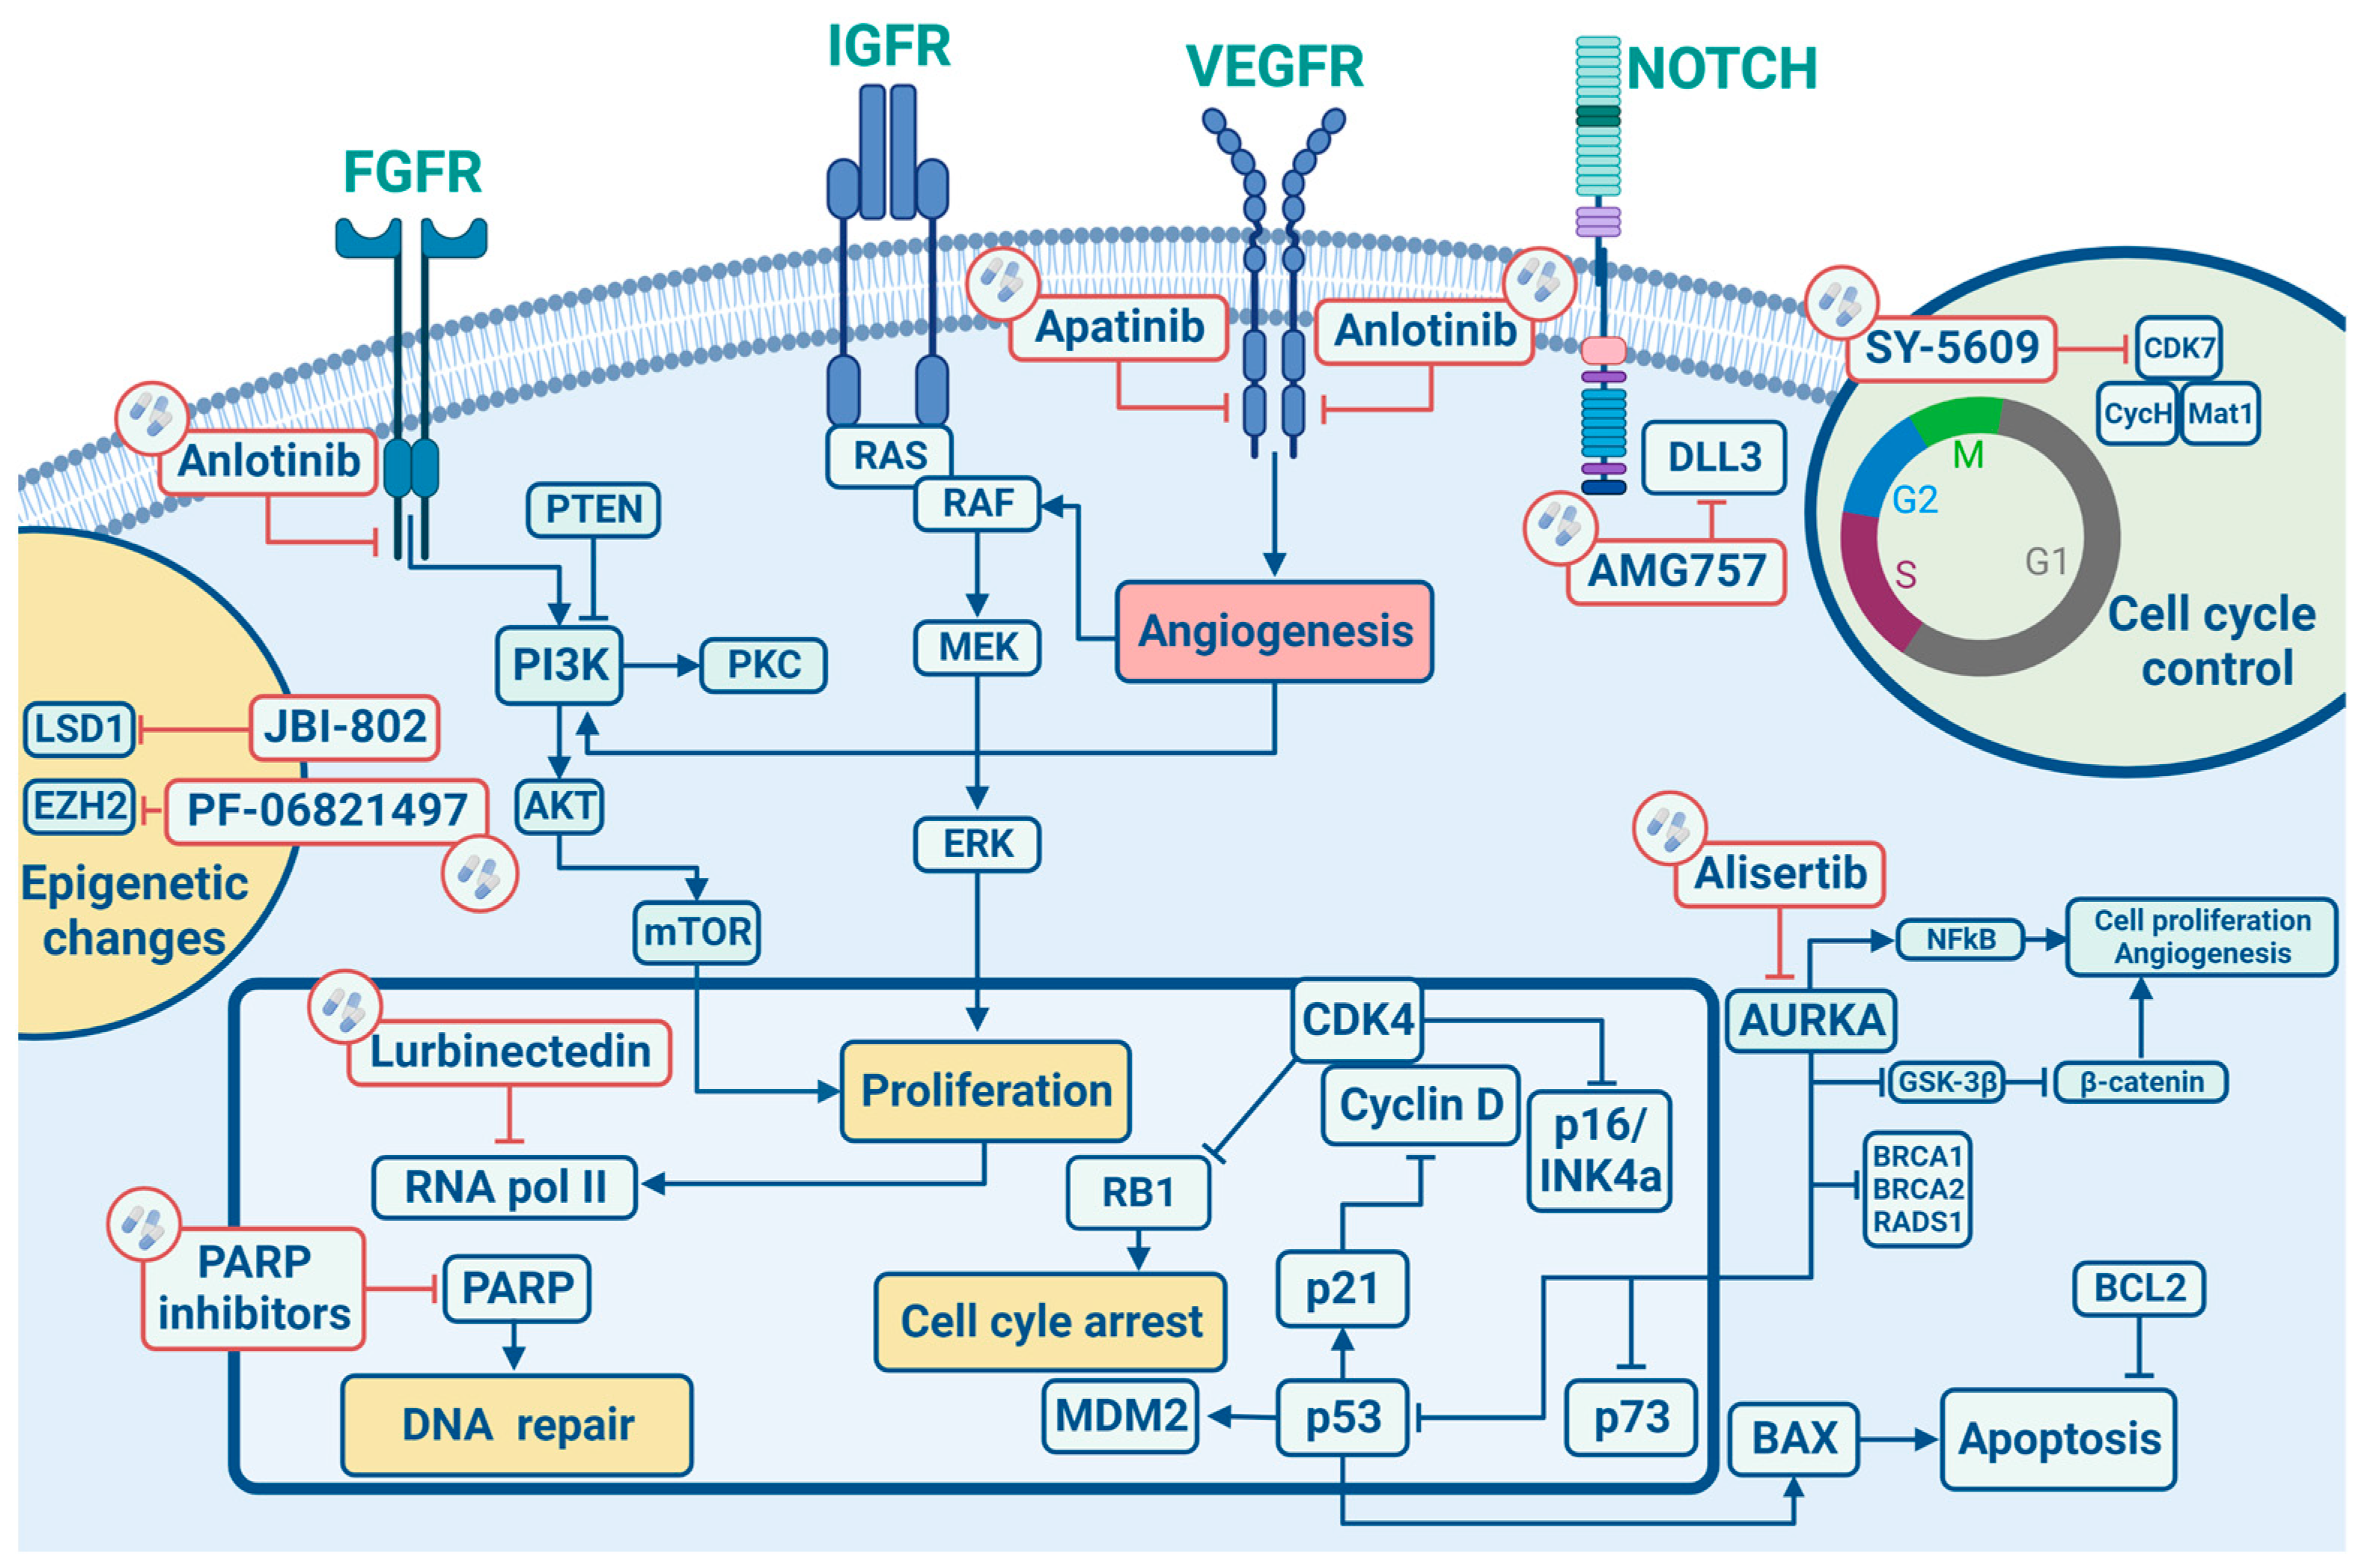
Beyond tarlatamab, there are a handful of other approaches in clinical trials that are worth monitoring. CLDN18.2-directed therapies are showing early signals, though the antigen expression rate in SCLC is lower and more heterogeneous. Nectin-4 antibodies have been tested with modest single-agent activity. The MYC family remains the holy grail that everyone wants to target but nobody has successfully cracked yet. There are some indirect approaches — CDK4/6 inhibitors, BCL-2 inhibitors — that show activity in combination but haven't demonstrated clear benefit as single agents in SCLC specifically. The real limitation of current targeted therapy in SCLC is that most patients still present with extensive-stage disease at diagnosis, and the standard first-line treatment remains platinum-etoposide plus a PD-L1 inhibitor. The targeted agents we have now are largely positioned in the relapsed setting. That's both a strength and a weakness — the data is strongest in heavily pretreated patients, which means the responses we're seeing are in people whose disease has already proven resistant to multiple mechanisms. The question that keeps coming up is whether these agents would work better earlier in the treatment sequence, and that's an active area of investigation. For anyone navigating this, the practical takeaway is that the field has moved from nothing to something tangible, but "something" is still limited. DLL3-directed therapy is the only approved targeted option right now, and it's reserved for relapsed disease after at least two lines of chemotherapy. The cytokine management is learnable but requires vigilance. Response rates are real but not universal. And the broader pipeline hasn't quite delivered the next breakthrough yet. If you're considering this for a patient, the discussion should center on DLL3 testing, CRS risk mitigation, and realistic expectations about what a response looks like in this population.
Get the Full Details