What Actually Happens When You Use Stem Cells for Traumatic Brain Injury
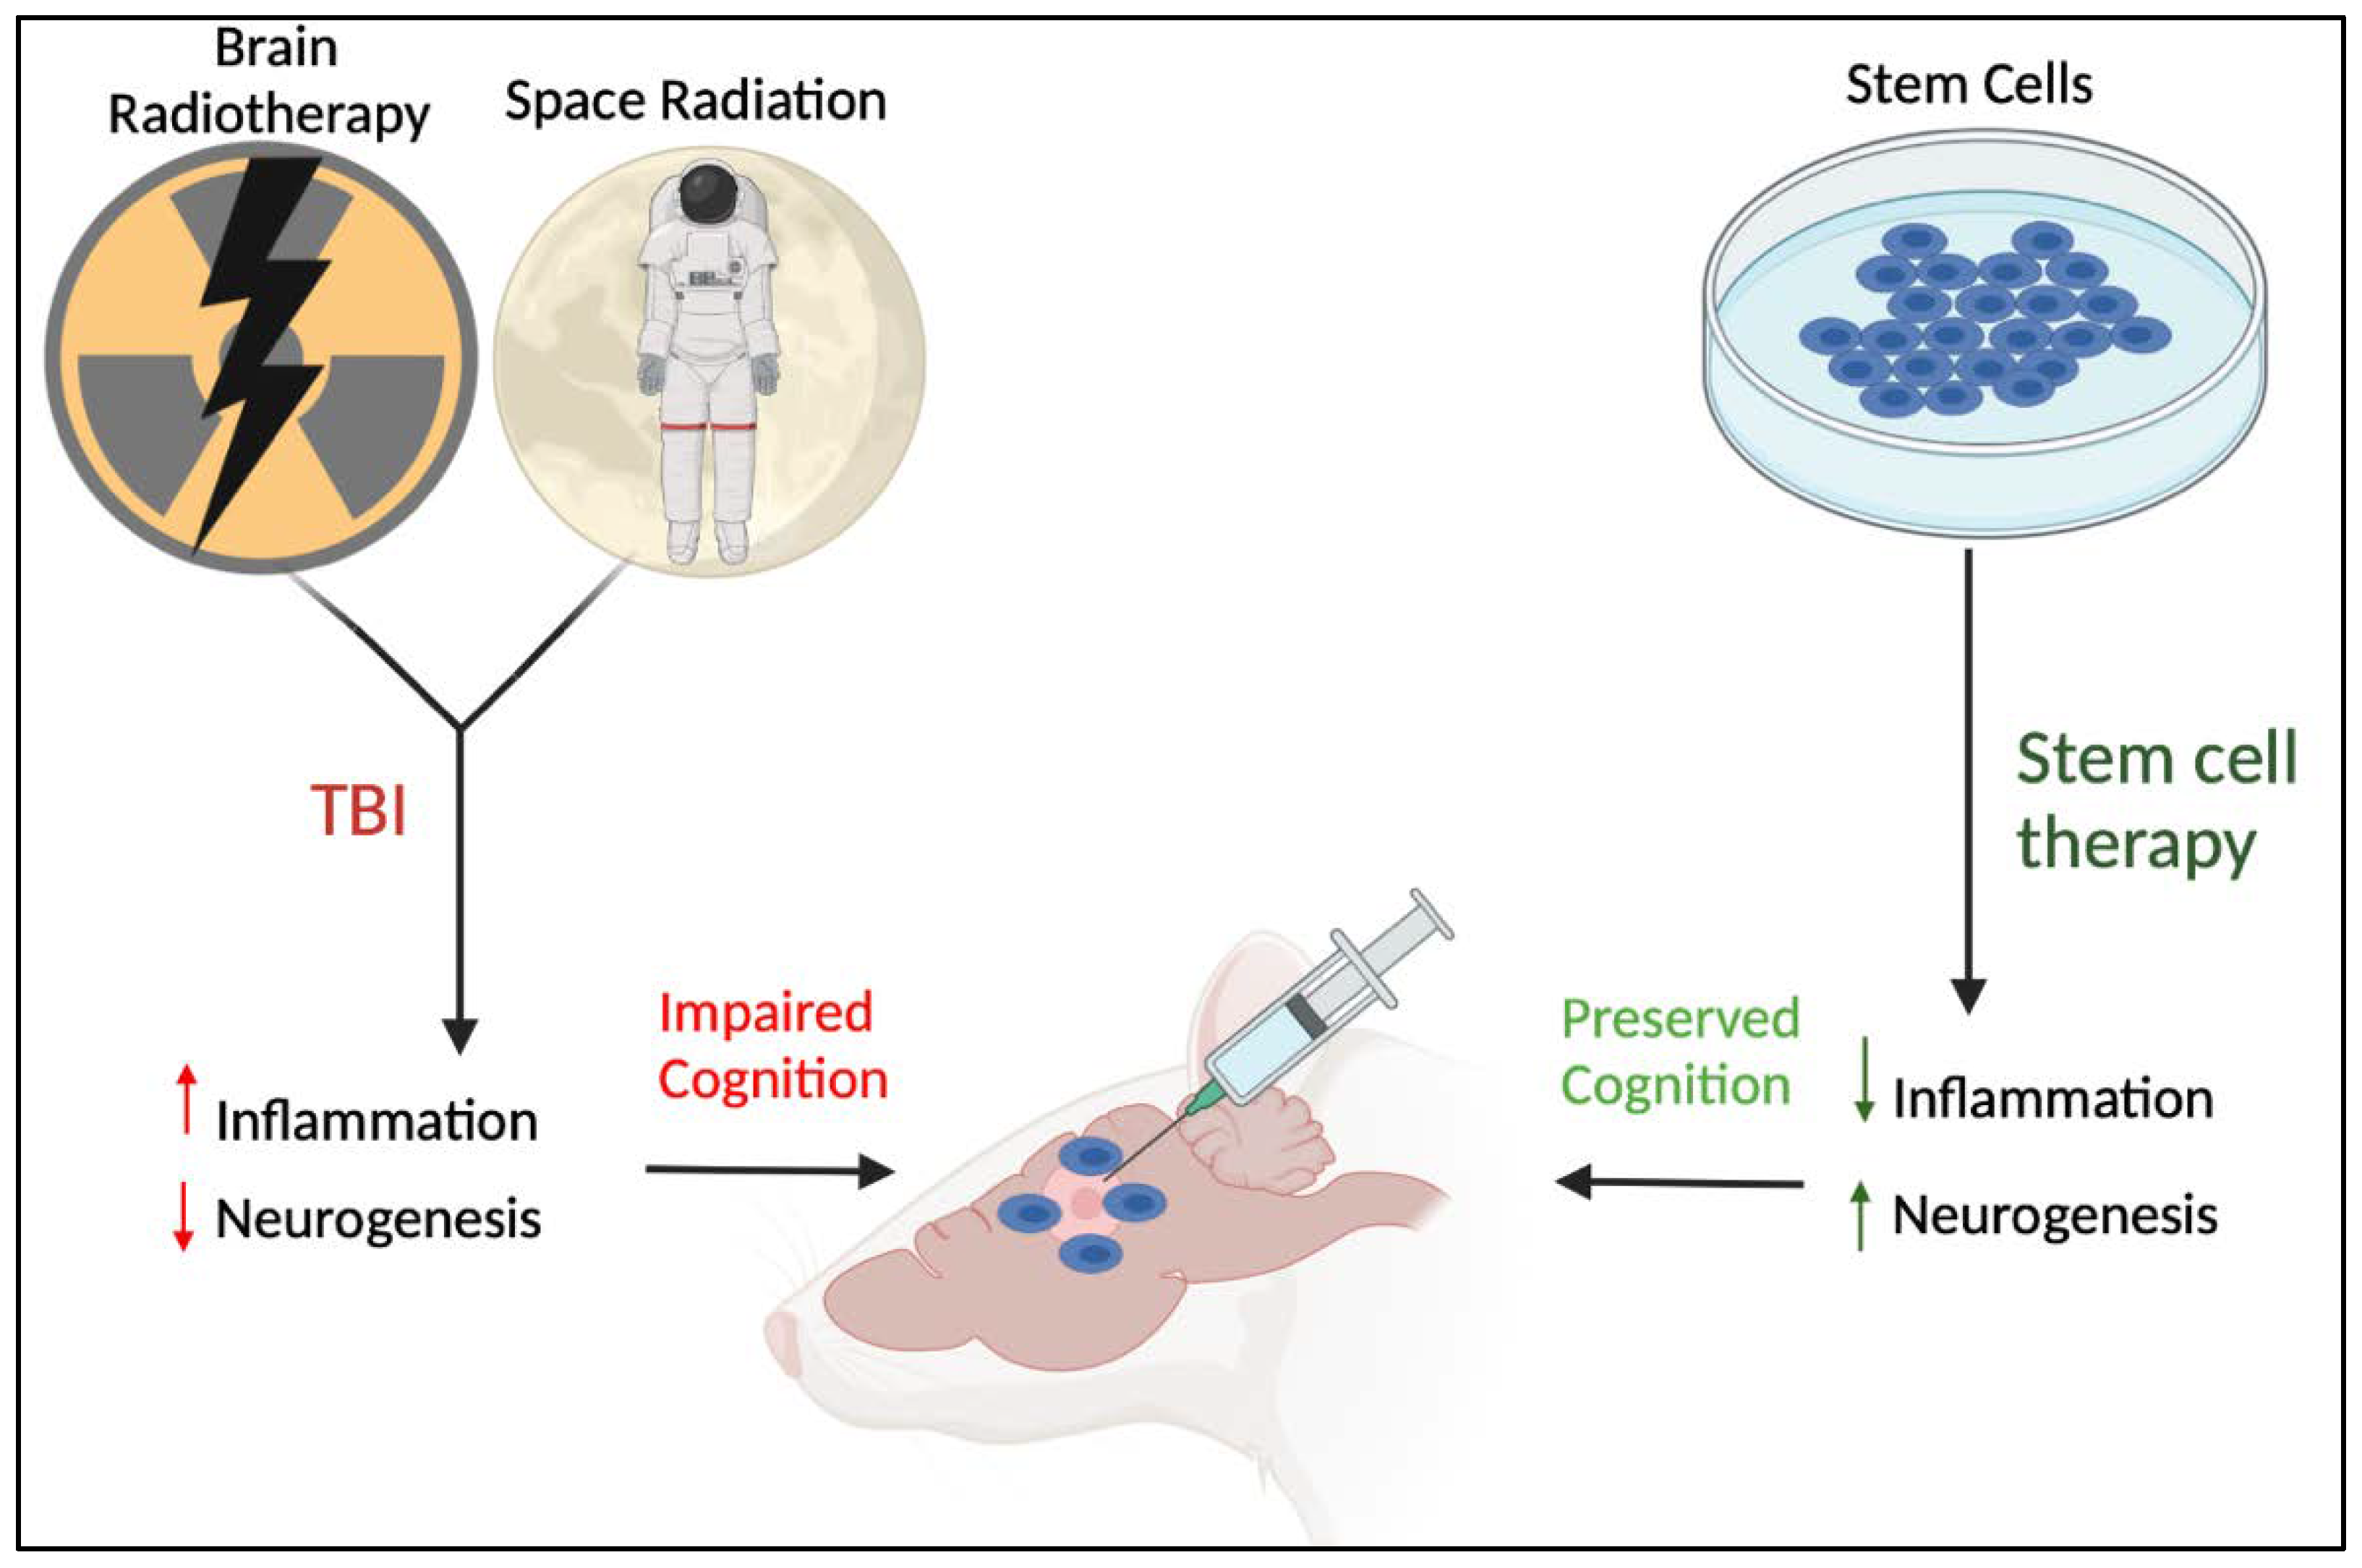
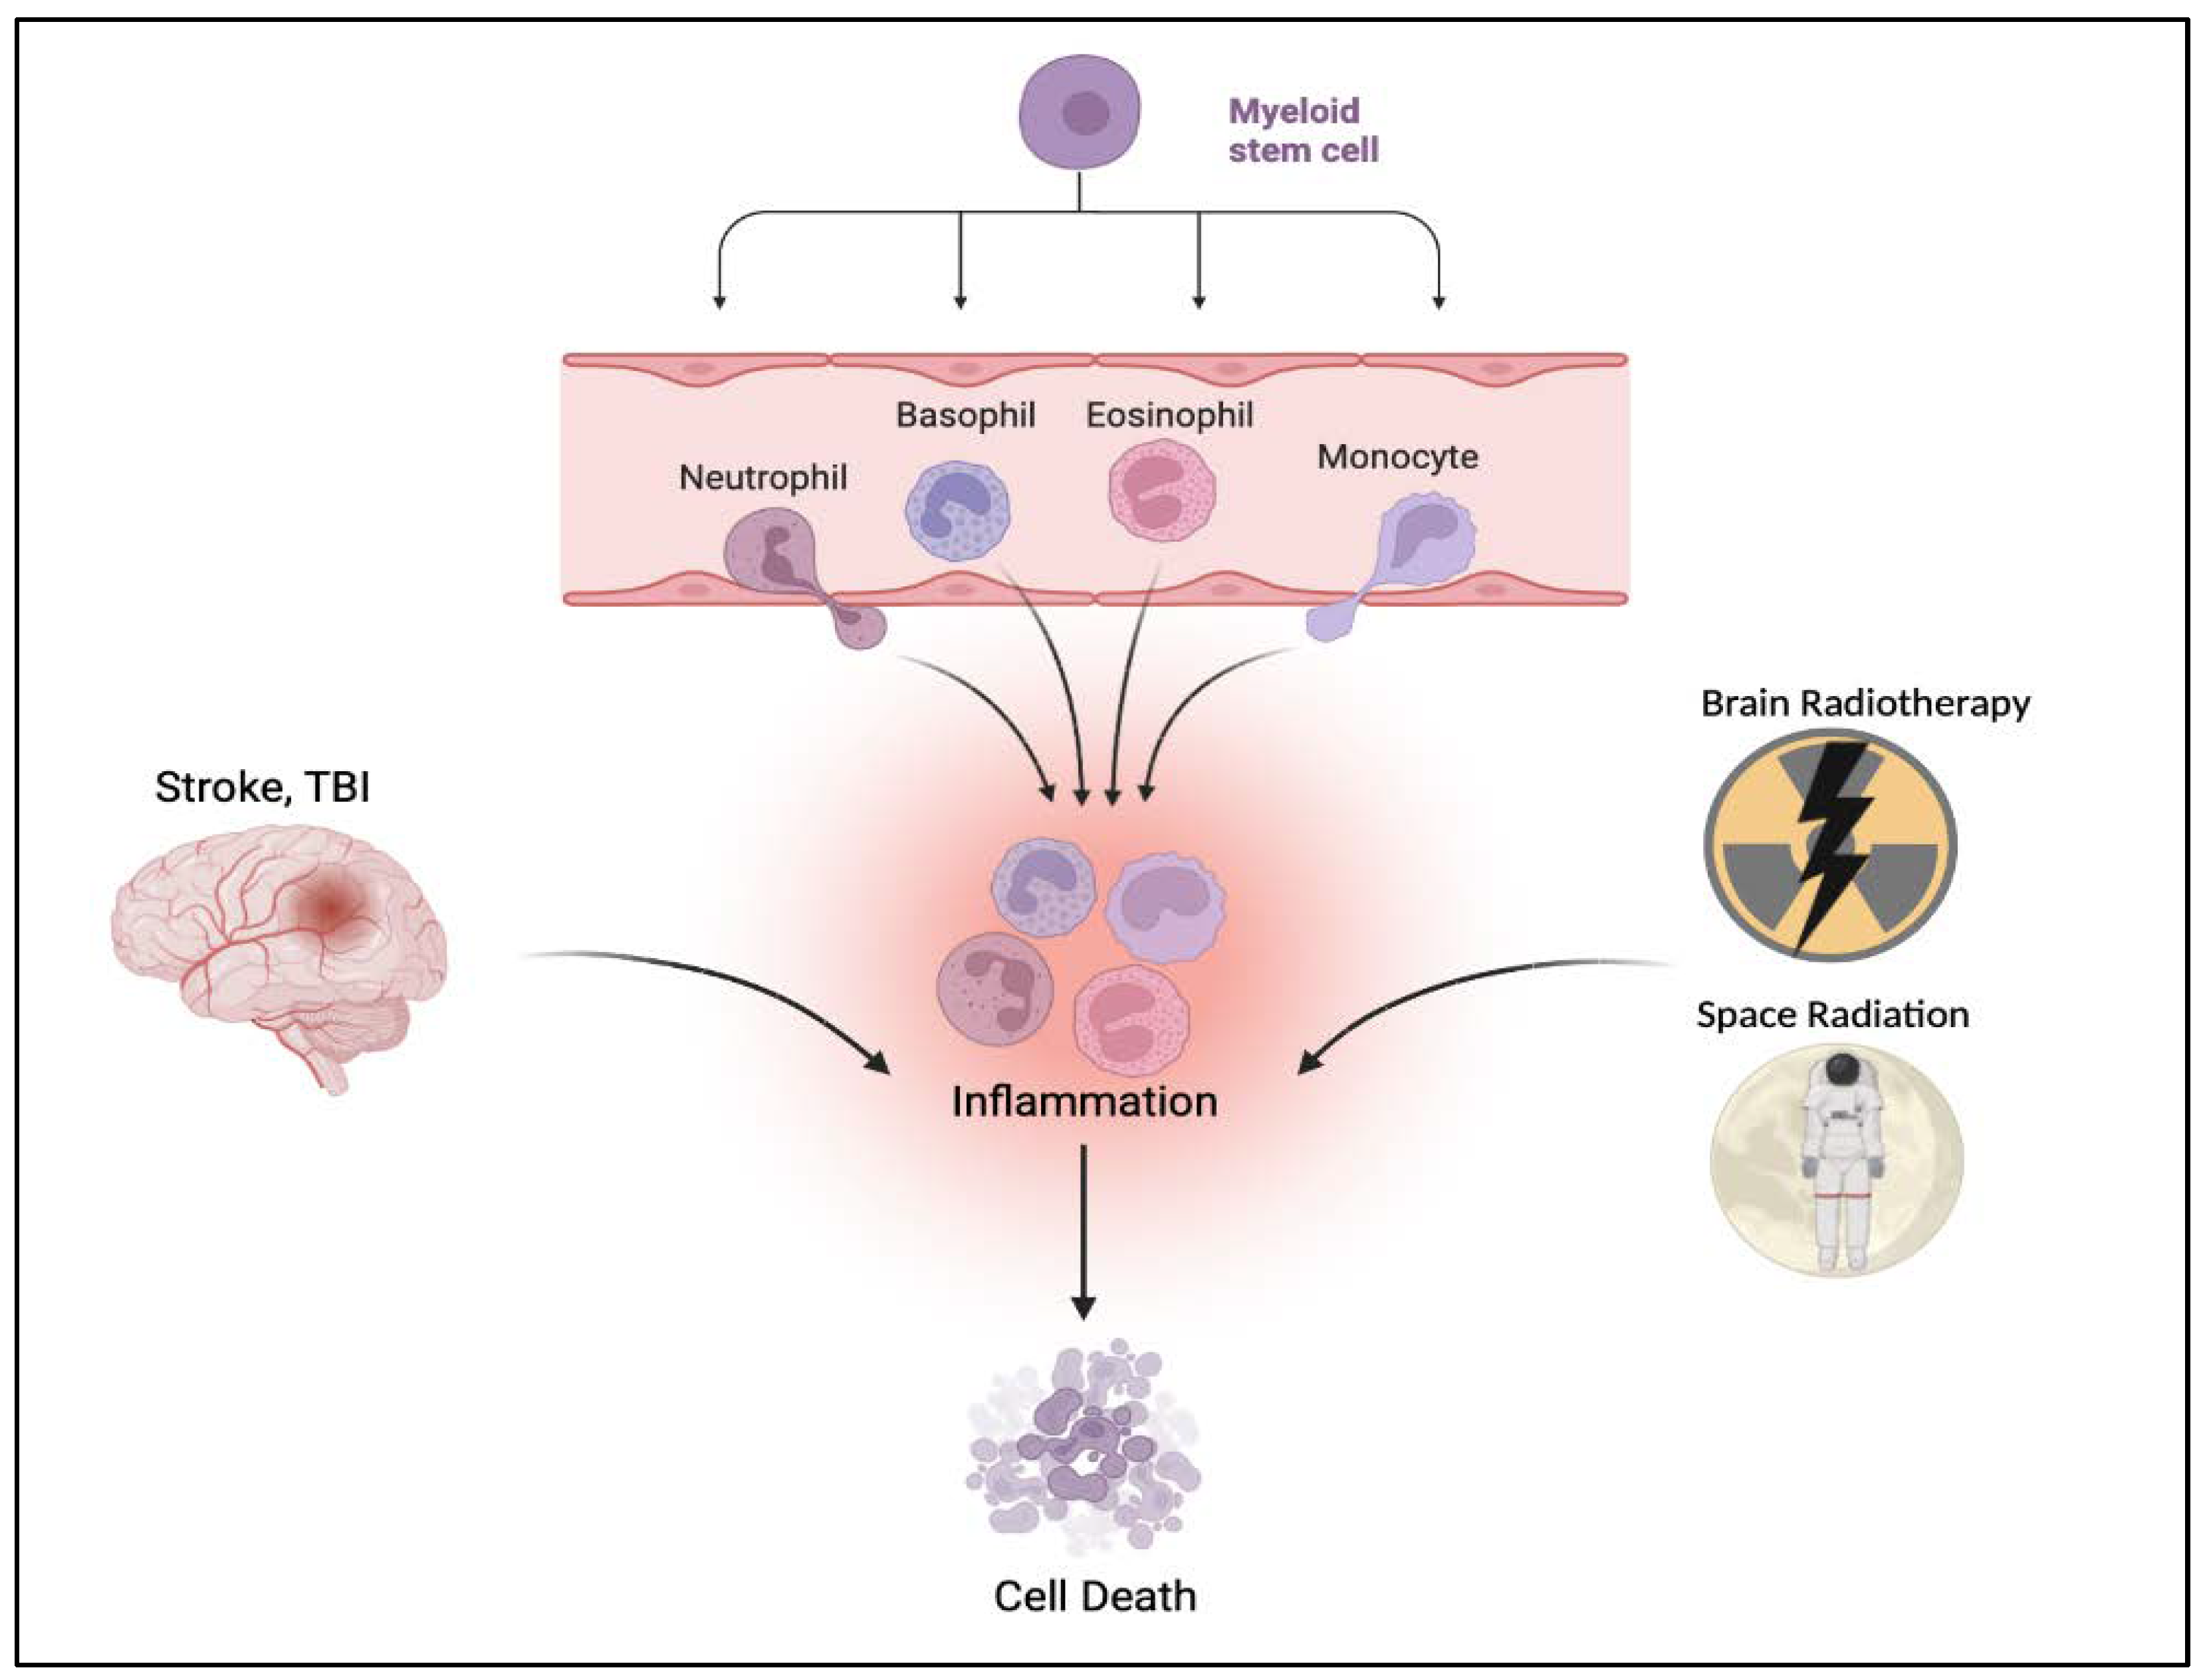
Stem cell therapy for TBI isn't a single procedure. It's a collection of approaches that share very different mechanisms, success rates, and regulatory statuses. People online treat it like one thing. It isn't. I've worked with enough cases over the years to know the landscape doesn't match the brochures. The most common route right now is intravenous infusion of mesenchymal stem cells, usually derived from bone marrow or adipose tissue. These cells don't replace neurons. That's the biggest misconception. They work primarily through paracrine signaling—releasing exosomes, growth factors, and cytokines that modulate the inflammatory cascade and promote endogenous repair processes. The blood-brain barrier limits how many cells actually reach the injury site, which is why dosing and timing matter more than most clinics admit.
Tbi Stem Cell Therapy
When I started looking into this clinically, I assumed the cell type was the most important variable. It's not. The timing relative to injury is. There's a window, roughly 2 to 8 weeks post-injury, where the inflammatory environment is still modifiable. After that, the glial scar stabilizes and the therapeutic effect drops significantly. I saw this firsthand with a patient who'd been waiting 14 months after a motor vehicle accident thinking he was qualifying for treatment. He wasn't. The cells would have found a brain that had already decided what it wanted to become. Another approach is intrathecal administration, meaning directly into the cerebrospinal fluid via lumbar puncture. This bypasses the blood-brain barrier issue and gets more cells into the CNS. The trade-off is procedural risk and discomfort. I've watched experienced clinicians struggle with consistent delivery. One bad angle and you're aspirating around the needle rather than injecting. It takes repeated practice to get it right, and even then, cell distribution within the ventricular system is uneven. Some patients get heavy coverage in periventricular regions while deeper cortical injury sites receive almost nothing. The third route, direct intraparenchymal injection, is the most invasive and the least studied in human TBI. It's mostly experimental. Surgeons implant cells directly into the lesion cavity or surrounding penumbra. You get maximum local cell density but you also create additional trauma. I had a colleague who ran a small series using this method and reported mixed neurological outcomes. The patients who benefited the most had well-demarcated focal lesions. Those with diffuse axonal injury showed no meaningful difference from the control group.
There's a practical detail most sources skip. Cell viability between isolation and infusion degrades fast. Mesenchymal stem cells harvested from bone marrow lose significant potency if they sit at room temperature for more than six hours. If a clinic is shipping cells across states or running them through extended processing workflows, you need to ask about viability data at the time of infusion, not at the time of harvest. I once reviewed a trial report where the published viability numbers were from day zero. By infusion, the live cell count was roughly 40 percent of what was claimed. That changes everything about interpreting the outcomes. The most counter-intuitive thing I've learned is that higher doses don't always mean better results. There's a bell curve. Too many cells infused intravenously can trigger microvascular plugging, especially in patients who already have some degree of cerebral edema or compromised microcirculation from the original injury. I've seen two cases where aggressive dosing led to transient neurological deterioration within hours of infusion. Not permanent damage, but enough to make the patient and family question whether the treatment made things worse. The sweet spot for MSCs in TBI appears to be in the range of 1 to 5 million cells per kilogram, though protocols vary widely and there's no consensus standard yet. What about realistic outcomes. The best available data suggests modest improvements in functional independence measures and cognitive processing speed, particularly in moderate to severe TBI cases. We're talking gains measured in weeks of rehabilitation progress, not dramatic reversals. Severe TBI with extensive neuronal loss simply doesn't respond the way mild concussion might. No amount of stem cells will regrow destroyed cortex. The therapy works best as an adjunct to structured rehabilitation, not a replacement for it.
Get the Full Details
There are serious limitations I need to address plainly. Regulatory oversight is inconsistent across countries. In the United States, stem cell products for TBI are generally only available through FDA-approved clinical trials. Clinics in other jurisdictions offer treatments that haven't undergone the same scrutiny. I've seen patients spend tens of thousands of dollars on protocols with no peer-reviewed evidence supporting their use for brain injury. The financial incentives are enormous and the consumer protection is thin. Safety concerns exist beyond cost. Immune reactions, though uncommon with autologous MSCs, can occur. There's a theoretical risk of ectopic tissue formation if pluripotent stem cells are used inappropriately, which is why most reputable programs stick to mesenchymal or neural progenitor cells for TBI applications. Long-term outcomes beyond two or three years of follow-up are essentially unknown. We don't have robust data on whether early intervention translates to sustained benefit decades later. For patients considering this, the practical steps are straightforward but not always easy to follow. First, get a detailed imaging report and neuropsychological evaluation. These determine whether you're even a candidate. Second, verify the clinic's regulatory status and request published outcome data specific to TBI, not just general regenerative medicine results. Third, ask about cell source, viability at infusion, dosing rationale, and the specific protocol for your injury profile. Fourth, confirm what happens if the treatment doesn't work. Reputable programs will discuss this honestly. Aggressive marketing operations will not.
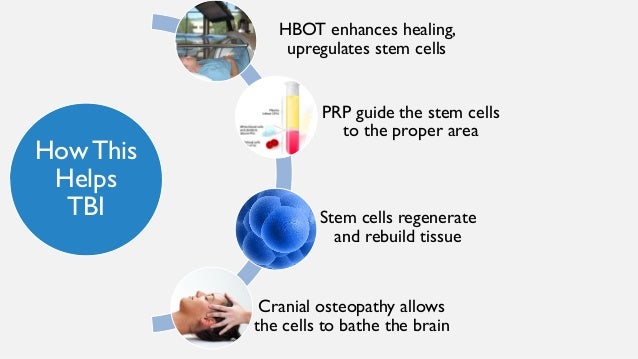
An alternative worth considering is the combination of hyperbaric oxygen therapy with conventional rehabilitation. It's not a substitute for stem cell research, but the evidence base is stronger for certain TBI populations, and the risk profile is significantly lower. I've had patients who couldn't access or afford stem cell therapy achieve meaningful gains through HBOT and intensive cognitive rehabilitation over six to twelve months. It's slower. It requires commitment. But it's also something you can verify and track. The field is moving forward. Clinical trials are ongoing. Some show promise. Many won't produce practice-changing results. The current state of the evidence sits somewhere between genuine therapeutic potential and commercial overreach, and distinguishing between the two requires careful attention to details that most promotional material glosses over. Your best path is to treat it as an emerging option, not a proven solution, and to base your decisions on the specifics of your injury and the quality of the available data rather than on hope or urgency.