When the Image Doesn't Cooperate
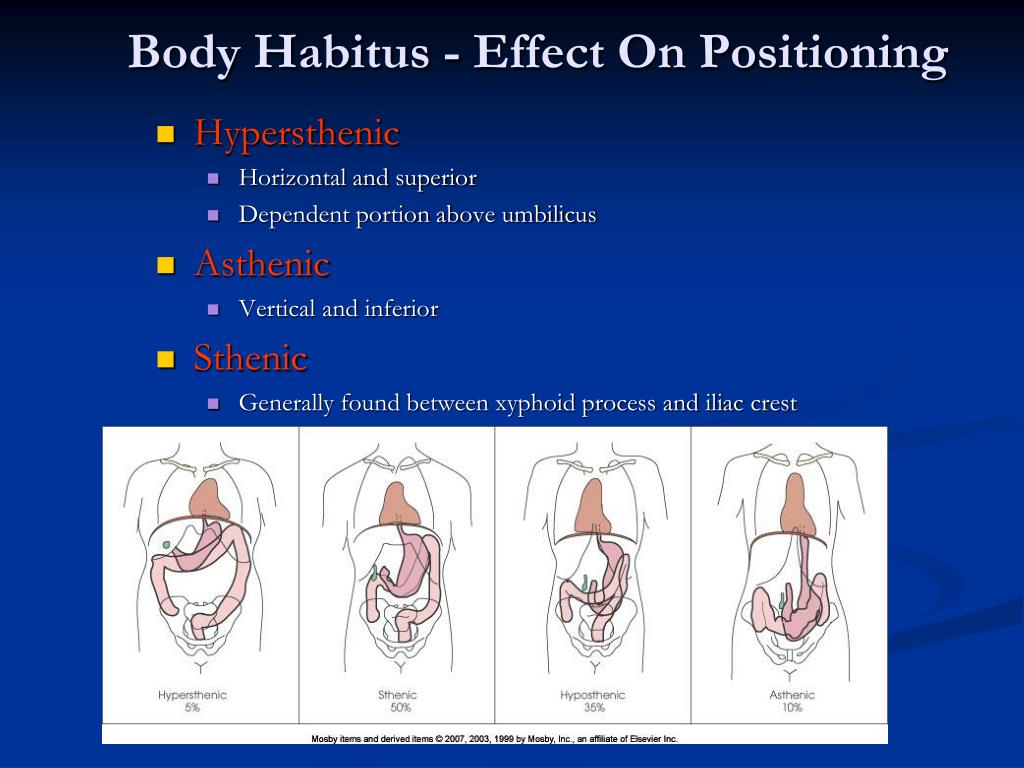
Body habitus matters more than most techs admit. I've been running protocols long enough to know that two patients with the same complaint can produce completely unusable exams if you don't adjust before you even think about hitting start. The term Technically Difficult Exam Due To Body Habitus shows up on reports all the time, but most people reading it don't realize what's actually happening under the gantry. Body habitus refers to the physical constitution of a patient - things like body mass index, adipose tissue distribution, muscle mass, and skeletal structure. When we flag an exam as technically difficult due to body habitus, we're saying the patient's physical characteristics prevented standard acquisition parameters from producing diagnostic-quality images. This isn't about making excuses. It's documentation that the exam had limitations and radiologists need to know how much they can trust what they're seeing. In CT imaging specifically, adipose tissue attenuates X-rays differently than soft tissue or bone. A standard liver protocol calibrated for a 70-kilogram patient will underpenetrate a 130-kilogram patient, producing noisy images where small hypodense lesions disappear into the grain. The opposite problem exists too - an underweight patient with minimal soft tissue can be over-penetrated with the same settings, washing out contrast between structures that should be clearly differentiated.
I ran into a case last year where a patient with severe kyphoscoliosis and a BMI over 42 was referred for a routine abdominal CT. Standard positioning was impossible. The curvature meant that no matter how I padded or positioned, the spine and surrounding musculature were creating beam-hardening artifacts across the entire field of view. The initial protocol produced images where I couldn't distinguish the pancreas from the surrounding retroperitoneal fat. I switched to a low-kVp protocol with iterative reconstruction, which cut the noise significantly, and then acquired the study in a prone position rather than supine. That shifted the abdominal contents away from the curved spine and cleared up about 60 percent of the artifact. The final images weren't perfect, but they were diagnostic. The radiologist noted the technical difficulty in the report and qualified his findings accordingly.
The Practical Side of Acquisition
Let's talk about what actually changes when body habitus becomes a factor. Tube current modulation is the first tool in the kit. Instead of a fixed mA, the system adjusts output based on real-time attenuation measurements. For a larger patient, this can mean the system ramps up to 400 or even 500 mA during the phases where anatomical density is highest. The trade-off is radiation dose, which climbs proportionally. You're not going to get a low-dose exam on a large patient, and that needs to be documented. Kilovoltage selection matters just as much. Dropping from 120 kVp to 100 kVp increases contrast between soft tissue structures, which helps when you're dealing with thick adipose layers that tend to compress tissue planes together. But lower kVp also means more photon starvation in dense regions. Modern scanners with photon-counting detectors handle this better than older systems, but if you're working with equipment that's more than five years old, the image quality improvement from lower kVp might not materialize the way it should. Padding and positioning are simpler tools that people overlook. A leg cushion that raises the knees slightly reduces lumbar lordosis and flattens the spine against the table, which can make a meaningful difference for lumbar imaging. Foam wedges behind the torso help maintain neutral positioning in patients who can't hold still or whose body shape makes standard alignment impossible. These adjustments take about two minutes but can determine whether you need to repeat an entire phase of contrast acquisition.
Get the Full Details

Collimation and field of view selection also play a role. Scanning a larger area with wider collimation spreads the X-ray beam more thinly across the patient's cross-section. Some facilities use overlapping table increments or double-loop acquisitions for large patients to ensure complete coverage without gaps, but this doubles scan time and increases dose. I've found that in practice, it's usually better to accept a slightly narrower field of view and focus on the region of clinical interest rather than trying to capture everything in one pass.
Documentation and Communication
Flagging an exam as technically difficult isn't just bureaucratic paperwork. It directly affects how the interpreting radiologist approaches the study. When I see that notation on a report, I know immediately that certain findings may be limited or that subtle abnormalities could have been missed. It changes my confidence level in a negative study, which matters for follow-up decisions. The specific details matter more than a generic label. "Technically difficult due to body habitus" tells the radiologist that something was wrong but not what. Better documentation would specify what was difficult and what was done about it. I typically note the patient's approximate weight range, what positioning modifications were used, whether iterative reconstruction was applied, and which phases were compromised. This gives the reader enough context to weigh the findings appropriately without needing to call back for clarification. There's a balance to strike here. Over-documenting can clutter the report and make it harder for the radiologist to find the clinically relevant information. Under-documenting leaves them guessing. I've learned to keep it to two or three sentences maximum, focusing on the acquisition modifications and the specific areas where image quality was compromised.
When Technology Has Limits
Here's the part that doesn't get discussed enough: no amount of protocol tweaking will make a truly non-diagnostic exam diagnostic. I've had patients where even after switching to the lowest available kVp, applying iterative reconstruction at the highest strength setting, and repositioning three separate times, the images remained so noisy that I couldn't confidently rule out a small lesion. In those cases, the honest answer is that the CT exam was non-diagnostic for the intended purpose, and the patient needs an alternative imaging modality. MRI is often the next step for larger patients, but it has its own habitus limitations. The bore size of most clinical scanners tops out at 70 centimeters, and patients above approximately 180 kilograms simply won't fit. Even when they do fit, the increased adipose tissue can affect RF coil coupling and produce artifact that degrades image quality. Ultrasound is another option, though operator dependence and acoustic shadowing from bowel gas or bone make it unreliable for certain studies. I've seen multiple patients go back and forth between modalities over weeks because each one hit a different body habitus wall. Dose is another hard constraint. There's a point where increasing tube current to compensate for patient size produces images that are diagnostically acceptable but deliver radiation doses that approach or exceed regulatory thresholds for certain protocols. Some facilities have hard limits at 500 mAs per rotation. Beyond that, the system simply won't operate, and you're left with noisy images or no image at all. I've had to document when a scan couldn't be completed because the required parameters exceeded the scanner's output capabilities.

What Beginners Miss
The most common mistake I see from technologists new to this is adjusting parameters after the first scan rather than anticipating the need. You'll get the localizer, see the patient's build, and then realize you need to change kVp or switching to a different reconstruction kernel. By then, you've already wasted contrast timing and potentially missed the optimal phase for enhancement. The fix is to evaluate the patient's habitus before the scout and set your protocol accordingly. It takes an extra thirty seconds and prevents a lot of headaches. Another pitfall is relying solely on automatic exposure control without monitoring the output. AEC systems are good at their job, but they can be fooled. Dense muscle mass in the shoulders might cause the system to ramp up mA for the entire study, even though the diagnostic target is the abdomen where less penetration is needed. I've learned to watch the real-time exposure indices and intervene manually when the system seems to be overcompensating in one region while underpenetrating in another. There's also the human factor that gets ignored. Larger patients often have mobility limitations that make positioning harder. Hip osteoarthritis, knee replacements, and general deconditioning can prevent the standard arms-over-head position needed for many thoracic and upper abdominal protocols. I've adapted by using arm supports and adjusting the table angle to accommodate limited shoulder flexion, which typically adds about four minutes to the setup time but eliminates the need for a repeat scan due to arm artifacts.
The Bottom Line
Body habitus isn't a variable you can eliminate. It's a constant in medical imaging that you learn to work with through preparation, protocol selection, and honest documentation. The best technologists I've worked with don't fight it - they anticipate it and adjust before the first image is acquired. The worst ones keep running the same protocol on every patient and then wonder why half their exams come back with technical qualifiers. When you see Technically Difficult Exam Due To Body Habitus on a report, it should tell you something specific about what was attempted and what limitations exist. If it just reads as a vague notation with no supporting detail, that's a documentation failure, not a patient problem. The images are what they are. The record should reflect exactly why and what was done about it.