Why Most People Get Therapeutic Communication Wrong
I spent years watching nurses, therapists, and even experienced clinicians fumble through patient interactions because they were reciting textbook techniques instead of actually listening. The gap between what the literature says and what works at 2 AM with a distressed patient is enormous. Let me walk through what actually happens in practice, not what a textbook recommends. Therapeutic communication is fundamentally about purposeful, goal-directed conversation where the focus stays on the patient's needs rather than the clinician's agenda. That sounds simple enough, but the execution is where things fall apart for most people.
Essential Techniques In Therapeutic Communication
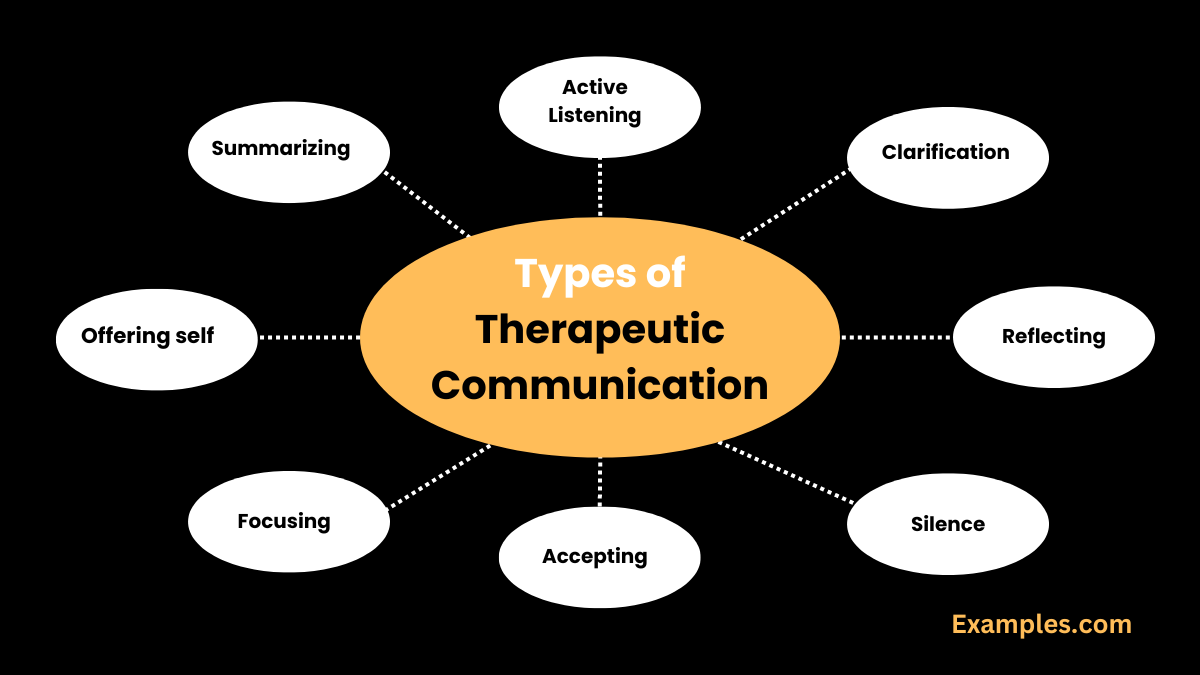
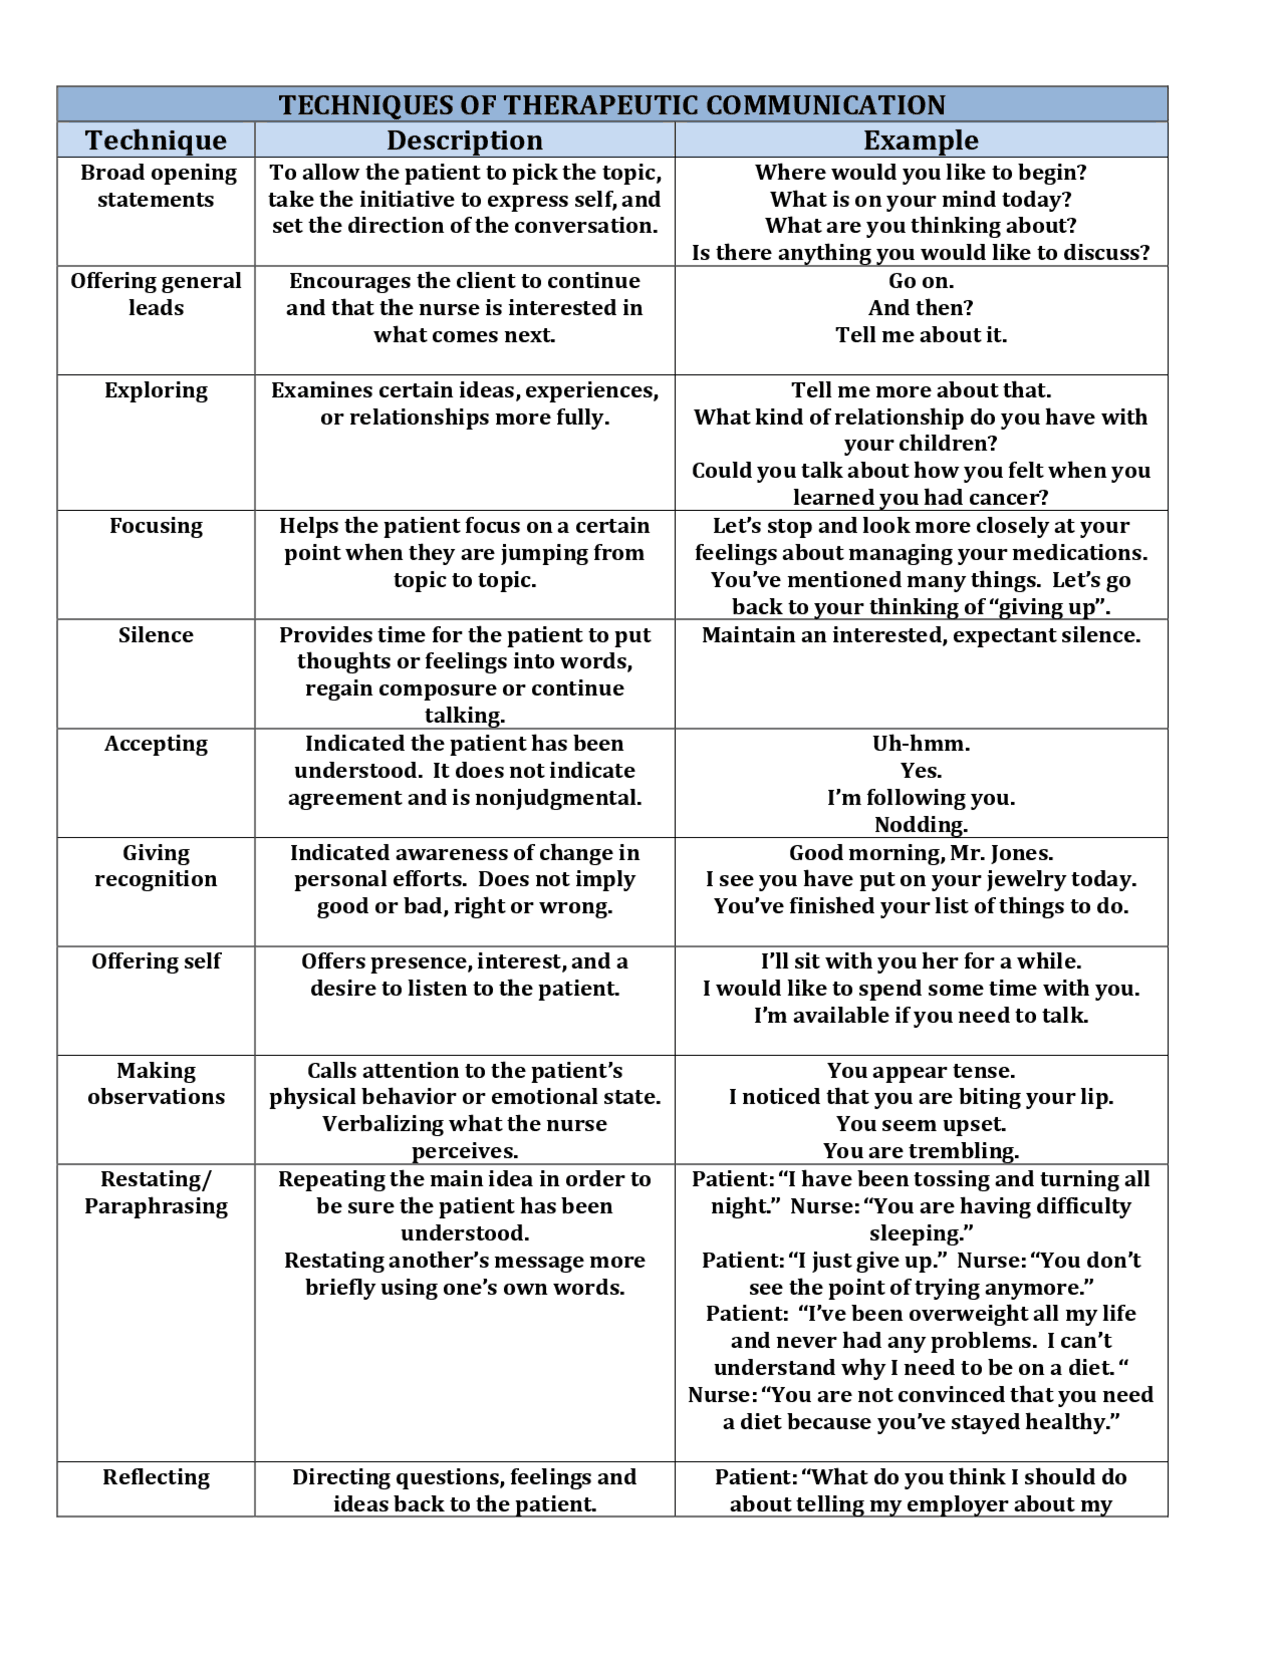
The core techniques break down into several categories, and I am going to go through each one with the kind of detail you will not find in a summary handout. Closed-ended questions are useful for gathering specific factual data. "Are you experiencing chest pain?" gets you a yes or no answer quickly. But if you rely on these exclusively, you shut down the conversation. Patients will give you the information you asked for and nothing more, which means you miss context that could change your entire approach. Open-ended questions do the opposite. "Can you tell me what has been bothering you?" invites the patient to guide the conversation. This is where most of the clinically relevant information comes from. I cannot stress enough how often clinicians skip straight to closed-ended questioning because they are pressed for time. That shortcut costs you information you will need later.
Reflection means repeating back or paraphrasing what the patient said in your own words. "So what you are saying is that the headaches started after you began the new medication." This serves two purposes. It confirms you understood correctly, and it signals to the patient that you are actually tracking what they are telling you. When a patient catches you reflecting back accurately, their posture and engagement level typically shift noticeably. Clarification is asking the patient to elaborate when something is vague. "When you say you feel anxious, can you describe what that feels like physically?" Vague language from patients is not laziness. They are often describing symptoms they do not have the vocabulary for. Your job is to help them articulate it. Silence is probably the most underrated technique and the one most clinicians are uncomfortable with. Sitting quietly for a few seconds after a patient finishes a statement gives them space to continue. I have watched experienced therapists rush to fill silence because they felt awkward, and in doing so they robbed the patient of the next important piece of information. Two seconds of silence after a patient speaks is usually enough time for them to add something significant. Ten seconds feels like an eternity to the clinician. It is not.
Get the Full Details

Restating is repeating key words or phrases the patient used. If a patient says "I just feel completely alone in this," you might respond with "Completely alone." This prompts them to expand without you leading them anywhere specific. Validation acknowledges the patient's feelings as real and understandable. "That sounds really frightening" does not mean you agree with every conclusion they drew. It means you recognize their emotional response as legitimate. This is distinct from sympathy. Sympathy puts you in a position above the patient. Validation meets them where they are. Summarization pulls together the main points of a conversation at the end. "Let me make sure I have this right. You have been having sleep difficulties for about three weeks, the anxiety peaks in the evening, and you are worried this is related to the dosage change." This gives the patient a chance to correct you before you move forward with a treatment plan based on incomplete information.
The Edge Case That Broke My Confidence
Early in my career I had a patient who was a retired engineer and responded to everything with extreme literalism. When I used open-ended questions, he would give me exhaustive technical details about his symptoms that were medically irrelevant. When I used reflection, he would fact-check my paraphrase. Standard techniques were not working because his communication pattern was fundamentally different from what the training assumes. The workaround was structured silence combined with very specific time-bounded questions. "I am going to ask you three questions, and I want a short answer for each. Then you can fill in whatever details you think matter." This gave him the structure he needed while still letting me control the direction of the conversation enough to get clinically useful information. It took longer upfront but saved twenty minutes of running in circles. This is not an anomaly. Patients with certain cognitive styles, neurodivergent patterns, or cultural backgrounds where direct communication is valued over exploratory dialogue will not respond to standard therapeutic communication techniques in the expected way. The techniques are tools, not procedures. You adapt them to the person, not the other way around.
Counter-Intuitive Things No One Teaches
Here is something most training programs will not emphasize. Therapeutic communication techniques work best when they are nearly invisible to the patient. If a patient can clearly identify that you are "using a technique" on them, the therapeutic effect drops significantly. The goal is naturalistic conversation that happens to incorporate these elements, not a checklist performance. Another thing beginners miss: you do not need to use all these techniques in every interaction. A brief check-in with a familiar patient might only require validation and a closed-ended question. A first psychiatric evaluation requires the full range. Matching the depth of your communication to the context prevents both under-engagement and listener fatigue, which is real and affects your judgment. There is also a timing component that is rarely discussed. Silence works differently depending on when you deploy it. Placing silence after the patient shares something emotionally charged is powerful. Placing silence after they ask you a direct question is usually confusing and counterproductive. The difference matters more than most clinicians realize.
Where These Techniques Completely Fail
I need to be blunt about the limitations because nobody else is. Therapeutic communication techniques are ineffective, or even harmful, in acute crisis situations where immediate safety decisions need to be made. A patient in active psychosis, severe mania, or acute suicidal crisis does not benefit from open-ended exploration. They need direct, structured, directive communication. Using reflective techniques with a patient who is actively disorganized can increase their agitation because they perceive you as not taking the situation seriously. Cognitive impairment is another hard limit. Patients with moderate to severe dementia may not have the capacity for the kind of reciprocal dialogue these techniques require. In those cases, validation therapy principles still apply, but the structured question-and-answer framework of therapeutic communication breaks down. You shift toward simpler validation and redirection rather than exploration. Cultural mismatch is a quieter but equally important failure mode. Some cultures value indirect communication and may interpret direct open-ended questions as aggressive or intrusive. Others may view prolonged silence as disrespectful rather than therapeutic. There is no universal application here, and assuming there is one is how you end up with poor outcomes and frustrated patients on both sides.
If you are working in a setting where these techniques are being evaluated purely on throughput metrics, they will feel like a burden. A conversation that takes twelve minutes using proper therapeutic communication might be logged as inefficiency by someone only looking at number of patients seen per hour. This is a structural problem in the system, not a flaw in the techniques. The long-term cost of missed diagnoses and poor patient adherence from rushed conversations is far higher than the time saved, but that cost is invisible on a daily productivity dashboard.
Practical Application
The most effective way to develop these skills is not through reading about them. It is through deliberate practice with feedback. Role-playing with a colleague and having them watch specifically for one technique at a time helps you notice patterns you are unaware of. Recording actual sessions (with consent) and reviewing them is uncomfortable but highly informative. You will hear yourself using "so" and "um" to fill silence you thought you were handling gracefully. Start by picking one technique and focusing exclusively on it for a week. Closed-ended questions are the easiest to notice yourself overusing because they require the least cognitive effort. If you audit your own questions for a single shift, you will likely find that more than sixty percent are closed-ended, even in contexts where open-ended questions would have been clearly more appropriate. The technique that produces the fastest improvement in patient satisfaction scores is validation. It is also the simplest to implement and the hardest to do poorly. Every interaction benefits from at least one genuine validation statement. The others refine and deepen the conversation, but validation is the foundation.

I have found that keeping a small notebook during shifts and jotting down one interaction that went well and one that did not forces you to reflect in real time rather than letting the day blur together. Over six months this habit produces more skill development than any workshop or certification course I have taken. The notebook entries themselves become a reference when you encounter similar situations later. The techniques themselves are straightforward. The difficulty is in the application, which depends entirely on reading the patient, managing your own discomfort with silence, and resisting the urge to control the conversation. Those are skills that only come from doing the work repeatedly and paying attention to what actually happens rather than what you expected to happen.