How Teg Platelet Mapping Actually Works in the ICU
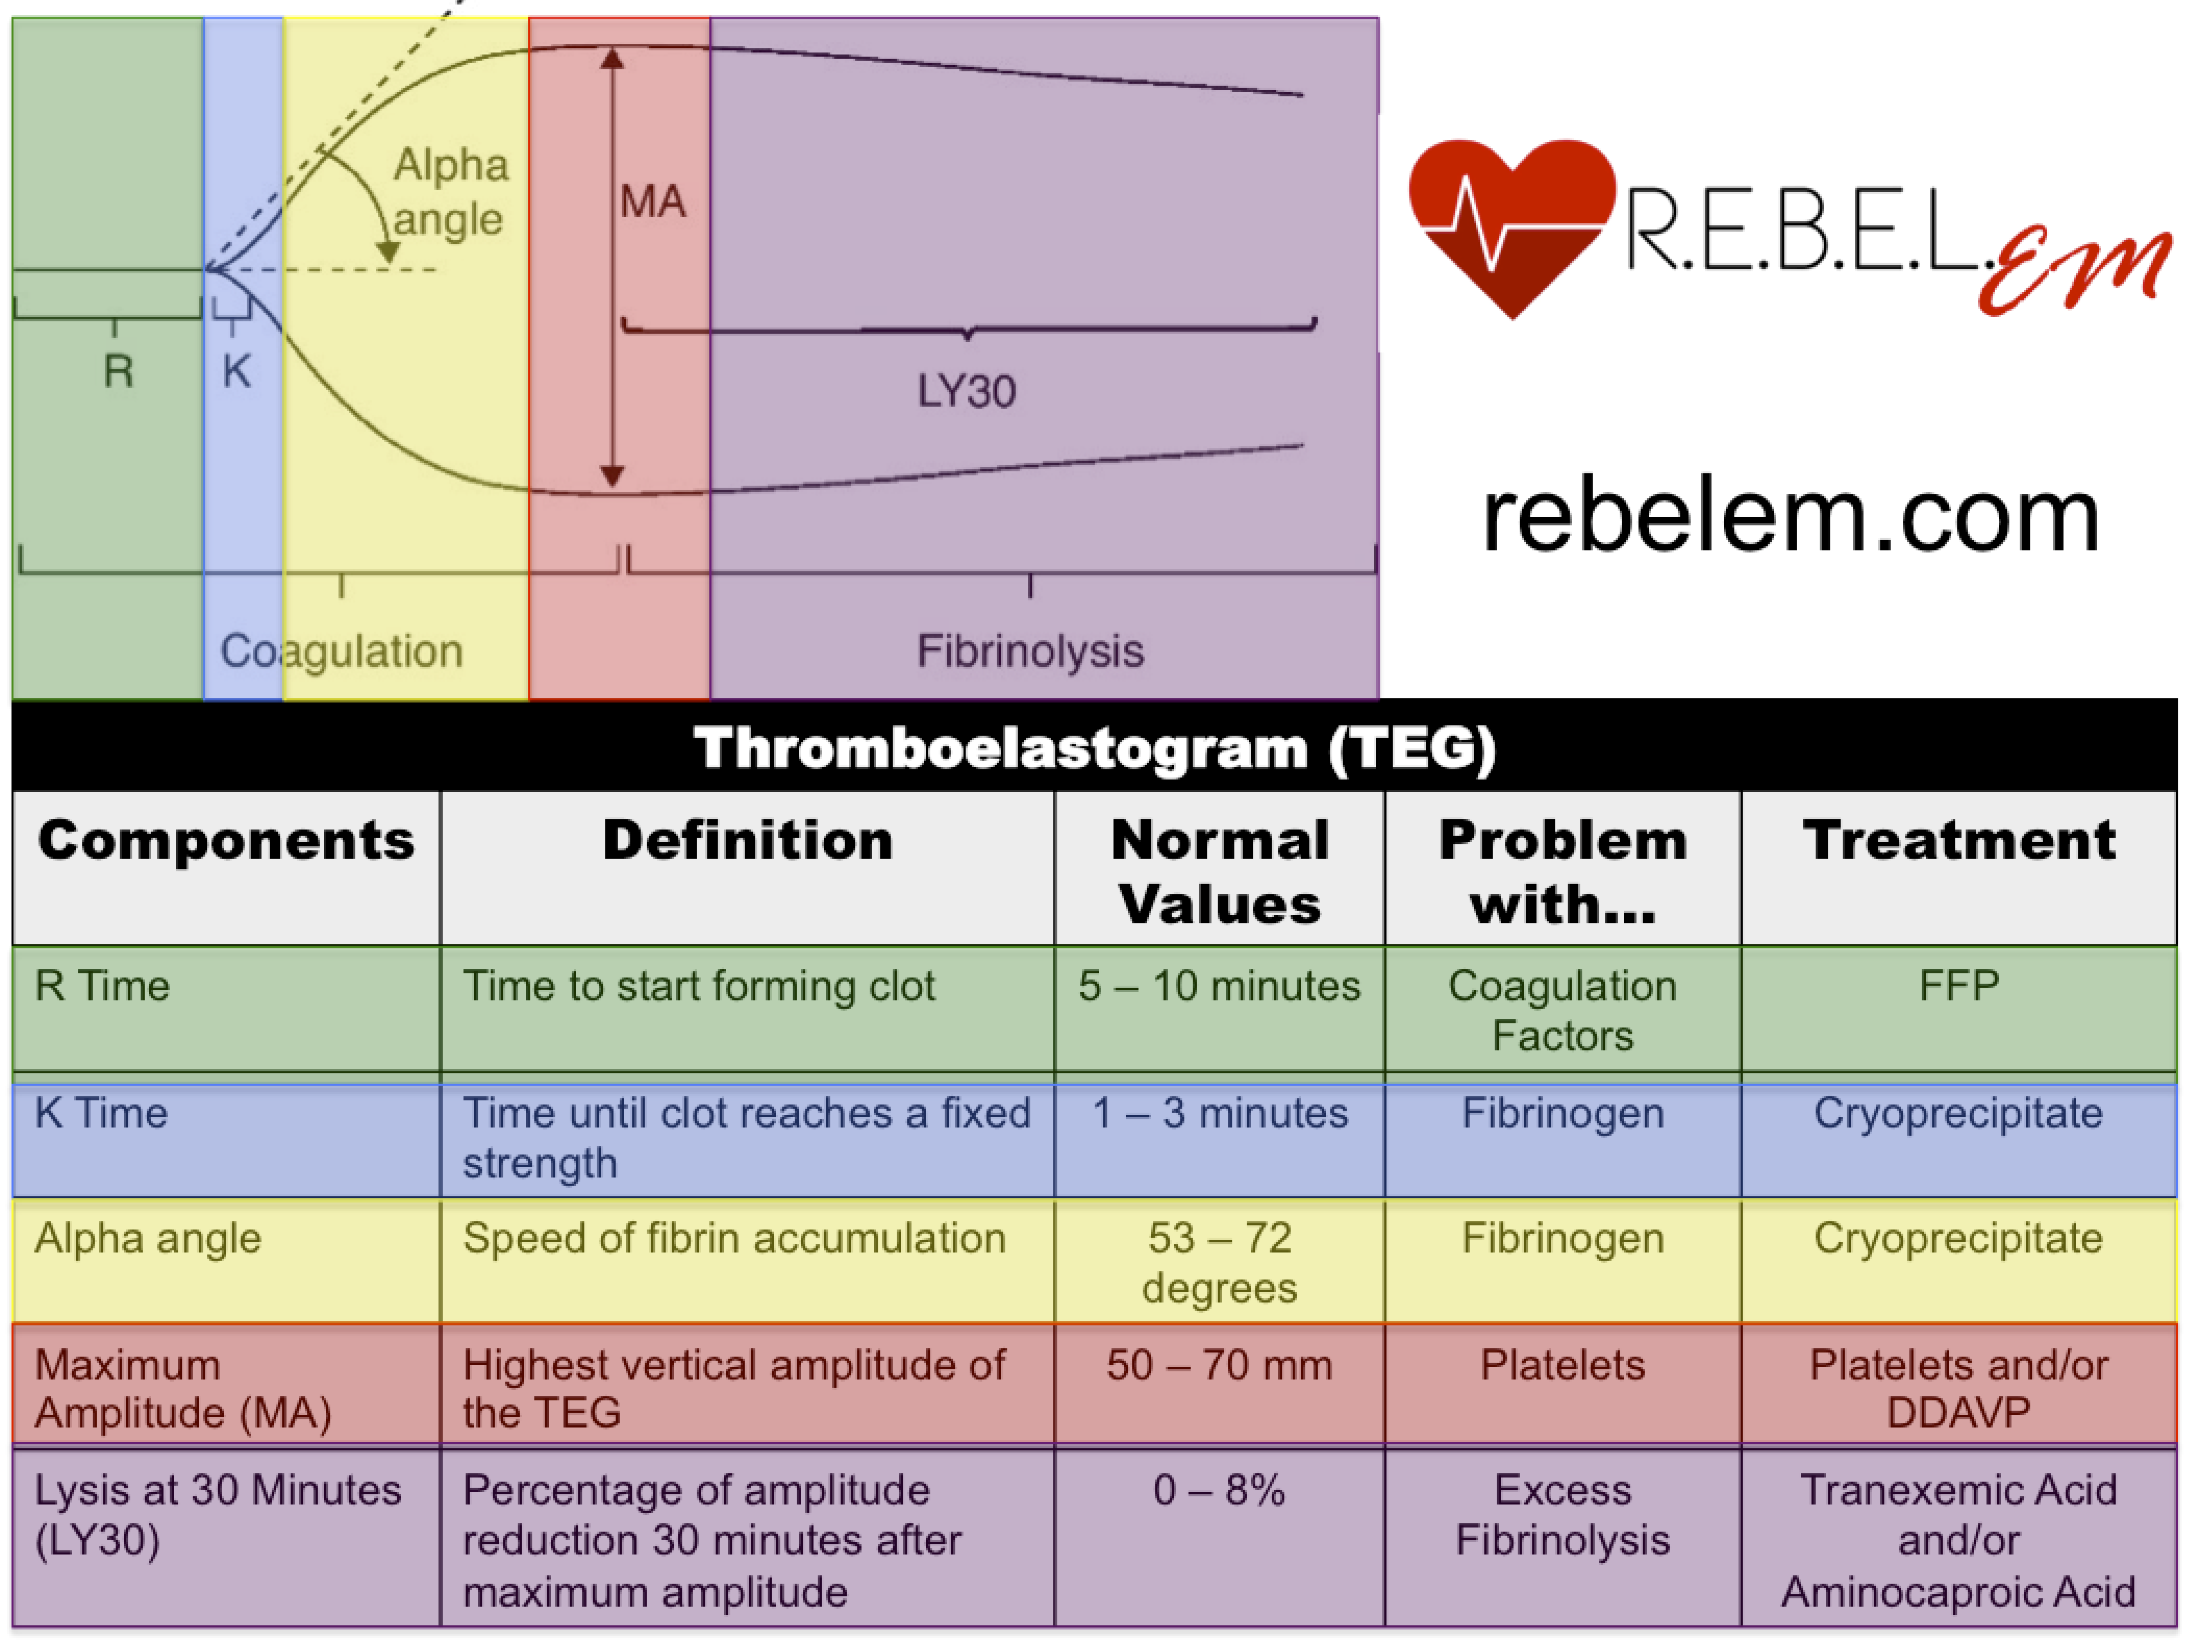
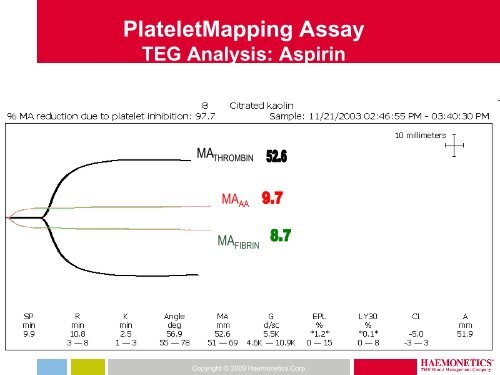
The Teg Platelet Mapping test runs on the TEG 5/5e hemostasis analyzer using a modified whole blood impedance aggregometry method. You draw 20 microliters of citrated blood, add it to a disposable cartridge with four separate reaction channels, and get results in about 43 minutes. That is the basic promise. The reality of running these at 2 AM when the perfusionist is shouting because someone is oozing from every venipuncture site is less cinematic. There are four channels in the cartridge. The unstimulated channel measures the baseline maximum clot firmness from all clotting pathways combined. The ADP channel reveals P2Y12 inhibitor effect, mostly what clopidogrel, prasugrel, and ticagrelor do. The TRAP channel tests thrombin receptor–activated platelets and gives you a general platelet function readout. The AA channel measures cyclooxygénase-1 pathway inhibition, so aspirin effect shows up here. Simple enough until you try to pull meaning out of a real patient's numbers. The output metric is Platelet Function Units, calculated as PFU = MCF unstimulated minus MCF test channel, divided by the contribution of functional fibrinogen to clot strength. That fibrinogen contribution is estimated from the difference between the FIBTEM MCF and the unstimulated MCF. The formula sounds straightforward. It breaks down fast when fibrinogen levels are abnormal, which they are in most of the surgical patients I run these on.
Teg Platelet Mapping Interpretation: The Practical Guide
Normal unstimulated MCF on this system typically sits around 65 millimeters. TRAP channel runs roughly 60 to 70 millimeters. ADP is usually 50 to 60 millimeters if the patient is not on any P2Y12 inhibitor. AA comes in around 55 to 65 millimeters in someone who has never touched aspirin. These are rough reference points, not hard cutoffs, and your lab may have slightly different normals depending on the reagent lot. When you see an elevated ADP channel MCF above your lab's upper reference limit, that means the P2Y12 pathway is not inhibited. In a patient who should be on clopidogrel and is still forming robust clots through that route, you would expect to see this. It does not necessarily mean non-responder status. It could mean the dose was missed, the drug interaction with rifampin is chewing through clopidogrel, or the patient simply has high platelet reactivity to begin with. Low ADP MCF in the 20 to 35 millimeter range after recent loading with prasugrel is exactly what you want to see. A patient on ticagrelor might show slightly higher ADP values compared to prasugrel, which is a known pharmacodynamic difference, not a failure of the drug.
The AA channel tells you about aspirin effect. Values below 55 millimeters suggest platelet inhibition from cyclooxygenase-1 blockade. Values above that suggest inadequate aspirin effect or that the patient simply does not take it. The issue with AA is that indomethacin and other NSAIDs also inhibit COX-1, so the signal is not perfectly specific to aspirin. Not something you need to worry about at 3 AM, but worth knowing before you send a transfusion request. I remember one case where the unstimulated MCF came back at 82 millimeters with a corresponding fibrinogen contribution of 45 millimeters. Someone had been given cryoprecipitate intraoperatively. The functional fibrinogen value inflated the denominator in the PFU calculation, which artificially depressed all the PFU results. The platelets were actually fine, but the math made them look suppressed. I recalculated manually using the actual fibrinogen concentration from the coagulation panel instead of relying on FIBTEM-derived estimates, and the interpretation shifted completely. Always check the FIBTEM result before trusting the default PFU numbers if fibrinogen has been manipulated.
Get the Full Details
Common Interpretation Pitfalls
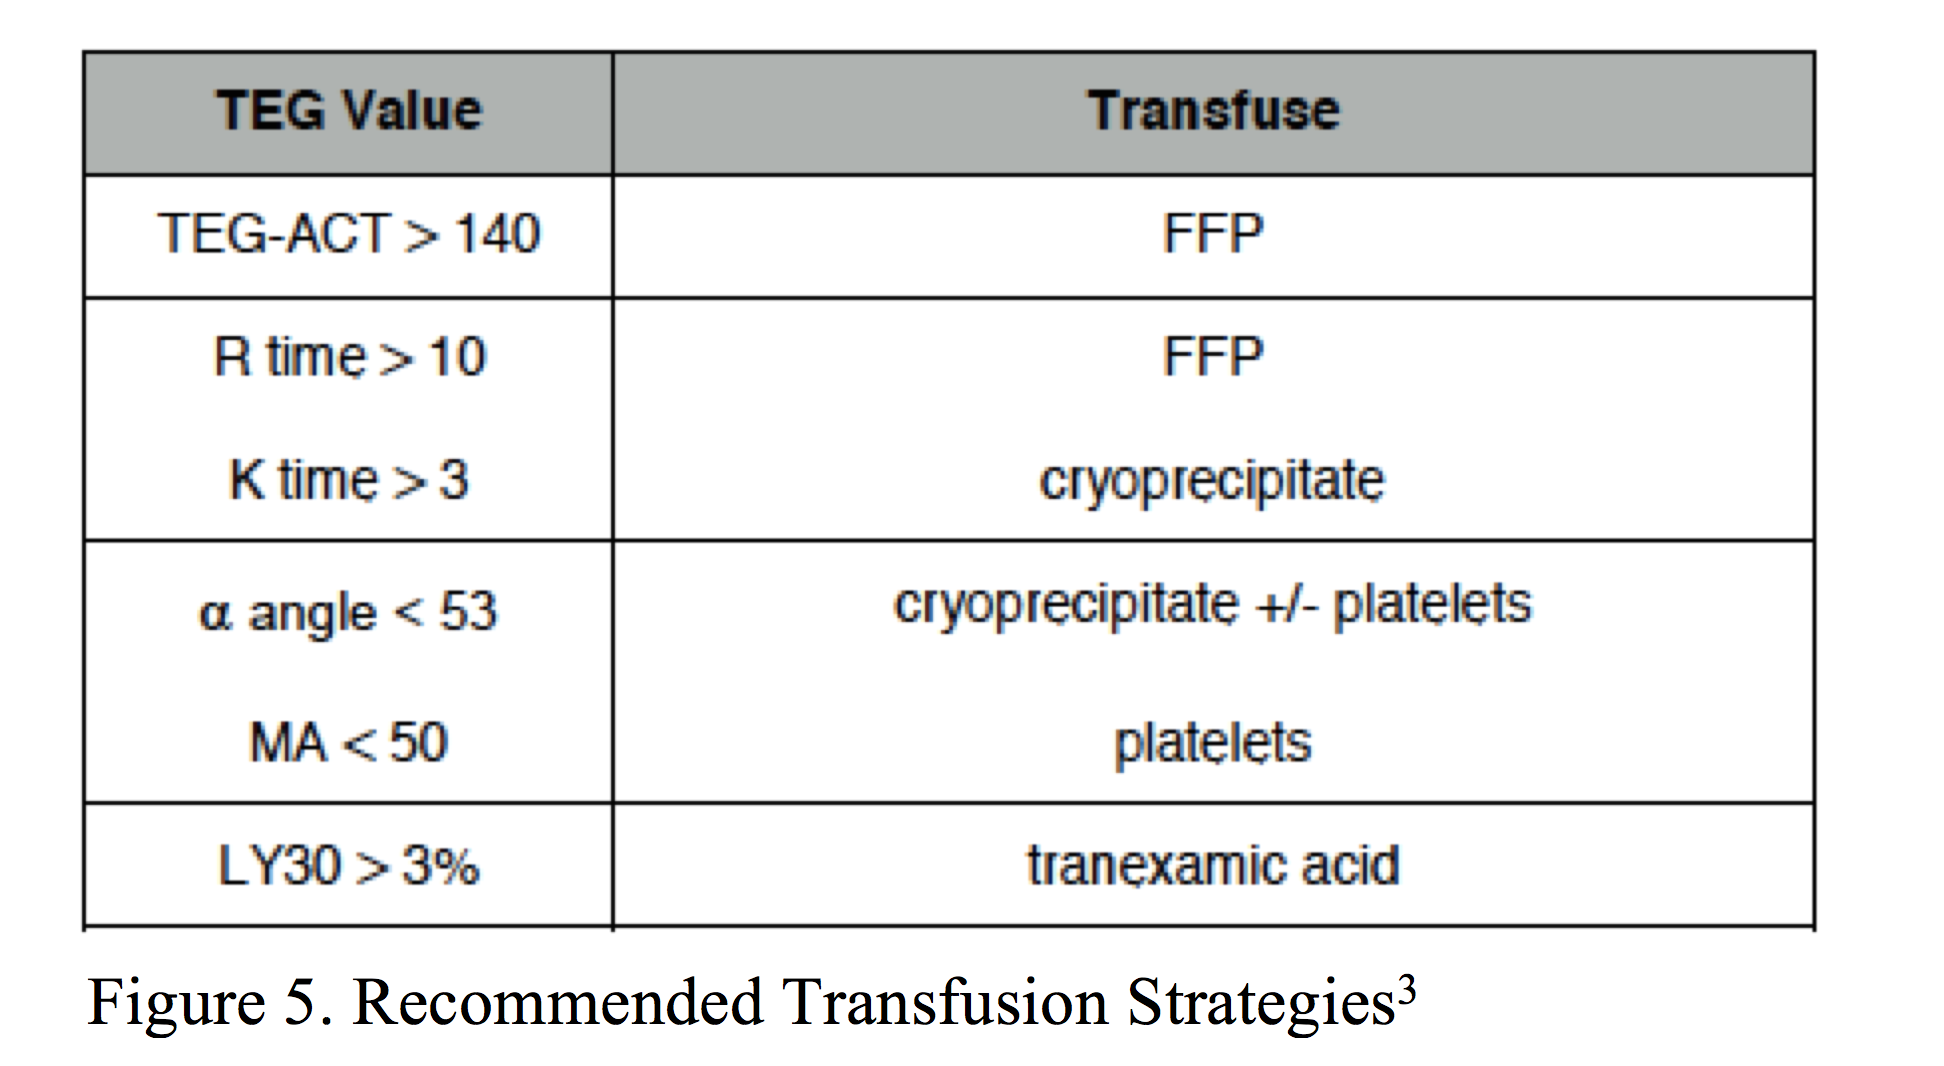
Heparin contamination is the biggest practical problem. If a blood sample gets drawn from a line that was recently flushed with heparin, the unstimulated channel will show reduced clot formation, and every subsequent channel becomes unreliable. The resulting pattern mimics a diffuse platelet function defect when none exists. Draw samples from a peripheral stick or from the arterial line after discarding at least ten milliliters. If the unstimulated MCF is below 40 millimeters and the patient is on heparin, the sample is likely contaminated or the heparin reversal is incomplete. Cold temperature during the assay is another silent killer of data quality. The TEG instrument warms the cartridge to 37 degrees Celsius, but if the blood sits on ice or at room temperature for too long before loading, platelet function degrades. I have seen ADP values drop into the therapeutic range purely because the phlebotomy team left the tube in the specimen cart for twenty minutes. Keep samples at body temperature or process them within fifteen minutes. When the OR calls you at midnight because the results look unexpectedly suppressive, check the phlebotomy timesheet first. The instrument's default interpretation uses a fixed threshold for what counts as therapeutic platelet inhibition. Some institutions use an ADP PFU cutoff of 20 for defining suppression, others use 30. There is no universal standard, and the difference matters when you are deciding between giving platelets or just watching. Know what threshold your institution adopted and why.
Teg Platelet Mapping Interpretation also struggles in extreme thrombocytopenia. When the platelet count drops below 50,000 per microliter, the MCF values become inherently low across all channels regardless of drug effect. The test was validated primarily in populations with platelet counts above 100,000, so extrapolating results below that threshold is unreliable. In that scenario, you are better off relying on viscoelastic assays like FIBTEM and EXTEM alongside a clinical assessment rather than pushing the platelet mapping numbers further than they will go.
When the Results Don't Match the Clinical Picture
This happens more often than the literature admits. A patient with normal PFU values on the cartridge can still bleed aggressively from a surgical field. Platelet mapping only measures aggregate strength under static conditions in citrated blood. It does not capture shear stress environments, von Willebrand factor dysfunction, or the interaction between platelets and the vascular wall that actually matters during hemorrhage. A patient with Bernard-Soulier syndrome or severe vWD can have perfectly normal Teg platelet mapping results and still have a major platelet-type bleeding diathesis. Conversely, a patient with profoundly suppressive PFU values may be clinically stable with minimal oozing. Do not treat the number. Treat the patient. The classic mistake I see repeatedly is ordering platelet transfusions based solely on an ADP PFU below the institutional cutoff in an asymptomatic post-op cardiac patient. The patient is hemodynamically stable, the drains are minimal, and the hemoglobin is acceptable. The transfusion adds volume, introduces inflammatory mediators, and carries immunomodulatory risk for zero clinical benefit. If the PFU is low but there is no bleeding, watch the patient. Recheck in two hours if things change. One more thing that trips people up: the timing of the draw relative to drug administration matters significantly. If you draw an ADP channel sample two hours after a clopidogrel dose, you will see near-maximal inhibition. Draw it six hours later and the effect is noticeably blunted because clopidogrel's active metabolite has a short half-life. Many surgeons forget this and attribute fluctuating PFU values to drug resistance when the variation is simply pharmacokinetic noise. Standardize your draw times when you are tracking response to antiplatelet therapy over multiple days.
Quick Reference for Teg Platelet Mapping Interpretation
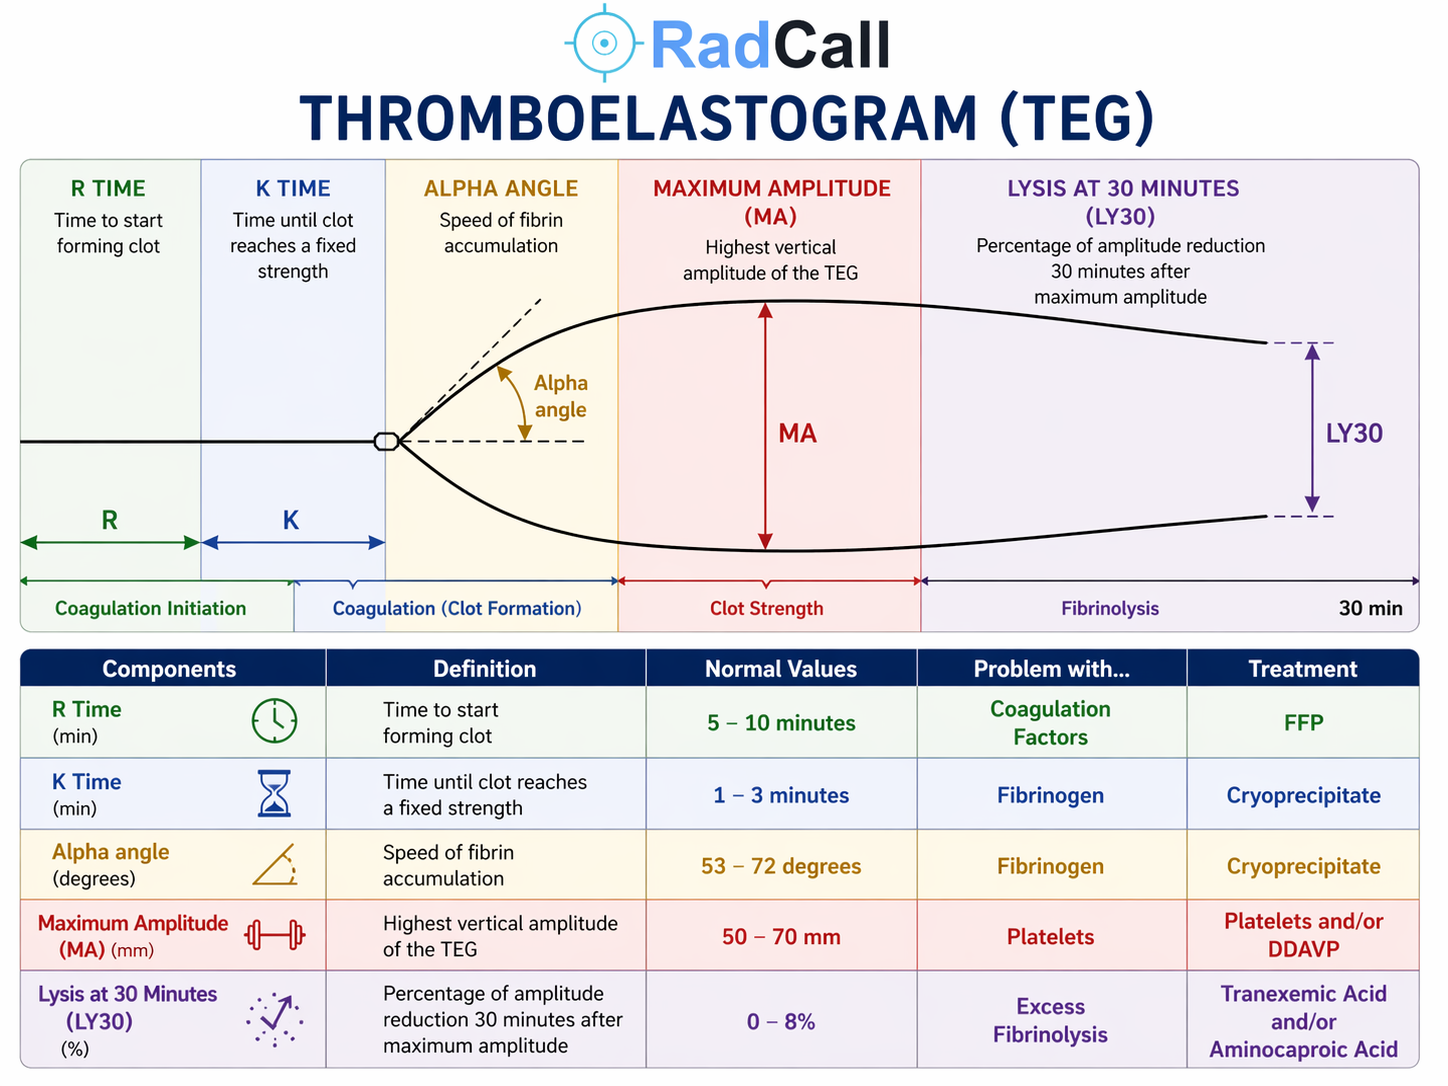
Unstimulated MCF above 70 with normal TRAP and AA: elevated fibrinogen or acute phase response, nothing platelet-specific to worry about. ADP MCF below 45 in a patient on ticagrelor: expected, not a cause for concern unless bleeding is present. AA MCF above 65 in a patient taking aspirin daily: poor adherence or drug interaction, verify the medication history before declaring aspirin resistance. TRAP MCF below 40 with normal ADP and AA: rare, consider glycoprotein IIb/IIIa antagonist exposure or an underlying platelet production disorder. Any channel with an unstimulated baseline below 40: suspect heparin contamination or severe consumptive coagulopathy, repeat the sample. The test is useful. It is not definitive. It gives you a snapshot of platelet function under artificial conditions, and that snapshot is sometimes very helpful and sometimes misleading. The skill is in knowing which is which. I have been running these long enough to stop being alarmed by a single weird number and start looking for the pattern across channels, the clinical context, and the timeline of drug administration. The answer is rarely in one channel alone.