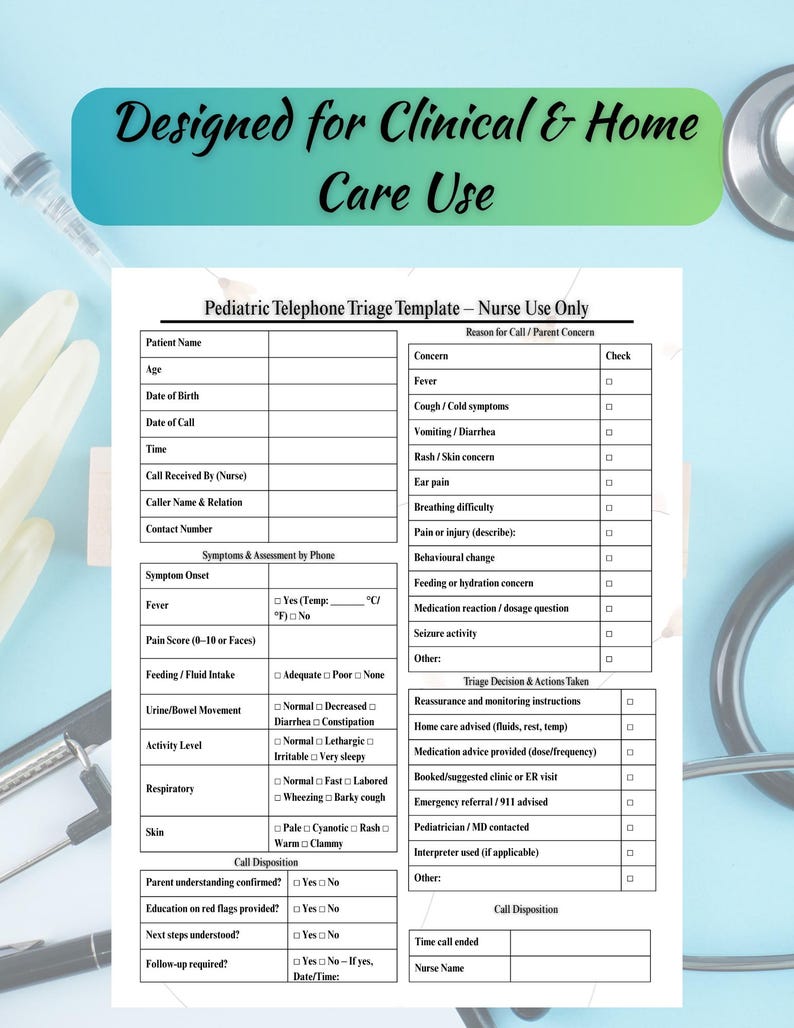
Telephone Triage For Nurses: What It Actually Looks Like When the Phone Won't Stop Ringing
Most people think telephone triage is just answering questions and sending people where they need to go. That is technically true but it leaves out the part where you are trying to extract symptoms from a panicked grandmother who insists her 72-year-old husband's "indigestion" is nothing because his brother had indigestion and lived to be ninety. The algorithm will not save you there. You have to. It is a structured decision-making process where a registered nurse takes patient calls, assesses the severity of symptoms in real time, and determines whether the person needs emergency care, same-day evaluation, home management, or a routine appointment. The standard protocols you will see referenced are AHRQ, ESI, and various nurse-advised disposition guidelines like those from the American College of Nurse Executives. The goal is consistency so that call T-13 gets the same level of escalation as call T-47. Here is the thing most training programs gloss over: the protocol is a safety net, not a crutch. Experienced triage nurses deviate from the algorithm constantly because the algorithm was written for ideal cases, not for the guy who says "my stomach hurts" for twenty minutes before admitting he has been vomiting blood. You learn to listen past the first complaint. The initial presentation is rarely the actual problem.
The Workflow When It Is Not Going Wrong
A standard shift runs like this. You log into the triage system, pull up the patient chart, and review their active medications and known conditions before the call even connects. Most systems flag high-risk profiles automatically. Then you run through the screening question set. The critical window is the first ninety seconds. Patient identifies their chief complaint, you immediately check for red flag criteria, and then you drill down into associated symptoms using a modified sample history format. By minute three you should already know whether this is a 911 situation, an urgent care referral, or "take acetaminophen and call back tomorrow" territory. The disposition codes matter more than you would think. A Lazarus response—where symptoms resolved before the patient reached the ED—gets coded differently than an active presentation, and misclassification here distorts your facility's utilization data and can trigger incorrect quality metrics. One wrong code on a call that turned around can look like a missed discharge on paper.
The Edge Case That Made Me Rethink My Entire Approach
I was covering a night shift at a mid-sized hospital system when a caller came in about mild lower abdominal pain. Standard protocol for a female in her fifties with that complaint would push toward same-day evaluation to rule out ovarian torsion or appendicitis. The triage algorithm gave it a B-level disposition. But the patient kept mentioning that her son had recently died of an abdominal aortic aneurysm, and she said the pain felt "different" from anything she had experienced before. She was being oddly calm about it. The algorithm said same-day clinic. My gut said otherwise. I asked specifically about pulsatile sensation in the abdomen and whether she had noticed any back pain radiating through to her spine. She said no to both, but then added almost as an afterthought that her mother also had an aneurysm. Family history plus subjective "different" pain in an older female is a known AAscreening trigger that some protocol versions underweight. I escalated to immediate ED evaluation rather than waiting until morning. CT confirmed a 5.2 centimeter AAA. She got to the table within forty-five minutes of the call. The workaround I built after that: I now flag any caller who mentions a family history of vascular events during abdominal complaints regardless of what the screening algorithm initially suggests. Document the deviation in the call notes with the specific clinical reasoning. It protects you later and it saves lives in the meantime. Most audit committees will review and support a well-documented clinical override.
Get the Full Details

Common Pitfalls That Nobody Warns You About
The first one is anchoring bias. Once the patient gives you a diagnosis or a symptom cluster, your brain locks onto it and you stop listening for contradictory information. I had a caller who insisted she was having a panic attack. She described the palpitations, the tingling, the dread. Every symptom matched. I was two-thirds through the anxiety protocol when she mentioned she had just flown in from an international flight six hours prior. Pulmonary embolism does not care that your patient thinks she is having anxiety. Always run the D-dimer and Wells criteria questions even when the picture looks psychiatric. The second pitfall is protocol fatigue. After three hundred calls a month, you start skimming the questioning sequence. You think you have heard every variation of chest pain until someone describes pain that is strictly positional and worse when lying flat, which turned out to be pericarditis, not gastritis. The algorithm has a branch for pericarditis but you will skip past it if you are not actually reading each question out loud instead of mentally checking boxes. The third one is documentation drag. The better your electronic health record integration, the less time you spend writing. Poor integration means you are bouncing between the triage software, the charting system, and the scheduling tool, and each switch costs you thirty to forty-five seconds. Over a twelve-hour shift with sixty to eighty calls, that adds up to nearly an hour of lost productivity. Factor that into your staffing models.
What the Protocols Do Not Cover
Telephone Triage For Nurses does not work well for pediatric fever in children under three months old unless you have a very specific cold-calling pathway built in. The threshold for concern is so low that almost every single call in that age group should route directly to a physician or the ED regardless of what the screening tool says. Same issue with post-surgical patients who are less than thirty days out from surgery. Any fever, any wound complaint, any respiratory distress from that population gets escalated, not triaged. Language barriers are another hard limit. If you do not have a certified medical interpreter available on the line within sixty seconds, your triage accuracy drops significantly. You cannot reliably assess symptom severity through a basic translator app when the patient is trying to describe acute chest pain. This is not a technology problem. It is a communication problem, and it requires staffing solutions, not better software.
How to Actually Get Good at This
Start by shadowing someone who has been doing this for at least two years. Watch how they handle the calls that do not fit neatly into any protocol category. Take notes on the exact questions they ask when the algorithm stalls. Then practice with case studies from the NAACOG or the Emergency Nurses Association resources. Run through at least fifty simulated calls before you are cleared for independent phone duty. After that, your improvement comes from audit feedback. Request monthly review of a random sample of your calls. Look for patterns where other nurses would have routed differently. The discrepancy rate between experienced triage nurses and junior nurses on complex cases is usually around eighteen to twenty-two percent according to internal audits at most large health systems. That gap closes with deliberate practice and case review, not with more protocol manuals.

When Telephone Triage For Nurses Simply Fails
It fails when you are understaffed and the call volume exceeds what one nurse can handle without compromising assessment quality. I have worked shifts where we were taking eight to ten simultaneous calls and the triage time per patient dropped to under two minutes. That is not triage. That is damage control. Under those conditions, the error rate climbs and the risk of missed time-critical presentations becomes unacceptable. The only real solution is capping concurrent calls or adding a second triage nurse during peak hours, usually between 7 PM and 11 PM on weekdays and Saturday mornings. It also fails with patients who have complex comorbidities where the symptom overlap makes remote assessment nearly impossible. A diabetic with renal disease, heart failure, and peripheral neuropathy calling about leg swelling could be anything from fluid overload to cellulitis to a DVT. No phone conversation resolves that safely. These patients should bypass telephone triage entirely and go straight to an in-person evaluation. Build that exemption into your protocol. The bottom line is that telephone triage works when you have adequate time, proper tools, and the clinical judgment to know when the tool is not enough. The protocols keep you from making obvious mistakes. Your experience keeps you from making the ones that do not show up in the handbook.