Nursing Documentation Templates: What Actually Works in Clinical Practice
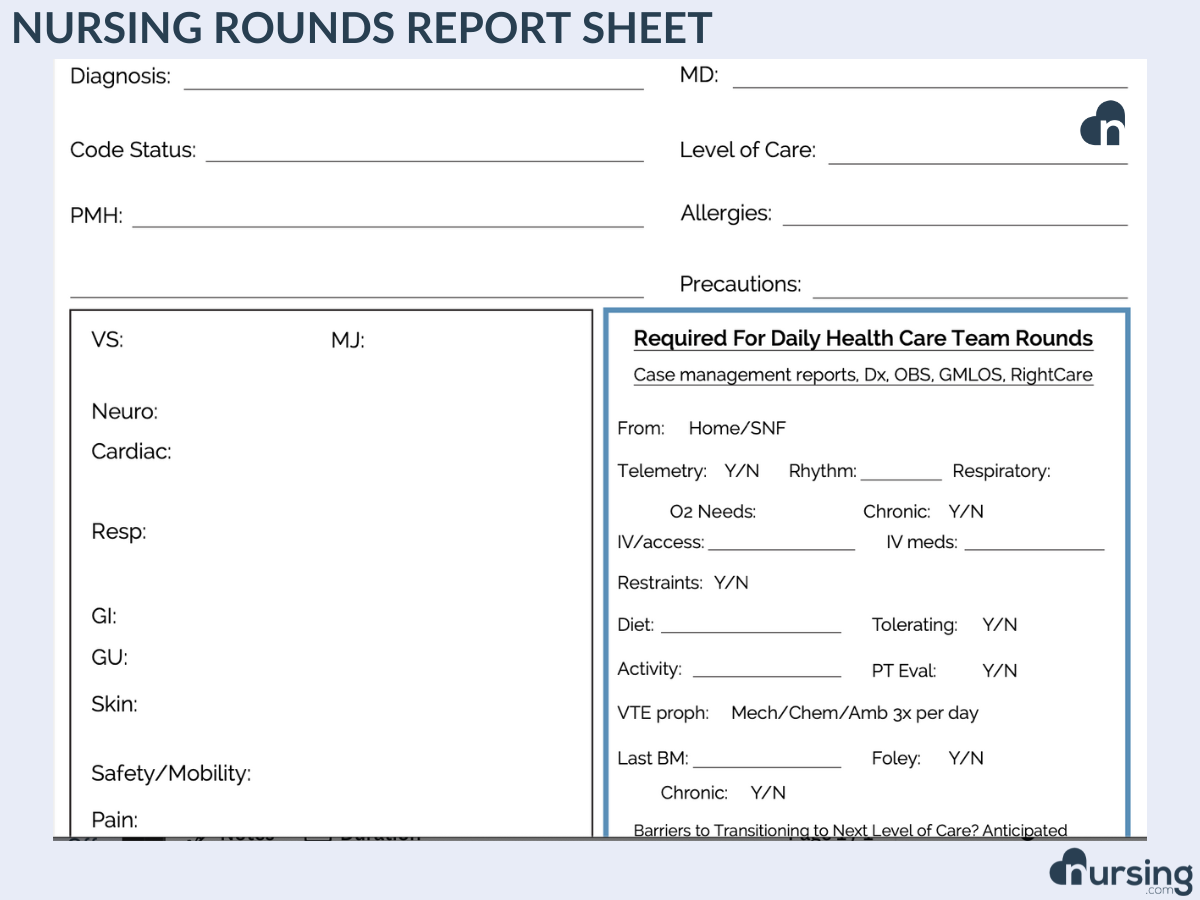
I spent three years managing chart audits across two hospital systems before I realized most nursing templates are either too rigid or too vague to be useful. The good ones cut your documentation time significantly while actually capturing the data your team needs. Most templates out there were written by people who haven't had to fill one out at 11pm after a twelve-hour shift. This is a comprehensive care plan template that covers the full nursing process in one structured format. It follows the standard ADPIE framework — Assessment, Diagnosis, Planning, Implementation, and Evaluation — but organizes it in a way that aligns with what hospital auditors actually look for. You can find it on nursing education forums and some academic resource sites. The exact link varies depending on where you're accessing it, but searching the exact phrase will bring up the PDF versions that circulate widely. The reason it gets referenced so often is that it includes fields for actual measurable outcomes. Most templates just have a box labeled "evaluation" and leave it at that. This one requires you to specify the timeline for reassessment, the criteria for measuring improvement, and what you would do if the patient isn't responding to the intervention. That last part is the one that actually matters during a chart review.
When I was coordinating quality improvement audits, I noticed a pattern. Nurses who used loose templates tended to write things like "patient improved" in the evaluation section without any specifics. Those charts flagged every time. The nurses using more detailed documentation had far fewer issues. Not because they were better writers, but because the template forced them to put actual numbers and timeframes in place of generic statements.
How It Actually Works in Practice
Fill it out during your shift handoff or right after your med pass. Don't wait until the end of your shift when you're trying to remember what happened at 3pm. The assessment section works best when you go system by system rather than trying to capture everything at once. Vital signs, intake and output, pain scores, skin integrity, mobility status — those are the baseline fields you should complete for every admission or every morning update. The nursing diagnosis section is where people stall out. The template gives you standard NANDA-approved categories to choose from, which helps, but the real skill is picking the right one. A lot of beginners default to "acute pain" for every patient with a pain score above zero. That's not wrong, but it's also not specific enough to drive actual interventions. If a post-surgical patient has a pain score of 7 and you only document "acute pain," your care plan looks the same as someone with a headache. Use the related factors and defining characteristics fields in the template to narrow it down. "Acute pain related to surgical incision as evidenced by report of pain score of 7, guarding behavior, and tachycardia" gives you something you can actually intervene against and measure. Planning and implementation are where the template shines. It forces you to separate short-term goals from long-term goals. Short-term might be "patient will report pain reduction to 3 or below within 1 hour of intervention." Long-term is "patient will demonstrate proper incision care techniques prior to discharge." Writing those out separately changes how you approach the implementation field because you can't just check a box and move on. You have to document each intervention with a rationale attached. Not for the grade, but because if another nurse picks up that chart at midnight, they need to understand why something was done, not just what was done.
Get the Full Details

The evaluation section is the one most people rush. I've seen complete care plans with a single sentence in evaluation because the template didn't make it painful enough to do it properly. This template includes a date-by-date reassessment field, which sounds minor but changes how you track progress. Instead of writing a general note about improvement, you log specific changes on specific dates. That becomes invaluable during discharge planning or when you're handing off to another unit.
What The Template Doesn't Handle Well
It's not designed for rapid-acuity situations. If you're in an emergency department or an ICU where patients change status every hour, this template is too cumbersome. The structure assumes a stable patient population where you have time for systematic documentation. Trying to force it into an acute trauma workflow just slows you down and creates incomplete records. In those environments, SBAR or a simplifiedchart format works better. Use this template for med-surg, step-down, and long-term care units where assessment patterns and chronic condition management are the focus. Another limitation: it doesn't integrate well with most electronic health record systems without modification. If your hospital uses Epic or Cerner, you'll likely need to map the template fields to their required documentation areas. Some nursing programs require students to submit this template as part of their coursework, but real-world hospitals often have their own EHR-driven forms. Learning to cross-reference between the two is a skill that takes time. I used to spend about twenty minutes each shift translating between the academic template and our hospital's system while I was still in school. Eventually I stopped carrying both and just used whichever one the current setting required, but I kept the template format in my head for the structure it imposed on my thinking.
A Common Mistake to Avoid
Copies the template without adapting it to the patient. I watched a student submit a care plan where the evaluation stated the patient was "alert and oriented" three times in a row for a patient who was clearly declining. The template was filled out correctly, but nobody had actually updated it after the patient's condition changed. A template only works if you keep it current. That means going back to revise the evaluation section when outcomes shift, not just filling it out once and treating it as a one-time assignment. The format itself doesn't cause problems. The problem is treating it like a form to complete rather than a living document. Update it when the diagnosis changes. Update it when interventions aren't working. Update it when the patient's response to treatment indicates you need to pivot. That's the difference between a template that saves you time and one that becomes paperwork you resent.