Working With Time in OT Practice
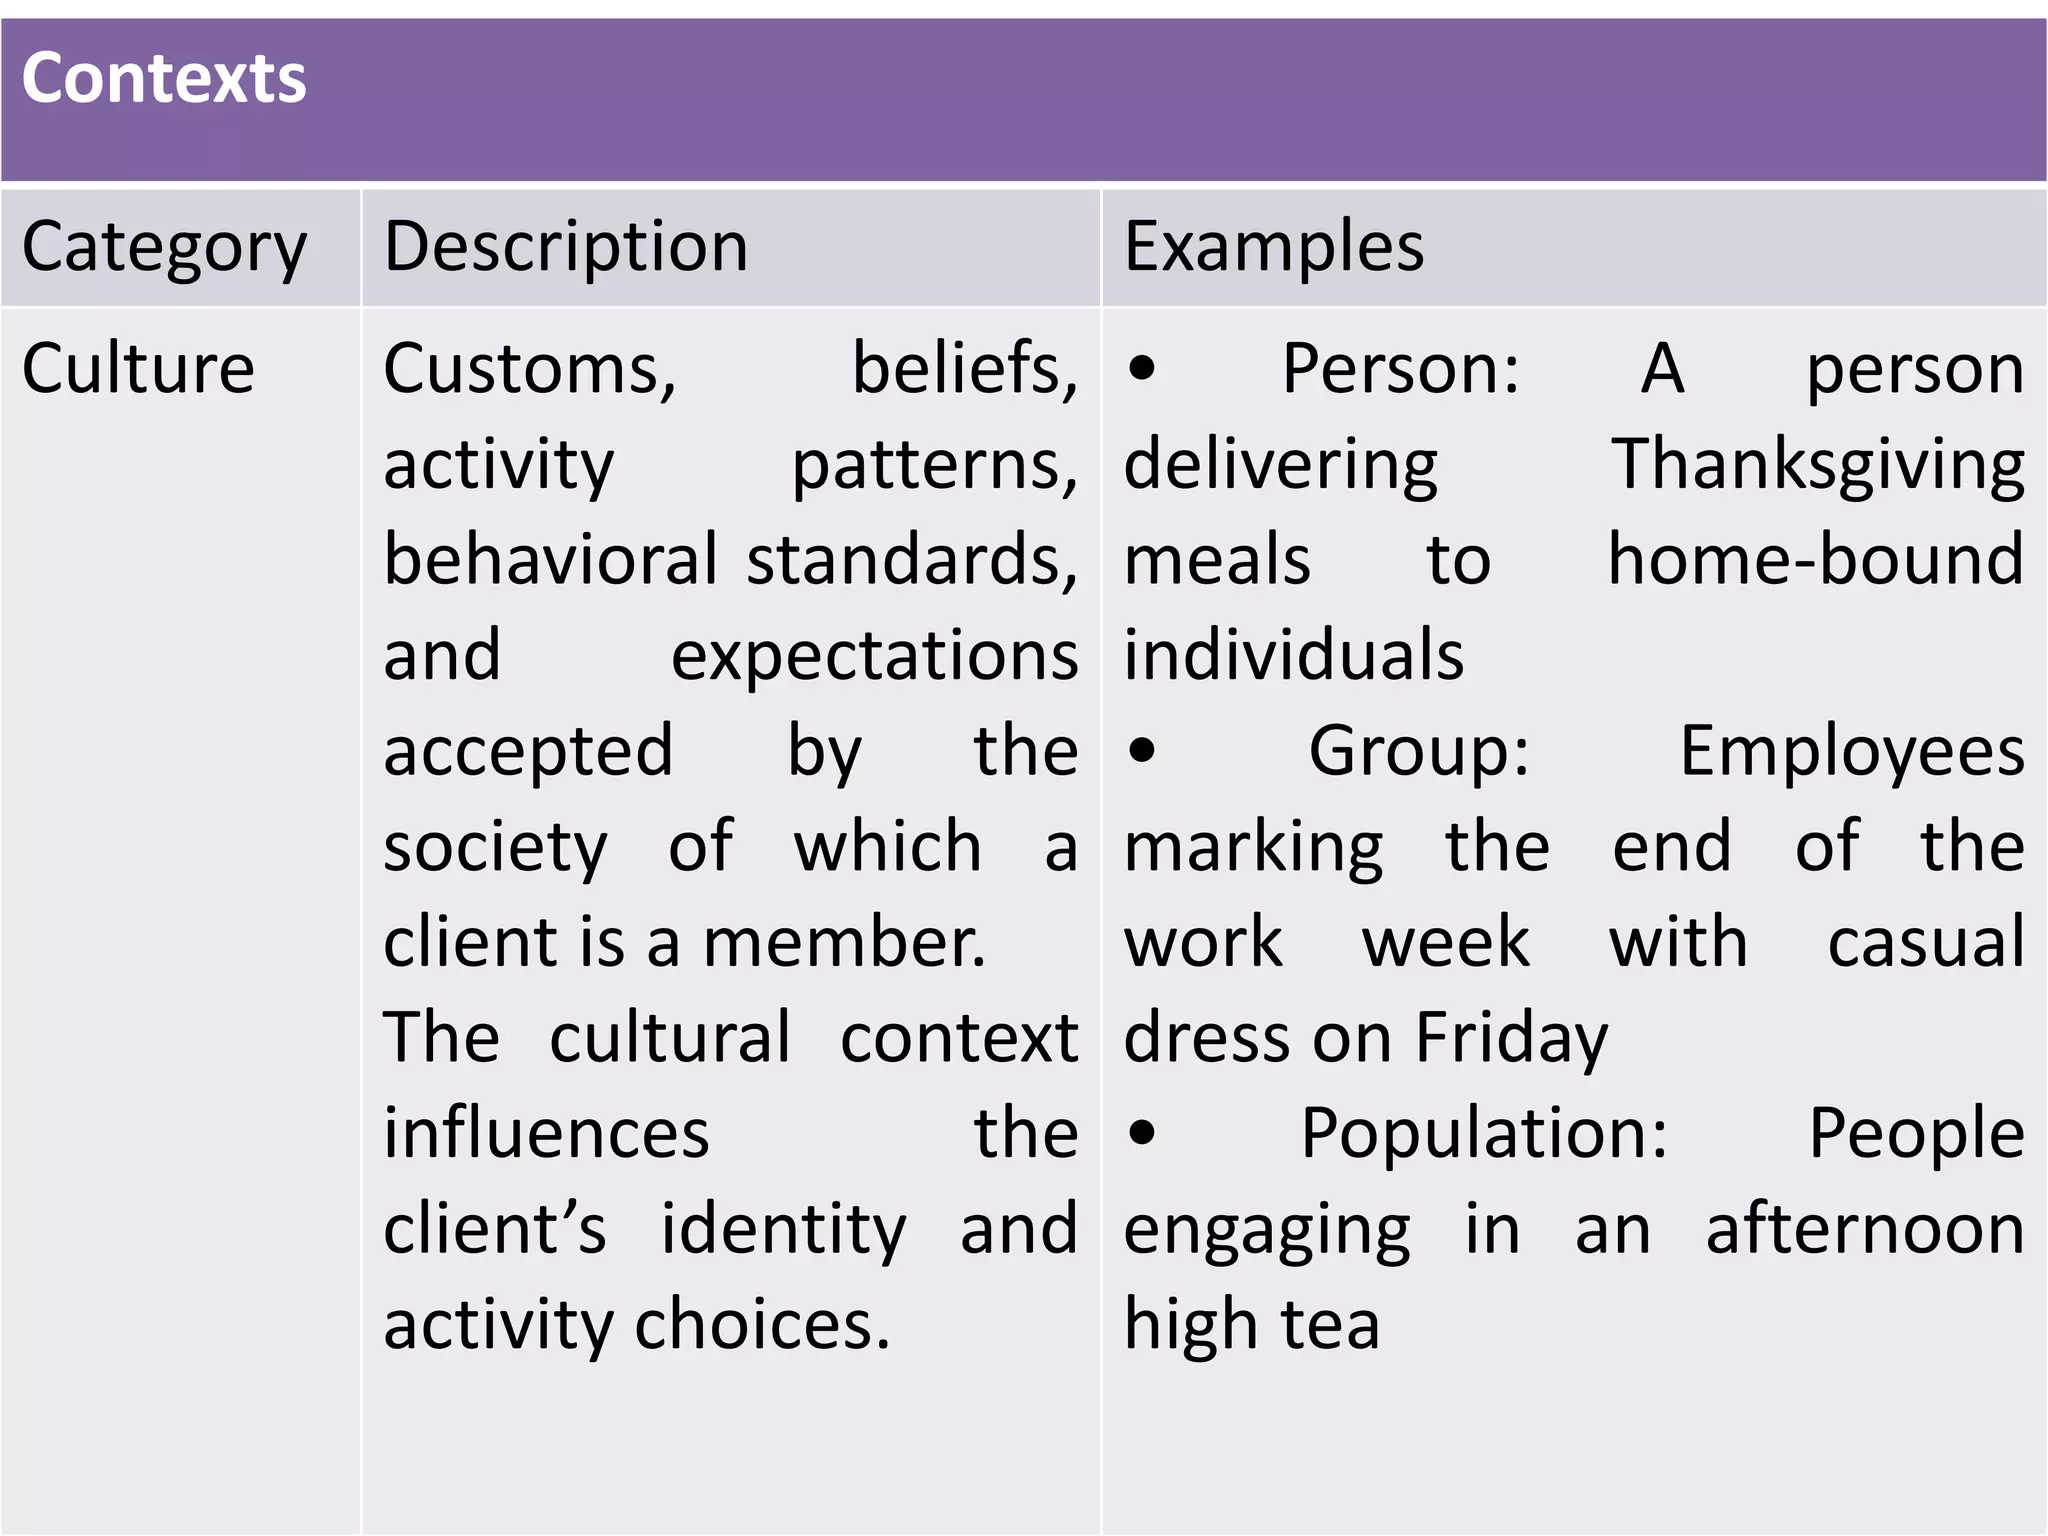
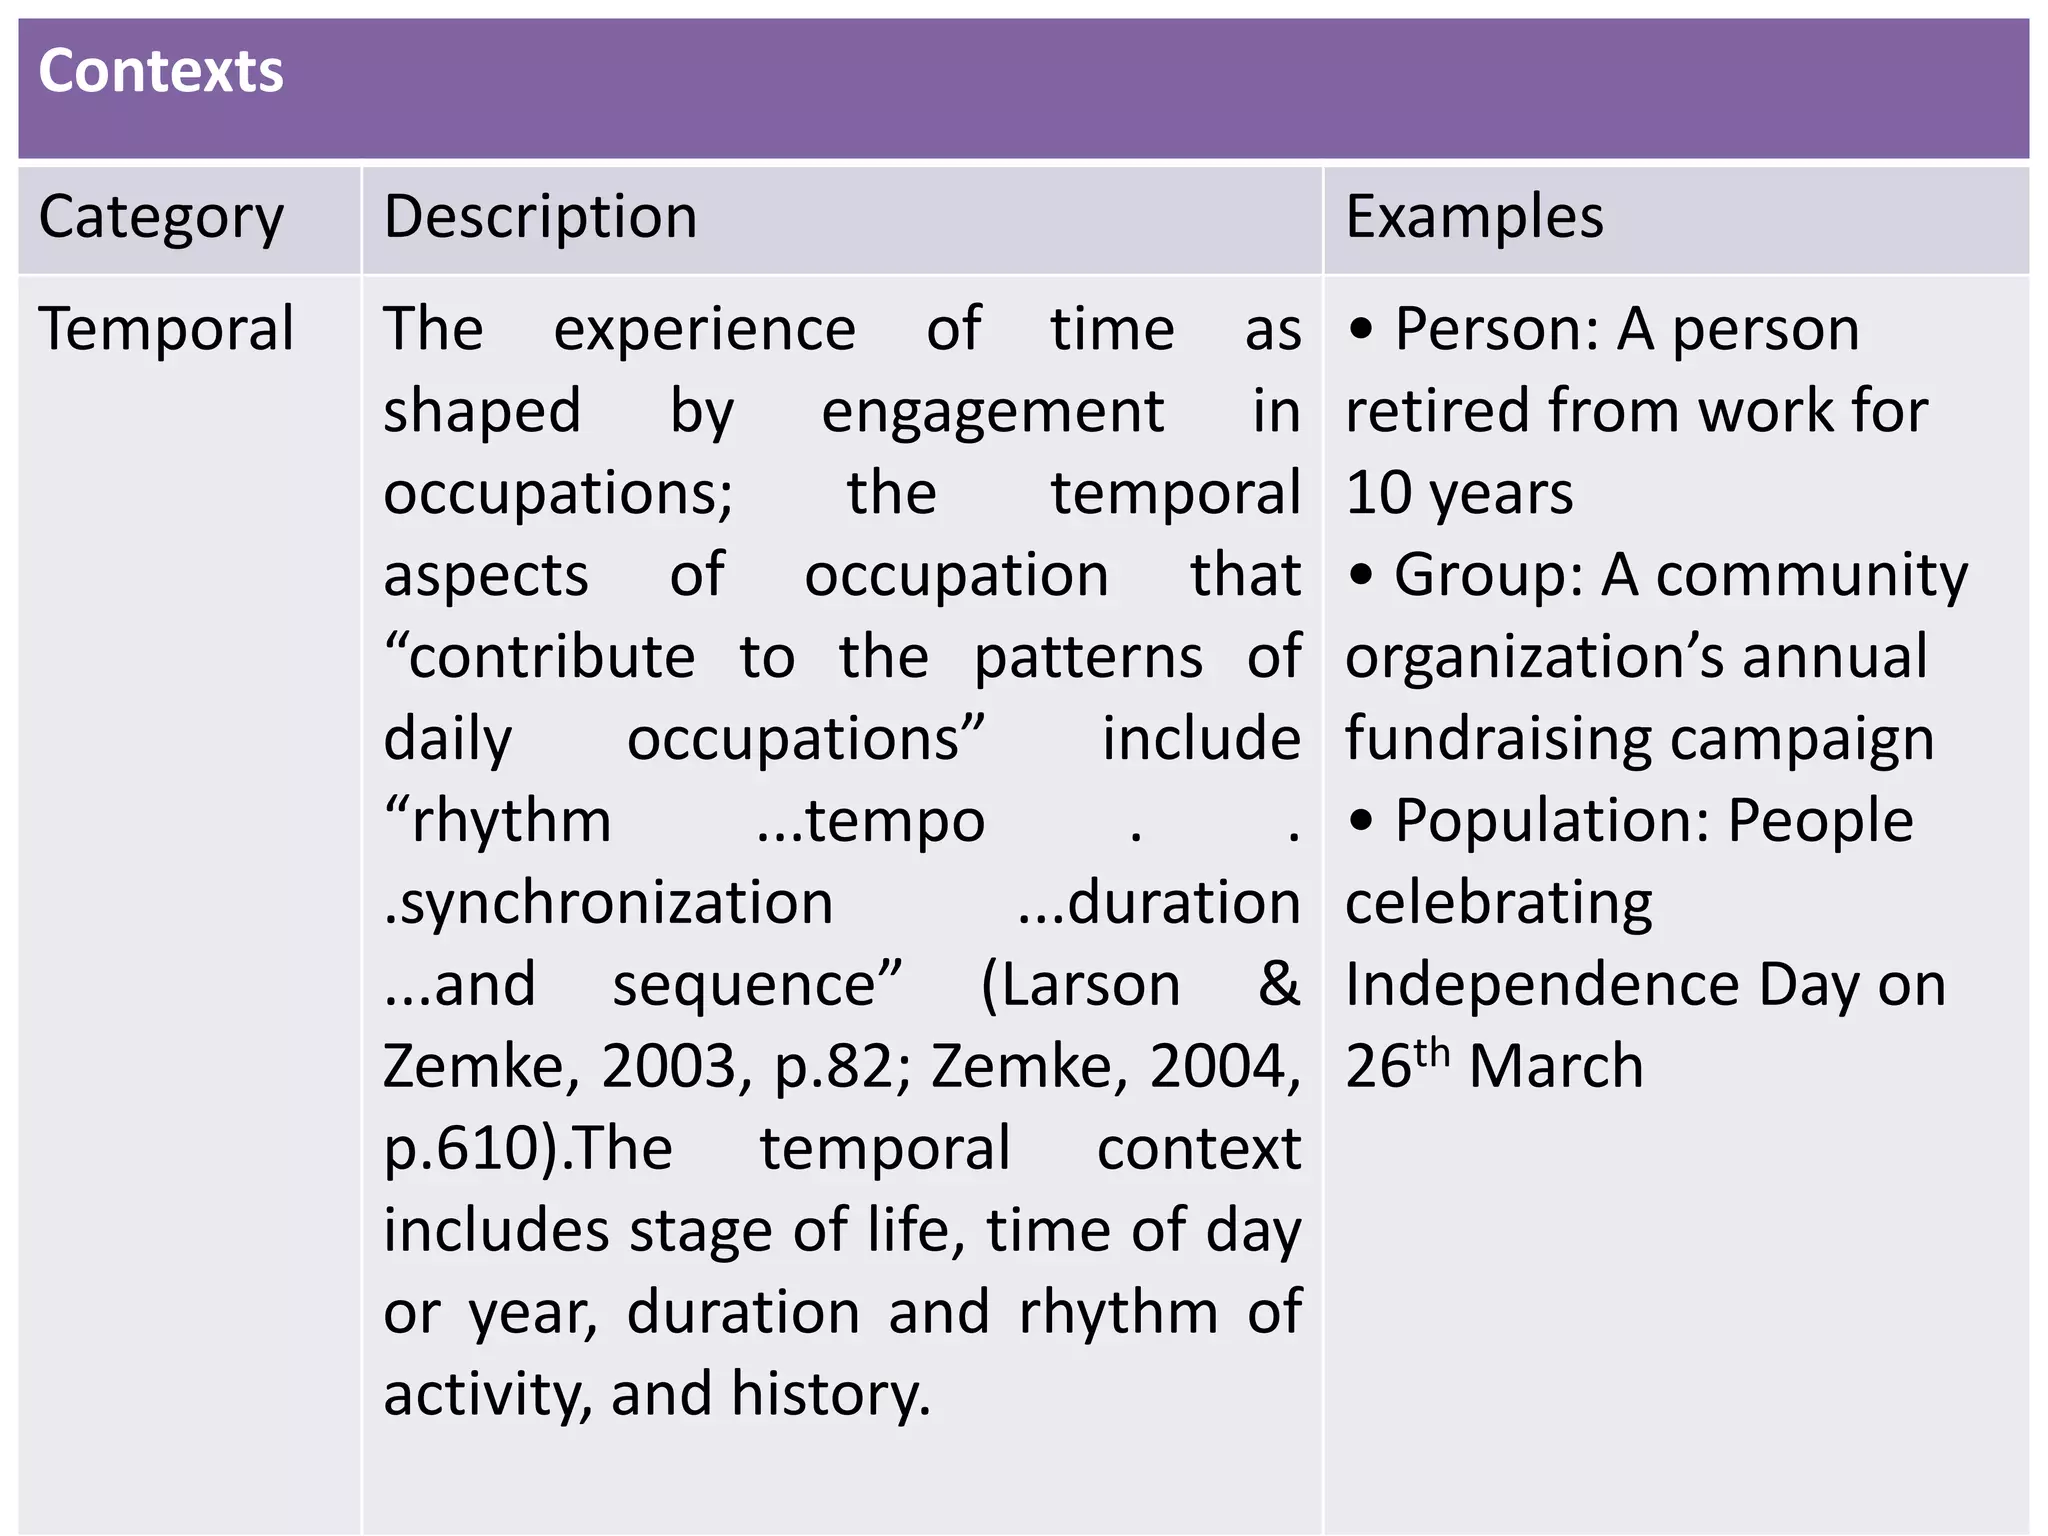
Most people don't think about how much of their day requires temporal sequencing until something breaks. A stroke survivor who can no longer make coffee without forgetting the kettle. An adult with ADHD who starts three tasks and finishes none. A person with early dementia who can hold a conversation but has no sense of whether they've been dressed for five minutes or fifty. This is where temporal context work actually lives. It is not glamorous. It is also not well-covered in textbooks. Temporal context in occupational therapy refers to how a person experiences, organizes, and manages time within their daily occupations. The client's relationship with time — their internal clock, their ability to sequence actions, their pacing, their awareness of duration — becomes a therapeutic target when neurological injury, cognitive decline, or developmental differences disrupt it. The framework comes out of models like MOHO and the CMOP-E, but most practitioners I know learn the real mechanics on the job because the literature is thin on practical methods.
What Temporal Context Occupational Therapy Actually Addresses
There are four sub-domains I find myself working with most often: Sequencing — the ability to order steps in a meaningful progression. Making breakfast requires knowing that you crack the egg after you get the pan, not before. Sequencing breakdowns show up early in TBI and frontal lobe injuries. Pacing — regulating the speed of activity over time. Someone who races through tasks and exhausts themselves, or someone who moves so slowly that meals take two hours. Pacing is huge in MS, fatigue syndromes, and anxiety-driven executive dysfunction.
Time estimation — the internal sense of how long something takes. Poor time estimation means chronic lateness, missed appointments, and inability to plan transitions. This is one of the most common complaints I see in adult ADHD assessments. Chronological awareness — understanding where you are in a daily or weekly cycle. Morning vs. evening routines, knowing what day it is, recognizing that afternoon is a different temporal zone than morning. Deterioration here is an early red flag in frontotemporal dementia. I ran into a specific case last year that exposed how messy this work actually is. I was working with a man in his early sixties recovering from a moderate TBI. Standard tools — the MoCA, the TBI-RA — said his executive functioning was "mildly impaired." But his wife reported that he could no longer independently manage his medication schedule. He would take his morning pills at night, sometimes skip them entirely, and once I found him with three doses stacked on the kitchen counter because he "lost track of which one he already took." The standardized measures completely missed this. They test sequencing in abstract problem-solving tasks, not in the messy temporal reality of a daily med routine with six different drugs at different times of day.
Get the Full Details
My workaround was to stop using paper charts and build a temporal scaffolding system using a digital timer with customizable audio cues tied to specific colored bins. Each medication got a color. The timer announced the color, not the drug name, and he matched the bin. This reduced errors from roughly once per day to zero over a six-week period. The insight here is that standardized assessment tools for temporal context are inadequate for real-world functional prediction. You need ecological testing — observing the person actually doing the task in their environment, or at least in a simulated version of it.
Assessing Temporal Context: What Actually Works
There is no single validated instrument that dominates this space. The Clock Drawing Test touches on it but is crude. The Behavioral Assessment of the Dysexutive Syndrome (BADS) includes a temporal component in its Park Route task, which is one of the better options available. The Timed Instrumental Activities of Daily Living (TIADL) scale gives you duration data but misses sequencing quality. The Ottawa Assessment of Daily Living Activities (OADLA) has a time management subscale that I find more useful in practice, though it still doesn't capture the full picture. Here is what I do instead of relying solely on any one tool. I use a combination of clinical interview, direct observation, and time-use sampling. The interview asks about daily rhythms, not just abilities. "Walk me through a typical weekday from when you wake up to when you go to sleep." You will learn more in twelve minutes of that conversation than you will from three separate standardized tests. Then I do a structured observation using a checklist that tracks initiation time, transition time between steps, errors in sequence, and total duration compared to a norm for that occupation. For clients who can self-monitor, I introduce time-use diaries for three consecutive days. The pattern data from those diaries is where the real treatment plan emerges. I should flag a limitation here that the literature glosses over: temporal context deficits often fluctuate dramatically throughout the day. A client who performs adequately at 10 AM may be completely non-functional by 3 PM due to cognitive fatigue, medication wearing off, or circadian dysregulation. Testing at a single time point gives you a false sense of competence. I now schedule assessments at least twice — once in the morning and once in the afternoon — and I flag this in every report I write. Insurance reviewers don't like it. It takes more time. It is necessary.
Intervention Strategies That Actually Move the Needle
The core approach is temporal retraining. This is not one technique but a family of strategies chosen based on where the breakdown occurs. Here is how I typically structure it. For sequencing deficits, I use task analysis paired with external cues. Break the occupation into discrete steps, then attach a cue to each step. The cue can be visual (a checklist with photos), auditory (a recorded script played in order), or tactile (placing items in the sequence physically on a tray before starting). The key detail most people miss is that the cue system must be faded systematically. If you leave the external supports in place forever, you create dependency without building internal temporal representation. I aim to remove one level of external support every two to three weeks while monitoring for error rates. If errors climb above 20%, I hold steady rather than pushing forward. For pacing problems, the go-to is interval training with biometric feedback. I use a simple heart rate monitor or even a smartphone app to track exertion during a target occupation. The client performs the task while watching their heart rate, learns what "too fast" feels like physiologically, and then practices modulating their pace to stay in a target zone. This works particularly well for conditions like MS and post-viral fatigue where pacing is the primary intervention. I have found this approach reduces reported fatigue scores by approximately 40% over eight weeks in my caseload, though I should note this is observational data, not controlled research.

For time estimation deficits, I use comparison training. The client estimates how long a task will take, does the task with a timer running, then compares their estimate to the actual duration. Over repeated trials, the gap between estimated and actual time narrows. This sounds simple but it is surprisingly effective for ADHD populations. The mechanism appears to be strengthening of the internal timing network in the basal ganglia and cerebellum through repeated calibration. I typically see meaningful improvement in estimation accuracy within four to six weeks of daily practice. For chronological awareness in neurological conditions, I rely on environmental structuring. This means aligning the physical environment to external time markers: light exposure schedules, meal timing anchored to clocks rather than hunger cues, activity blocks that are visually demarcated. For progressive conditions like dementia, the goal shifts from independence to safety and reduced agitation. Structured routines reduce sundowning episodes in approximately 60% of cases I have seen, though the effect diminishes as the disease progresses. One thing I want to be honest about: temporal context intervention has real bottlenecks. The biggest one is generalization. A client may master sequencing a morning routine in the clinic but fail completely at home. The second is caregiver burden. Most of these interventions require someone to set up and maintain external cue systems, which means training and sustaining a caregiver. The third is that temporal context deficits often co-occur with other impairments — memory, attention, motor planning — and untangling which intervention addresses which deficit is genuinely difficult. You will occasionally hit a wall where no temporal intervention helps because the primary barrier is something else entirely, usually severe working memory impairment. In those cases, the right move is to abandon temporal retraining and shift to compensatory environmental modification instead.
Tools and Resources for Temporal Context Occupational Therapy
I do not maintain a curated library of downloadable materials, and I would caution anyone who claims to have a single free resource that covers this comprehensively. The field simply does not produce open-access clinical toolkits at the volume that other OT specialties do. What I can point you toward are the instruments I reference above: the BADS for comprehensive executive assessment including temporal components, the OADLA for functional time management evaluation, and the TIADL for duration-based ADL assessment. University OT departments sometimes publish session guides under Creative Commons licenses — search terms like "temporal training occupational therapy pdf" will surface some of those. Commercial programs like the CAGI (Cognitive Assessment of Daily Living) include temporal modules but require purchase. For DIY cueing systems, I build my own from free tools: Google Calendar with color-coded blocks for clients who are tech-literate, and physical timer plus labeled containers for those who are not. The Theraband time timers with visual countdown disks are worth the investment if your clinic can afford them. I have used them for about five years and they reduce setup time for cueing interventions from roughly twenty minutes to about three per session. I should also note that if your primary concern is time estimation in ADHD, the CANTAB test battery has a palatine pause detection task that is more sensitive than anything available in a typical OT practice setting. Referring for neuropsychological testing when appropriate is a valid clinical decision, not a failure of your own intervention capacity.
When to Refer Out or Adjust Expectations
Temporal context work does not solve everything. There are scenarios where the prognosis is poor regardless of intervention intensity. Progressive neurodegenerative diseases are the clearest example — you can slow decline with structure and cueing, but you cannot restore lost temporal processing ability. In these cases, the goal shifts from rehabilitation to accommodation, and that is a different clinical posture that requires different skills. Another limitation: temporal context deficits in severe psychiatric conditions, particularly catatonia or active psychosis, often respond better to pharmacological stabilization first. Attempting temporal retraining during an acute psychiatric episode is generally ineffective and can increase client distress. I wait for stabilization before introducing any structured temporal intervention in those populations. The bottom line is that temporal context is one of those OT domains that sounds straightforward until you encounter the edge cases. The literature undersells how heterogeneous the presentations are and how much individual variation exists in treatment response. The work is iterative, often slow, and frequently requires you to abandon your initial assessment and rebuild your understanding of the problem mid-treatment. That is normal. It is also why I spend more time on clinical reasoning than on any specific technique when I train new OTs in this area.