What Actually Happens When You Test Cerebellar Function
Most medical students treat this as a rote checklist. Point at the nose, tap the foot, spin your fingers. They get the mechanics right and miss everything that matters. The cerebellum isn't just about coordination. It is about timing, prediction, and error correction during movement. When you understand that, the tests stop being trivia and start revealing real pathology. I learned this the hard way during my neurology rotation. A patient came in with what looked like normal finger-to-nose testing. Smooth, accurate, no overshoot. But when I asked him to do the test with his eyes closed, he started dysmetric. He was compensating visually for a subtle cerebellar sign that was invisible with visual feedback present. Most residents would have written that off as normal and moved on. That patient had early vitamin E deficiency affecting his spinocerebellar pathways. The visual compensation masked the deficit until you removed the crutch.
Tests Of Cerebellar Function That Actually Matter
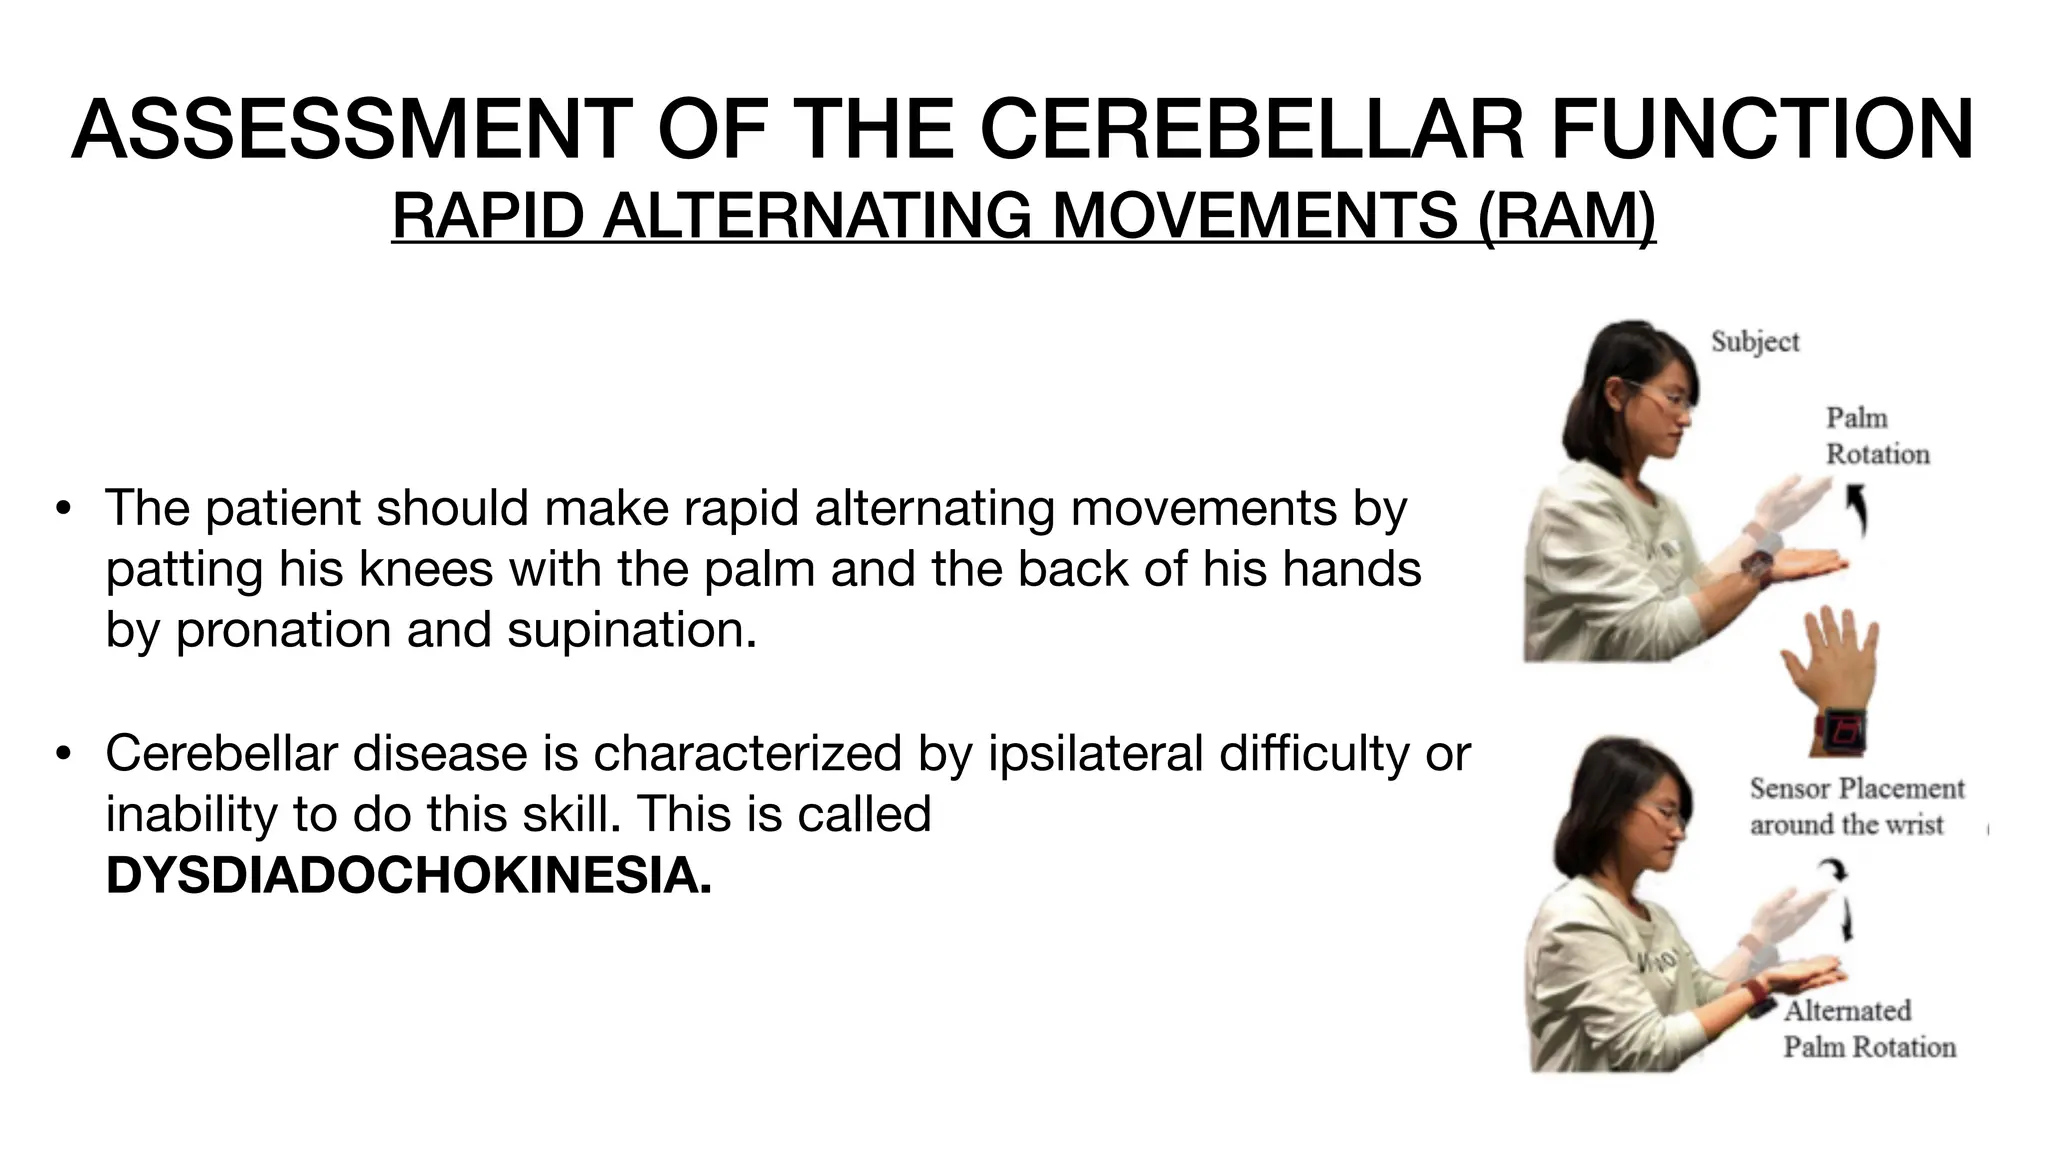
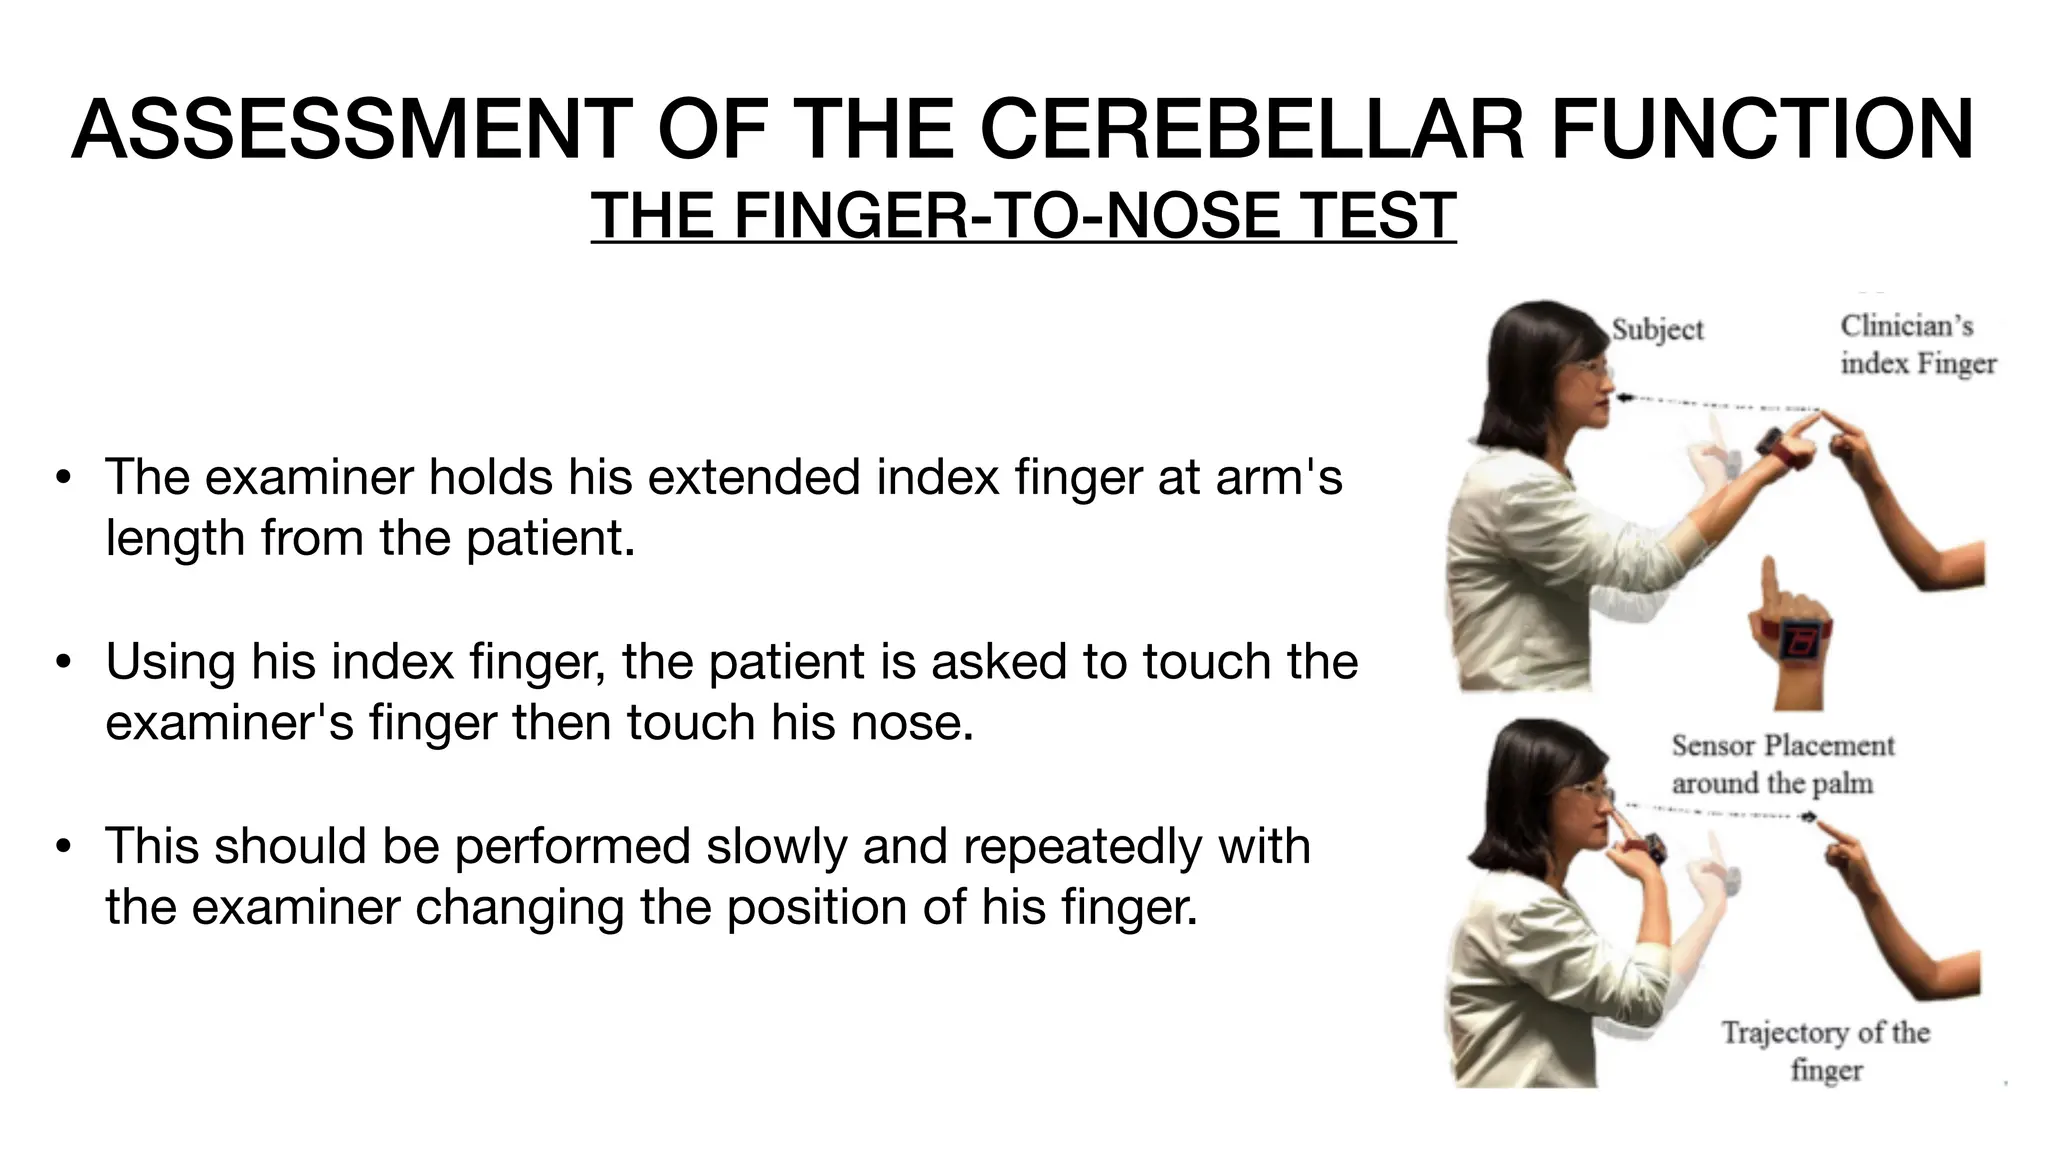
Start with the upper limbs because they reveal more than the lower limbs in most cases. The finger-to-nose test should be done at multiple velocities. Slow, then fast, then eyes closed. Watch for dysmetria — that's the overshoot or undershoot. Watch for intention tremor, which gets worse as the finger approaches the target. Intention tremor and resting tremor are completely different things. Resting tremor is basal ganglia. Intention tremor is cerebellar. Don't confuse them on the exam note. The rapid alternating movements test, also called pronation-supination, is where most cerebellar pathology shows up clearly. Ask the patient to flip their hands on their thigh quickly. Normal is smooth and rhythmic. Cerebellar dysfunction produces irregular, arrhythmic movements. The key word here is diadochokinesia. When it's impaired, it's called dysdiadochokinesia. Write that in the chart when you see it. It's specific enough to matter legally and clinically. Heel-to-shin testing evaluates the lower extremities. Have the patient place their heel on the opposite knee and slide it down the shin. Cerebellar ataxia makes this wobble or fall off. Again, do it with eyes open and eyes closed. Vestibular issues and proprioceptive loss change the results differently than pure cerebellar disease, so the comparison tells you something about localization.
Rebound phenomenon is one of the most underutilized tests in the cerebellar exam. Ask the patient to flex their elbow against your resistance, then abruptly remove your support. A normal person controls the limb and it doesn't slam into themselves. Someone with cerebellar dysfunction — specifically, someone with lesions on the same side as the tested limb — will fail to check the movement and their hand will hit their face. This tests for the loss of antagonistic muscle control. It's called impersistence of tone in the literature, but rebound is the clinical term everyone uses at the bedside. Testing the eyes is mandatory and frequently skipped. Look for nystagmus, particularly gaze-evoked nystagmus. Have the patient follow your finger through the six cardinal fields of gaze. Direction-changing nystagmus is central. Direction-fixed nystagmus that changes intensity is usually peripheral vestibular. This distinction separates a cerebellar stroke from an inner ear problem, and getting it wrong has serious consequences. Speech assessment is part of the cerebellar exam too. Cerebellar dysarthria is scanning speech — the kind where each syllable gets equal, hammer-like emphasis. "What-are-you-doing-tonight?" reads like a robot. Ask the patient to repeat a phrase while you watch their face and listen to the rhythm. Don't skip this. Some residents don't even mention speech in their notes and wonder why attendings flag incomplete exams.
Get the Full Details
Here's a practical problem I ran into multiple times. Patients with mild cerebellar signs often perform just well enough on standard testing to appear normal if you're not looking carefully. The workaround I use is adding speed and instability to the demands. Fast finger-to-nose. Finger-to-nose while the examiner rotates the patient's head side to side. Heel-to-shin while the patient is standing with feet together and eyes closed. Increasing the cognitive and postural load unmasks deficits that disappear under relaxed conditions. This is sometimes called the Fukuda stepping test principle applied to upper extremities — you're unmasking subclinical ataxia by removing compensatory mechanisms. A couple of counter-intuitive points that beginners miss. First, cerebellar signs are almost always ipsilateral. A lesion in the right cerebellar hemisphere affects the right side of the body. This is because the cerebellar output crosses twice — once within the cerebellum and once leaving it. So when you see dysmetria on the right hand, look at the right cerebellar hemisphere, not the left. Neurology students constantly map these wrong in their first year. Second, the cerebellum doesn't initiate movement. It refines it. This is why patients with cerebellar damage can still move normally at rest and even walk without assistance in mild cases. They just don't move well. The difference between "can walk" and "walks normally" is what the exam detects. If you're looking for paralysis, you'll miss cerebellar disease entirely.
Limitations worth acknowledging. The bedside cerebellar exam has poor sensitivity for early or mild disease. You need quantitative measures like finger tapping rate, grip force variability, or instrumental gait analysis to catch subtle dysfunction. A normal bedside exam does not rule out cerebellar pathology. MRI and neurological consultation are necessary when clinical suspicion is high despite a normal exam. Also, the test is operator-dependent. Two clinicians can give different grades for the same patient's coordination depending on how firmly they apply the rebound test or how quickly they ask for rapid alternating movements. For documentation purposes, use a standardized scale. The Scaled Assessment for Ataxia (SARA) and the International Cooperative Ataxia Rating Scale (ICARS) both provide structured scoring across multiple domains. Neither is perfect, but they're better than writing "coordination intact" and leaving it at that. If you're doing research or following a patient over time, these scales reduce inter-rater variability significantly compared to free-text descriptions. The cerebellar exam takes roughly three to five minutes if you know what you're doing. Budget more time if the patient has significant ataxia and needs to rest between tests. The whole battery — upper limbs, lower limbs, eye movements, speech, gait, station — is complete in that window. Anything longer means you're probably testing something repeatedly without adding new information, or the patient has severe dysfunction that requires frequent breaks.