Understanding Thalamus And Hypothalamus Function in Real Clinical Practice
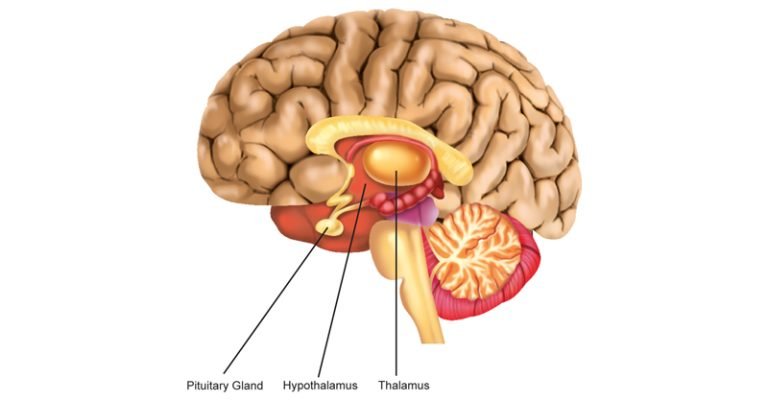
Most people learn about the thalamus and hypothalamus as separate structures in a textbook diagram, but they rarely work alone. When you actually look at patient cases involving these regions, their functions overlap in ways that make localization tricky even for experienced clinicians. The thalamus routes sensory information to the cortex, while the hypothalamus handles autonomic and endocrine regulation. Together they form a circuit that can produce confusing symptom patterns if either piece is damaged. I spent years working with neurology patients who presented with what initially looked like unrelated complaints. One case stands out. A patient came in with chronic insomnia, unexplained temperature dysregulation, and intermittent confusion. The MRI showed a small lesion near the third ventricle. At first glance it could have been misattributed to just one region. But the symptom combination pointed squarely at the interaction between thalamic relay nuclei and hypothalamic centers. Treating only one aspect of that connection would have left the patient cycling through unresolved symptoms for months.
Thalamus And Hypothalamus Function: What Actually Happens Under the Surface
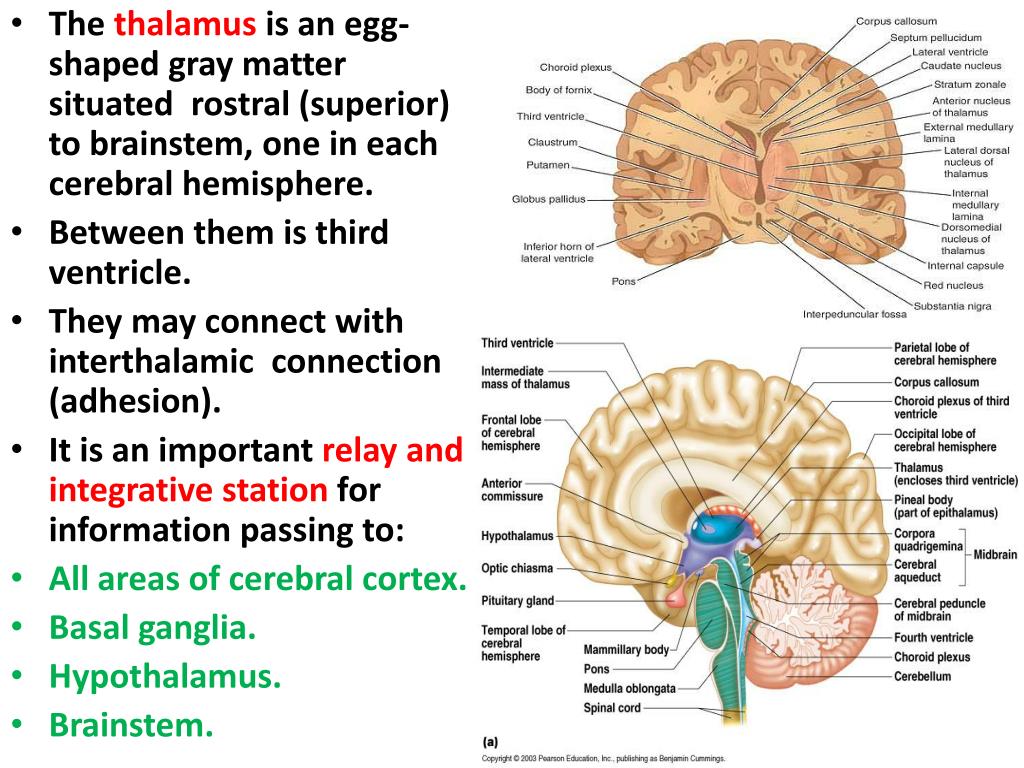
The thalamus contains multiple nuclei, each with a distinct role. The lateral geniculate nucleus handles visual relay. The ventral posterior nucleus processes somatosensory input. The anterior thalamic nuclei connect to limbic structures. These are not abstract categories. When you see a patient with combined sensory and cognitive complaints, the pattern of deficits can help you map which nuclear groups are involved. The ventral lateral and ventral anterior nuclei feed into motor cortex circuits. Damage here produces movement issues that look like Parkinsonian symptoms but respond differently to treatment. The hypothalamus operates on a completely different timescale. It does not process information in milliseconds like cortical circuits. It regulates hormonal release, body temperature, hunger signals, and circadian rhythms. The suprachiasmatic nucleus receives direct input from the retina and sets the master clock. The paraventricular and supraoptic nuclei produce oxytocin and vasopressin. The arcuate nucleus modulates appetite through neuropeptide Y and pro-opiomelanocortin pathways. When these systems malfunction, the effects are systemic and slow-moving. That is why hypothalamic disorders are often diagnosed late. There is a common misconception that the thalamus is simply a relay station. It is not. Modern research shows the thalamus participates in cortical feedback loops and modulates attention and consciousness states. The intralaminar nuclei, for example, are involved in arousal and pain modulation. Lesions here can produce prolonged unconsciousness that does not correlate with obvious structural damage elsewhere. Similarly, the hypothalamus is not just a plumbing system for hormones. It integrates neural and endocrine signals continuously, adjusting pituitary output based on real-time physiological feedback. This bidirectional relationship means dysfunction in one area almost always creates secondary effects in the other.
One thing I wish more trainees understood is that hypothalamic-pituitary axes do not operate in isolation. The suprachiasmatic nucleus projects to the paraventricular nucleus, which then influences corticotropin-releasing hormone release. Stress responses involve the thalamus routing nociceptive and emotional signals to both the hypothalamus and cortical areas simultaneously. A patient presenting with chronic stress symptoms may actually have a thalamic processing issue that cascades into hypothalamic dysregulation. Standard hormone panels often come back normal because the problem is not in the gland itself. It is in the signaling pathway.
Get the Full Details
Practical Approach to Evaluating Thalamus And Hypothalamus Function
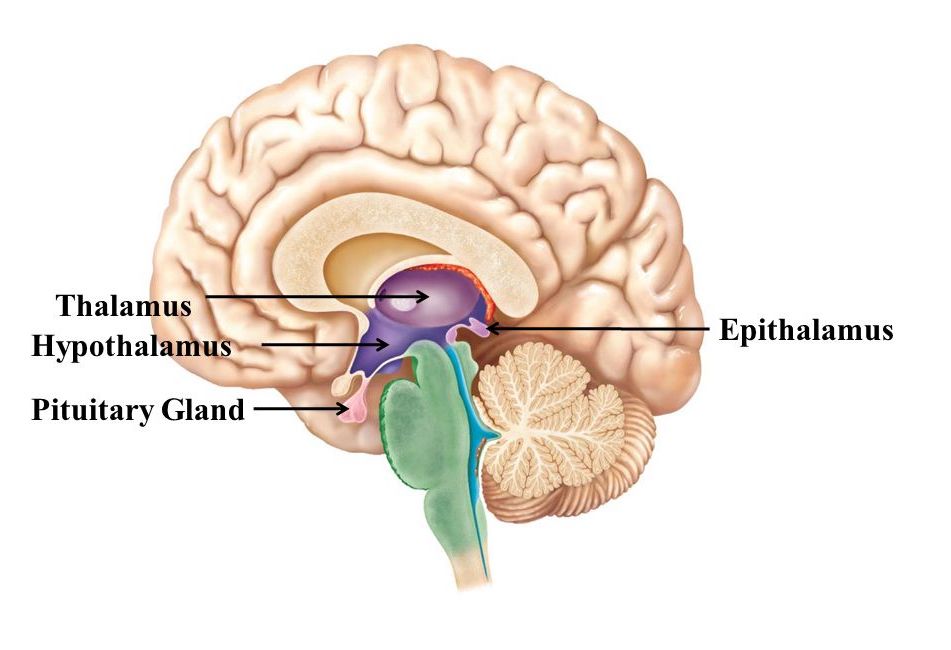
When you are assessing these structures clinically, start with a detailed symptom history before ordering imaging. Write down the timeline. Note whether symptoms fluctuate with circadian patterns, stress levels, or meals. The hypothalamus governs these rhythms, so temporal patterns in symptoms are diagnostically useful. Patients who report worse symptoms in the early morning versus evening can point toward specific hypothalamic nuclei involvement. Thalamic symptoms often present with sensory disturbances that follow dermatomal or cortical mapping patterns rather than peripheral nerve distributions. Blood work should include a full pituitary panel: cortisol, ACTH, TSH, free T4, FSH, LH, prolactin, IGF-1, and sodium levels. Hyponatremia is a frequent finding in hypothalamic dysfunction due to impaired vasopressin regulation. Do not skip the sodium check. I have seen cases where electrolyte imbalance was treated as an isolated issue when it was actually the presenting sign of a hypothalamic lesion. MRI of the brain with hypothalamic-pituitary protocol is the standard imaging approach. Use thin slices through the sellar region. Contrast enhancement helps identify lesions that might be missed on non-contrast scans. However, imaging has limitations. Small gliomas, microadenomas, and inflammatory changes can be subtle. A normal scan does not rule out functional disruption. In those cases, functional imaging like PET or specialized fMRI sequences may provide additional information about metabolic activity in thalamic nuclei and hypothalamic regions.
Treatment depends entirely on the underlying cause. If a tumor is compressing these structures, surgical or radiation intervention addresses the mechanical problem. If the issue is functional, such as in cases of insomnia or temperature dysregulation without structural damage, management focuses on symptom control. Melatonin receptor agonists can help with circadian rhythm disorders linked to suprachiasmatic dysfunction. Temperature regulation issues may require environmental modifications and medications like bromocriptine in some cases. Thyroid and adrenal axis replacement is straightforward when hormone deficiency is confirmed.
Limitations and When Standard Approaches Fall Short
Here is the part that is not always covered in training materials. The thalamus and hypothalamus can be affected by conditions that do not show up on routine MRI. Autoimmune encephalitis, particularly anti-NMDA receptor encephalitis, can target these regions and present with psychiatric symptoms before any neurological signs appear. Multiple sclerosis plaques in the periventricular white matter can disrupt thalamo-hypothalamic connections without producing obvious mass effect. Metabolic disorders like Wernicke's encephalopathy affect the mammillary bodies and thalamic nuclei, but early stages may only show subtle clinical findings. Another issue is that many symptoms of thalamic and hypothalamic dysfunction overlap with more common conditions. Insomnia is frequently attributed to stress or primary sleep disorders. Appetite changes are often labeled as eating disorders or depression. Temperature intolerance gets dismissed as autonomic dysfunction without deeper investigation. The diagnostic delay is real. In my experience, the average time from symptom onset to correct diagnosis for hypothalamic disorders is several months, sometimes years. The thalamus is even more challenging because isolated thalamic strokes can present with mixed motor and sensory symptoms that resemble other neurological conditions. When standard treatment approaches fail, consider referring to a center with expertise in neuroendocrinology or functional neurosurgery. Deep brain stimulation has been explored for certain thalamic disorders, though it is not a first-line treatment. For hypothalamic obesity, which can occur after damage to the ventromedial nucleus, traditional weight loss interventions are largely ineffective. Medications like setmelanotide have shown promise in specific genetic forms of hypothalamic obesity, but access is limited and the cost is significant.

The bottom line is that these structures are deceptively simple in textbooks and genuinely complex in practice. They sit at the intersection of neural and endocrine systems, and dysfunction here affects nearly every aspect of physiology. If you are working with patients who have unexplained multi-system symptoms, keeping thalamus and hypothalamus involvement on your differential list is worth the effort. The diagnostic workup requires patience and a willingness to look beyond the obvious. The payoff is catching conditions that would otherwise be missed until significant damage has occurred.