Understanding Brain Lobes: A Practical Guide
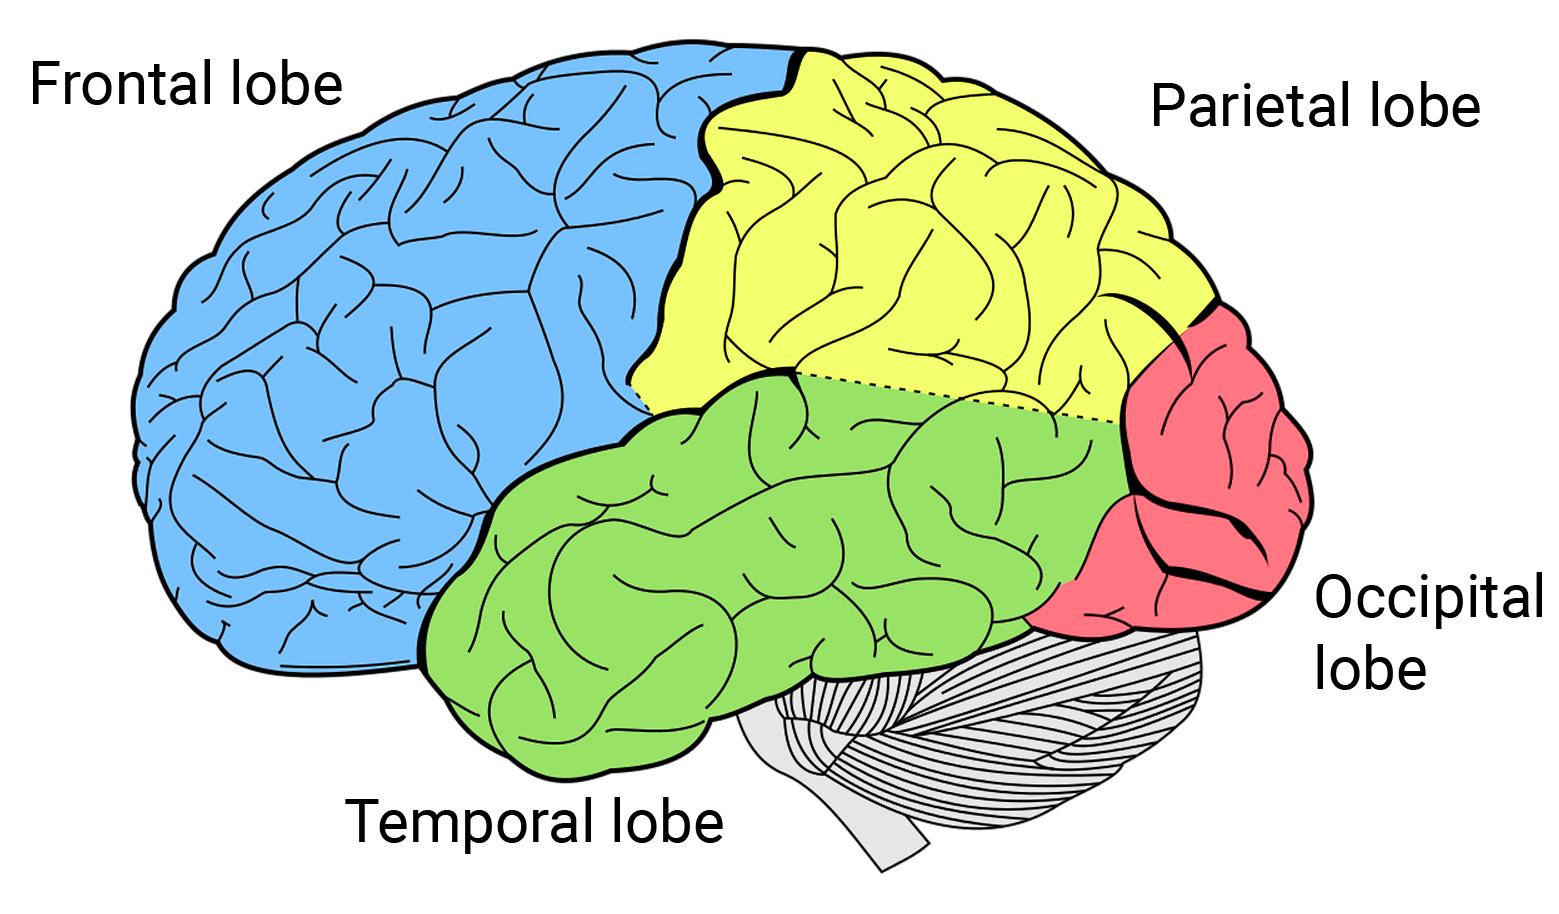
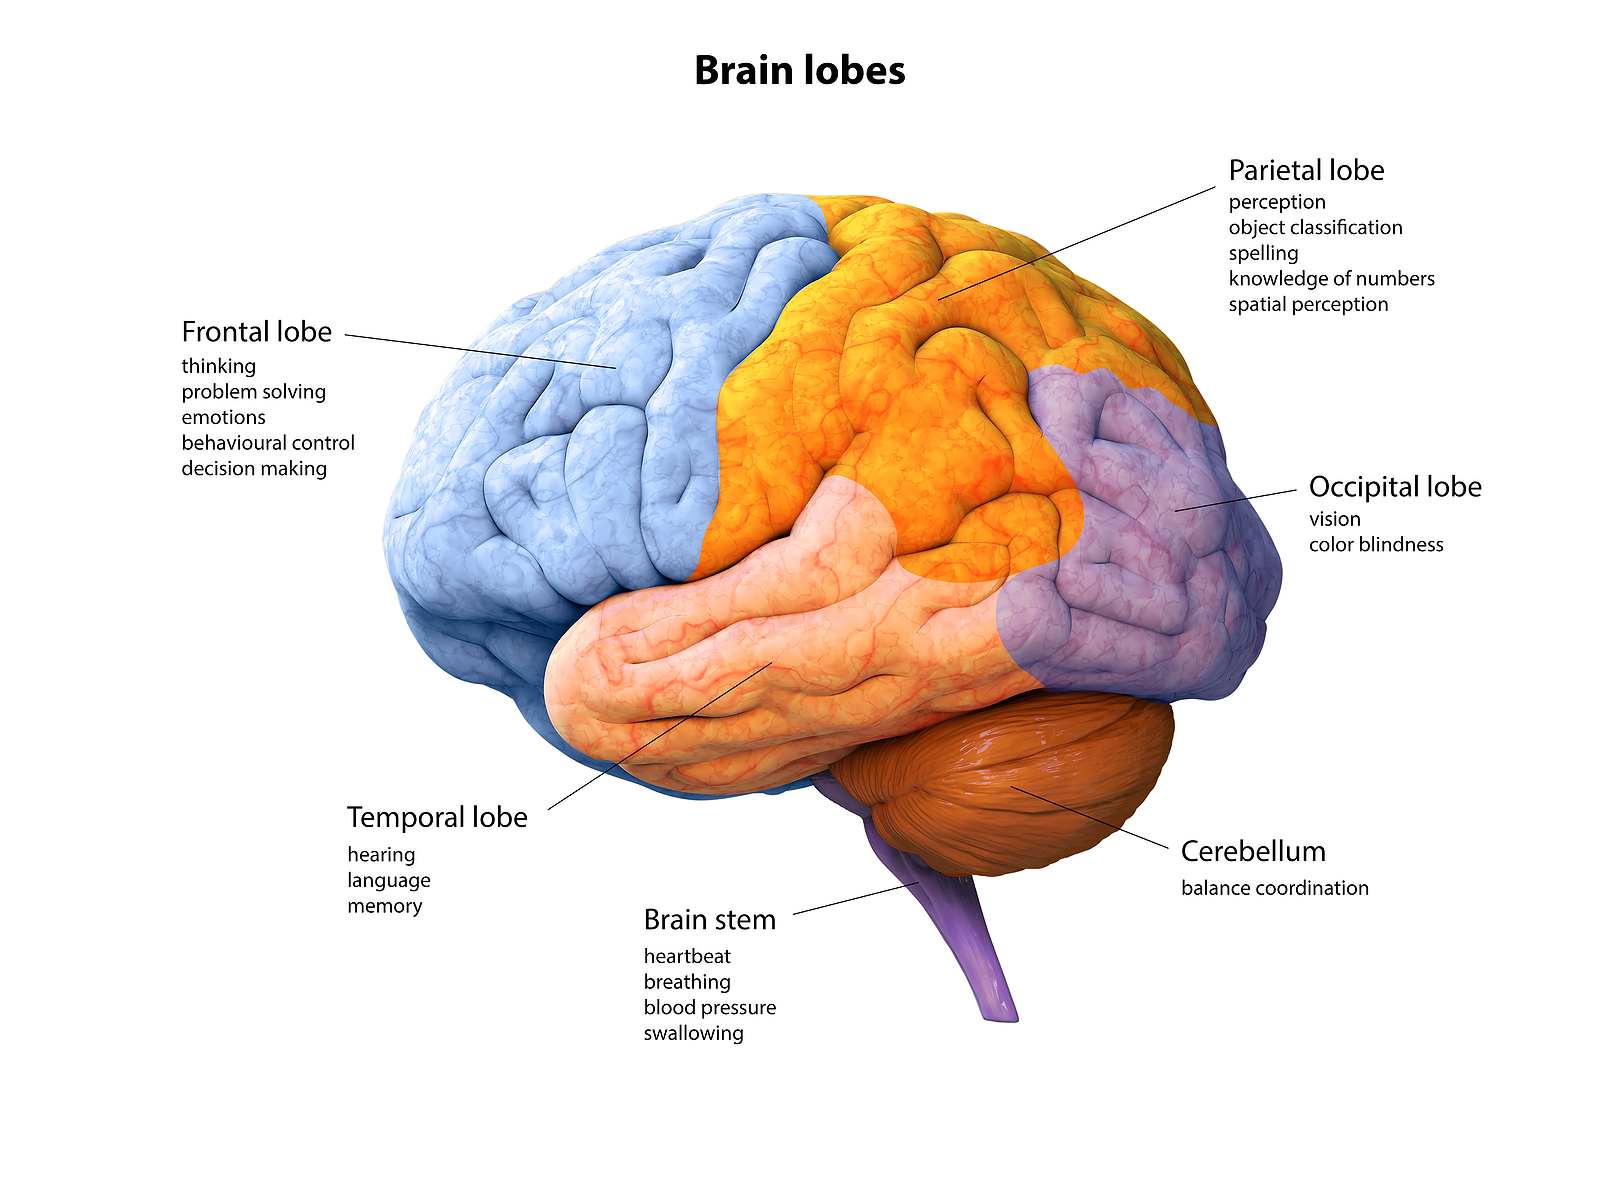
The four lobes of the brain are anatomical regions divided by prominent sulci. The frontal lobe sits behind the forehead and extends to the central sulcus. The parietal lobe lies above the temporal lobe and behind the frontal lobe. The temporal lobe rests below the lateral sulcus, and the occipital lobe occupies the posterior cranial fossa. That is the basic neuroanatomy you will find in any textbook. The question is what each region actually does when things go wrong. The frontal lobe houses the primary motor cortex, premotor areas, and prefrontal cortex. Broca's area sits in the left inferior frontal gyrus for most right-handed people. Damage here causes expressive aphasia, which is the inability to produce fluent speech despite preserved comprehension. The prefrontal cortex handles executive function, working memory, and social behavior regulation. Lesions in the dorsolateral prefrontal cortex create planning deficits. Ventromedial damage produces personality changes and poor impulse control. Phineas Gage is the textbook example, but you do not need a railroad spike to see frontal lobe syndromes. I have evaluated patients with small frontal lesions who scored within normal ranges on standard cognitive screens. The tests did not catch the problem. A 54-year-old with a right dorsolateral prefrontal infarct passed language and memory assessments but could not organize a multi-step work task. His wife reported he started cooking and forgot about it entirely. He would leave the stove on. This is the classic dysexecutive syndrome, and it shows up after stroke, traumatic brain injury, or neurodegeneration. Standard cognitive screening tools miss it because they are designed for global cognition, not executive function. You need trail making test part B, verbal fluency tasks, and behavioral observation to detect it. Informant reports are essential. The patient often lacks insight into their own deficits.
The frontal lobe also contains the supplementary motor area and the cingulate motor regions. These areas coordinate sequences of movement. Patients with supplementary motor area damage have difficulty initiating voluntary movement despite intact muscle strength. They can walk with external cues like metronome pacing, but cannot initiate steps independently. This is distinct from Parkinsonian bradykinesia, though the presentation can look similar to an untrained observer.
Parietal Lobe Function and Spatial Neglect
The parietal lobe integrates sensory information and constructs spatial representations. The primary somatosensory cortex occupies the postcentral gyrus. Damage produces contralateral sensory loss, but the clinically significant findings go beyond simple numbness. The inferior parietal lobule, particularly the angular gyrus and supramarginal gyrus, supports language processing, arithmetic, and body schema. Right parietal damage causes hemispatial neglect, where patients ignore the left side of space. This is not visual field loss. The eyes work fine. The attention system fails to orient toward stimuli on one side. I encountered a patient with a right middle cerebral artery stroke who could read text normally except for words on the left page. He would start reading from the right margin and skip entire lines. He denied any problem. This was extinction rather than blindness. When I touched both sides simultaneously, he only felt the right side. Single stimulation on the left was detected. This distinction matters because rehabilitation strategies differ. Neglect patients benefit from limb activation training and prism adaptation therapy. Simple visual field exercises do not address the attentional deficit. Alexia without agraphia occurs with left occipital and splenium lesions. Patients cannot read but can write. The visual information reaches the left hemisphere through the right hemisphere and corpus callosum, but the connection between visual cortex and language areas is disrupted. This is a localization puzzle that requires understanding white matter pathways, not just cortical anatomy.
Get the Full Details
Temporal Lobe: Memory, Language, and Seizures
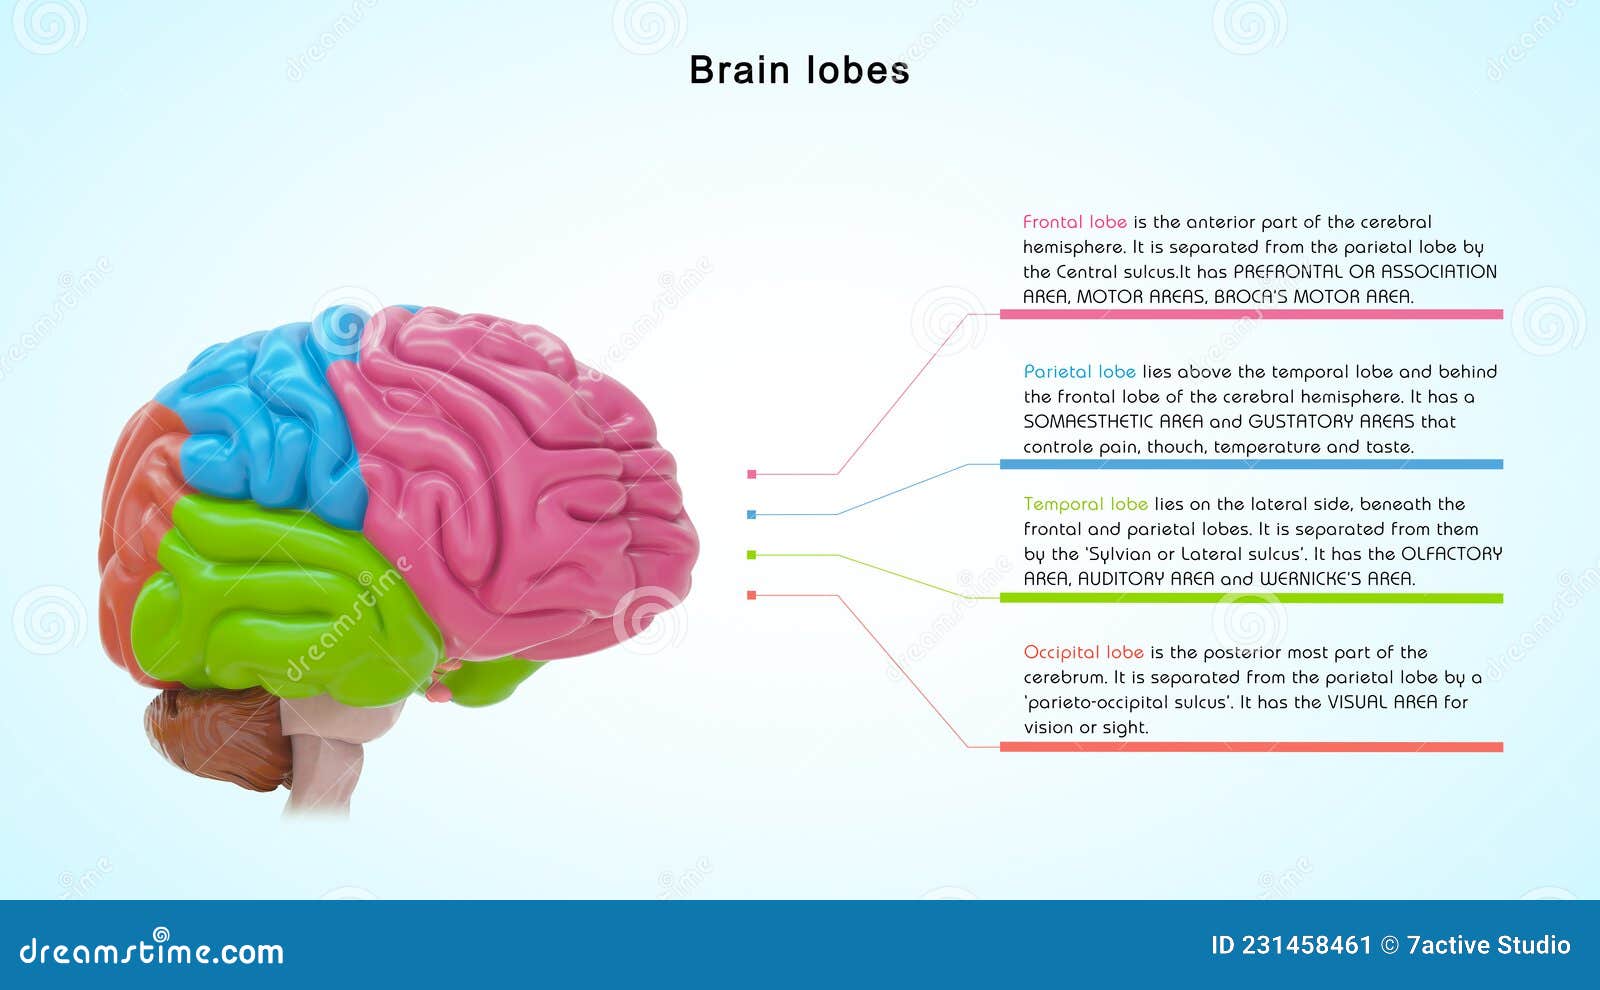
The temporal lobe processes auditory information in the primary auditory cortex and complex sounds in association areas. Wernicke's area in the left superior temporal gyrus supports language comprehension. Damage here causes receptive aphasia, where speech is fluent but meaningless. Patients produce word salads and cannot understand others. The hippocampus and adjacent medial temporal structures consolidate declarative memory. Bilateral medial temporal damage produces anterograde amnesia. Patient H.M. is the famous case, but temporary hippocampal dysfunction occurs with seizures, encephalitis, and hypoxia. Temporal lobe epilepsy presents with aural hallucinations, déjà vu, rising epigastric sensations, and automatisms. The seizure focus is often in the mesial temporal structures. ictal fear is a common aura. Patients describe an overwhelming sense of dread without external cause. This distinguishes temporal lobe seizures from panic attacks, though differential diagnosis requires EEG confirmation. Interictal personality changes, including hyposexuality and hypergraphia, were described in Geschwind syndrome, though the clinical significance remains debated. I worked with a patient whose temporal lobe seizures were misdiagnosed as psychiatric episodes for three years. He experienced episodes of intense anxiety with autobiographic memory fragmentation. MRI showed mesial temporal sclerosis. The seizures were subtle, with no convulsive activity. Only prolonged video-EEG monitoring captured the ictal pattern. This case illustrates why temporal lobe pathology is frequently missed. The symptoms overlap with anxiety disorders, dissociative conditions, and transient ischemic attacks. Clinicians should consider epileptic phenomena when episodic symptoms lack a clear structural or vascular explanation.
Occipital Lobe and Visual Processing
The occipital lobe contains the primary visual cortex and higher visual areas. Lesions produce contralateral visual field defects. Homonymous hemianopia results from post-chiasmal damage. Macular sparing occurs with occipital lesions because the pole of the calcarine cortex receives dual blood supply from posterior cerebral and middle cerebral arteries. Visual agnosias arise from bilateral occipitotemporal damage. Patients can see but cannot recognize objects. They describe visual features without semantic access. Cerebral achromatopsia follows bilateral ventral occipitotemporal lesions. Patients see the world in grayscale. The eyes and retina function normally. The visual cortex loses color processing capacity. This condition is rare but provides evidence for specialized neural pathways. Color perception requires intact v4 and adjacent regions in the lingual and fusiform gyri. Stroke affecting the posterior choroidal arteries can produce this deficit. Occipital lobe seizures generate simple visual phenomena: phosphenes, colored circles, geometric patterns. Complex formed visuals suggest temporal or parietal involvement. Localization based on ictal semiology alone is unreliable but provides useful clues when combined with EEG and imaging findings.
Assessment Approaches and Clinical Pearls
Evaluating lobe function requires more than observing reflexes and strength. Specific tests target regional capabilities. For frontal lobe assessment, use the stroop test, verbal fluency measures, and frontals assessment battery. The delis kaplan memory test includes frontal lobe sensitive indices. For parietal lobe function, test Constructional praxis, finger agnosia, and right-left discrimination. Ideomotor apraxia suggests parietal involvement. Temporal lobe evaluation requires language comprehension testing and memory assessments. The WAIS working memory indices are sensitive to frontal and temporal dysfunction. Neuroimaging reveals structural lesions, but functional assessment requires clinical examination. MRI protocols should include T2 FLAIR sequences for temporal lobe epilepsy evaluation. High resolution temporal lobe protocols with thin cuts through the mesial structures improve detection of hippocampal sclerosis. Functional imaging with PET or SPECT during interictal periods shows temporal hypometabolism in epilepsy patients. Ictal SPECT localizes seizure onset with greater accuracy. The four lobes of the brain do not operate in isolation. White matter tracts connect regions into networks. The arcuate fasciculus links frontal and temporal language areas. Damage along this pathway produces conduction aphasia with preserved comprehension and fluency but impaired repetition. The superior longitudinal fasciculus connects parietal and frontal regions for sensorimotor integration. Disconnection syndromes demonstrate that lobe-based models are simplified representations of distributed processing systems.
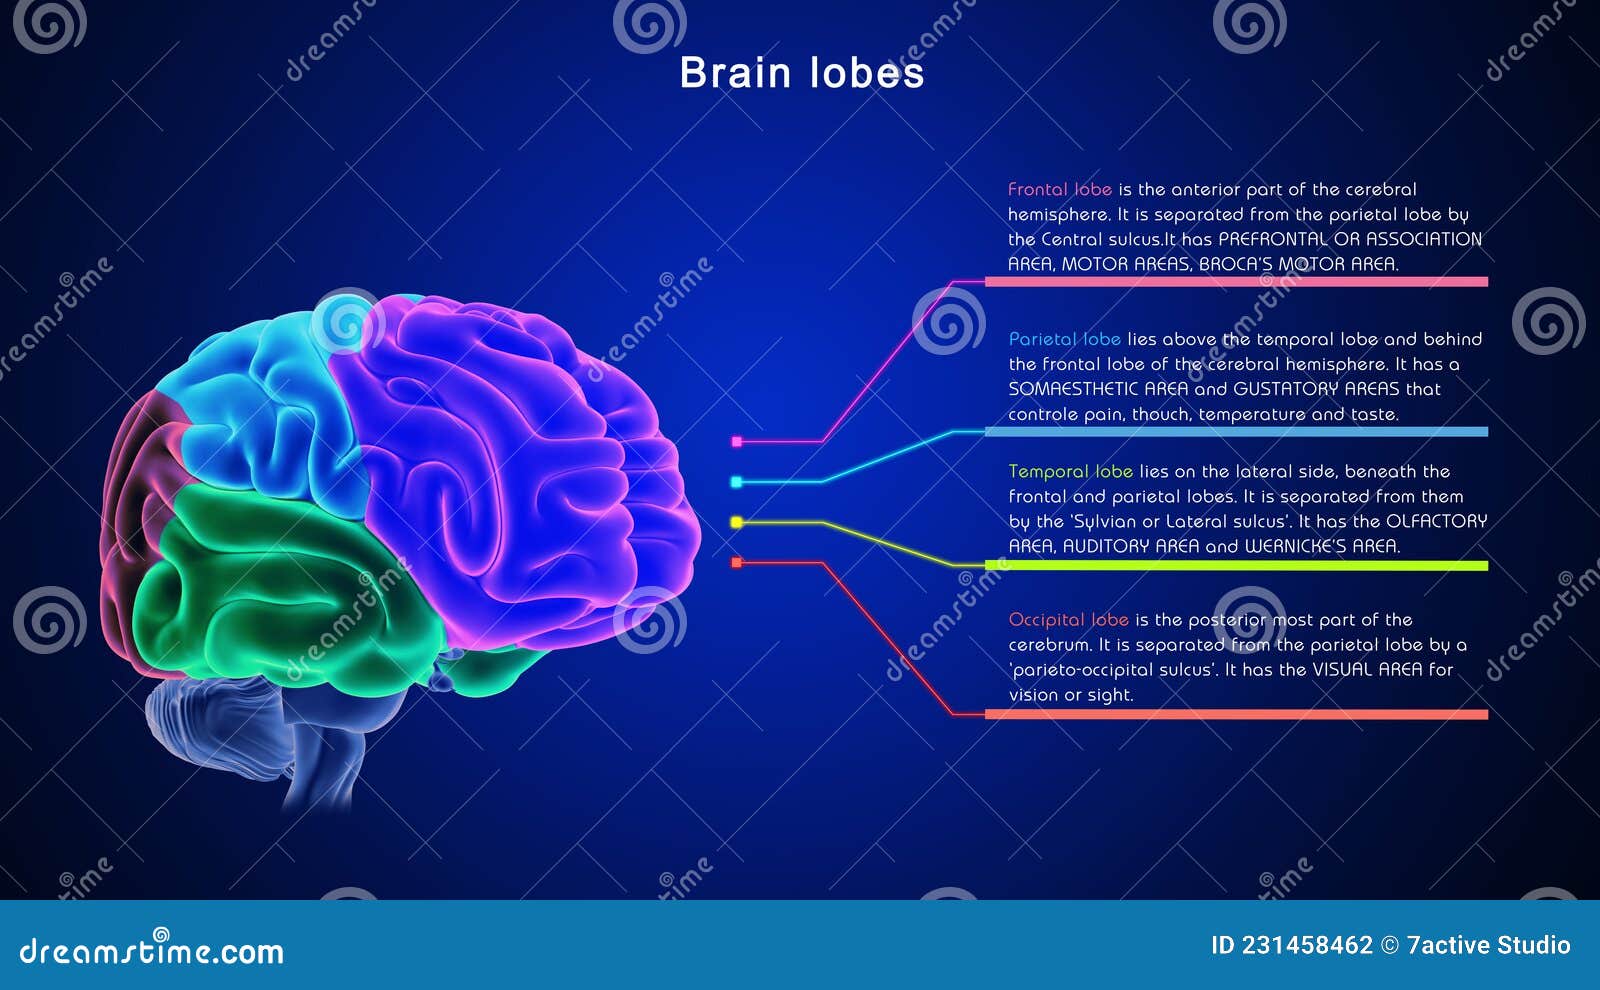
Predicting outcomes from lobe damage is imprecise. Recovery depends on lesion size, location, etiology, age, and preinjury cognitive reserve. Frontal lobe recoveries vary widely. Some patients regain independence within months. Others remain dependent on caregivers for executive support. Parietal lobe rehabilitation benefits from constraint-induced movement therapy for hemiparesis and neglect-specific interventions. Temporal lobe seizure outcomes depend on surgical candidacy. Medial temporal resections achieve seizure freedom in approximately 60-70% of carefully selected patients. Complications include memory decline and visual field defects. Occipital lobe lesions produce permanent visual deficits with limited recovery potential. Understanding the four lobes of the brain provides a framework for localizing neurological dysfunction, but clinical practice requires integrating anatomy with network neuroscience. The brain functions as interconnected systems, and damage to one region affects distributed networks. Treatment planning should consider both local deficits and network consequences. This approach improves diagnostic accuracy and rehabilitation effectiveness.