Understanding Calcitonin and Its Role in Calcium Regulation
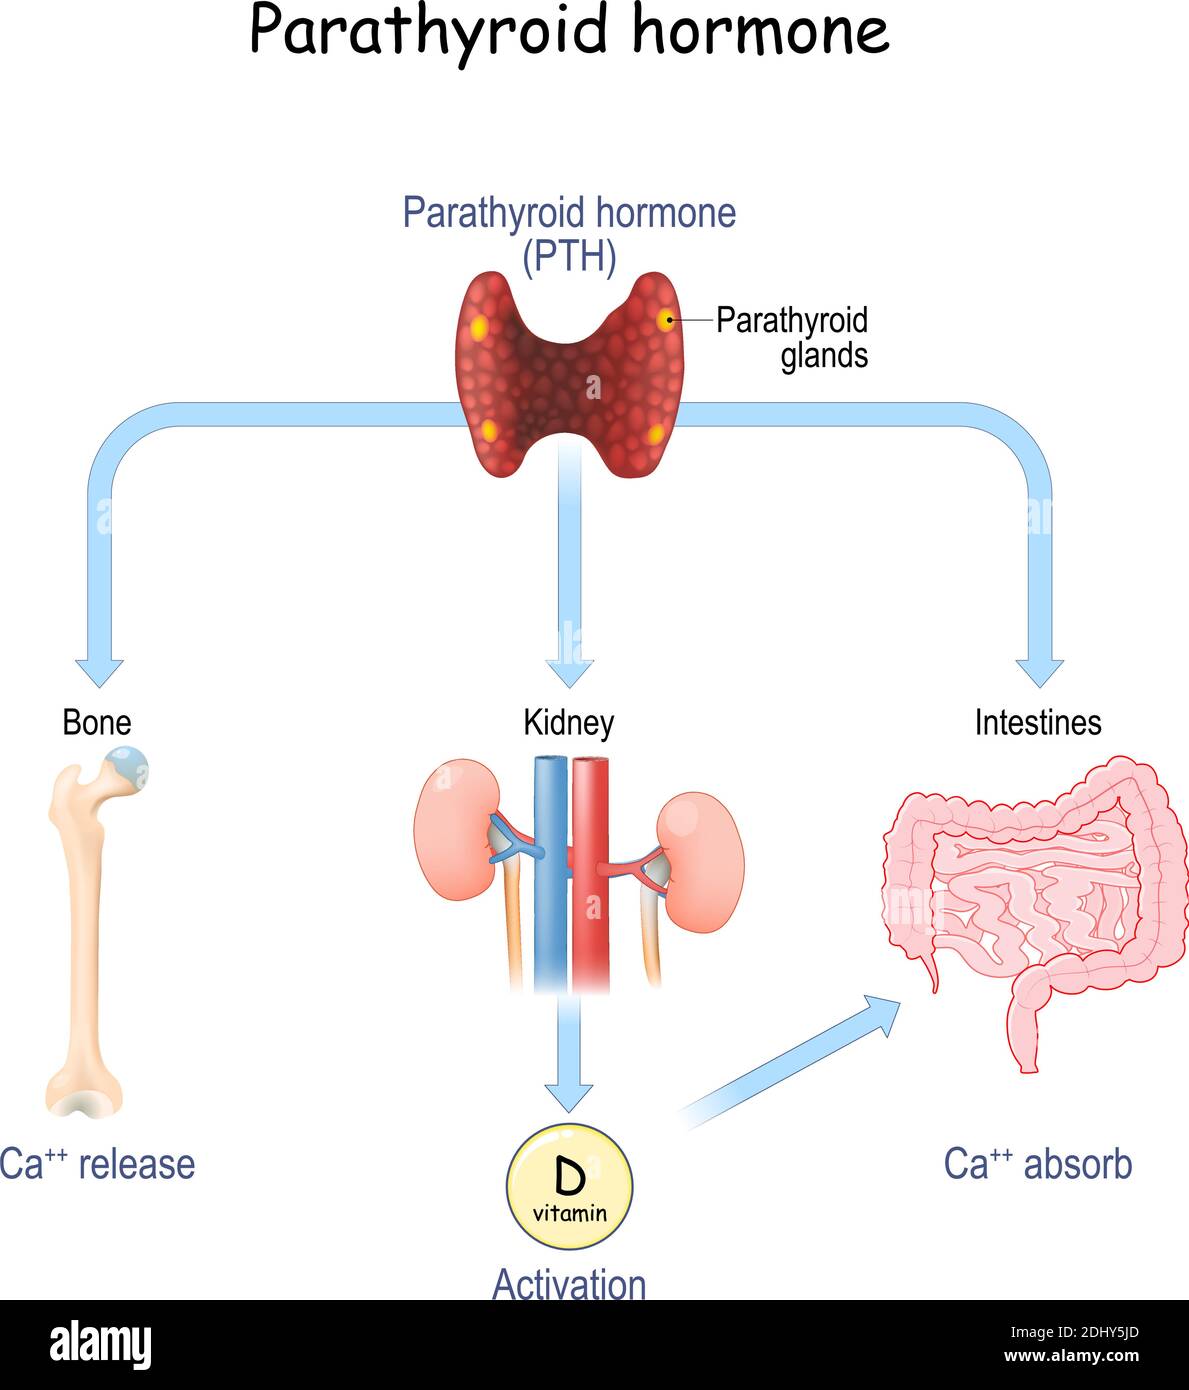
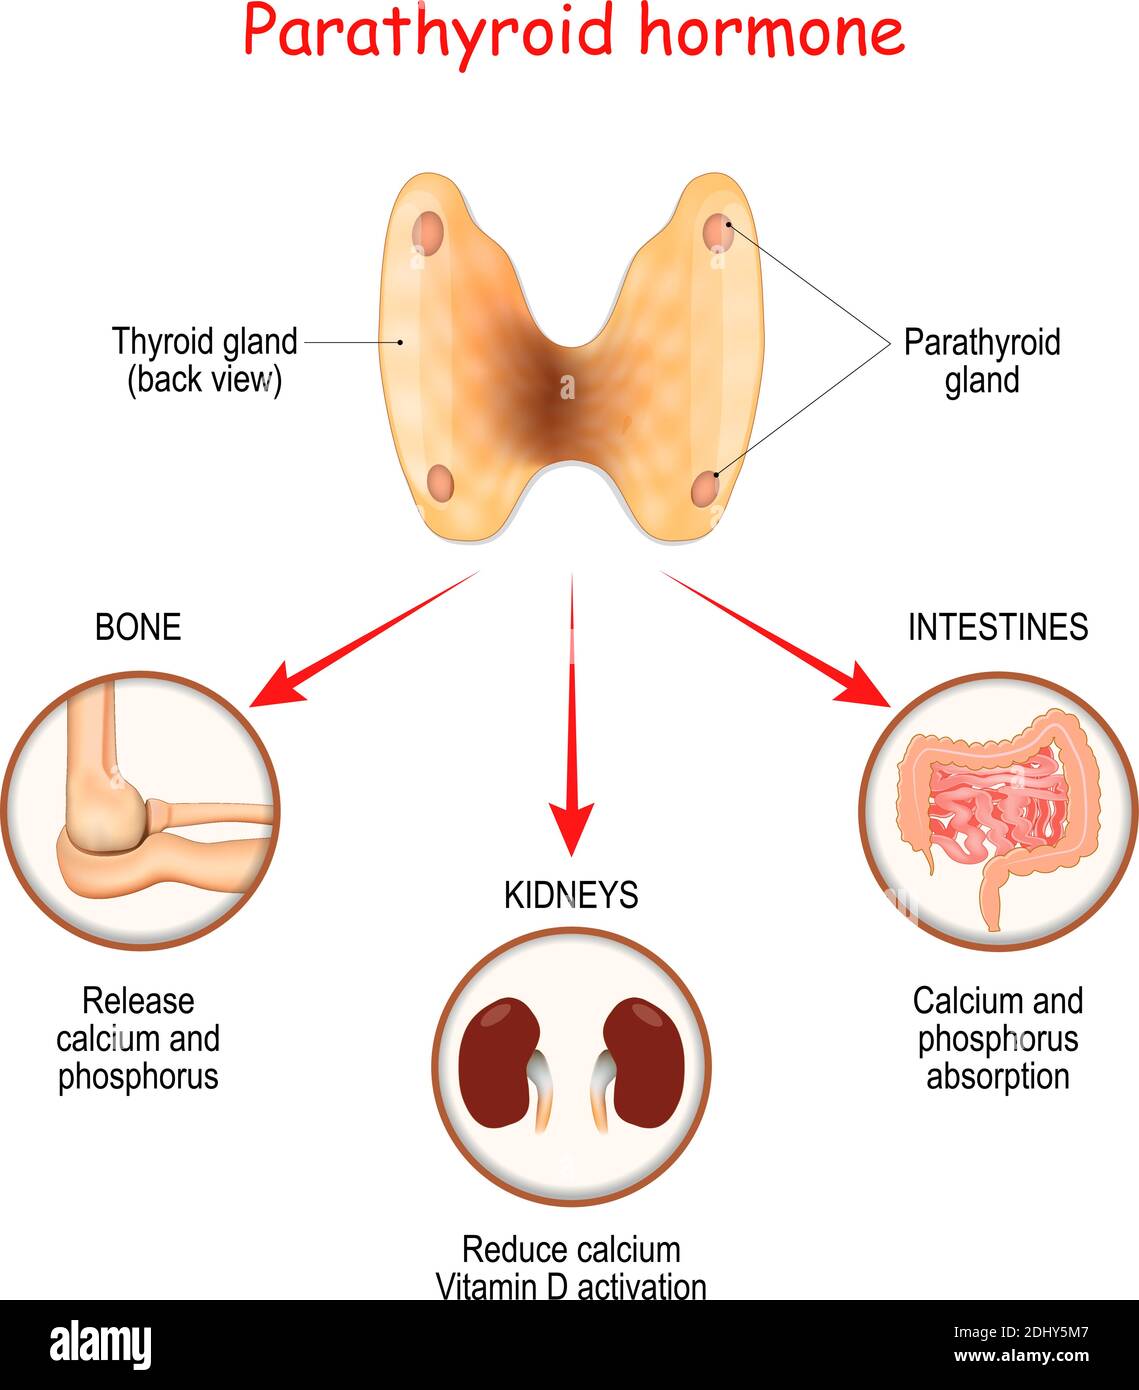
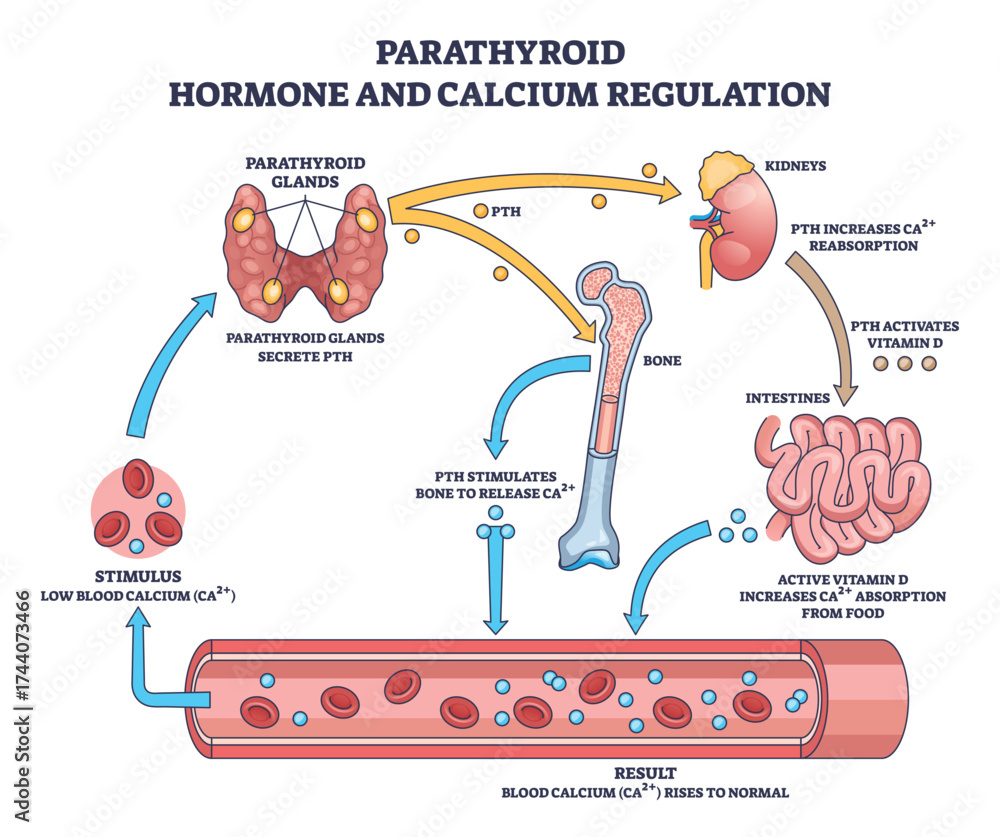
Most people studying endocrinology hit a wall when they try to understand how the body actually keeps calcium levels stable. The textbook answer is simple, but the real mechanism is messier. The antagonist to parathyroid hormone (PTH) is calcitonin, produced by the C-cells of the thyroid gland. It's not as dramatic as a yin-yang swap, though. PTH raises blood calcium by pulling it from bone, increasing kidney reabsorption, and activating vitamin D. Calcitonin does the opposite: it signals osteoblasts to deposit calcium into bone matrix and increases renal excretion of calcium. That's the basic equation. Here's what most resources skip. Calcitonin's effect in adult humans is surprisingly weak. I spent years watching patients with severe hypercalcemia where calcitonin was the first-line bridge treatment, and the drop in serum calcium was measurable but modest — typically 0.2 to 0.5 mg/dL within the first few hours, then the effect blunted dramatically due to receptor desensitization. This is a critical clinical reality that gets glossed over in exam prep materials. The body doesn't rely on calcitonin as a primary calcium buffer the way it relies on PTH. PTH is the real heavyweight. Calcitonin is more of an emergency brake than a cruise control. The counterintuitive part is that calcitonin's physiological significance in adults is genuinely debated. Some researchers argue it's essentially vestigial in human calcium homeostasis. Others point out that it's far more important during periods of rapid bone turnover — pregnancy, lactation, childhood growth spurts. I once managed a patient with a calcitonin-secreting medullary thyroid carcinoma who had serum calcitonin levels in the tens of thousands. Even at those astronomical concentrations, her calcium never dropped below normal. That told me everything I needed to know about the margin between calcitonin's action and clinical relevance in the average adult.
How Calcitonin Actually Works at the Cellular Level
Calcitonin binds to G-protein coupled receptors on osteoblasts, which then signal osteoclasts to reduce their resorptive activity. The secondary messenger is cAMP, same pathway as PTH, but the downstream effect is suppression rather than stimulation. Osteoclasts literally shrink and reduce their ruffled border — the specialized membrane structure they use to dissolve bone mineral. This isn't instant. You're looking at a timeline of hours to days for meaningful skeletal effects, which is why calcitonin's clinical utility is limited to short-term stabilization. Kidney effects are simpler. Calcitonin inhibits proximal tubule reabsorption of calcium, phosphate, sodium, and bicarbonate. It's a mild natriuretic and phosphaturic hormone. In practice, the calciuric effect is modest compared to the hormonal drivers that regulate distal tubule calcium handling. Things like volume status, aldosterone, and of course PTH dominate that conversation.
Clinical Applications and Limitations
Synthetic calcitonin (salmon calcitonin is more potent than human calcitonin by a factor of about 40) is used for a handful of indications. Paget's disease of bone was the big one historically — it reduces bone turnover and can lower alkaline phosphatase levels within weeks. I used it frequently in the 2010s before bisphosphonates became the default first-line therapy. The patient who reminded me of calcitonin's limitations was a 68-year-old woman with severe hypercalcemia of malignancy. We started her on IV calcitonin expecting a rapid correction. Her calcium dropped from 14.2 to 12.8 in six hours, then plateaued. We had to add bisphosphonate therapy and hydration to make real headway. The calcitonin bought us time but didn't solve the problem. That's the pattern you'll see repeatedly. Other uses include osteoporosis treatment, though its place has been largely superseded by antiresorptives with stronger evidence bases. Nasal calcitonin for postmenopausal osteoporosis was approved in the US until 2013 when the manufacturer voluntarily withdrew it due to low market demand — not safety concerns, but the realization that the clinical benefit was marginal compared to far cheaper alternatives. That's a practical lesson in itself: knowing what a treatment does is different from knowing whether it matters enough to use it.
Get the Full Details
Testing and Interpretation
Measuring calcitonin is clinically important, but not for calcium regulation monitoring. It's a tumor marker for medullary thyroid carcinoma. Post-thyroidectomy surveillance uses calcitonin levels to detect residual or recurrent disease. A level that doesn't drop to undetectable after surgical removal of a calcitonin-producing tumor is a red flag. I had a case where a patient's post-op calcitonin was "normal" by lab reference range but actually three times her expected post-surgical baseline. We tracked it over months and confirmed recurrence before any imaging could localize it. That's the value of understanding what you're measuring rather than just checking a box. For calcium disorders, calcitonin levels are rarely the diagnostic pivot point. PTH is. If a patient has hypercalcemia with elevated or inappropriately normal PTH, you're dealing with primary hyperparathyroidism until proven otherwise. Calcitonin would be relevant only if you suspected medullary thyroid cancer or familial medullary thyroid carcinoma (MEN2 syndrome). Adding calcitonin testing to every hypercalcemia workup is unnecessary and reflects a misunderstanding of the endocrine hierarchy.
The Bigger Picture on Calcium Homeostasis
People want clean antagonistic pairs in endocrinology. Insulin and glucagon. PTH and calcitonin. But biology rarely works with clean pairs. Calcitonin is PTH's rough counterpart, but the relationship is asymmetric. PTH has multiple potent effectors across bone, kidney, and gut. Calcitonin has one primary target — bone — and even there its signal is weak in adults. The body can maintain calcium balance adequately without calcitonin. People who undergo total thyroidectomy don't develop hypocalcemia because calcitonin deficiency isn't a problem. They develop hypocalcemia only if the parathyroid glands are damaged or removed during surgery. This asymmetry matters for how you approach the topic clinically and academically. Don't overattribute to calcitonin what belongs to PTH, vitamin D, fibroblast growth factor 23, or the kidneys' direct regulatory capacity. The hormone is real, it has defined mechanisms, and it has limited applications. Knowing the boundaries of its relevance is what separates a memorized fact from actual understanding.