Understanding the Oropharynx: What It Is and Why It Matters
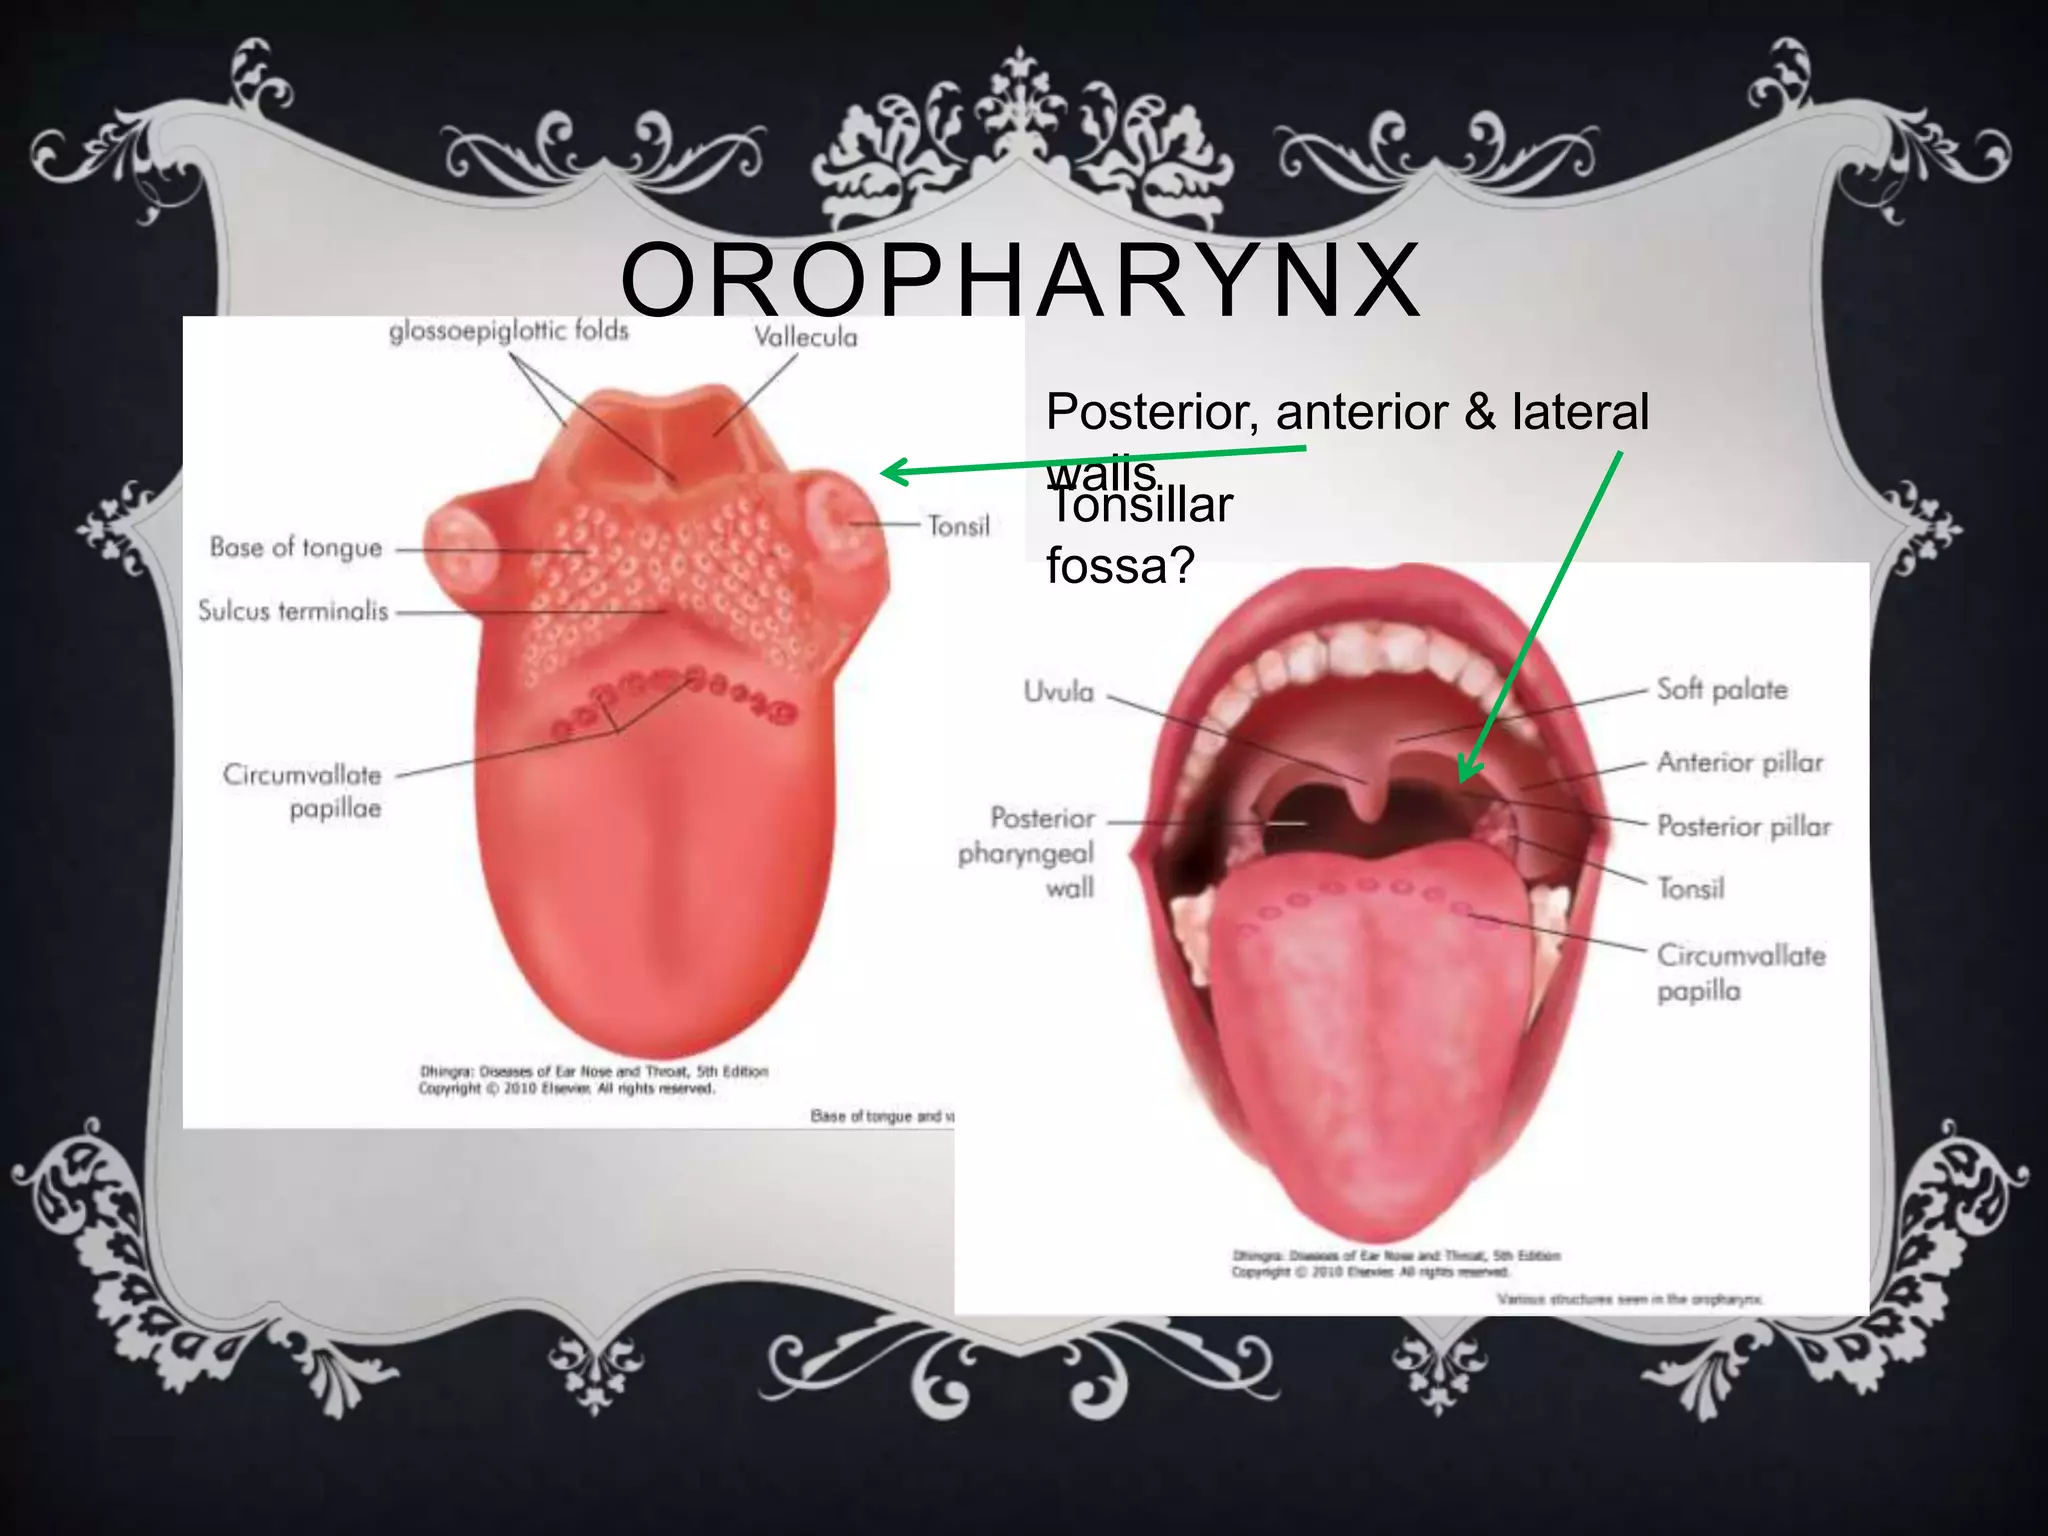
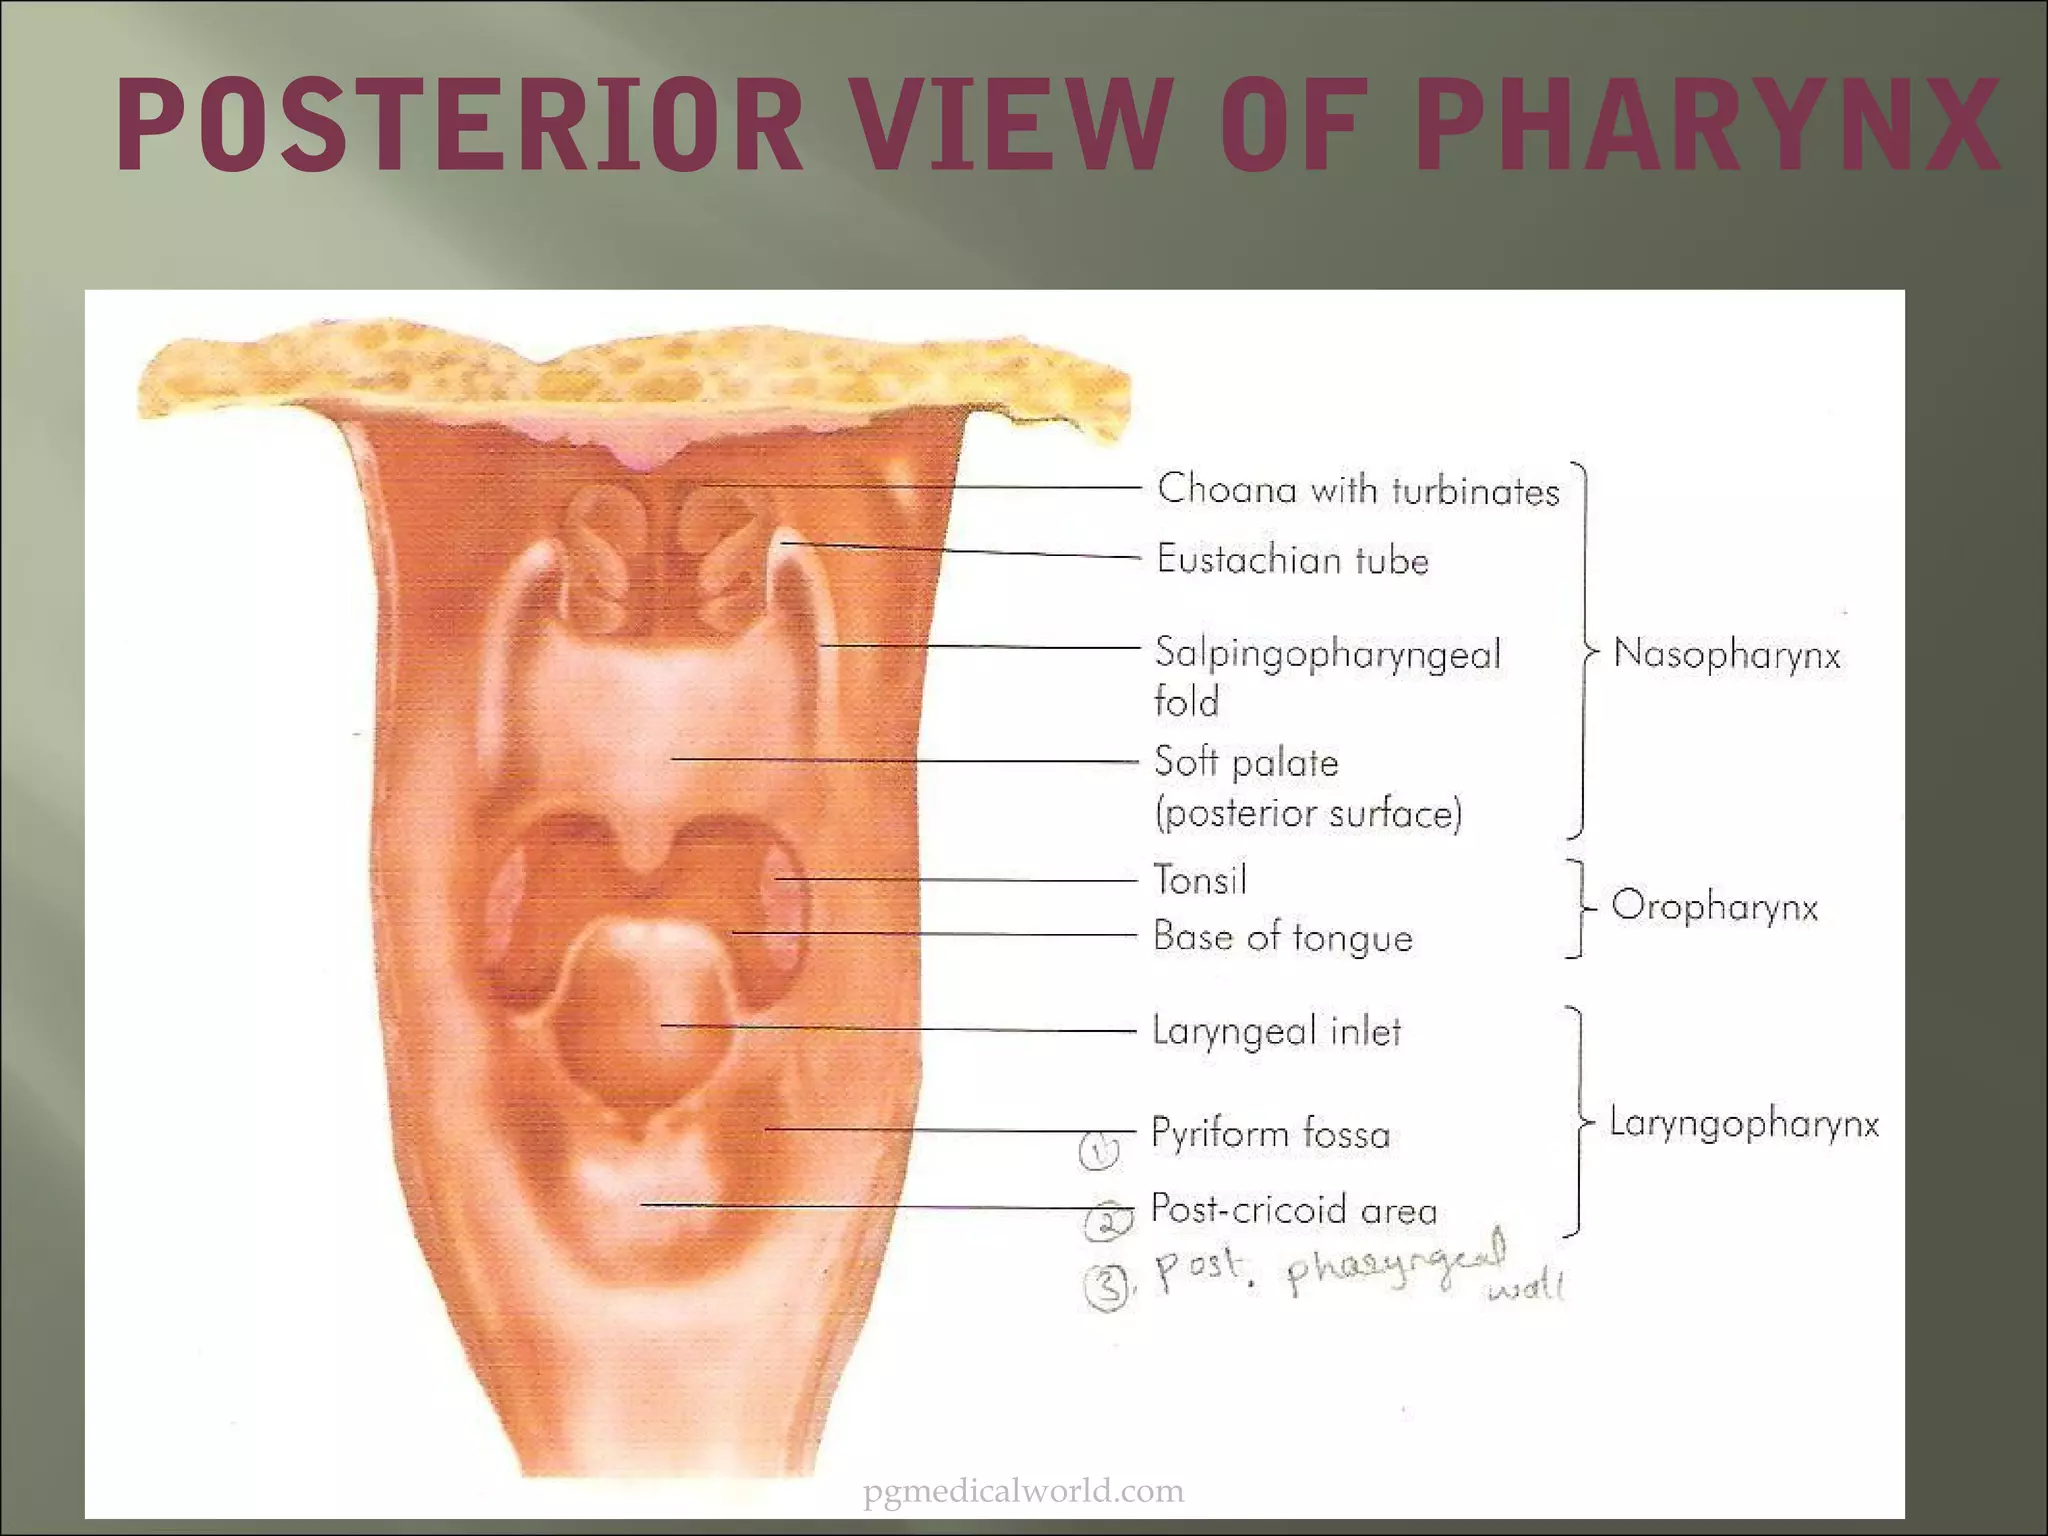
The area of the pharynx directly posterior to the mouth is the oropharynx. It sits right behind the oral cavity, bounded superiorly by the soft palate and inferiorly by the epiglottis at the level of the hyoid bone and C2 vertebra. When you look in a mirror and pull your tongue forward, the structure you're seeing at the back is the anterior surface of this region — the fauces, the tonsillar pillars, the base of the tongue, and the posterior pharyngeal wall beyond that. This is not a theoretical anatomy question. It's something you actually encounter when you're dealing with airway management, swallowing disorders, or upper respiratory infections. I remember a case a few years back where a patient came in with what appeared to be a routine sore throat. The symptoms pointed toward viral pharyngitis, but the exudate pattern was atypical — more posteriorly distributed than usual, with some asymmetry near the tonsillar fossa. A standard visual exam wasn't giving me enough information, so I proceeded with a quick lateral neck X-ray and then a flexible nasopharyngolaryngoscopy. What we found was a peritonsillar abscess that had tracked posteriorly into the parapharyngeal space, which is right adjacent to the oropharyngeal wall. If I'd stopped at the visual exam, that would have been a serious miss. The abscess wasn't going to resolve on its own, and the infection was creeping toward the deeper cervical spaces. We got an ENT consult, drained it, and the patient was stable within a day. The takeaway here is that the oropharynx isn't just a passageway. It's a compact anatomical zone where infections can hide in the surrounding fascial planes and present deceptively. The posterior wall itself is lined with non-keratinized stratified squamous epithelium, and it's richly supplied by branches of the glossopharyngeal nerve (CN IX) and the vagus nerve (CN X). That's why referred pain from oropharyngeal issues can show up in the ear — the same nerve roots are involved.
When you're examining this area clinically, the standard approach is a three-part inspection: the anterior pillar region and tonsils, the base of tongue, and the posterior pharyngeal wall. You need a good light source, a tongue depressor, and patience. The gag reflex will interfere if you're not careful. I use a topical anesthetic spray like lidocaine 4% when I know the patient has a sensitive reflex, and it makes the entire examination significantly more reliable. Without it, you're mostly looking at the upper portion and guessing about the rest. One counter-intuitive point that most people miss: the oropharynx is functionally both a respiratory and a digestive passage, and that dual role creates a coordination problem during swallowing. The soft palate elevates to close off the nasopharynx, the tongue base retracts to push the bolus backward, and the larynx elevates to protect the airway. All of this happens in roughly 0.5 seconds. When any part of that sequence is disrupted — stroke, neurodegenerative disease, post-surgical changes — you get dysphagia, and the oropharynx is where the breakdown typically shows up first on a videofluoroscopic swallow study. Another thing beginners overlook is the lymphatic drainage. The oropharynx drains primarily to the jugulodigastric node, which sits just below the angle of the mandible. That's the node you palpate when you're assessing for infection or malignancy in this region. If it's enlarged and firm, you're not dealing with a simple viral pharyngitis. You need to consider streptococcal infection, abscess formation, or underlying neoplasm — particularly squamous cell carcinoma, which is increasingly linked to HPV in the tonsillar and base-of-tongue regions.
The blood supply comes mainly from the tonsillar branch of the facial artery and the ascending pharyngeal artery. During surgery in this area, like a tonsillectomy, the danger zone is around the stylomandibular ligament and the internal carotid artery, which lies approximately 2 to 2.5 cm lateral to the tonsillar fossa. That's close enough that a deep post-tonsillectomy hemorrhage can be catastrophic if not managed immediately. I've seen it happen. It's rare, but when it does, the time between recognition and intervention is measured in minutes. For imaging, CT with contrast is the workhorse for evaluating deep space infections or tumors in the oropharynx. MRI is better for soft tissue delineation, especially when you're staging a malignancy. Plain radiographs have limited utility but can show prevertebral soft tissue swelling or air-fluid levels in an abscess. Ultrasound is rarely used here because of the depth and the overlying structures, though it can help guide drainage of superficial collections. There's no single definitive test for every condition affecting the oropharynx. The diagnosis usually comes from putting together the visual exam findings, the patient's symptoms, and targeted imaging or labs. If you're dealing with persistent unilateral pain, a neck mass, or changes in voice that last more than two weeks, you don't wait. You refer for an endoscopic evaluation. The oropharynx is small, but the structures around it matter a lot.
Get the Full Details